Language Disorders
Medical and Psychosocial
Aspects of Disability
By: Hina Khalid
Communication
 There are 3 elements in this exchange,
and all must be present:
1. Message
2. Message must be expressed
3. Message must be understood
Speech and Language
 Speech is the motor act of
communicating by articulating verbal
expression
 Language is the knowledge of a
symbol system used for interpersonal
communication.
Four domains of language
Phonology
Grammar
Semantics
Pragmatics
Phonology
 The ability to produce and
discriminate the specific sounds of a
given language.
 Its unit, the phoneme, is characterized
by distinctive features.
 Babies start discriminating phonemes
during the first few months of life, and
they produce them soon after.
Phonology
 Phonological receptivity is pluripotential
at birth
 Starts to decay at around 10 months
 Reaches a rather general inability to
acquire native phonology by
preadolescence
Grammar
 The underlying rules that organize
any specific language.
 The combinatorial rules that most native
speakers of a language recognize as
acceptable for that language and that
allow a native speaker an infinite array
of generative possibilities.
Grammar
 Composed of both morphology and
syntax.
Semantics
 The study of meaning
 Includes the study of vocabulary
(lexicon).
Lexicon
 Lexical entries are organized in the
mental dictionary according to well-
defined rules
 Allows the young child to acquire a
peak average of 10 new words per day.
 By 24 months the average child knows
50 words.
Lexicon Growth
 The subsequent
exponential growth
makes it difficult to
determine
vocabulary size with
exactitude.
Environmental factors
predicting large vocabularies
 Reading and discussing children's stories
 The quality of dinner table conversations
 Large mother-produced number of words
 Higher socioeconomic status (SES)
 Being the firstborn ( Hoff-Ginsberg, 1998 )
 Quantity and sophistication of mother's
vocabulary ( Snow, 1998 ).
Pragmatics
 A number of sub-domains reflecting
communicative competence.
Sub domains of Pragmatics
 Rules of conversation (turn-taking, topic
maintenance, conversational repair)
 Politeness
 Narrative and extended discourse
 The implementation of communicative
intents
Pragmatic disorders
 Little variety in language use
 May say inappropriate or unrelated
things during conversations
 May tell stories in a disorganized way
 Can often make demands, ask
questions, and greet people
 Has trouble organizing language to talk
about what happened in the past.
Pragmatic disorders
 Appear to pull topics out of the air
 May not use statements that signal a
change in topic, such as "That reminds
me."
 Peers may avoid having conversations
with such a child.
 Can lower social acceptance.
Language Developmental
Trajectory
Canonical Babbling
Word comprehension
Word production
Word combinations
Telegraphic speech
Continue…..
 By age 3, most
normal children
have mastered the
basic structures of
their native
language
Language acquisition
 Occurs with uniformity and rapidity
 Supports the hypothesized existence of
innate, genetically determined Universal
Grammars
 Recently proposed a combination of
traditional learning and innate language
modules.
Disfluencies in Children
 Almost all children go through a stage
of frequent disfluency
 usually between the ages of 2 and 5.
 Speech is produced easily in spite of
the disfluencies.
Etiology of Speech & Language
Disorders
 Mental retardation
 Hearing loss
 Maturation delay
(developmental
language delay)
 Expressive
language disorder
(developmental
expressive aphasia)
 Bilingualism
 Psychosocial
deprivation
 Autism
 Elective mutism
 Receptive aphasia
 Cerebral palsy
Overview of major types of
speech disordersspeech disorders
 Definitions vary, but
generally agree that
speech disorders involve
deviations of sufficient
magnitude to interfere
with communication.
 They draw attention to
the speaking act and
away from the message
1. Fluency Disorders
 Speech is characterized by repeated
interruptions, hesitations, or repetitions
 Stuttering is by far the most well-
known fluency disorder
1. Stuttering
 Flow of speech is abnormally
interrupted by repetitions, blocking, or
prolongations of sounds, syllables,
words, or phrases
 Very familiar, but actually quite rare –
only 1-5% of the population.
 Articulation disorders actually occur
much more frequently than stuttering
Stuttering -- Causes
 Still a mystery
 Three perspectives:
1. Symptom of emotional
disturbance
2. Result of biological
makeup
3. Learned response
Stuttering
 Disorder of speech fluency that
interrupts the forward flow of speech.
 All individuals are disfluent at times
 Differentiated by the kind and amount of
the disfluencies
Characteristics-Repetition
 Sounds
 b-b-b-ball
 Syllables
 mo-mo-mommy
 Parts of words
 basket-basket-basketball
 Whole words, and phrases
Characteristics-Prolongation
 Stretching, of sounds or syllables
 r-----abbit
Characteristics
 Tense pauses, hesitations, and/or no
sound between words
 Speech that occurs in spurts
 as the child tries to initiate or maintain
voice
 Variability in stuttering behavior
 depending on the speaking situation
Related behaviors
 tense muscles in the lips, jaw, and/or
neck
 tremor of the lips, jaw, and/or tongue
 foot tapping
 eye blinks
 head turns
2. Articulation disorders
 This is the largest category of all
speech problems
 DSM-IV calls these “phonological
disorders.”
 “abnormal speech-sound production,
characterized by inaccurate or
otherwise inappropriate execution of
speaking”
2. Articulation disorders
 Great majority are functional articulation
disorders
 Might represent as much as 80% of the
speech disorders diagnosed by speech
clinicians
 Must be very careful to distinguish true
problems from delay.
 E.g., r, s, th problems may largely disappear
naturally after 5 years of age
2. Articulation disorders
1. Omissions
2. Substitutions
3. Additions
4. Distortions
3. Voice disorders
 Unusual or abnormal acoustical
qualities in the sounds made when a
person speaks
 Very little research here
 What is a “normal” sounding voice?
 Nasality, hoarseness, breathiness
Normal Speech Development
4. Delayed speech
 Failure to develop speech at the
expected age
 Somewhat subjective
 Usually associated with other
maturational delays
 May also be associated with a hearing
impairment, mental retardation,
emotional disturbance, or brain injury
 Often the result of environmental
deprivation
Epidemiology of Speech Delay
 Common childhood problem
 Affects 3 to 10 percent of children.
 3-4X more common in boys than in
girls.
Most common causes of speech
delay
Mental retardation
Hearing loss
Maturation delay
Overview of major types of
language disorderslanguage disorders
 Need to understand normal language
and prelanguage development
 See Table 10.1 on 320
 May involve comprehension
(understanding) or expression in
written or spoken language
 These are very complex to diagnose
and treat
Language and Brain
Language disordersLanguage disorders
1. Expressive language disorders
2. Receptive language disorders
3. Aphasia – loss of the ability to speak
or comprehend language because of
an injury or developmental
abnormality in the brain
EXPRESSIVE LANGUAGE
DISORDER
(developmental expressive aphasia)
 Fail to develop the use of speech at the
usual age.
EXPRESSIVE LANGUAGE DISORDER
 Normal intelligence
 Normal hearing
 Good emotional relationships
 Normal articulation skills.
 Comprehension of speech is
appropriate to the age of the child
EXPRESSIVE LANGUAGE DISORDER
 Brain dysfunction
that results in an
inability to
translate ideas
into speech.
EXPRESSIVE LANGUAGE DISORDER
 The child is at risk for language-based
learning disabilities (dyslexia).
 May use gestures to supplement their
limited verbal expression .
Maturation Delay vs. Expressive
Language Disorder?
 The late bloomer will
eventually develop
normal speech
 The child with an
expressive language
disorder will not do
so without
intervention.
Maturation Delay vs. Expressive
Language Disorder?
It is sometimes difficult, if not
impossible, to distinguish at
an early age a late bloomer
from a child with an
expressive language disorder.
BILINGUALISM
 A bilingual home
environment may
cause an apparent
temporary delay in
the onset of both
languages.
BILINGUALISM
 The bilingual child's comprehension of
the two languages is normal for a child
of the same age.
 Usually becomes proficient in both
languages before the age of five years.
Interference or transfer
 An English error due to the direct
influence of the primary language
structure.
 This is a normal phenomenon
Silent period
 Common second-language acquisition
phenomenon
 Often very quiet, speaking little
 Focus on understanding the new
language
 The younger the child, the longer the
silent period tends to last.
Code switching
 Changing languages over phrases or
sentences.
 Normal phenomenon
Benefits of Bilingualism
 Children who are fluent bilinguals
actually outperform monolingual
speakers on tests of metalinguistic skill.
Benefits of Bilingualism
 Our world is shrinking and business
becomes increasingly international
 Children who are fluent bilingual
speakers are potentially a tremendously
valuable resource for the U.S.
economy.
Language Disorders
 Egyptians reported
speech loss after
blow to head 3000
years ago
 Broca (1861) finds
damage to left inferior
frontal region (Broca’s
area) of a language
impaired patient, in
postmortem analysis
Language Disorders
 In language disorders
 90-95% of cases, damage is to the left
hemisphere
 5-10% of cases, to the right hemisphere
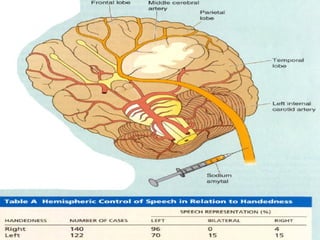
 Wada test is used to determine the
hemispheric dominance
 Sodium amydal is injected to the carotid artery
 First to the left and then to the right
Language Disorders
 Paraphasia:
 Substitution of a word by a sound, an incorrect
word, or an unintended word
 Neologism:
 Paraphasia with a completely novel word
 Nonfluent speech:
 Talking with considerable effort
 Agraphia:
 Impairment in writing
 Alexia:
 Disturbances in reading
Three major types of Aphasia
Rosenzweig: Table 19.1, p. 615
 Borca’s aphasia
 Nonfluent speech
 Wernicke’s aphasia
 Fluent speech but unintelligible
 Global aphasia
 Total loss of language
Others: Conduction, Subcortical, Transcortical
Motor/Sensory (see also Kandel, Table 59-1)
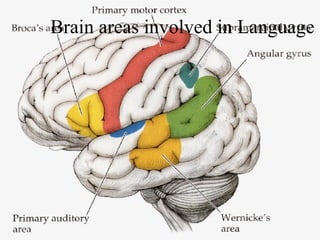
Brain areas involved in Language
Broca’s Aphasia
Brodmann 44, 45
 Lesions in the left inferior frontal region
(Broca’s area)
 Nonfluent, labored, and hesitant speech
 Most also lost the ability to name persons or
subjects (anomia)
 Can utter automatic speech (“hello”)
 Comprehension relatively intact
 Most also have partial paralysis of one side of
the body (hemiplegia)
 If extensive, not much recovery over time
Wernicke’s
Aphasia
Brodmann 22, 30
 Lesions in posterior of the left superior
temporal gyrus, extending to adjacent parietal
cortex
 Fluent speech
 But contains many paraphasias
 “girl”-“curl”, “bread”-“cake”
 Syntactical but empty sentences
 Cannot repeat words or sentences
 Unable to understand what they read or hear
 Usually no partial paralysis
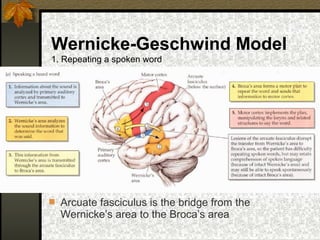
Wernicke-Geschwind Model
1. Repeating a spoken word
 Arcuate fasciculus is the bridge from the
Wernicke’s area to the Broca’s area
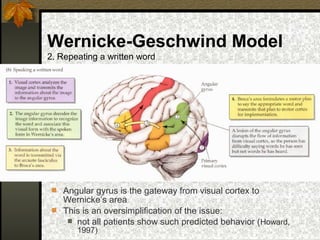
Wernicke-Geschwind Model
2. Repeating a written word
 Angular gyrus is the gateway from visual cortex to
Wernicke’s area
 This is an oversimplification of the issue:
 not all patients show such predicted behavior (Howard,
1997)
Sign Languages
 Full-fledged languages, created by hearing-
impaired people (not by Linguists):
 Dialects, jokes, poems, etc.
 Do not resemble the spoken language of the same
area (ASL resembles Bantu and Navaho)
 Pinker: Nicaraguan Sign Language
 Another evidence of the origins of language (gestures)
 Most gestures in ASL are with right-hand, or
else both hands (left hemisphere dominance)
 Signers with brain damage to similar regions
show aphasia as well
Signer Aphasia
 Young man, both spoken and sign language:
 Accident and damage to brain
 Both spoken and sign languages are affected
 Deaf-mute person, sign language:
 Stroke and damage to left-side of the brain
 Impairment in sign language
 3 deaf signers:
 Different damages to the brain with different
impairments to grammar and word production
Spoken and Sign Languages
 Neural mechanisms are similar
 fMRI studies show similar activations for
both hearing and deaf
 But in signers, homologous activation
on the right hemisphere is unanswered
yet
Dyslexia
 Problem in learning to read
 Common in boys and left-handed
 High IQ, so related with language only
 Postmortem observation revealed anomalies
in the arrangement of cortical cells
 Micropolygyria: excessive cortical folding
 Ectopias: nests of extra cells in unusual location
 Might have occurred in mid-gestation, during
cell migration period
Acquired Dyslexia = Alexia
 Disorder in adulthood as a result of
disease or injury
 Deep dyslexia (pays attn. to wholes):
 “cow” -> “horse”, cannot read abstract
words
 Fails to see small differences (do not read
each letter)
 Problems with nonsense words
 Surface dyslexia (pays attn. to details):
 Nonsense words are fine
 Suggests 2 different systems:
 One focused on the meanings of whole
words
Electrical Stimulation
 Penfield and Roberts (1959): During epilepsy
surgery under local anesthesia to locate
cortical language areas, stimulation of:
 Large anterior zone:
 stops speech
 Both anterior and posterior temporoparietal cortex:
 misnaming, impaired imitation of words
 Broca’s area:
 unable comprehend auditory and visual semantic
material,
 inability to follow oral commands, point to objects, and
understand written questions
Studies by Ojemann et al.
 Stimulation of the brain of an English-Spanish
bilingual shows different areas for each
language
 Stim of inferior premotor frontal cortex:
 Arrests speech, impairs all facial movements
 Stim of areas in inferior, frontal, temporal,
parietal cortex:
 Impairs sequential facial movements, phoneme
identification
 Stim of other areas:
 lead to memory errors and reading errors
 Stim of thalamus during verbal input:
 increased accuracy of subsequent recall
Williams Syndrome
 Caused by the deletion of a dozen genes from
one of the two chromosomes numbered 7
 Shows dissociation between language and
intelligence, patients are:
 Fluent in language
 But cannot tie their shoe laces, draw images, etc.
 Developmental process is altered:
 Number skills good at infancy, poor at adulthood
 Language skills poor at infancy, greatly improved in
adulthood
Lateralization of the Brain
 Human body is asymmetrical: heart,
liver, use of limbs, etc.
 Functions of the brain become
lateralized
 Each hemisphere specialized for
particular ways of working
 Split-brain patients are good examples
of lateralization of language functions
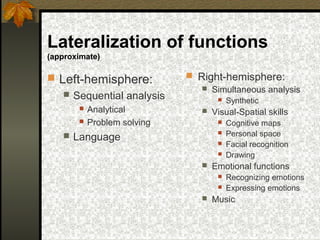
Lateralization of functions
(approximate)
 Left-hemisphere:
 Sequential analysis
 Analytical
 Problem solving
 Language
 Right-hemisphere:
 Simultaneous analysis
 Synthetic
 Visual-Spatial skills
 Cognitive maps
 Personal space
 Facial recognition
 Drawing
 Emotional functions
 Recognizing emotions
 Expressing emotions
 Music
Split-brain
 Epileptic activity spread from one hemisphere
to the other thru corpus callosum
 Since 1930, such epileptic treated by
severing the interhemispheric pathways
 At first no detectible changes (e.g. IQ)
 Animal research revealed deficits:
 Cat with both corpus callosum and optic chiasm
severed
 Left-hemisphere could be trained for
symbol:reward
 Right-hemisphere could be trained for inverted
symbol:reward
Left vs. Right Brain
 Pre and post operation studies showed that:
 Selective stimulation of the right and left hemisphere
was possible by stimulating different parts of the body
(e.g. right/left hand):
 Thus can test the capabilities of each hemisphere
 Left hemisphere could read and verbally communicate
 Right hemisphere had small linguistic capacity:
recognize single words
 Vocabulary and grammar capabilities of right is far less
than left
 Only the processes taking place in the left hemisphere
could be described verbally