













































Preanalytical Errors
in Medical Laboratory
Meeqat General Hospital, 25 October 2016
By
Prof. Asmaa El Reweny, MD
Professor & Consultant of Clinical & Chemical
Pathology, Faculty of Medicine, Cairo University &
AMS, Taibah University (2006-2016)
Objectives
At the end of this lecture you will be able to:
1- Identify what is meant by preanalytical
period.
2- Recognize magnitude of preanalytical
errors in relation to total analytical errors.
3- Identify steps of preanalytical process & its
potential errors.
4- Recognize how to avoid these errors
5- Identify markers for sample rejection
2Prof Asmaa El Reweny, MD
Introduction
 Three phases of laboratory testing:
 Pre-analytical:
Specimen collection, transport & processing
 Analytical:
Testing
 Post-analytical:
Results transmission, interpretation, follow-
up, retesting.
3Prof Asmaa El Reweny, MD
Why Preanalytics?
 Preanalytical variables can dramatically
affect the results of laboratory tests.
 Paying close attention to control the
preanalytical variables will help to ensure
accurate test results in clinical laboratory.
Implications of Errors
 Compromise
diagnosis &
treatment of
the patient
• May influence
the quality of
final results ...
• Errors made
in the period
prior to the
analysis ...
No result is better than bad result.
Accurate result is the best of all. 5Prof Asmaa El Reweny, MD
Steps of preanalytical phase
Preparation prior to
sampling
Sampling/handling
Transport/Storage
Preparation
prior to analysis
6Prof Asmaa El Reweny, MD
“The weak link”
The preanalytical phase
is the weak link in the
Patient Focus Circle.
The more steps
involved in a process,
the more likely there
will be errors.
Magnitude of Preanalytical Errors
In Relation To Total Analytical Errors
 93% (2014)
 32 - 75% *
*Stankovic 2008
“Quality Improvements in the Preanalytical Phase:
Focus on Urine Specimen Workflow”
8Prof Asmaa El Reweny, MD
9
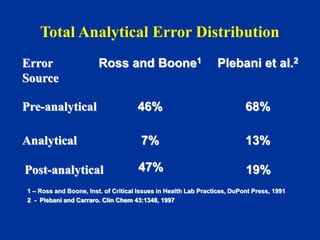
Sources of Lab Errors
Error
Source
Ross and Boone1 Plebani et al.2
Pre-analytical 46% 68%
Analytical 7% 13%
Post-analytical 47% 19%
1 – Ross and Boone, Inst. of Critical Issues in Health Lab Practices, DuPont Press, 1991
2 - Plebani and Carraro. Clin Chem 43:1348, 1997
Total Analytical Error Distribution
Pre-analytical errors
 Pre-& post-analytical errors: > 90% of errors
 These potential errors are not inevitable but
could be prevented with a diligent application of
quality control, continuing education and
effective collection systems.
11Prof Asmaa El Reweny, MD
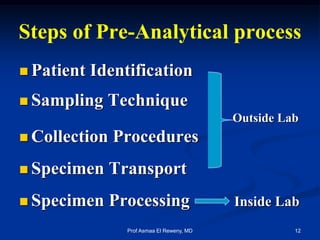
Steps of Pre-Analytical process
 Patient Identification
 Sampling Technique
Outside Lab
 Collection Procedures
 Specimen Transport
 Specimen Processing Inside Lab
12Prof Asmaa El Reweny, MD

 Attention to the preanalytical variables
associated with blood collection is
critical in ensuring accurate test
results.
 Record significant variables on request
form.
Effects of Pre-analytical Variables on
Quality of Laboratory Testing
14Prof Asmaa El Reweny, MD
Effects of Pre-analytical Variables on
the Results of Laboratory Testing
 Some patient variables that affect test results
- Age - Genetic variation/ Race
- Sex - Nutritional status
- Diet - Diagnostic & therapeutic
- Drugs procedures (PR, endoscopy)
- Exercise - Pregnancy
- Posture - Timing: Biorythm
- Special habits - Hemolysis, lipemia, Jaundic
- Diagnosis (provisional)
15Prof Asmaa El Reweny, MD
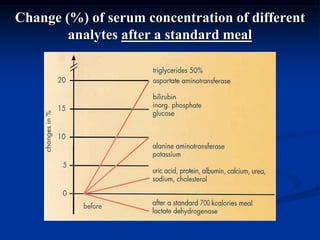
Change (%) of serum concentration of different
analytes after a standard meal
When identifying the patient, get:
 Full name
 Age & sex
 Address/Nationality
 Identification number:
Hospital No for inpatients,
Identification band should contain the above
information (confirm before venipuncture).
Patient and specimen
identification
17Prof Asmaa El Reweny, MD
 Patient Identification: It is important to
identify a patient accurately so that blood is
collected & labeled from the correct person
with his correct data.
(otherwise mislabeling ???)
18Prof Asmaa El Reweny, MD
Patient and specimen identification
 The highest frequency of errors occurs with
the use of handwritten labels & request forms.
 These can be eliminated by:
 Confirming patient’s identifiers (name, medical
record number, date of birth, room location or
address)
 Barcode technology.
 Locate Patient
 Prepare Patient
 Draw Sample
 Label
 Dispose of supplies
Sampling and Collection
20Prof Asmaa El Reweny, MD
Sample Collection
 Timing of Collection
 Therapeutic Drug Monitoring
 Peak and trough collection times
 Basal State Collections
 Fasting requirements: no food or liquid
except water (10-12h), (12-14 h for TG)
 2h postprandial, from the start of food .
 Specimens affected by time of day, for
example, cortisol, iron and TSH.
21Prof Asmaa El Reweny, MD
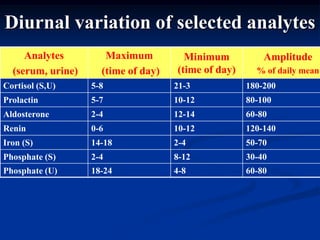
Diurnal variation of selected analytes
Analytes
(serum, urine)
Maximum
(time of day)
Minimum
(time of day)
Amplitude
% of daily mean
Cortisol (S,U) 5-8 21-3 180-200
Prolactin 5-7 10-12 80-100
Aldosterone 2-4 12-14 60-80
Renin 0-6 10-12 120-140
Iron (S) 14-18 2-4 50-70
Phosphate (S) 2-4 8-12 30-40
Phosphate (U) 18-24 4-8 60-80
Timing of Collection
 Between 7 and 9 a.m.
 Before interfering diagnostic and therapeutic
procedures
 In drug monitoring: consideration of the peak
after administration and the steady state phase
before the next dose
 Documentation of the exact time of
sampling is very important !
Phlebotomy
 Venipuncture requires expert knowledge
and critical judgment.
 Phlebotomy errors may cause harm to
patients or result in needle stick injury to
the phlebotomist.
 It could result in many preanalytical errors
in Lab results.
24Prof Asmaa El Reweny, MD
Error Prevention
 Phlebotomy Education
 Academic course and training under the supervision
of a senior phlebotomist.
 Continuous Medical Education
 Competency assessments (written and observational).
 Professional Licensure.
 Phlebotomy Staffing
 Adequate staffing to maintain collection standards.
 Technology
 Use of barcode scanners for patient identification.
25Prof Asmaa El Reweny, MD
Phlebotomy Technique
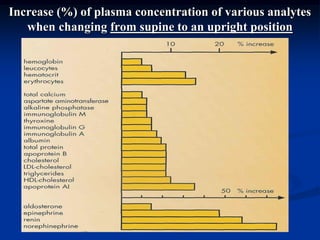
1. Posture:
- Comfortably seated patient or supine for 20 min
before sampling (not standing).
- The arm should be extended in a straight line
from the shoulder to the wrist.
2. Collection site.
- The median cubital vein is the preferred site.
- Veins on the hand or at ankle may be used.
26Prof Asmaa El Reweny, MD
Increase (%) of plasma concentration of various analytes
when changing from supine to an upright position
Phlebotomy Technique
 Cleaning of venipuncture site
 Thorough cleaning with alcohol
 Allow alcohol to dry completely to avoid
stinging sensation and hemolysis of sample
 Iodine for blood culture samples (sterile
sample)
NB: contamination occurs in 50% at some
hospitals with increased costs & patient
overtreatment.
28Prof Asmaa El Reweny, MD
Collection site
Avoid the arm with:
- Extensive scarring, hematoma, infection, edema
or burn
- On the same side of mastectomy.
- I.V. infusion (Document if IV ).
29Prof Asmaa El Reweny, MD
Phlebotomy Technique
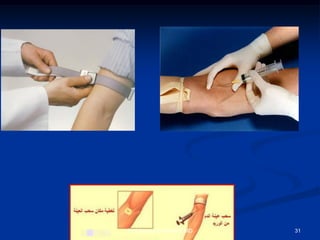
3. Correct collection system
 Vacutainers for large veins in antecubital fossa.
 Syringe for small, fragile veins or veins outside
antecubital fossa.
4. Venous access
 Needle entry should be at 15-30o depending on depth
of vein.
 Needle entry should be in same direction as vein,
centered over vein.
 Anchor vein to prevent movement during needle
entry and to reduce pain to patient.
30Prof Asmaa El Reweny, MD
31Prof Asmaa El Reweny, MD
Phlebotomy Technique Errors
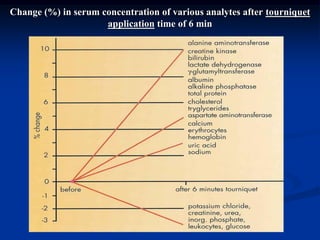
 Tourniquet Application
 Tourniquet tied too close to venipuncture site
can cause hematoma.
 Veins may not become prominent if tourniquet
is tied too high (> 3-4 inches above venipuncture site)
 Tourniquet left for > 1 min can result in
hemoconcentration, affecting some test results.
 Tourniquet should be released as soon as
needle is in the lumen of vein and blood flow is
established.
32Prof Asmaa El Reweny, MD
Change (%) in serum concentration of various analytes after tourniquet
application time of 6 min
Collection
 Additives used:
- EDTA,
- Citrate,
- Lithium heparin,
- Fluoride/ Oxalate
34Prof Asmaa El Reweny, MD
Selection of tubes - Common problems
Solution: New sample needs to be sent to lab.
Typical errors Consequences
Incorrect tube • cannot be analysed
• risk of contamination
Incorrect order of tubes • contaminations
• false results
Common problem: Hemolysis
 Causes of Hemolysis
 Traumatic venipuncture
 Blood collected from area with hematoma
 Vigorous shaking after collection
 Milking the site when collecting capillary samples
 Blood collected using a small diameter needle.
 High filling pressure through a narrow entrance (e.g
during too vigorous sample aspiration)
 Cooling down the sample < 0 °C.
36Prof Asmaa El Reweny, MD
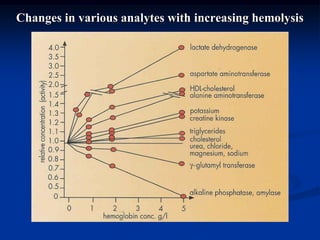
Hemolysis:
Affects analytes that are present at
higher concentrations in erythrocytes
than in plasma (K, LD, AST, Mg, P, ACP)
Hemolysis may also affect unblanked
analytical methods.
37Prof Asmaa El Reweny, MD
Collection
 Capillary Collections:
 Appropriate site
 Heel stick: sides of bottom surface
of the heel (infants)
 Finger stick: third or fourth fingers,
perpendicular to fingerprint lines on fleshy
pads on finger surface.
 Warm before collection to increase capillary
blood flow near skin surface.
 Clean site with alcohol and allow to dry.
 Discard first drop of blood.
38Prof Asmaa El Reweny, MD
Recommended order of draw (NCCLS):
1. Blood Culture Bottles
2. Coagulation Tube
3. Serum Tube with or without clot activator,
with or without gel separator
4. Heparin Tube with or without gel plasma
separator
5. EDTA
6. Glycolytic Inhibitor
39Prof Asmaa El Reweny, MD
Correct Specimen Volume
(blood to additive ratio).
 Little blood in heparin tube makes heparin
relatively higher in concentration and may
potentially interfere with some chemistry
analysis
 In Coagulation Studies incomplete filling
results in specimen dilution and prolonged
Prothrombin Time & PTT results.
40Prof Asmaa El Reweny, MD
 Proper Tube Mixing:
All tubes with additives need to be
inverted (10 times) to mix the
additive evenly with the blood.
Improper mixing of the tube after
venipuncture could contribute to
sample clotting.
41Prof Asmaa El Reweny, MD
Sampling - Common problems
Typical errors Consequences
Trauma, strangulation, stasis hemolysis, hemoconcentration
IV contamination dilution, false results
Sample volume is insufficient incomplete lab results, repeat
sampling
Incomplete filling of tubes inappropriate anticoagulant:blood
ratio, false results
Inappropriate mixing clotted, hemolysed sample
Solution:
Lab report with preanalytical comment (if problem
recognized).
New sample is requested.
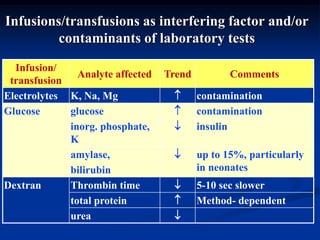
Infusions/transfusions as interfering factor and/or
contaminants of laboratory tests
Infusion/
transfusion
Analyte affected Trend Comments
Electrolytes K, Na, Mg  contamination
Glucose glucose  contamination
inorg. phosphate,
K
 insulin
amylase,
bilirubin
 up to 15%, particularly
in neonates
Dextran Thrombin time  5-10 sec slower
total protein  Method- dependent
urea 
Infusion, transfusion, catheters
 Blood should never be collected proximal to the
infusion site.
 It is recommended that the laboratory be
informed of when and what type of infusion were
carried out and when blood samples were taken.
 If samples are to be taken from catheters, the
cannula should be rinsed with isotonic saline
suitable for the volume of catheter. The first 5 ml
of blood should be discarded before a blood
sample is taken.
Some points in sampling from A-lines
Preparation
prior
to sampling
Sampling/
handling
•Label with patient ID.
•Use dry electrolyte balanced heparin.
•Keep patient respiratory condition stable
for a certain period prior to sampling.
•Make sure that the A-line has been
adequately cleared of flush solution.
•Aspirate the sample slowly to prevent
degassing & hemolysis.
•Expel any air bubbles immediately after
sampling.
•Mix sample thoroughly with heparin after
sampling.
45Prof Asmaa El Reweny, MD
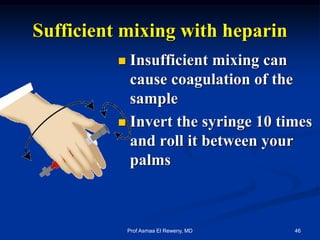
Sufficient mixing with heparin
 Insufficient mixing can
cause coagulation of the
sample
 Invert the syringe 10 times
and roll it between your
palms
46Prof Asmaa El Reweny, MD
Transportation to the Laboratory
Specimen Transport
- Time
- Temperature
- Light
48Prof Asmaa El Reweny, MD
Blood Specimen Transport
 Proper transport of specimens after
collection ensures quality of sample
(& tests).
 Timing
 Some specimens must be transported
immediately (Arterial Blood Gases).
 Specimens for serum or plasma chemistry
testing should be centrifuged and separated
within 2 hs. 49Prof Asmaa El Reweny, MD
Transport Errors
 Temperature
On ice: ABGs, Ammonia
Warmed (37 C): cryoglobulins
Avoid temperature extremes if transported
via vehicle.
 Transport Container
 Some samples need to be protected from light
e.g. bilirubin.
 Transport in leak-proof plastic bags in
lockable rigid containers & avoid agitation.
50Prof Asmaa El Reweny, MD
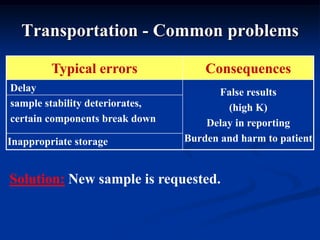
Transportation - Common problems
Typical errors Consequences
Delay False results
(high K)
Delay in reporting
Burden and harm to patient
sample stability deteriorates,
certain components break down
Inappropriate storage
Solution: New sample is requested.
Special Handling of Blood Specimens:
 Chilled tube:
To maintain stability of some analytes, a
slurry of ice & water is recommended for
chilling.
Examples :
1. ACTH, PTH, Catecholamine & Renin
2. Angiotensin Converting Enzyme (ACE),
3. Acetone, Ammonia,, Free Fatty Acids,
Lactic Acid, Pyruvate…
52Prof Asmaa El Reweny, MD
Intra-laboratory Handling,
Preparation and Storage of Samples
 Registration, identification
 Checking for clots
 Centrifugation
 Distribution
 Storage (non routine daily analysis ,
for post-analysis if it is needed)
Intra-laboratory handling –
Common problems
Typical errors Consequences
Native blood centrifugated before
clotting
Hemolysed sample, fibrin strand
in serum, clogging
Inappropriate melting of frozen
specimens
False concentration or
precipitation, …… false result
Inappropriate storage of samples
in lab (sample ID lost,
contamination, break down of
unstable components … etc.)
False results
Contamination
Clots in anticoagulated blood
Cryoglobulins
False results
Solution: New sample is requested when necessary.
Common Interferences
Typical errors Consequences
in vitro hemolysis •High K, LDH, HB
•interference with many analytical
procedures
Hyperlipidaemia •Pseudo-hyponatraemia
•Interference with many analytical
procedures
Hyperbilirubinaemia •Interferences
Drugs •Interference
Solution: - New sample is requested.
- Alternative methods used.
- Results commented.
Changes in various analytes with increasing hemolysis
Quality Markers for
Rejection of Samples
 Clotted
 Hemolyzed
 Underfilled, overfilled
 Insufficient quantity
 Incorrect labeling
 Unlabeled specimen
 Incorrect patient
 Incorrect specimen
 Contaminated
 Lost sample
 Too old to process
 Broken and leaking
57Prof Asmaa El Reweny, MD
Finally…
 The human role in sample collection makes
complete elimination of errors associated with
laboratory testing unrealistic
 However, good practices and compliance with
strategies for error prevention can lead to a
substantial reduction in pre-analytical errors.
Thank You
58Prof Asmaa El Reweny, MD
References
[ 1] Magee, L. S. Preanalytical variables in the chemistry
laboratory. Becton Dickinson Lab Notes 2005; 1 (1)
[2] Sarstedt AG: Tipps und Tricks in der Preanalytik, 2008
[3] Tyndall, L. Managing Preanalytical Variability in
Hematology. Becton Dickinson Lab Notes 2004; 14 (1)
[4] WHO guidelines on drawing blood: best practices in
phlebotomy, 2010
Prof Asmaa Elreweny, MD59
‫العالمين‬‫رب‬ ‫هلل‬ ‫الحمد‬
‫التنزيل‬ ‫مواطن‬ ‫شهدت‬ ‫بلدة‬ ‫هي‬
‫وجبرائيل‬ ‫ميكائيل‬ ‫اتها‬‫طرق‬ ‫في‬ ‫مشى‬
60
Prof Dr Asmaa El-Reweny