1
UNIVERSITY INSTITUTE OF APPLIED HEALTH SCIENCES
DEPARTMENT OF MEDICAL LAB TECHNOLOGY
LAB MANUAL
PROGRAM NAME: B.Sc. MLT / Sem-1 / Batch-2022-23
Subject Name: Physiology – I Lab
Subject Code: 22_MLH-104
Faculty Name: Attuluri Vamsi Kumar (E13404)
Assistant professor
Department of MLT
Prepared by Verified by Approved by
Attuluri Vamsi Kumar
E13404
2
SYLLABUS
LIST OF EXPERIMENTS
Coarse Objectives
To learn the basic knowledge blood and its components
To develop an understanding of the physiology of organs and organ systems in normal human body.
Subject outcomes
CO1 Recall the functions of different components of blood
CO2 Explain the working of heart and different parts of digestive system
CO3 Inspect the working of different parts of respiratory system and physiology of hormones
CO4 Test for vital signs in the patient
Experiment No Experiment Name
1. To estimate bleeding time and clotting time.
2. To determine the blood group using an antisera kit.
3. To record the blood pressure using a sphygmomanometer.
4. To estimate the hemoglobin content of your own blood
5. To demonstrate the working and significance of ECG
6. To record the body temperature and pulse rate.
7. To study the physiology of heart.
8. To study the physiology of digestive system.
9. To study the physiology of respiratory system.
10. To study the lung volumes and capacities
Textbooks / Reference Books
1. Guyton (Arthur): Suggested Readings/ Books: of Physiology. Latest Ed. Prism publishers.
2. Chatterjee CC: Human Physiology Latest Ed. Vol-1, Medical Allied Agency.
3
Course Name/ code Physiology-I / 22-MLH-104
Experiment No 1
Title To estimate bleeding time and clotting time.
Faculty in charge Mr. Attuluri Vamsi Kumar
Department / Institute Department of MLT/ UIAHS
Program B.Sc. MLT
Semester 1
1. TO ESTIMATE BLEEDING TIME AND CLOTTING TIME
BLEEDING TIME
INTRODUCTION:
➢ The bleeding time is the required for a small cut to stop bleeding.
➢ When a blood vessel is injured, blood comes out for some time and then it stops
because of the formation of platelet plug.
➢ The duration of bleeding is the bleeding time
➢ Normal value for bleeding time is 1-3 minutes.
➢ The bleeding time can be performed by following methods:
➢ Finger prick Method, Ivy Method, Duke’s method
AIM:
To demonstrate the Bleeding Time by Finger prick method
PRINCIPLE:
A small puncture is made on the skin and the time for which it bleeds is noted. Bleeding stops
when platelet plug forms and breach in the vessel wall has sealed.
EQUIPMENT:
• Sterile lancet
• Filter paper
• Stopwatch
• Cotton, sprit
4
• Other PPE’s
PROCEDURE
1. Clean the tip of a finger with spirit.
2. Prick with a disposable needle or lancet.
3. Start the stop-watch immediately.
4. Start gently touching the pricked finger with a filter paper for every 30 seconds till
blood spots continue to be made on the filter paper.
5. Stop the watch when no more blood spot comes on the filter paper and note the time.
Normal values:
1 – 3 Minutes
Observation
…………………………………………………………………………………………………
…………………………………………………………………………………………………
………………………………………………………………………………………………….
Result
The bleeding time of the subject is found to be ………………………. Minutes
Clinical Significance
…………………………………………………………………………………………………
…………………………………………………………………………………………………
…………………………………………………………………………………………………
…………………………………………………………………………………………………
…………………………………………………………………………………………………
…………………………………………………………………………………………………
…………………………………………………………………………………………………
…………………………………………………………………………………………………
5
CLOTTING TIME
INTRODUCTION
• Whenever a great blood vessel ruptures bleeding continues. In a few minutes blood
looses its fluidity and sets into a semisolid mass. This mass is referred as clot and the
phenomenon as coagulation.
Definition
• Clotting time is defined as the time interval in between onset of bleeding and
appearance of semisolid mass i.e. Clot.
• Normal value of clotting time is 3-4 minutes.
• It is a screening test for coagulation disorders.
Methods
1. Capillary tube method
2. Lee and White method
AIM:
To demonstrate the clotting time by Capillary tube method
1. Capillary Tube Method
EQUIPMENT:
• Sterile lancet
• capillary tube
• Stopwatch
• Cotton, sprit
• Other PPE’s
Procedure
1. Clean the tip of a finger with spirit.
2. Puncture it upto 3 mm deep with a disposable needle.
3. Start the stop-watch.
4. Fill two capillary tubes with free flowing blood from the puncture after wiping the first
drop of blood.
6
5. Keep these tubes at body temperature.
6. After 2 minutes start breaking the capillary tube at 1cm distance to see whether a thin
fibrin strand is formed between the two broken ends.
7. Stop the watch and calculate the time from average of the two capillary tubes.
Observation
…………………………………………………………………………………………………
…………………………………………………………………………………………………
………………………………………………………………………………………………….
Result
The clotting time of the subject is found to be ………………………. Minutes
Clinical Significance
…………………………………………………………………………………………………
…………………………………………………………………………………………………
…………………………………………………………………………………………………
…………………………………………………………………………………………………
…………………………………………………………………………………………………
7
Course Name/ code Physiology-I / 22-MLH-104
Experiment No 2
Title To determine the blood group using an antisera kit.
Faculty in charge Mr. Attuluri Vamsi Kumar
Department / Institute Department of MLT/ UIAHS
Program B.Sc. MLT
Semester 1
2. TO DETERMINE THE BLOOD GROUP USING AN ANTISERA KIT.
Aim: To perform ABO bold group by Forward & Reverse blood group method
Objectives:
Using the slide agglutination method, determine with 100% accuracy the ABO group of
specimens using reagent antiseras, blood specimens, and other materials provided.
1. If applicable, evaluate reagent package inserts / instructional materials to determine the
substance being analyzed, the principle of the procedure, the expected value,
significance of abnormal results, limitations of the procedure, and troubleshooting
procedures to follow if / when control results are unacceptable.
2. Utilize lecture notes, textbook and laboratory information to answer study questions.
Principle:
When red cells are mixed with various reagent antiseras (soluble antibody), agglutination
will occur on the slides containing cells positive for (possessing the antigen) the
corresponding antigen. No agglutination will occur when the red cells do not contain the
corresponding antigen. One primary application of this principle is blood typing.
Material: 1. Antibody A
2. Antibody B
3. Red blood cells (#1 and #2)
4. Slides
5. Applicator sticks
6. Pipets
Procedure: 1. On the section of slide labeled anti-A place one drop of antibody A.
8
2. On the section of slide labeled anti-B place one drop of antibody B.
3. Place one drop of cells in each antibody containing circle.
4. Carefully mix each solution with a separate applicator stick.
5. Tilt slowly for one minute.
6. Record results.
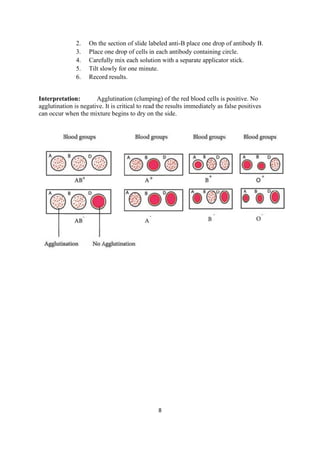
Interpretation: Agglutination (clumping) of the red blood cells is positive. No
agglutination is negative. It is critical to read the results immediately as false positives
can occur when the mixture begins to dry on the side.
9
Course Name/ code Physiology-I / 22-MLH-104
Experiment No 3
Title To record the blood pressure using a sphygmomanometer.
Faculty in charge Mr. Attuluri Vamsi Kumar
Department / Institute Department of MLT/ UIAHS
Program B.Sc. MLT
Semester 1
3. TO RECORD THE BLOOD PRESSURE USING A SPHYGMOMANOMETER.
Introduction:
Blood pressure is the force exerted by blood against the walls of arteries and veins. It is
created by the pumping action of the heart. Blood pressure is measured in millimeters of
mercury (mm Hg) and is expressed by two numbers—120/80, for example. The higher
number is systolic blood pressure, the maximum pressure that occurs when the heart
contracts. The lower number is diastolic blood pressure, the pressure when the heart is
relaxed between contractions.
Aim: To determine the blood pressure by sphygmomanometer
Principle:
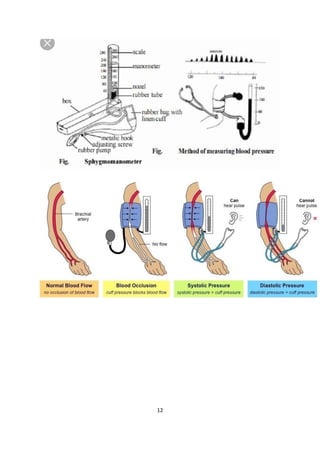
The sphygmomanometer cuff is inflated to well above expected systolic pressure. As the valve
is opened, cuff pressure (slowly) decreases. When the cuff’s pressure equals the arterial systolic
pressure, blood begins to flow past the cuff, creating blood flow turbulence and audible sounds.
Using a stethoscope, these sounds are heard and the cuff’s pressure is recorded. The blood flow
sounds will continue until the cuff’s pressure falls below the arterial diastolic pressure. The
pressure when the blood flow sounds stop indicates the diastolic pressure.
Systolic and diastolic pressures are commonly stated as systolic ‘over’ diastolic. For example,
120 over 80. Blood flow sounds are called Korotkoff sounds.
Equipment
1. Sphygmomanometer (A sphygmomanometer consists of an inflatable bag inside a
covering called a cuff, an inflating bulb, a manometer from which blood pressure can
be read, and a valve that is used for deflation.)
2. Stethoscope
3. Chair
4. Table or other surface to support arm
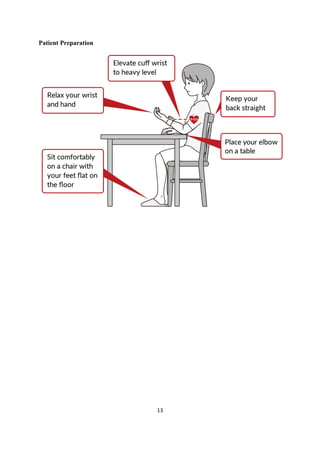
Patient Preparation:
For the person being tested:
➢ Wear clothing that allows your upper arm to be bare.
10
➢ Avoid heavy exercise or eating prior to the test.
➢ Don’t smoke or ingest caffeine for at least 30–60 minutes before being tested.
➢ Sit quietly for several minutes before the test begins.
Procedure:
1. The subject should sit comfortably, with the arm slightly flexed, palm up, and the
forearm supported at heart level on a table or other smooth surface. If such a surface isn’t
available, you will need to support the subject’s forearm while you take the
measurements.
2. Place the deflated cuff on the subject’s upper arm, with the lower edge of the cuff about
1 inch above the inner elbow crease. The inflatable bag should rest on the brachial artery,
which is on the inner part of the upper arm. The inflatable bag should encircle at least
80% of the arm; if it does not, use a larger sphygmomanometer.
3. Apply the stethoscope lightly to the arm, just at the inner elbow crease. Make sure the
stethoscope doesn’t touch the cuff or any of the tubing from the sphygmomanometer.
4. While watching the manometer and listening for pulse sounds through the stethoscope,
inflate the bag about 30 mm Hg above the point at which pulse sounds disappear.
(Inflating the bag closes off the blood flow in the brachial artery, causing the pulse
sounds to stop.)
5. Slowly deflate the bag at a rate of about 3 mm Hg per second (or per heartbeat). As you
release the pressure, pulse sounds will become audible, go through several changes in
clarity and intensity, and then disappear again. You must listen carefully to the pulse
sounds while you watch the readings on the manometer.
• Systolic pressure is the point at which pulse sounds first become audible. You
should hear faint but clear tapping sounds.
• Diastolic pressure is the point at which the pulse sounds disappear. (Note: If you
are measuring blood pressure as part of an exercise test, the method for
determining diastolic pressure is somewhat different. Sometimes during exercise
the sounds are audible all the way down to 0 mm Hg. If this occurs, diastolic
pressure is the point at which there is a definite change in the loudness of the
sound—an abrupt muffling.)
6. Wait 1–2 minutes and then repeat the test. Record both results and indicate which arm was
used for the measurements.
11
Observation
…………………………………………………………………………………………………
……………………………………………….
Result:
…………………………………………………………………………………………………
………………………………………………….
Clinical significance:
…………………………………………………………………………………………………
……………………………………………………………
12
13
Patient Preparation
14
Course Name/ code Physiology-I / 22-MLH-104
Experiment No 4
Title To estimate the hemoglobin content of your own blood
Faculty in charge Mr. Attuluri Vamsi Kumar
Department / Institute Department of MLT/ UIAHS
Program B.Sc. MLT
Semester 1
4. TO ESTIMATE THE HEMOGLOBIN CONTENT OF YOUR OWN BLOOD
Aim: To estimate hemoglobin in the given sample by Sahli’s method.
Principle: Hb is converted into acid haematin with the action of dilute hydrochloric acid
(N/10 HCl). The acid haematin is brown in colour and its intensity is matched with a standard
brown glass comparator in a visual colorimeter called Sahli’s
colorimeter.
Materials required:
• Sahli’s Apparatus
o Hemoglobin pipette (0.02 ml or 20 µl capacity)
o Sahli’s graduated Hemoglobin tube
o Thin glass rod Stirrer for Hemoglobin Tube
o Sahli’s Comparator box with brown glass standard
• Spirit swab
• Blood Lancet
• Dry cotton swab
• Pasteur pipette
Procedure:
• Fill Sahli’s Hb tube up to mark 2 with N/10 HCl.
• Deliver 20 μl (0.02 ml) of blood from a Hb pipette into it.
• Stir with a stirrer and wait for 10 minutes.
• Add distilled water drop by drop and stir till colour matches
• with the comparator.
• Take the reading at upper meniscus
Observation
………………………………………………………………………………………………………………………………………………
………………………………………………………………………………………………………………………………………………
15
Result
…………………………………………………………………………………………………
………………………………………………………………………………………………….
Normal Values:
Raised Hemoglobin Content
• Polycythemia Vera
• Associated with Hypoxia
• Cyanotic Congenital Heart disease
• High Altitudes
• Heavy smoking
• Methemoglobinemia
• Elevated erythropoietin levels
o Tumors of Kidney, Liver, CNS, Ovary etc.
o Renal Diseases (Hydronephrosis & Vascular impairment)
• Adrenal hypercorticism
• Therapeutic androgens
• Relative causes of high hemoglobin content
o Dehydration – Water deprivation, Vomiting, Diarrhea
o Plasma loss – Burns, Enteropathy
Reduced Hemoglobin Content
Low Hemoglobin value means anemia caused by the following conditions
16
Leukemia
Tuberculosis
Iron deficiency anemia
Parasitic infections severely in hookworm infection
Sickle cell anemia
Thalassemia
Aplastic anemia
Hemolytic anemia
Loss of blood
Reference:
https://www.notesonzoology.com/practical-zoology/laboratory/top-3-haematological-experiments-
for-counting-blood-cells-under-microscope/3003
17
Course Name/ code Physiology-I / 22-MLH-104
Experiment No 5
Title To demonstrate the working and significance of ECG
Faculty in charge Mr. Attuluri Vamsi Kumar
Department / Institute Department of MLT/ UIAHS
Program B.Sc. MLT
Semester 1
5. TO DEMONSTRATE THE WORKING AND SIGNIFICANCE OF ECG
Introduction:
Electrocardiogram refers to the recording of electrical changes that occurs in heart during a
cardiac cycle. It may be abbrivated as ECG or EKG. It is an instrument that picks up the electric
currents produced by the heart muscle during a cardiac cycle of contraction and relaxation.
Aim:
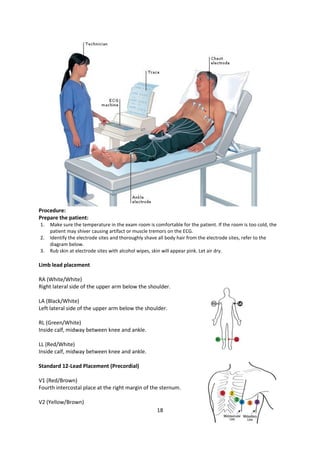
To perform Electro Cardiogram (ECG) in the patient by placing electrodes over chest.
Working principle of electrocardiograph:
➢ It works on the principle that a contracting muscle generates a small electric current that can
be detected and measured through electrodes suitably placed on the body.
➢ For a resting electrocardiogram, a person is made to lie in the resting position and
electrodes are placed on arms, legs and at six places on the chest over the area of the heart.
The electrodes are attached to the person’s skin with the help of a special jelly.
➢ The electrode picks up the current and transmit them to an amplifier inside the
electrocardiograph. Then electrocardiograph amplifies the current and records them on a
paper as a wavy line.
➢ In an electrocardiograph, a sensitive lever traces the changes in current on a moving sheet of
paper.
➢ A modern electrocardiograph may also be connected to an oscilloscope, an instrument that
display the current on a screen.
18
Procedure:
Prepare the patient:
1. Make sure the temperature in the exam room is comfortable for the patient. If the room is too cold, the
patient may shiver causing artifact or muscle tremors on the ECG.
2. Identify the electrode sites and thoroughly shave all body hair from the electrode sites, refer to the
diagram below.
3. Rub skin at electrode sites with alcohol wipes, skin will appear pink. Let air dry.
Limb lead placement
RA (White/White)
Right lateral side of the upper arm below the shoulder.
LA (Black/White)
Left lateral side of the upper arm below the shoulder.
RL (Green/White)
Inside calf, midway between knee and ankle.
LL (Red/White)
Inside calf, midway between knee and ankle.
Standard 12-Lead Placement (Precordial)
V1 (Red/Brown)
Fourth intercostal place at the right margin of the sternum.
V2 (Yellow/Brown)
19
Fourth intercostal place at the left margin of the sternum.
V3 (Green/Brown)
Midway between V2 and V4 (on top of the 5th rib).
V4 (Blue/Brown)
Fifth intercostal place at the left midclavicular line.
V5 (Orange/Brown)
At the horizontal level of V4, at the anterior axillary.
V6 (Purple/Brown)
At the horizontal level of V4, at the midaxillary line.
Attach the electrodes and lead wires:
4. After the locations are properly prepared; apply fresh electrodes to the patient.
5. Make sure the electrodes are adhering well; if not, ensure the locations are cleaned properly with alcohol
wipes and the locations are dry before applying the fresh electrodes.
6. Attach the clips to the disposable electrodes. Refer to the label on the patient cables, see image below,
for proper placement sites.
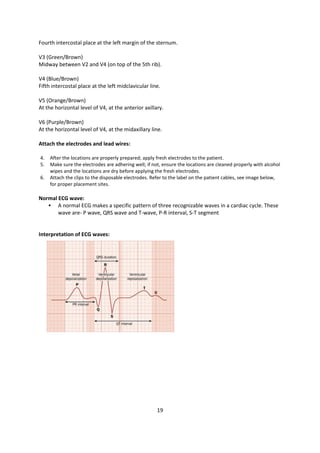
Normal ECG wave:
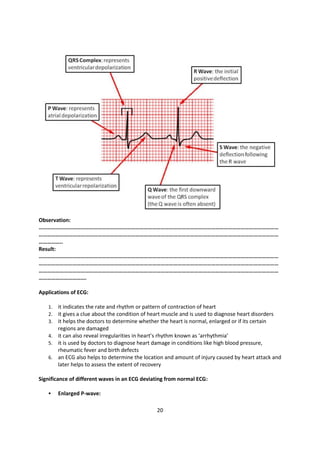
▪ A normal ECG makes a specific pattern of three recognizable waves in a cardiac cycle. These
wave are- P wave, QRS wave and T-wave, P-R interval, S-T segment
Interpretation of ECG waves:
20
Observation:
………………………………………………………………………………………………………………………………………………………
………………………………………………………………………………………………………………………………………………………
……………..
Result:
………………………………………………………………………………………………………………………………………………………
………………………………………………………………………………………………………………………………………………………
………………………………………………………………………………………………………………………………………………………
…………………………….
Applications of ECG:
1. it indicates the rate and rhythm or pattern of contraction of heart
2. it gives a clue about the condition of heart muscle and is used to diagnose heart disorders
3. it helps the doctors to determine whether the heart is normal, enlarged or if its certain
regions are damaged
4. it can also reveal irregularities in heart’s rhythm known as ‘arrhythmia’
5. it is used by doctors to diagnose heart damage in conditions like high blood pressure,
rheumatic fever and birth defects
6. an ECG also helps to determine the location and amount of injury caused by heart attack and
later helps to assess the extent of recovery
Significance of different waves in an ECG deviating from normal ECG:
▪ Enlarged P-wave:
21
▪ It indicates enlarged atrium (it occurs in a condition called mitral stenosis in which
due to narrowing of mitral valve, blood backs up into left atrium)
▪ Enlarged Q-wave: downward wave
▪ It indicates a myocardial infraction ( heart attack)
▪ Enlarged R- wave:
▪ It indicates enlarged ventricles
▪ Long P-Q interval:
▪ It indicates more time taken by impulse to travel through atria and reach ventricles
▪ It happens in coronary artery disease and rheumatic fever when a scar tissue may
form in heart
▪ Elevated S-T segment:
▪ When S-T segment is above the base line, it may indicates acute myocardial
infraction
▪ Depressed S-T segment:
▪ It indicates that heart muscles receive insufficient oxygen
▪ Flatter T-wave:
▪ It indicates insufficient supply of oxygen to heart muscle as it occurs in coronary
artery disease
▪ Elevated T-wave:
▪ It may indicates increased level of potassium ions in blood as in hyperkalemia
22
Course Name/ code Physiology-I / 22-MLH-104
Experiment No 6
Title To record the body temperature and pulse rate.
Faculty in charge Mr. Attuluri Vamsi Kumar
Department / Institute Department of MLT/ UIAHS
Program B.Sc. MLT
Semester 1
6. TO RECORD THE BODY TEMPERATURE AND PULSE RATE
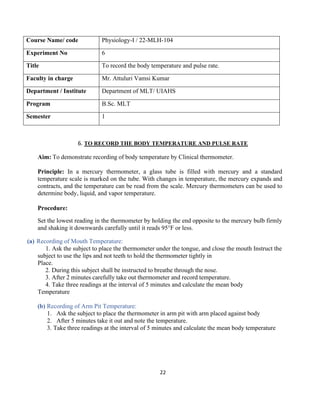
Aim: To demonstrate recording of body temperature by Clinical thermometer.
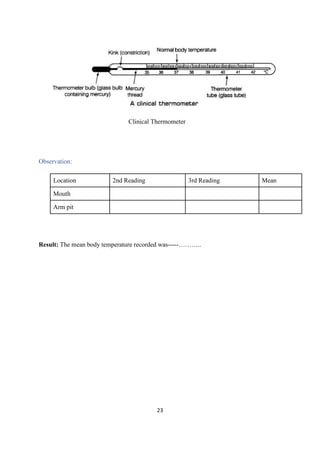
Principle: In a mercury thermometer, a glass tube is filled with mercury and a standard
temperature scale is marked on the tube. With changes in temperature, the mercury expands and
contracts, and the temperature can be read from the scale. Mercury thermometers can be used to
determine body, liquid, and vapor temperature.
Procedure:
Set the lowest reading in the thermometer by holding the end opposite to the mercury bulb firmly
and shaking it downwards carefully until it reads 95°F or less.
(a) Recording of Mouth Temperature:
1. Ask the subject to place the thermometer under the tongue, and close the mouth Instruct the
subject to use the lips and not teeth to hold the thermometer tightly in
Place.
2. During this subject shall be instructed to breathe through the nose.
3. After 2 minutes carefully take out thermometer and record temperature.
4. Take three readings at the interval of 5 minutes and calculate the mean body
Temperature
(b) Recording of Arm Pit Temperature:
1. Ask the subject to place the thermometer in arm pit with arm placed against body
2. After 5 minutes take it out and note the temperature.
3. Take three readings at the interval of 5 minutes and calculate the mean body temperature
23
Clinical Thermometer
Observation:
Location 2nd Reading 3rd Reading Mean
Mouth
Arm pit
Result: The mean body temperature recorded was-----………..
24
PULSE RATE
Aim: To determine the pulse rate of the patient
Principle: The circulatory system functions to deliver oxygen and nutrients to the tissues for
growth and to remove metabolic wastes. The heart pumps blood through a circuit that
includes arteries, arterioles, capillaries, venules, and veins. One important circuit is the
pulmonary circuitwhere there is an exchange of gases within the alveoli of the lung. With
increased exercise several changes occur within the circulatory system to increase the
delivery of oxygen to activelyrespiring muscle cells
Materials: The following materials are needed to complete this laboratory experience:
• stopwatch or watch with
• pens and pencils
• lab papers
• graph paper
Procedure:
1. The subject should sit at ease for two minutes.
2. At the end of this time take your partner's pulse by placing index and middle finger near to the
wrist.
3. Count the number of beats for 30 seconds and multiply by 2.
4. Record this data in the data sheetprovided.
5. Make sure NOT to use your thumb in taking a pulse.
Clinical Observation
………………………………………………………………………………………………………
………………………………………………………………………………………………………
Result
………………………………………………………………………………………………………
………………………………………………………………………………………………………
Pulse Reading
25
Course Name/ code Physiology-I / 22-MLH-104
Experiment No 7
Title To study the physiology of heart
Faculty in charge Mr. Attuluri Vamsi Kumar
Department / Institute Department of MLT/ UIAHS
Program B.Sc. MLT
Semester 1
7. TO STUDY THE PHYSIOLOGY OF HEART
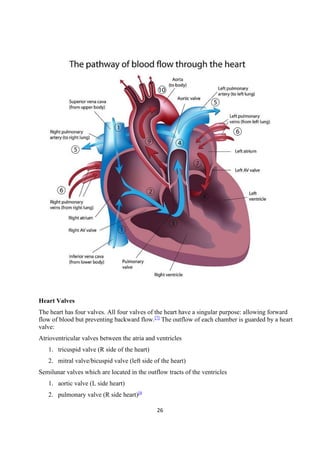
Aim: To demonstrate anatomy & physiology of human heart
The heart is a muscular organ that serves to collect deoxygenated blood from all parts of the body,
carries it to the lungs to be oxygenated and release carbon dioxide. Then, it transports the
oxygenated blood from the lungs and distributes it to all the body parts
• The heart pumps around 7,200 litres of blood in a day throughout the body
• The heart is situated at the centre of the chest and points slightly towards the left.
• On average, the heart beats about 100,000 times a day, i.e., around 3 billion beats in a
lifetime.
• An adult heart beats about 60 to 80 times per minute, and newborn babies heart beats faster
than an adult which is about 70 to 190 beats per minute.
Structure and Function
The heart is subdivided by septa into right and left halves, and a constriction subdivides
each half of the organ into two cavities, the upper cavity being called the atrium, the
lower the ventricle. The heart, therefore, consists of four chambers:
• right atrium
• left atrium
• right ventricle
• left ventricle[4]
.
26
Heart Valves
The heart has four valves. All four valves of the heart have a singular purpose: allowing forward
flow of blood but preventing backward flow.[7]
The outflow of each chamber is guarded by a heart
valve:
Atrioventricular valves between the atria and ventricles
1. tricuspid valve (R side of the heart)
2. mitral valve/bicuspid valve (left side of the heart)
Semilunar valves which are located in the outflow tracts of the ventricles
1. aortic valve (L side heart)
2. pulmonary valve (R side heart)[4
27
Heart Conduction System
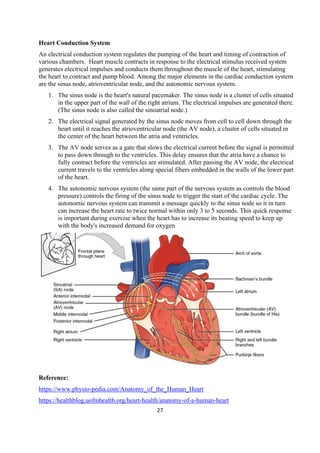
An electrical conduction system regulates the pumping of the heart and timing of contraction of
various chambers. Heart muscle contracts in response to the electrical stimulus received system
generates electrical impulses and conducts them throughout the muscle of the heart, stimulating
the heart to contract and pump blood. Among the major elements in the cardiac conduction system
are the sinus node, atrioventricular node, and the autonomic nervous system.
1. The sinus node is the heart's natural pacemaker. The sinus node is a cluster of cells situated
in the upper part of the wall of the right atrium. The electrical impulses are generated there.
(The sinus node is also called the sinoatrial node.)
2. The electrical signal generated by the sinus node moves from cell to cell down through the
heart until it reaches the atrioventricular node (the AV node), a cluster of cells situated in
the center of the heart between the atria and ventricles.
3. The AV node serves as a gate that slows the electrical current before the signal is permitted
to pass down through to the ventricles. This delay ensures that the atria have a chance to
fully contract before the ventricles are stimulated. After passing the AV node, the electrical
current travels to the ventricles along special fibers embedded in the walls of the lower part
of the heart.
4. The autonomic nervous system (the same part of the nervous system as controls the blood
pressure) controls the firing of the sinus node to trigger the start of the cardiac cycle. The
autonomic nervous system can transmit a message quickly to the sinus node so it in turn
can increase the heart rate to twice normal within only 3 to 5 seconds. This quick response
is important during exercise when the heart has to increase its beating speed to keep up
with the body's increased demand for oxygen
Reference:
https://www.physio-pedia.com/Anatomy_of_the_Human_Heart
https://healthblog.uofmhealth.org/heart-health/anatomy-of-a-human-heart
28
Course Name/ code Physiology-I / 22-MLH-104
Experiment No 8
Title To study the physiology of digestive system
Faculty in charge Mr. Attuluri Vamsi Kumar
Department / Institute Department of MLT/ UIAHS
Program B.Sc. MLT
Semester 1
8. TO STUDY THE PHYSIOLOGY OF DIGESTIVE SYSTEM
Aim: To demonstrate the physiology of digestive system
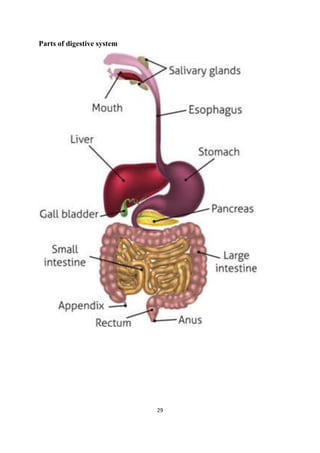
In the human digestive system, large organic masses are broken down into smaller particles that
the body can use as fuel. This is a complex process. The breakdown of the nutrients requires the
coordination of several enzymes secreted from specialized cells within the mouth, stomach,
intestines, and liver. The major organs or structures that coordinate digestion within the human
body include the mouth, esophagus, stomach, small and large intestines, and liver.
Parts of human digestive
29
Parts of digestive system
30
Physiology & functions of the digestive system
Reference:
https://www.topperlearning.com/neet/biology/digestion-and-absorption
31
Course Name/ code Physiology-I / 22-MLH-104
Experiment No 9
Title To study the physiology of respiratory system
Faculty in charge Mr. Attuluri Vamsi Kumar
Department / Institute Department of MLT/ UIAHS
Program B.Sc. MLT
Semester 1
9. TO STUDY THE PHYSIOLOGY OF RESPIRATORY SYSTEM
Aim: To demonstrate the physiology of respiratory system.
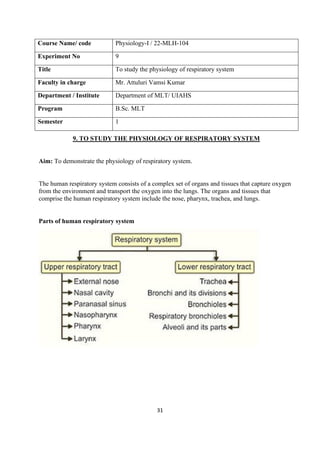
The human respiratory system consists of a complex set of organs and tissues that capture oxygen
from the environment and transport the oxygen into the lungs. The organs and tissues that
comprise the human respiratory system include the nose, pharynx, trachea, and lungs.
Parts of human respiratory system
32
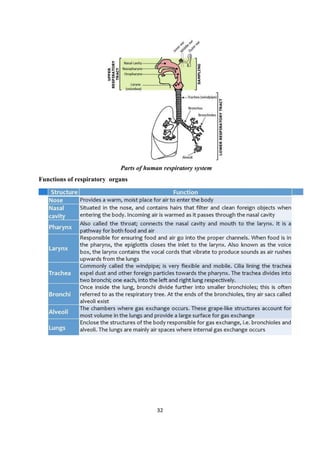
Parts of human respiratory system
Functions of respiratory organs
33
Course Name/ code Physiology-I / 22-MLH-104
Experiment No 10
Title To study the lung volumes and capacities
Faculty in charge Mr. Attuluri Vamsi Kumar
Department / Institute Department of MLT/ UIAHS
Program B.Sc. MLT
Semester 1
10. TO STUDY THE LUNG VOLUMES AND CAPACITIES
Aim: To demonstrate the lung volumes and capacities.
Introduction:
➢ Vital capacity is the amount of air that the lungs can expel after having been filled
completely.
➢ The vital capacity represents the change in volume from completely emptied lungs to
completely filled lungs.
➢ In human medicine, vital capacity is an important measure of a person’s respiratory health.
➢ A healthy adult will have a vital capacity between 2 and 5 liters.
➢ A severely decreased vital capacity is an indication of restrictive lung disease, in which the
lungs cannot expand fully.
➢ If the vital capacity is normal, but the lungs are still not functioning properly, it could be
indication of a obstructive lung disease, in which the lungs are clogged or blocked in the
airways
➢ The vital capacity can be measured with the use of a spirometer, which can also separate
the different components of the vital capacity.
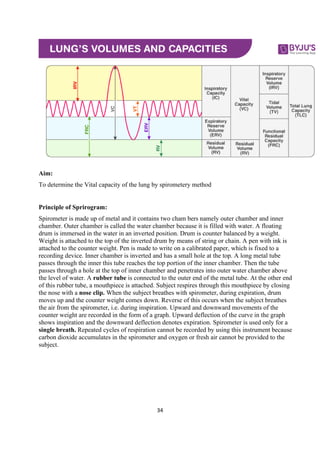
➢ As seen in the following spirograph, the vital capacity consists of the expiratory reserve
volume, the tidal volume, and the inspiratory reserve volume.
➢ The expiratory and inspiratory reserve volumes are the volumes of air taken in and exhaled
above and beyond normal breaths, while the tidal volume represents the standard, low-
volume breath.
34
Aim:
To determine the Vital capacity of the lung by spirometery method
Principle of Sprirogram:
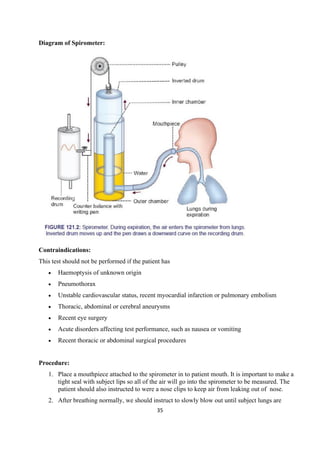
Spirometer is made up of metal and it contains two cham bers namely outer chamber and inner
chamber. Outer chamber is called the water chamber because it is filled with water. A floating
drum is immersed in the water in an inverted position. Drum is counter balanced by a weight.
Weight is attached to the top of the inverted drum by means of string or chain. A pen with ink is
attached to the counter weight. Pen is made to write on a calibrated paper, which is fixed to a
recording device. Inner chamber is inverted and has a small hole at the top. A long metal tube
passes through the inner this tube reaches the top portion of the inner chamber. Then the tube
passes through a hole at the top of inner chamber and penetrates into outer water chamber above
the level of water. A rubber tube is connected to the outer end of the metal tube. At the other end
of this rubber tube, a mouthpiece is attached. Subject respires through this mouthpiece by closing
the nose with a nose clip. When the subject breathes with spirometer, during expiration, drum
moves up and the counter weight comes down. Reverse of this occurs when the subject breathes
the air from the spirometer, i.e. during inspiration. Upward and downward movements of the
counter weight are recorded in the form of a graph. Upward deflection of the curve in the graph
shows inspiration and the downward deflection denotes expiration. Spirometer is used only for a
single breath. Repeated cycles of respiration cannot be recorded by using this instrument because
carbon dioxide accumulates in the spirometer and oxygen or fresh air cannot be provided to the
subject.
35
Diagram of Spirometer:
Contraindications:
This test should not be performed if the patient has
• Haemoptysis of unknown origin
• Pneumothorax
• Unstable cardiovascular status, recent myocardial infarction or pulmonary embolism
• Thoracic, abdominal or cerebral aneurysms
• Recent eye surgery
• Acute disorders affecting test performance, such as nausea or vomiting
• Recent thoracic or abdominal surgical procedures
Procedure:
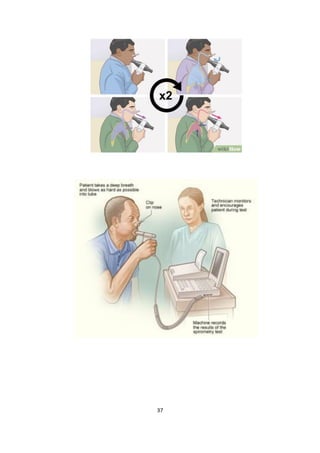
1. Place a mouthpiece attached to the spirometer in to patient mouth. It is important to make a
tight seal with subject lips so all of the air will go into the spirometer to be measured. The
patient should also instructed to were a nose clips to keep air from leaking out of nose.
2. After breathing normally, we should instruct to slowly blow out until subject lungs are
36
empty.
3. Then instruct the subject to take a big, deep breath to fill up his/her lungs completely.
4. As soon as lungs are full, instruct the patient to blow out as hard and as fast as he/she can
until their lungs are absolutely empty.
5. Instruct the subjects to repeat the test until there are three good efforts.
Normal Vital capacity:
Vital capacity (VC) is the maximum volume of air that can be expelled out forcefully after a deep
(maximal)
inspiration. VC includes inspiratory reserve volume, tidal volume and expiratory reserve volume.
VC = IRV + TV + ERV
= 3,300 + 500 + 1,000 = 4,800 mL
Observation
………………………………………………………………………………………………………
………………………………………………………………………………………………………
………………………………………………………………………………………………………
……………………..
Result:
………………………………………………………………………………………………………
………………………………………………………………………………………………………
………………………………………………………………………………………………………
……………
Clinical Significance
………………………………………………………………………………………………………
………………………………………………………………………………………………………
………………………………………………………………………………………………………
………………………………………………………………………………………………………
………………………………………………………………………………………………………
………………………………………………………………………………………………………
…………………………
37
38