











HEMATINICS
IRON
VITAMIN B9 FOLIC ACID
VITAMIN B12 COBALAMIN
ERYTHROPOETIN
HAEMATINICS are substances required in the
formation of blood, and are used for treatment of
anaemias.
• Anaemia occurs when the balance between
production and destruction of RBCs is disturbed by:
(a) Blood loss (acute or chronic)
(b) Impaired red cell formation due to:
• Deficiency of essential factors, i.e. iron, vitamin B12 &
folic acid.
• Bone marrow depression (hypoplastic anaemia),
erythropoietin deficiency.
(c) Increased destruction of RBCs (haemolytic anaemia)
ANAEMIA Types:
Normocytic, normochromic anaemia
 Acute blood loss
Microcytic, hypochromic anaemia
 Iron deficiency anaemia, thalessimia
Macrocytic anaemia
 Vit B12 deficiency, folic acid deficiency
Pernicious anaemia
 Vit B12 deficiency
Hemolytic anaemia
 Destruction of RBC
Sickle cell anaemia
 Sickle shaped RBC
Aplastic anaemia
 Bone marrow disorder
• IRON is an essential body constituent. It is an
essential constituent of hemoglobin, cytochrome, and
other components of respiratory enzyme systems. Its
chief functions are in the transport of oxygen to tissue
(hemoglobin) and in cellular oxidation mechanisms.
Depletion of iron stores may result in iron-deficiency
anemia. Iron is used to build up the blood in
anemia.Total body iron in an adult is 2.5–5 g. It is
more in men (50 mg/kg) than in women (38 mg/kg). It
is distributed into:
• Haemoglobin (Hb) : 66%
• Iron stores as ferritin and haemosiderin: 25%
• Myoglobin (in muscles) : 3%
• Parenchymal iron (in enzymes, etc.) : 6%
• Daily requirement
• Adult male : 0.5–1 mg (13 μg/kg)
• Adult female : 1–2 mg (21 μg/kg)(menstruating)
• Infants : 60 μg/kg
• Children : 25 μg/kg
• Pregnancy : 3–5 mg (80 μg/kg)(last 2 trimesters)
• Dietary sources of iron
• Rich : Liver, egg yolk, oyster, dry beans, dry fruits,
wheat germ, yeast.
• Medium : Meat, chicken, fish, spinach, banana,
apple.
• Poor : Milk and its products, root vegetables.
• Haemoglobin is a protoporphyrin; each molecule
having 4 iron containing haeme residues. It has
0.33% iron; thus loss of 100 ml of blood (containing
15 g Hb) means loss of 50 mg elemental iron. To
raise the Hb level of blood by 1 g/dl—about 200 mg
of iron is needed. Iron is stored only in ferric form,
in combination with a large protein apoferritin.
Iron is found in two forms:
• Heme Iron: Meat, Myoglobin
• Non-Heme Iron: Cereals, Fruits, Legumes
Vitamin C increases absorption of Non-Heme
Iron
Iron is absorbed via two mechanisms:
i) active transport of ferrous iron and
ii) absorption of iron complexed with heme
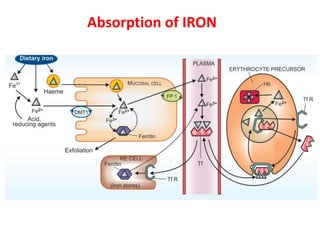
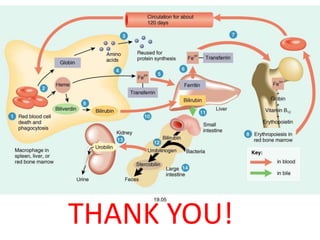
Absorption of IRON
• MOA: Iron is important component of hemoglobin that
carries oxygenated blood from lungs to different body parts.
It also acts as catalyst for many metabolic reactions essential
for cell growth. It maintains a healthy immune system & aids
in energy production. It is transported inside mucosal cell by
DMT1 & across basolateral membrane BY FP1 transporter
protein . Iron released into plasma binds to transferrin &
transported to different cells.
• Indication:
• Dietary Iron deficiency
• Pregnancy
• Premature babies
• Malabsorption
• Haemodialysis
• Anaemia
Oral iron
• The preferred route of iron administration is oral.
• Ferrous sulfate: (hydrated salt 20% iron, dried salt 32% iron)
• Ferrous gluconate (12% iron)
• Ferrous fumarate (33% iron)
Dose: 200 mg elemental iron (infants and children 3–5 mg/kg) TDS
Absorption is much better in empty stomach.
A/E: Gastric Irritaion, Constipation, Staining of teeth, Metallic taste
Parenteral iron
• Iron therapy by injection is indicated only when:
1. Oral iron is not tolerated: bowel upset is too much.
2. Failure to absorb oral iron: inflammatory bowel disease.
3. Non-compliance to oral iron.
4. In presence of severe deficiency with chronic bleeding.
5. Along with erythropoietin.
• IRON DEXTRAN
• IRON SUCROSE, DOSE: 75mg i.m (Max 100mg i.m.)
ACUTE IRON POISONING
• It occurs mostly in infants and children: 10–20 iron tablets or
equivalent of the liquid preparation (> 60 mg/kg iron) may
cause serious toxicity in them.
• Manifestations are vomiting, abdominal pain, haematemesis,
diarrhoea, lethargy, cyanosis, dehydration, acidosis,
convulsions; finally shock, cardiovascular collapse and death.
• Treatment It should be prompt.
To prevent further absorption of iron from gut
(a) Induce vomiting or perform gastric lavage with sodium
bicarbonate solution
(b) Give egg yolk and milk orally: to complex iron.
To bind and remove iron already absorbed Desferrioxamine (an
iron chelating agent) is the drug of choice. It should be injected
i.m. (preferably) 0.5–1 g (50 mg/kg) repeated 4–12 hourly as
required, or i.v. (if shock is present) 10–15 mg/kg/hour; max 75
mg/kg in a day till serum iron falls below 300 μg/dl.
VITAMIN B12
(Cobalamin, Antipernicious anemia factor)
VITAMIN B12 (COBALAMIN)
• It occurs as red crystals synthesized in nature only by
microorganisms; plants and animals acquire it from
them.
• MOA: Vitamin B12 is essential constituents of the
human diet, being necessary for DNA synthesis and
consequently for cell proliferation.
• Vitamin B12 is important in the normal functioning
of the nervous system due to its role in the synthesis
of myelin and in the maturation of developing red
blood cells in the bone marrow.
• Dietary sources Liver, kidney, sea fish, egg yolk, meat,
cheese, legumes, etc.
• Daily requirement 1–3 μg, pregnancy and lactation
3–5 μg.
Vitamin B12 is a family of related compounds
containing a cobalt atom (cobalamins).
The two dietary forms of vitamin B12 are
available and they are known as
methylcobalamin (methyl-B12) and 5-
deoxyadenosylcobalamin (coenzyme-B12).
Synthetic forms of vitamin B12 are known as
hydroxy-cobalamin and cyanocobalamin (not
occur naturally in foods).
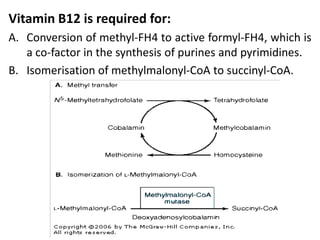
Vitamin B12 is required for:
A. Conversion of methyl-FH4 to active formyl-FH4, which is
a co-factor in the synthesis of purines and pyrimidines.
B. Isomerisation of methylmalonyl-CoA to succinyl-CoA.
• METHYLCOBALAMIN is the active coenzyme form of
vit B12 for synthesis of methionine and S-
adenosylmethionine that is needed for integrity of
myelin.
• This preparation of vit B12 in a dose of 1.5 mg/day
has been especially promoted for correcting the
neurological defects in diabetic, alcoholic and other
forms of peripheral neuropathy.
• Indications:
a) Megaloblastic anemia
b) Neurologic syndrome associated with cobalamin
deficiency
c) Pernicious anemia
d) Treatment of vit B12 deficiency
VITAMIN B9
(FOLIC ACID)
VITAMIN B9 (FOLIC ACID)
• It occurs as yellow crystals which are insoluble in
water, but its sodium salt is freely water soluble.
• Chemically it is Pteroyl glutamic acid (PGA)
consisting of pteridine + paraaminobenzoic acid
(PABA) + glutamic acid.
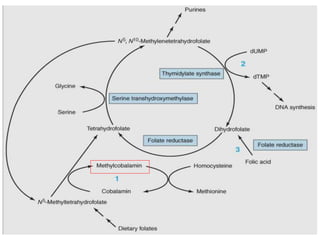
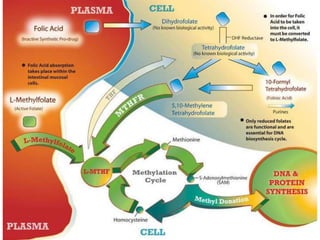
• MOA: Folic acid is a precursor needed to make,
repair, and methylate DNA; a cofactor in cell
division and growth, such as in infancy and
pregnancy.
• Folate is itself inactive. After absorption it is
converted into the active coenzyme, tetrahydrofolic
acid, essential for amino acid and DNA biosynthesis
and cell division.
Folate deficiency occurs due to:
(a) Inadequate dietary intake
(b) Malabsorption: especially involving upper intestine—coeliac
disease, tropical sprue, regional ileitis, etc.
(c) Biliary fistula; bile containing folate for recirculation is drained.
(d) Chronic alcoholism: intake of folate is generally poor.
(e) Increased demand: pregnancy, lactation, rapid growth periods,
haemolytic anaemia and other diseases.
(f) Drug induced: prolonged therapy with anticonvulsants
(phenytoin, phenobarbitone, primidone) and oralcontraceptives—
interfere with absorption and storage of folate.
Manifestations of deficiency are:
(i) Megaloblastic anaemia, indistinguishable from that due to vit
B12 deficiency.
(ii) Epithelial damage: glossitis, enteritis, diarrhoea, steatorrhoea.
(iii) Neural tube defects, including spina bifida in the offspring, due
to maternal folate deficiency.
Sources : yeast , liver , green vegetables, fruits , nuts and
cereals
Daily requirements : Adult: 50 mcg / day
Pregnant women : 100-200 mcg / day
Lactating women : 100-200 mcg / day
Dose: Therapeutic 2 to 5 mg/day, prophylactic 0.5 mg/day.
Indications:
1) Treat magaloblastic anemia due to folate deficiency
2) Pregnant women
3) Premature infants
4) Patients with hemolytic anemia
5) Methotrexate toxicity
6) Citrovorum factor rescue
7) Enhance anticancer efficacy of 5-fluorouracil
8) With anticonvulsant drugs
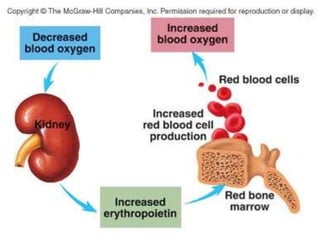
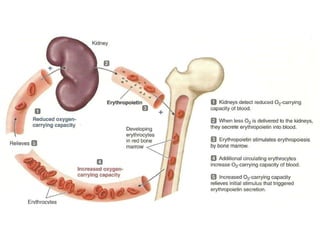
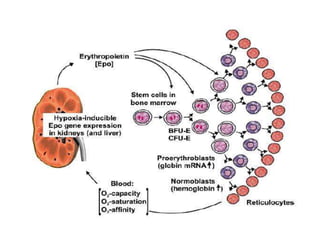
ERYTHROPOIETIN is a glycoprotein, normally
made by the kidneys, that regulates red blood cell
proliferation and differentiation in bone marrow.
(a)Stimulates proliferation of colony forming cells.
(b)Induces haemoglobin formation & erythroblast
maturation.
(c)Releases reticulocytes in the circulation.
The recombinant human erythropoietin (Epoetin α, β) is
administered 25–100 U/kg by i.v. or s.c. injection 3 times
a week.
Indication:
• Anaemia
• Chronic Renal failure
(patients with Hb ≤ 8 g/dl should be considered for EPO)
• Anaemia in AIDS patients treated with zidovudine.
• Cancer chemotherapy induced anaemia.
• Preoperative increased blood production for
autologous transfusion during surgery.
• A/E: Increased clot formation in the A-V shunts (most
patients are on dialysis), hypertensive episodes,
serious thromboembolic events, occasionally seizures
& Flu like symptoms.
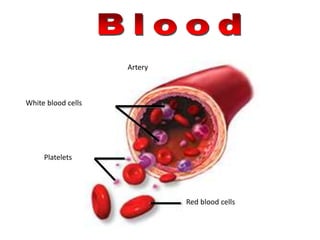
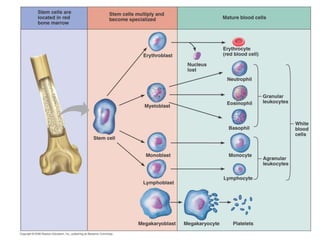
White blood cells
Platelets
Red blood cells
Artery
Stem cell
Hemocytoblast
Proerythro-
blast
Early
erythroblast
Late
erythroblast Normoblast
Phase 1
Ribosome
synthesis
Phase 2
Hemoglobin
accumulation
Phase 3
Ejection of
nucleus
Reticulo-
cyte
Erythro-
cyte
Committed
cell
Developmental pathway
THANK YOU!