Drugs for Congestive
Heart Failure
Dr Lokendra Sharma
Sr. Professor, Pharmacology
SMS Medical College, Jaipur
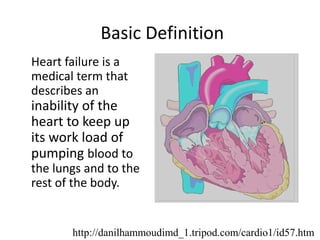
Basic Definition
Heart failure is a
medical term that
describes an
inability of the
heart to keep up
its work load of
pumping blood to
the lungs and to the
rest of the body.
http://danilhammoudimd_1.tripod.com/cardio1/id57.htm
Classification
I) Drugs with positive inotropic effects-
a) Cardiac glycosides- Digoxin, Digitoxin,
Ouabain
b) Phosphodiesterase inhibitors- Inamrinone,
Milrinone, Levosimendan
c) Beta adrenergic agonist- Dopamine,
Dobutamine, Dobuxamine
II) Drugs without positive inotropic effects-
a) Diuretics- Bumetanide, Furosemide,
Hydrochlorothiazide, Spironolactone
b) ACEIs- Enalapril, Lisinopril, Ramipril
c) Beta-1 adrenoceptor antagonist-
Bisoprolol, Carvedilol, Metoprolol
A, B, C, D, Es of Heart Failure Therapy
A Angiotensin converting enzyme inhibitors
anticoagulants, amiodarone, AICD, assist
devices
B Beta blocking drugs
C Calcium channel blocking drugs, coronary
revascularization, cardiac transplant,
cardiomyoplasty, cardiac reduction surgery
D Diet, diuretics, digitalis, dobutamine
E Exercise
CHF ClassificationNew York Heart Association
Class I - Asymptomatic
Class II - Symptomatic with moderate
exertion
Class III - Symptomatic with mild exertion
Class IV - Symptomatic with no exertion/or
at rest
CHF: Clinical Assessment
Left or right sided
History
– Left sided
• Orthopnea
• Dyspnea
– Right sided
• Anorexia
• Abdominal distension
• Ankle edema
Exam
– Left sided
• Rales
• Narrow pulse pressure
• Increasing S3
– Right sided
• Elevated JVP
• Hepato-jugular reflex
• Loud P2
CHF: Pharmacotherapy
 Relief of symptoms
Diuretics
Digoxin
 Reduction in mortality/hospitalizations
ACE Inhibitors
Beta blockers
Spironolactone
 Rescue in advanced failure
Inotropic infusions (dobutamine)
Vasodilators
Principles in selecting appropriate
medications
Reduction in
Pre-load: Diuretics
After-load: ACE Inhibitors
Filling pressures: Nitrates
Restoring perfusion
Inotropic agents
Beta adrenergic receptor agents: Dobutamine
Phosphodiesterase inhibitors: Milrinone
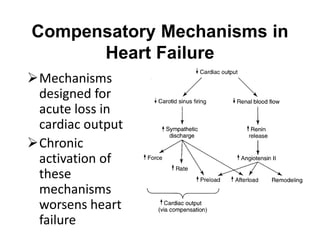
Compensatory Mechanisms in
Heart Failure
Mechanisms
designed for
acute loss in
cardiac output
Chronic
activation of
these
mechanisms
worsens heart
failure
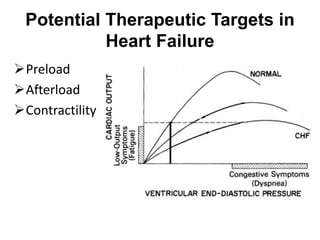
Potential Therapeutic Targets in
Heart Failure
Preload
Afterload
Contractility
Positive Inotropic Agents
Cardiac Glycosides
Phosphodiesterase inhibitors
 b-adrenoceptor agonists and
dopamine receptor agonists
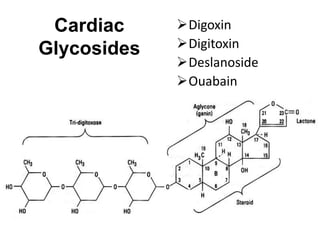
Cardiac
Glycosides
Digoxin
Digitoxin
Deslanoside
Ouabain
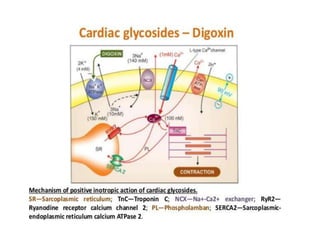
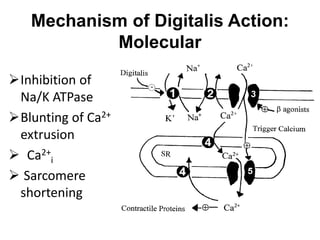
Mechanism of Digitalis Action:
Molecular
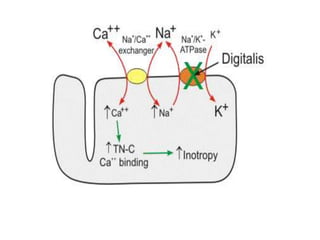
Inhibition of
Na/K ATPase
Blunting of Ca2+
extrusion
 Ca2+
i
 Sarcomere
shortening
Effects on Cardiac Function
Positive inotropy
Direct electrophysiological effects
Effects mediated through increased
vagal tone
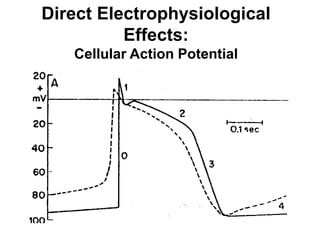
Direct Electrophysiological
Effects:
Cellular Action Potential
Summary Direct
Electrophysiological Effects
Less negative membrane potential:
decreased conduction velocity
Decreased action potential duration:
decreased refractory period in ventricles
Enhanced automaticity due to
Steeper phase 4
After depolarizations
Parasympathomimetic Effects
Decreased conduction velocity in the
AV node
increased effective refractory period
in the AV
Heart block (toxic concentrations)
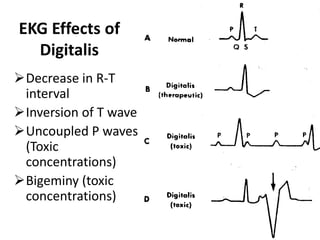
EKG Effects of
Digitalis
Decrease in R-T
interval
Inversion of T wave
Uncoupled P waves
(Toxic
concentrations)
Bigeminy (toxic
concentrations)
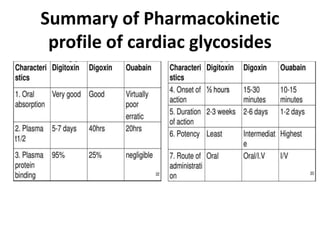
Summary of Pharmacokinetic
profile of cardiac glycosides
Therapeutic Uses of Digitalis
Congestive Heart Failure
Atrial fibrillation
Overall Benefit of Digitalis to
Myocardial Function
 cardiac output
 cardiac efficiency
  heart rate
  cardiac size
NO survival benefit
Other Beneficial Effects
Restoration of baroreceptor
sensitivity
Reduction in sympathetic activity
Increased renal perfusion, with 
edema formation
Administration
Digoxin has a long enough half life (24-36
hr.) and high enough bioavailability to allow
once daily dosing
Digoxin has a large volume of distribution
and dose must be based on lean body mass
Increased cardiac performance can increase
renal function and clearance of digoxin
Eubacterium lentum
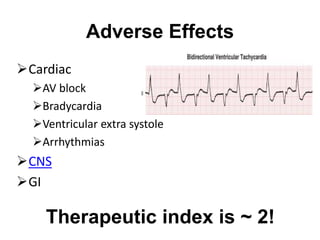
Adverse Effects
Cardiac
AV block
Bradycardia
Ventricular extra systole
Arrhythmias
CNS
GI
Therapeutic index is ~ 2!
Serum Electrolytes Affect
Toxicity
K+
Digitalis competes for K binding at Na/K ATPase
Hypokalemia: increase toxicity
Hyperkalemia: decrease toxicity
Mg2+
Hypomagnesemia: increases toxicity
Ca2+
Hypercalcemia: increases toxicity
Treatment of Digitalis Toxicity
Reduce dose: 1st degree heart block,
ectopic beats
Atropine: advanced heart block
KCl: increased automaticity
Antiarrhythmic: ventricular arrhythmias
Fab antibodies: toxic serum
concentration; acute toxicity
Phosphodiesterase
Inhibitors
 Amrinone
 Milrinone
 levosimendan
Mechanism of Action
 Inhibition of type III phosphodiesterase
 intracellular cAMP
 activation of protein kinase A
 Ca2+ entry through L type Ca2+ channels
 inhibition of Ca2+ sequestration by SR
 cardiac output
  peripheral vascular resistance
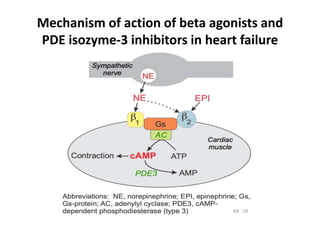
Mechanism of action of beta agonists and
PDE isozyme-3 inhibitors in heart failure
Phosphodiesterase Inhibitors:
Therapeutic Use
Short term support in
advanced cardiac failure
Long term use not possible
Adverse Effects of
Phosphodiesterase Inhibitors
Cardiac arrhythmias
GI: Nausea and vomiting
Dose dependent
thrombocytopenia
Sudden death
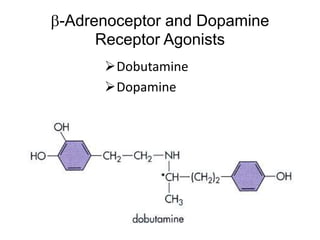
b-Adrenoceptor and Dopamine
Receptor Agonists
Dobutamine
Dopamine
Mechanism of Action: Dobutamine
Stimulation of cardiac b1-
adrenoceptors: inotropy >
chronotropy
Peripheral vasodilatation
 myocardial oxygen demand
Mechanism of Action: Dopamine
Stimulation of peripheral
postjunctional D1 and
prejunctional D2 receptors
Splanchnic and renal
vasodilatation
Therapeutic Use
Dobutamine: management of acute
failure only
Dopamine: restore renal blood in
acute failure
Dobutamine
 ß-1 receptor agonist
 Low-dose dobutamine (2-3 ug/kg/min)
 ļ‚­ myocardial contractility and cardiac output,
arteriovenous dilatation
 High-dose dobutamine (5-15 ug/kg/min)
tachycardia, arrhythmia, splanchnic and renal
vasoconstriction
associated with symptomatic benefit
 Continuous home pump infusion
 T .half life 2 minute
Adverse Effects
Dobutamine
Tolerance
Tachycardia
Dopamine
tachycardia
arrhythmias
peripheral vasoconstriction
Mechanism of Action
Afterload reduction
Preload reduction
Reduction of facilitation of
sympathetic nervous system
Reduction of cardiac
hypertrophy
ACE Inhibitors: Therapeutic
Uses
Drugs of choice in heart failure
(with diuretics)
Current investigational use:
Acute myocardial infarction
AT II antagonists
Diuretics: Mechanism of Action
in Heart Failure
Preload reduction: reduction of excess
plasma volume and edema fluid
Afterload reduction: lowered blood
pressure
Reduction of facilitation of
sympathetic nervous system
Vasodilators
Mechanism of action: reduce
preload and afterload
Drugs used
Sodium nitroprusside
Hydralazine
Ca2+ channel blockers
Prazosin
b-Blockers in Heart Failure:
Mechanism of Action
Standard b-blockers:
Reduction in damaging sympathetic
influences in the heart (tachycardia,
arrhythmias, remodeling)
inhibition of renin release
Carvedilol:
Beta blockade effects
peripheral vasodilatation via a1-
adrenoceptor blockade (carvedilol)
Spironolactone
Aldosterone antagonist, K-sparing diuretic
Prevention of aldosterone effects on:
Kidney
Heart?
Aldosterone inappropriately elevated in CHF
Mobilizes edema fluid in heart failure
Prevention of hypokalemia induced by loop
diuretics (protection against digitalis toxicity?)
Prolongs life in CHF patients
Take Home Message
Diuretics of choice in acute CHF- Loop
diuretic
Short term management of acute CHF- Inotropic
drugs
Cardiac glycosides act by inhibiting Na+ K+
ATPase
Digoxin is only inotropic drug, can be given orally
Thrombocytopenia side effect of Inamrinone
CCBs should not used in CHF – may increase
mortality
Aldosterone antagonist and beta
blocker- reduce the mortality
Widely used beta blocker- Carvedilol
Beta blockers contraindicated in
acute CHF.
Thank You