IPOP/IPSF
Immediate Post operative Prosthesis/Immediate Post-surgical fitting
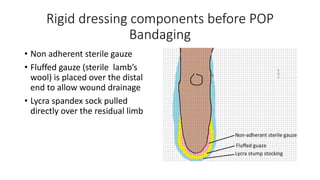
Rigid dressing components before POP
Bandaging
• Non adherent sterile gauze
• Fluffed gauze (sterile lamb’s
wool) is placed over the distal
end to allow wound drainage
• Lycra spandex sock pulled
directly over the residual limb
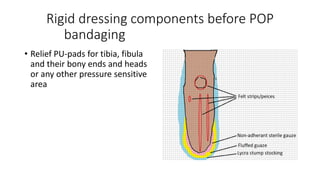
Rigid dressing components before POP
bandaging
• Relief PU-pads for tibia, fibula
and their bony ends and heads
or any other pressure sensitive
area
Rigid dressing components with POP
Bandaging
• Stump is positioned in 10 degree
of flexion
• Elastic POP plaster (ACE wrap)
• Regular plaster with stockinette
impregnated
• POP bandage incorporated
safety buckle for connection
with Waist belt
Immediate Post Operative Prosthesis
• What is an IPOP?
• Device applied before wound
closure (in case healing by
secondary intension is indicated)
or after wound closure that
protects the suture site and allows
limited weight bearing and gait
training
• Immediate Post Operative
Prosthesis applied in the
Operating Room by prosthetist
• Bridge between surgery and
definitive prosthesis
History of IPOP uses
• Immediate Post-Surgical Prosthetics by ERNEST M. BURGESS;
Orthopaedic and Prosthetic appliances Journal,1967-02-105
Application of IPOP
IPOP uses
• Lower Extremity can be custom fabricated or prefabricated
• Upper Extremity can be external power or body powered
• can be used on all levels, but best results at the tran-radial level and trans-
tibial level
Advantages
1. Most importantly, helps patient with phantom limb sensation, as they can see a
leg
2. Reduces severity of phantom limb pain
3. Positive psychological attributes of seeing leg.
4. Patient with transtibial and knee disarticulation may bear weight, using an
assistive device, 5-21days following surgery
5. Usually 20 lb or 10 kg of weight is enough for bearing on IPOP, to begin with
6. Maintenance of lower and upper limb strength, trunk balance
7. Physiological standing advantage, maintaining cardio-vascular status
8. Prevent contracture,
9. Shorter hospital stay, shorter recovery time
10. Quicker identification of patient’s activity level
Comparison between conventional post
operative management and IPOP
• Soft dressing
• Semi-rigid dressing
• Removable rigid dressing (RRD)
• Removable Semi-rigid dressing
• Rigid dressing
• IPOP
• Air Splint
Application (Air Splint)
• Non custom IPOP are available, these
are light than fiberglass or plaster,
contain air bladder which can be
inflated to accommodate the size of
residual limb.
• Its advantages are that it can be easily
removed so that wound inspection is
easy.
• Therefore non custom IPOP are very
much useful in diabetic and PVD
cases.
• “Air-splint” was originally designed for
emergency to stabilize fracture site.
Parts of Air Splint
Weight bearing frame with distal end
adopter Transfemoral Pneumatic cover
Parts of Air Splint
Pneumatic end bearing cover End bearing cushion
Air splint (application)
• Application
• Patient wears a sock on the residual limb to absorb moisture and prevent skin
maceration
• Air splint is applied and zipped to secure it arround the residual limb
• A hose is attached to pump
• A distal to proximal measured pressurization occur as the bladder is inflated
to a pressure of 25mm of hg with the pump.
• Finally the hose is disconnected
• More air is added as edema subsides
Advantage and limitation
• Advantages
• Easy inspection of incision site
• Provision for drainage
• Provision for uniform pressure distribution
• Ease of use and removal
• Usually applied 2-10 days after amputation
• Partial bearing is possible with air splint, which helps in balance training
• Continuous support and protection
• Reduces occurance of hematoma
• Limitation
• Build up of heat in warm climate
• Difficult weight bearing
Silicone liner
• Its applied by inverting and than rolling it over the residual limb and
hence less traumatic
• Disadvantages are that its not good for weight bearing and build-up
of heat
Thank you