MINIMAL CHANGE DISEASE
MINIMAL CHANGE  DISEASE background also known as lipoid nephrosis or  nil disease is the most common single form of nephrotic  syndrome in children It refers to a histopathologic lesion in  the glomerulus that almost always is associated with nephrotic  syndrome. It typically is a disease of childhood, but it also  can occur in adults.
MINIMAL CHANGE  DISEASE PATHOPHYSIOLOGY It is postulated that MCD is a disorder of T cells, which  release a cytokine that injures the glomerular epithelial foot  processes.  This, in turn, leads to a decreased synthesis of  polyanions.  polyanions constitute the normal charge barrier  to the filtration of macromolecules, such as albumin.  When the  polyanions are damaged, leakage of albumin follows.
MINIMAL CHANGE  DISEASE PATHOPHYSIOLOGY Some of the cytokines that have been studied in MCD are  interleukin-12 (IL-12) and interleukin-4 (IL-4).   IL-12 levels  have been found to be elevated in peripheral blood monocytes  during the active phase and normalized during remission.  Interleukin-18 (IL-18) can synergize with IL-12 to selectively  increase the production of vascular permeability factor from T  cells.
MINIMAL CHANGE  DISEASE PATHOPHYSIOLOGY Synaptopodin is a proline-rich protein intimately associated  with actin microfilaments present in the foot processes of  podocytes.  Greater synaptopodin expression in podocytes is  associated with a significantly better response to steroid  therapy.  this marker could be used in the future to help determine  appropriate therapy
MINIMAL CHANGE  DISEASE PATHOPHYSIOLOGY Interleukin-13 (IL-13) has been implicated in the pathogenesis of MCD.  In a study on Chinese children in Singapore, it was  shown that IL-13 genetic polymorphisms correlate with the  long-term outcome of MCD.  An animal study by Lai suggested  that IL-13 overexpression can cause podocyte foot process fusion and proteinuria.
MINIMAL CHANGE  DISEASE PATHOPHYSIOLOGY In patients who develop acute renal failure, endothelin 1  expression is greater in the glomeruli, vessels, and tubules  than in the nonacute renal failure group.  The glomerular  epithelial cells (podocytes) and the slit diaphragm connecting  the podocyte foot processes play a primary role in the  development of proteinuria. Although a multitude of studies have been published, the  mechanism by which T cells increase glomerular permeability has  remained unproven .
MINIMAL CHANGE  DISEASE COMPLICATIONS Hypovolemic shock is perhaps the most serious complication of  MCD.  Hypovolemic shock typically occurs during the edema-forming  phase of relapse and may be precipitated by diarrhea, sepsis,  drainage of ascitic fluid, or the use of diuretics. Hypertension, somewhat paradoxically, also may occur in  approximately 9-14% of children.  Hypertension occurs in  approximately 30% of adults, with a greater incidence in older  patients (>60 y).
MINIMAL CHANGE  DISEASE COMPLICATIONS Thromboembolic events are serious complications of nephrotic  syndrome.  Peripheral thrombosis may result in gangrene, and deep  venous thrombosis in the legs or pelvic veins may be a source of  pulmonary emboli.  Bacterial infections, especially peritonitis,  occur with greater frequency, partly because of the loss of  immunoglobulin G (IgG) and complement factors B and D in the  urine.  In fact, the largest reduction in mortality in these  patients follows the introduction of antibiotics rather than any  specific therapy.
MINIMAL CHANGE  DISEASE SUSCEPTIBILITY Race  = Asians may be at increased risk. Sex  = It is found twice as frequently in boys than in girls; The frequency is the same between the sexes in adults. Age  = The incidence peaks in children aged 2 years, with  approximately 80% being younger than 6 years at the time of  diagnosis; In adults, the mean age of onset is 40 years.
MINIMAL CHANGE  DISEASE CLINICAL SIGNS Edema  may be preceded by an upper respiratory tract infection,  an allergic reaction to a bee sting, or the use of certain drugs  or malignancies. Facial edema  is noted first. Malaise  and  easy fatigability  can occur. Weight gain  often is an additional feature. The patient also may present with the following: Hypovolemia, Hypertension, Thromboembolism, Infection
MINIMAL CHANGE  DISEASE PHYSICAL SIGNS The blood pressure usually is normal in children but may be  elevated in adults. (In addition, the  plasma creatinine  in  adults is often slightly elevated at presentation.) Dependent edema  is the most prominent sign.  The  retina  has a  wet appearance.  Subungual edema with horizontal lines (called  Muehrcke lines ) also may occur. Hernias  may be found, and the elasticity of the  ears  may be  decreased.
MINIMAL CHANGE  DISEASE PHYSICAL SIGNS Heavy proteinuria  over an extended period of time leads to a  state of protein depletion with muscle wasting, thinning of the  skin, and growth failure. Pleural and ascitic fluid can accumulate. Rarely,  cellulitis,  peritonitis, or pneumonia  may be the first indication of an  underlying nephrotic syndrome. Children may have  growth failure .
MINIMAL CHANGE  DISEASE DIFFERENTIAL  DIAGNOSES Other Problems to Be Considered C1q nephropathy Focal segmental glomerulosclerosis Immunoglobulin M (IgM) nephropathy Membranous nephropathy Other variables
MINIMAL CHANGE  DISEASE LABORATORY  STUDIES Urine analysis  is benign, but profound proteinuria and oval fat  bodies may be observed. A random  albumin-to-creatinine concentration  ratio is in excess  of 5. Urine   specific gravity  is high because of proteinuria. A  24-hour urine measurement  is obtained for protein and  creatinine clearance. Hypoalbuminemia  is an important marker of nephrotic syndrome.  The level at which edema occurs varies, but it tends to be lower  in children than in adults. Nephrotic syndrome in children is  defined by a serum albumin of less than 2.5 g / dL.
MINIMAL CHANGE  DISEASE LABORATORY  STUDIES Hyperlipidemia  also is a feature of a nephrotic state  Serologic workup  (including antinuclear antibodies,  complements, and cryoglobulins) is normal. Hyponatremia  often is observed, which is, in part, a spurious  finding secondary to the hyperlipidemic state. This condition  also occurs from water retention caused by hypovolemia and  antidiuretic hormone release. Elevated hemoglobin and hematocrit  are consequences of plasma  volume contraction.
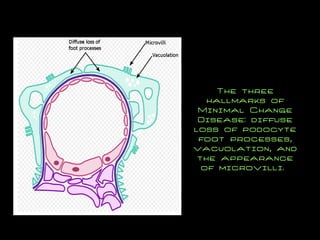
MINIMAL CHANGE  DISEASE HISTOLOGICAL  FINDINGS Electron microscopy:  Retraction of the epithelial foot processes  is observed consistently in patients with MCD. This is, at  times, erroneously described as foot-process fusion and results  from disordered epithelial cell structure with withdrawal of the  dendritic process.  This finding is not unique to MCD, and the  diagnosis is one of exclusion of other diseases based on lack of  other processes on light microscopy, immunohistology, or  electron microscopy
MINIMAL CHANGE  DISEASE TREATMENT Corticosteroids  are the treatment of choice, leading to complete  remission of proteinuria in most cases.  If patients are  steroid-resistant or they relapse frequently, a trial of  immunosuppressants is given ( cyclophosphamide and  chlorambucil ) These drugs expose the patient to a wide range of  serious adverse effects that include life-threatening  infections, gonadal dysfunction, bone marrow dysfunction, and,  in the case of chlorambucil, increased risk of leukemia.  Mycophenolate mofetil (MMF)  has been shown in limited studies to  be beneficial to patients who are steroid-dependent or with  frequent remissions
MINIMAL CHANGE  DISEASE TREATMENT Angiotensin   converting enzyme inhibitors  and  angiotensin II  receptor blockers , alone or in combination should be used with a  goal of reducing the proteinuria  Hypovolemia: purified  plasma protein fraction  isotonic sodium chloride solution albumin infusion (not appropriate) Edema dietary sodium  restriction  use of diuretics
MINIMAL CHANGE  DISEASE TREATMENT Thrombotic episodes   Mobilization meticulous attention to venipuncture  intravenous infusion sites  heparinization  Infections administration of penicillin prophylaxis  corticosteroids increase the problem of infection.
MINIMAL CHANGE  DISEASE TREATMENT Diuretics These agents control volume overload. Furosemide (Lasix)=  Has potent diuretic effects by blocking the sodium reabsorption  in the thick ascending limb of the loop of Henle Corticosteroids For remission of proteinuria. Antineoplastic agents For remission of nephrotic syndrome.
MINIMAL CHANGE  DISEASE TREATMENT Diuretics These agents control volume overload. Furosemide (Lasix)=  Has potent diuretic effects by blocking the sodium reabsorption  in the thick ascending limb of the loop of Henle Corticosteroids For remission of proteinuria. Antineoplastic agents For remission of nephrotic syndrome. Cyclophosphamide (Cytoxan, Neosar) =  Interferes with normal function of DNA by alkylation and  cross-linking strands of DNA and by possible protein  modification.
MINIMAL CHANGE  DISEASE TREATMENT Immunosuppressant agents For remission of nephrotic syndrome. Cyclosporine A (Sandimmune, Neoral)  = Inhibits production and release of IL-2, leading to inhibition  of IL-2–mediated activation of T lymphocytes. Chlorambucil (Leukeran) =  To induce remission of proteinuria. Interferes with DNA  replication and RNA transcription.
MINIMAL CHANGE  DISEASE TREATMENT Immunomodulators To induce remission of nephrotic syndrome. Levamisole (Ergamisol)  = Stimulates formation of antibodies and enhances T-cell  responses. Acts as a biochemical modulator of fluorouracil Mycophenolate mofetil (CellCept)=  Inhibitor of de novo purine pathway with preferential inhibitory  effects on T and B lymphocyte proliferation, has been used to  treat steroid-dependent nephrotic syndrome.
 
BEFORE AND AFTER
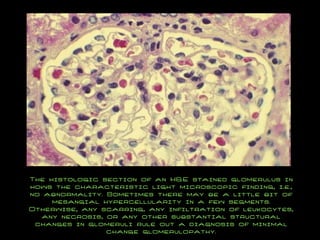
The histologic section of an H&E stained glomerulus in hows the characteristic light microscopic finding, i.e., no abnormality. Sometimes there may be a little bit of mesangial hypercellularity in a few segments. Otherwise, any scarring, any infiltration of leukocytes, any necrosis, or any other substantial structural changes in glomeruli rule out a diagnosis of minimal change glomerulopathy.
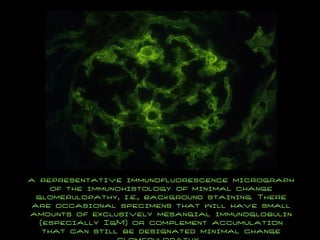
a representative immunofluorescence micrograph of the immunohistology of minimal change glomerulopathy, i.e., background staining. There are occasional specimens that will have small amounts of exclusively mesangial immunoglobulin (especially IgM) or complement accumulation that can still be designated minimal change glomerulopathy.
The three hallmarks of Minimal Change Disease: diffuse loss of podocyte foot processes, vacuolation, and the appearance of microvilli.
MINIMAL CHANGE DISEASE