Prepared by- Shagufta Farooqui
Department of Pharmacology
Nanded Pharmacy, College, Nanded.
“Fight or Flight”
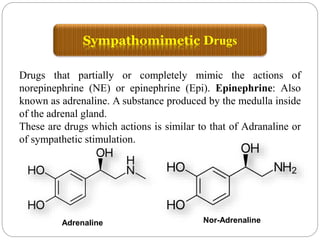
Drugs that partially or completely mimic the actions of
norepinephrine (NE) or epinephrine (Epi). Epinephrine: Also
known as adrenaline. A substance produced by the medulla inside
of the adrenal gland.
These are drugs which actions is similar to that of Adranaline or
of sympathetic stimulation.
Sympathomimetic Drugs
Adrenaline Nor-Adrenaline
ADRENERGIC TRANSMISSION
Adrenergic (more precisely ‘Noradrenergic’) transmission is
restricted to the sympathetic division of the ANS. There are three
closely related endogenous catecholamines (CAs).
Noradrenaline (NA) It acts as transmitter at postganglionic
sympathetic sites (except sweat glands, hair follicles and some
vasodilator fibres) and in certain areas of brain.
Adrenaline (Adr) It is secreted by adrenal medulla and may have a
transmitter role in the brain.
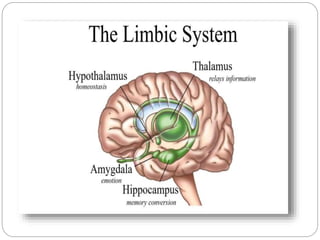
Dopamine (DA) It is a major transmitter in basal ganglia, limbic
system, CTZ, anterior pituitary, etc. and in a limited manner in the
periphery.
1.Synthesis of Norepinephrine :
It begins with the amino acid tyrosine, which enters the neuron by
active transport, perhaps facilitated by a permease.
In the neuronal cytosol, tyrosine is converted by the enzyme tyrosine
hydroxylase to dihydroxyphenylalanine (dopa), which is converted to
dopamine by the enzyme aromatic L-amino acid decarboxylase,
sometimes termed dopa-decarboxylase.
2.Storage norepinephrine in vesicles:
The dopamine is actively transported into storage vesicles, where it is
converted to norepi-nephrine (the transmitter) by dopamine 3
hydroxylase, an enzyme within the storage vesicle. In noradrenergic
neurons, the end product is norepi-nephrine.
In the adrenal medulla, the synthesis is carried one step further by the
enzyme phenylethanolamine N-methyltransferase, which
converts norepinephrine to epinephrine.
3.Release of Norepinephrine:
An action potential arriving at the nerve junction triggers an
influx of calcium ions from the extracellular fluid into the
cytoplasm of the neuron.
The increase in calcium causes vesicles inside the neuron to
fuse with the cell membrane and expel (exocytose) their
contents into the synapse.
This release is blocked by drugs such as guanethidine.
4.Action on Post synaptic receptor: Nor epinephrine
from the synaptic vesicles the sympathetic system diffuses
across the synaptic space and binds to either postsynaptic
receptors on the effecte organ or to presynaptic receptors on
the nerve ending.
Receptors may be divided into alpha (a), beta (B),
and dopamine (D) receptors.
Drugs that bind to these receptors and modulate or mimic
the function of the sympathetic nervous system may be
divided into those which augment the system
(sympathomimetics) and those which antagonize the system
(sympatholytics).
5.Removal of norepinephrine:
The nor epinephrine may-
(1) diffuse out of the synaptic space and enter the general
circulation .
(2) be metabolized to O-methylated derivatives by
postsynaptic cell membrane-associated catechol O-
methyltransferase (COMT) in the synaptic space, or
(3) be recaptured by an uptake system that pumps the nor
epinephrine back into the neuron.
6.Potential fates of recaptured norepinephrine:
Once norepinephrine reenters the cytoplasm of the
adrenergic neuron, it may be taken up into adrenergic
vesicles via the amine transporter system and be sequestered
for release by another action potential, or it may persist in a
protected pool.
Alternatively, norepinephrine can be oxidized by
monoamine oxidase (MAO) present in neuronal
mitochondria.
The inactive products of norepinephrine metabolism are
excreted in the urine as vanillylmandelic acid, metanephrine,
and normetanephrine.
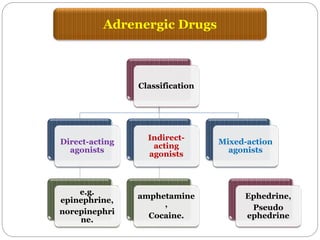
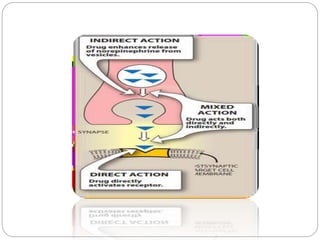
Classification
Direct-acting
agonists
e.g.
epinephrine,
norepinephri
ne.
Indirect-
acting
agonists
amphetamine
,
Cocaine.
Mixed-action
agonists
Ephedrine,
Pseudo
ephedrine
Adrenergic Drugs
THERAPEUTIC CLASSIFICATION OF
ADRENERGIC DRUGS
I. Pressor agents
Noradrenaline,Phenylephrine,EphedrineMethoxamine,
Dopamine Mephentermine
II. Cardiac stimulants
Adrenaline Dobutamine ,Isoprenaline
III. Bronchodilators
Isoprenaline Salmeterol, Salbutamol Formoterol,(Albuterol)
Bambuterol, Terbutalin
IV. Nasal decongestants
Phenylephrine,Naphazoline,XylometazolinePseudoephedrine
,
Oxymetazoline Phenylpropanolamine
V. CNS stimulants
Amphetamine Methamphetamine, Dexamphetamine
VI. Anorectics
Fenfluramine ,Sibutramine ,Dexfenfluramine
VII. Uterine relaxant and vasodilators
Ritodrine, Salbutamol, Isoxsuprine Terbutaline
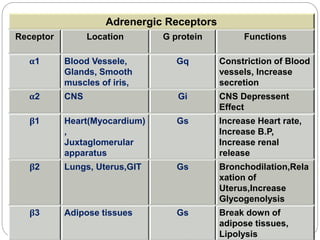
Adrenergic Receptors
Receptor Location G protein Functions
α1 Blood Vessele,
Glands, Smooth
muscles of iris,
Gq Constriction of Blood
vessels, Increase
secretion
α2 CNS Gi CNS Depressent
Effect
β1 Heart(Myocardium)
,
Juxtaglomerular
apparatus
Gs Increase Heart rate,
Increase B.P,
Increase renal
release
β2 Lungs, Uterus,GIT Gs Bronchodilation,Rela
xation of
Uterus,Increase
Glycogenolysis
β3 Adipose tissues Gs Break down of
adipose tissues,
Lipolysis
Epinephrine Pharmacological
Action
Heart:
The direct β1 receptor mediated actions of epinephrine are positive
chronotropic ( heart rate) and ionotropic ( force of contraction) effect
on the heart, increased cardiac output, myocadical contractility,
coronary blood flow and so oxygen consumption by heart.
The conduction velocity through A-V node, bundle of His, parkinje
fibres, atrias and ventricular fibres is increased by epinephrine to
cause the above responses. Epi→ B1 receptor → Gs → Ad. cycl. →
cAMP → PKA - Ca-channels open →[Ca++ Ca calmodulin
complex-MLCK → Phosphorylation of MLC Contraction of
myocardial
fibre.
Blood Vessels:
Both vasoconstriction (α) and vasodilatation (β2) can occur
depending on the drug, its dose and vascular bed. Epinephrine mainly
acts on small arterioles and precapillary sphincters. It also exerts its
action, to some extent, on veins and large arteries.
It causes constriction of cutaneous, renal, pulmonary, arterial and
venous, and other visceral blood vessels because of the presence of
predominant a receptors.
It dilates blood vessels of skeletal muscles (at low doses), coronary
and liver which is mediated by powerful B2 receptors.
At higher dose, it causes vasoconstriction in skeletal muscle.
Blood Pressure:
The effect depends on the amine, its dose and rate of administration.
At lower concentration slow iv infusion or S.C. injection of
epinephrine causes fall in peripheral resistance because vascular
Bereceptors are more sensitive than receptors.
At High dose or rapid i.v. infusion produces marked increase in
systolic as well as diastolic B.P. (as the number of a receptors are
more than β2 receptors in blood vessels), which is followed by a fall
in the mean B.P. (because when the epinephrine concentration is
reduced by degradation, rest of the amount remain attached on more
sensitive B2 receptors).
This is called as biphasic response of epinephrine on blood pressure.
Smooth Muscle:
The GIT of smooth muscle is relaxed by epinephrine. This effect is
mediated by both a and B2 receptors on effectors cells and a
receptors on the membrane of para sympathetic nerve endings.
The α1 receptor activation causes increase in K+ efflux and thereby
hyperpolarization of the muscle cell.
B2 receptor activation increases cytosolic concentration of CAMP.
Stimulation of presynaptic a receptors renders inhibition of release
of excitatory neurotransmitter Ach from intramural nerve.
These three response combined cause relaxation of GIT smooth
muscles.
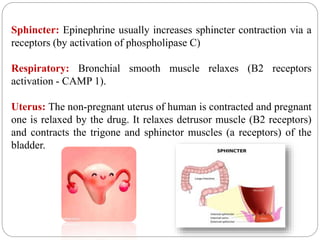
Sphincter: Epinephrine usually increases sphincter contraction via a
receptors (by activation of phospholipase C)
Respiratory: Bronchial smooth muscle relaxes (B2 receptors
activation - CAMP 1).
Uterus: The non-pregnant uterus of human is contracted and pregnant
one is relaxed by the drug. It relaxes detrusor muscle (B2 receptors)
and contracts the trigone and sphinctor muscles (a receptors) of the
bladder.
Metabolism: It stimulates glycogenolysis (P2 mediated) in liver
and muscle, causes inhibition of insulin secretion (a mediated)
and increases free fatty acids in blood (B1 mediated activation of
triglyceride lipase breakdown of triglycerides into free fatty acids
and glycerol)
Eye: Mydriasis occurs due to contraction of radial muscles (a;
receptors) of iris by epinephrine. The intraoccular pressure falls,
specially in wide angle glaucoma, due to relaxation of ciliary
muscle (B2 receptors).
Skeletal Muscle:
It does not directly excite skeletal muscle but facilitates
neuromuscular transmission through the activation of a and B2
receptors of somatic Motor neurons releasing Ach rapidly.
The twitch tension of white muscle (fast contracting fibres) is
increased.
Whereas that of red muscle (slow fibres) is reduced. Other B2
agonists (e.g. salbutamol) may also act similarly.
CNS:
Being polar compound, epinephrine cannot enter into the CNS
but restlessness, apprehension, headache and tremor may occur
due to its secondary to some peripheral effects on CNS, skeletal
muscles, and intermediary metabolism
GIT :
In isolated preparations of gut, relaxation occurs through
activation of both α and β receptors.
In intact animals and man peristalsis is reduced and sphincters are
constricted, but the effects are brief and of no clinical import.
NOREPINEPHRINE (LEVARTERENOL):
It is also found in plants and is used pharmacologically as a
sympathomimetic.
It is a precursor of epinephrine that is secreted by the adrenal medulla
and is a widespread central and autonomic neurotransmitter.
It is the principal transmitter of most postganglionic sympathetic fibers
and of the diffuse projection system in the brain arising from the locus
ceruleus.
Mechanism of action: It acts on both alpha-1 and alpha-2 adrenergic
receptors to cause vasoconstriction.
It functions as a peripheral vasoconstrictor by acting on alpha-adrenergic
receptors.
It is also an inotropic stimulator of the heart and dilator of coronary
arteries as a result of it's activity at the beta-adrenergic receptors.
Dopamine (DA):
It is a dopaminergic (D1 and D2) as well as adrenergic α
and β1 (but not β2) agonist.
The D1 receptors in renal and mesenteric blood vessels are
the most sensitive: i.v. infusion of low dose of DA dilates these
vessels (by raising intracellular cAMP).
This increases g.f.r. In addition DA exerts natriuretic effect by
D1 receptors on proximal tubular cells. Moderately high doses
produce a positive inotropic (direct β1 and D1 action + that
due to NA release), but little chronotropic effect on heart.
Vasoconstriction (α1 action) occurs only when large doses are
infused.
At doses normally employed, it raises cardiacoutput and
systolic BP with little effect on diastolic BP.
It has practically no effect on nonvascular α and β
receptors; does not penetrate blood-brain barrier—no CNS
effects.
Dopamine is used in patients of cardiogenic or septic shock
and severe CHF wherein it increases BP and urine outflow.
It is administered by i.v. infusion (0.2–1 mg/min) which is
regulated
by monitoring BP and rate of urine formation.
Dobutamine:
A derivative of DA, but not a D1 or D2 receptor agonist.
Though it acts on both α and β adrenergic receptors, the only
prominent action of clinically employed doses (2–8 μg/kg/ min i.v.
infusion) is increased force of cardiac contraction and output,
without significant change in heart rate, peripheral resistance and
BP.
As such, it is considered to be a relatively selective β1 agonist.
It is used as an inotropic agent in pump failure accompanying
myocardial infarction, cardiac surgery, and for short term
management of severe congestive heart failure.
It is less arrhythmogenic than Adr.
Ephedrine
It is an alkaloid obtained from Ephedra vulgaris. Mainly acts
indirectly but has some direct action as well on α and β receptors.
Repeated injections produce tachyphylaxis, primarily because the
neuronal pool of NA available for displacement is small.
It is resistant to MAO, therefore, effective orally.
It is about 100 times less potent than Adr, but longer acting (4–6
hours).
Ephedrine crosses to brain and causes stimulation, but central:
peripheral activity ratio is lower than that of amphetamine.
Ephedrine can be used for a variety of purposes, but it lacks
selectivity, and efficacy is low.
Use is now restricted to that in mild chronic bronchial asthma and
for hypotension during spinal anaesthesia; occasionally for
postural hypotension; 15–60 mg TDS.
Amphetamines
These are synthetic compounds having a pharmacological
profile similar to ephedrine; orally active with relatively
long duration (4–6 hours).
They exert potent CNS stimulant and weaker peripheral
cardiovascular actions.
Maximal selectivity is exhibited by dextroamphetamine
and methamphetamine, which in the usual doses produce
few peripheral effects.
The central actions of amphetamines are largely mediated
by release of NA from adrenergic neurones in the brain.
Phenylephrine It is a selective α1 agonist, has
negligible β action. It raises BP by causing
vasoconstriction. Because it has little cardiac action,
reflex bradycardia is prominent.
Topically it is used as a nasal decongestant and in the
eye for producing mydriasis when cycloplegia is not
required. Phenylephrine tends to reduce intraocular
tension by constricting ciliary body blood vessels.
It is also a frequent constituent of orally
administered nasal decongestant preparations.
NASAL DECONGESTANTS
These are α agonists which on topical applicationas dilute solution
(0.05–0.1%) produce local
vasoconstriction. The imidazoline compounds— naphazoline,
xylometazoline and oxymetazoline are relatively selective α2
agonist (like clonidine).
They have a longer duration of action (12 hours) than ephedrine.
After-congestion is claimed to be less than that with ephedrine or
phenylephrine. They may cause initial stinging sensation
(specially naphazoline). Regular use of these agents for long
periods should be avoided because mucosal ciliary function is
impaired: atrophic rhinitis and anosmia can occur due to persistent
vasoconstriction. They can be absorbed from the nose and
produce systemic effects, mainly CNS
depression and rise in BP. These drugs should be used cautiously
in hypertensives and in those receiving MAO inhibitors.
Pseudophedrine A stereoisomer of ephedrine;
causes vasoconstriction, especially in mucosae and skin, but has
fewer CNS and cardiac effect and is a poor bronchodilator (little
β2 agonistic
activity).
It has been used orally as a decongestant of upper respiratory
tract, nose and eustachian tubes. Combined with antihistaminics,
mucolytics, antitussives and analgesics, it is believed to afford
symptomatic relief in common cold, allergic rhinitis, blocked
eustachian tubes and upper respiratory tract infections.
However, no selective action on these vascular beds has been
demonstrated; rise in BP can occur, especially in hypertensives.
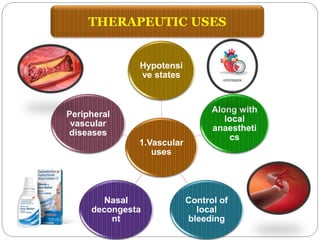
THERAPEUTIC USES
1.Vascular
uses
Hypotensi
ve states
Along with
local
anaestheti
cs
Control of
local
bleeding
Nasal
decongesta
nt
Peripheral
vascular
diseases
2.Cardiac
uses
Cardiac
arrest
Partial or
complete A-
V block
Congestive
heart failure
(CHF)
3. Bronchial asthma and
COPD
4. Allergic disorders
5. Mydriatic
6. Uterine relaxant
7. Insulin hypoglycaemia
8. Nocturnal enuresis
inchildren
Central
uses
Attention
deficit
hyperkinetic
disorder
(ADHD):
Narcolepsy
Epilepsy
Obesity
ADVERSE EFFECTS AND CONTRAINDICATIONS
Transient restlessness, headache, palpitation, anxiety, tremor and
pallor may occur after s.c./ i.m. injection of Adrenaline.
Marked rise in BP leading to cerebral haemorrhage, ventricular
tachycardia/ fibrillation, angina, myocardial infarction are the
hazards of large doses or inadvertent i.v. injection of Adrenaline.
Adrenaline is contraindicated in hypertensive, hyperthyroid and
angina patients.
Adrenaline should not be given during anesthesia with halothane
(risk of arrhythmias) and to patients receiving β blockers (marked
rise in BP can occur due to unopposed α action).
Sympathomimetic Drugs