





























Domina Petric, MD
Potassium-sparing diuretics
Introduction
• Potassium-sparing diuretics prevent
potassium secretion by antagonizing the
effects of aldosterone in collecting tubules.
Inhibition may occur by:
• direct pharmacologic antagonism of
mineralocorticoid receptors
(spironolactone, eplerenone)
• inhibition of sodium influx through ion
channels in the luminal membrane
(amiloride, triamterene)
Pharmacokinetics
Spironolactone is a synthetic steroid that
acts as competitive antagonist to
aldosterone.
Substantial inactivation of spironolactone
occurs in the liver.
It has slow onset of action, requiring
several days before full therapeutic effect
is achieved.
Pharmacokinetics
• Eplerenone is a spironolactone
analog with much greater
selectivity for the mineralocorticoid
receptor.
• It is several hundredfold less active
on androgen and progesterone
receptors than spironolactone:
fewer adverse effects.
Pharmacokinetics
• Amiloride and triamterene are
direct inhibitors of sodium influx in
the cortical collecting tubule (CCT).
• Triamterene is metabolized in the
liver.
• Renal excretion is a major route of
elimination for the active form of
triamterene and the metabolites.
Pharmacokinetics
Triamterene is extensively
metabolized and it has shorter
half-life.
It must be given more
frequently than amiloride,
which is not metabolized.
Pharmacodynamics
• Potassium-sparing diuretics reduce
sodium absorption in the collecting
tubules and ducts.
• Potassium absorption and secretion
at this site is regulated by
aldosterone.
• Aldosterone antagonists interfere
with this process.
Pharmacodynamics
• Spironolactone and eplerenone bind
to mineralocorticoid receptors and
blunt aldosterone activity.
• Amiloride and triamterene do not
block aldosterone.
• They directly interfere with sodium
entry through the epithelial Na+
channels (ENaC) in the apical
membrane of the collecting tubule.
Pharmacodynamics
Potassium secretion is
coupled with sodium
entry in the collecting
tubule: potassium-
sparing effect.
Pharmacodynamics
The actions of the aldosterone
antagonists depend on renal
prostaglandin production.
The actions of potassium-
sparing diuretics can be
inhibited by NSAIDs.
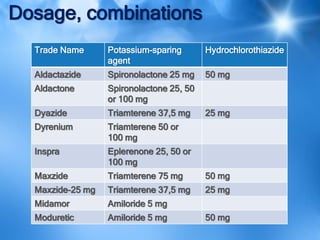
Dosage, combinations
Trade Name Potassium-sparing
agent
Hydrochlorothiazide
Aldactazide Spironolactone 25 mg 50 mg
Aldactone Spironolactone 25, 50
or 100 mg
Dyazide Triamterene 37,5 mg 25 mg
Dyrenium Triamterene 50 or
100 mg
Inspra Eplerenone 25, 50 or
100 mg
Maxzide Triamterene 75 mg 50 mg
Maxzide-25 mg Triamterene 37,5 mg 25 mg
Midamor Amiloride 5 mg
Moduretic Amiloride 5 mg 50 mg
Clinical indications
States of mineralocorticoid excess or
hyperaldosteronism (aldosteronism):
• PRIMARY hypersecretion: Conn´s
syndrome, ectopic
adrenocorticotropic hormone
production
• SECONDARY hyperaldosteronism:
evoked by heart failure, hepatic
cirrhosis, nephrotic syndrome
Clinical indications
• Thiazides and loop agents can cause
or exacerbate volume contraction
and may cause secondary
hyperaldosteronism.
• These agents also cause potassium
wasting.
• Potassium-sparing diuretics blunt the
potassium secretory response.
Clinical indications
• Eplerenone 25-50 mg/day may
interfere with some of the fibrotic and
inflammatory effects of aldosterone.
• It can slow progression of
albuminuria in diabetic patients.
• Eplerenone can reduce myocardial
perfusion defects after myocardial
infarction.
Clinical indications
Eplerenone can also
reduce mortality rates in
patients with mild to
moderate heart failure
after myocardial infarction.
Toxicity
Hyperkalemia
Hyperchloremic metabolic acidosis
Gynecomastia
Acute renal failure
Kidney stones
Hyperkalemia
These agents reduce urinary
excretion of potassium.
They can cause mild,
moderate or even life-
threatening hyperkalemia.
Hyperkalemia
The risk is increased by:
• renal disease
• use of other drugs that reduce or
inhibit renine (β blockers,
NSAIDs, aliskiren)
• use of drugs that reduce
angiotensin II activity (ACE-
inhibtors, angiotensin receptor
inhibitors).
Hyperkalemia
• With fixed-dosage combinations of
potassium-sparing and thiazide
diuretics, the thiazide-induced
hypokalemia and metabolic alkalosis
are ameliorated.
• It is preferable to adjust the doses of
the two drugs separately because
thiazide-associated adverse effects
predominate in fixed combinations.
Hyperchloremic metabolic acidosis
Potassium sparing diuretics
cause acidosis similar to
acidosis in type IV renal
tubular acidosis by inhibiting
hydrogen ions secretion in
parallel with potassium
secretion.
Gynecomastia
Acute renal failure
Triamterene and
indomethacin
combination has been
reported to cause acute
renal failure.
Kindey stones
Contraindications
• Potassium-sparing agents can
cause severe, even fatal,
hyperkalemia in susceptible
patients.
• Patients with chronic renal
insufficiency are especially
vulnerable.
Contraindications
• Patients with liver disease may have
impaired metabolism of triamterene
and spironolactone.
• Strong CYP3A4 inhibitors can
increase blood levels of eplerenone:
erythromycin, fluconazole, diltiazem,
grapefruit juice.
LOOP AGENTS AND
THIAZIDES COMBINATIONS
Loop agents and thiazides
• Some patients are refractory to the
usual dose of loop diuretics or
become refractory after an inital
response.
• These agents have a short half-life
(2-6 hours).
• Refractoriness may be due to an
excessive interval between doses.
Loop agents and thiazides
• Renal sodium retention may be greatly
increased during the time period when
the drug is no longer active.
• After the dosing interval for loop
agents is minimized or the dose is
maximized, the use of two drugs
acting at different nephron sites may
exhibit synergy.
Loop agents and thiazides
• Salt reabsorption in either the
thick ascending limb (TAL) or the
distal convoluted tubule (DCT)
can increase when the other
segment is blocked.
• Inhibition of both can produce
additive diuretic response.
Loop agents and thiazides
• Thiazide diuretics often produce a
mild natriuresis in the proximal tubule
that is usually masked by increased
reabsorption in the TAL.
• The combination blocks sodium
reabsorption from all three segments.
• Combination can mobilize large
amounts of fluid.
Loop agents and thiazides
• Close hemodynamic
monitoring of the patients
on combination is
necessary, as well as
careful monitoring of fluid
and electrolyte status,
especially potassium.
Literature
• Katzung, Masters, Trevor.
Basic and clinical
pharmacology.