Management ofManagement of
MenopauseMenopause
Dr Yusmadi Abdullah
Life After MenopauseLife After Menopause
 Age at menopause : 51.7 (average)
 1900 : life expectancy at 40 years old
 1950 : life expectancy at 65 years old
 2000 : life expectancy at 83 years old
(Malaysian women - 75.4 years)
“Women now live
a third of their lives
after menopause”
8th International Congress on Menopause, Sydney 1996
MenopauseMenopause
 MenopauseMenopause is the permanentis the permanent
cessation of menstruation thatcessation of menstruation that
results from loss of ovarian follicularresults from loss of ovarian follicular
activity.activity.
 Menopausal age :Menopausal age : 45 – 55 years45 – 55 years
 Mean age ( M )Mean age ( M ) :: 50.7 years50.7 years
 Premature menopausePremature menopause < 45< 45
yearsyears
 Late menopauseLate menopause > 55 years> 55 years
 is the cessation of menstruationis the cessation of menstruation
that follows surgical removal ofthat follows surgical removal of
both ovaries orboth ovaries or iatrogenic ablationiatrogenic ablation
of ovarian functionof ovarian function byby
chemotherapy, radiotherapy orchemotherapy, radiotherapy or
treatment with GnRH analogues.treatment with GnRH analogues.
Induced /surgical menopauseInduced /surgical menopause
PerimenopausePerimenopause
 Is the period beginnning with the first
clinical, biological and endocrinological
features of the approaching
menopause such as vasomotor
symptoms and menstrual irregularity
 Can be 1 or 2 years and for some as
long as 7 to 10 year
DiagnosisDiagnosis
 For those 50 years and above :For those 50 years and above :
12 consecutive month of12 consecutive month of
amenorrhoea is diagnostic.amenorrhoea is diagnostic.

 For those below 50 years :For those below 50 years :
** FSHFSH > 30 IU/l> 30 IU/l
Consequences of menapauseConsequences of menapause
 Vasomotor
symptoms
 Psychological
symptoms
 Sexual dysfunction
 Osteoporosis
 Cardiovascular
Disease
 Urogenital Atrophy
Vasomotor SymptomsVasomotor Symptoms
 Hot flushes and night sweats are
experienced by as many as 85% of
women around the menopause.
 Most would experience these symptoms
for < 5 years, however about 25%
would experience it for more than 5
years.
Sexual DysfunctionSexual Dysfunction
 The underlying problem for female sexual
dysfunction are usually multifactorial.
 Oestrogen deficiency can lead vaginal dryness
and dyspareunia,
 Non hormonal factors such as conflict between
partners, insomnia, inadequate stimulation,
life stresses can also lead to sexual
dysfunction.
 Depressed mood, anxiety, irritability,
mood swings, lethargy and lack of
energy have been associated with the
menopause.
 General population studies suggest that
most women do not experience major
mood changes during the menopause.
Psychological SymptomsPsychological Symptoms
Prospective epidemiologicalProspective epidemiological
studiesstudies
‘ psychological problems experienced
during the menopause are likely to be
associated with past problem and
current life stresses’
OsteoporosisOsteoporosis
 Affects 1:3 women.
 Risk factors include family history of fracture,
low BMI, early menopause, cigarette smoking,
alcohol abuse, sedentary lifestyle,
corticosteroids, hyperthyroidism.
 Common sites for osteoporotic fracture are
lower end of radius (wrist/Colles’ fracture),
proximal femur (hip) and vertebrae.
Cardiovascular DiseaseCardiovascular Disease
 common cause of death in women after the
age of 60 years.
 Risk factors for myocardial infarction are
abnormal FLP, smoking, depression and
stress.
 Incidence of stroke increases with age.
 Risk factors are hypertension, smoking,
diabetes, hyperlipidaemia, obesity.
Urogenital AtrophyUrogenital Atrophy
 Oestrogen and progestrone receptors are
present in the vagina, urethra, bladder and
pelvic floor musculature.
 Oestrogen deficiency after menopause cause
atrophic changes in the urogenital tract and is
associated with urinary symptoms which may
co-exist with symptoms of vaginal atrophy.
Treatment OptionTreatment Option
Making lifestyle changes - healthy
diet, exercise and stress reduction.
Hormone replacement therapy.
Complementary and alternative
therapies.
Hormone ReplacementHormone Replacement
TherapyTherapy
How to approach?How to approach?
Counseling
Health screening – history ,
examination and investigation
Knowledge??
Hormone ReplacementHormone Replacement
TherapyTherapy
 combine regime- estrogen and
progestogen in women with uterus
 Oestrogen /ERT only – women with no
uterus
OestrogensOestrogens
 Natural : oestradiol, oestrone and
oestriol which are chemically
synthesised from soya beans or yams;
conjugated equine oestrogen (CEE)
consisting primarily of estrone sulphate
and equilin sulphate,obtained from
urine of pregnant horses,
 Synthetic : ethinyl oestradiol and
mestranol (less suitable for HRT)
ProgestogensProgestogens
 High androgenic potency
 marked adverse effects on lipoproteins!
 negates beneficial effects of estrogen
 eg. 19-nor progestogens, norgestrel,
norethisterone
 Moderate androgenic potency
 some effects on plasma lipids
 eg. Medroxyprogesterone acetate (MPA)
No androgenic potency
 no effect on blood lipids
 Eg dydrogesterone (Duphaston)
Eg - Femaston
Routes of AdministrationRoutes of Administration
 Oral
-most widely used
-well tolerated
-highly effective
-rapid onset
-‘first-pass’ effect
(beneficial changes in
HDL:LDL)
 Transdermal
-patches or gels
-messy, time consuming
-redness/itchiness
-need of oral progestogen:
low compliance
 Intravaginal
-vaginal rings, pessaries,
cream
-no effects on vasomotor
symptoms, osteoporosis or
CVD
-creams or tablets:messy
-need oral progestogen: poor
compliance
 Subcutaneous
-surgically inserted pellets
-hormone release varies
-treatment can’t be
reversed
-estrogen effects persist
Prescribing RegimensPrescribing Regimens
 Estrogen therapy may be
 cyclical :administered for first 21 days of
the cycle)
 continuous :administered throughout the
cycle)
 Progestogens therapy may be
 sequentially :added for last 10 - 14 days of
the cycle (induces a withdraw bleed)
 continuously (to eliminate withdrawal bleed)
HRT CHARTHRT CHART
link
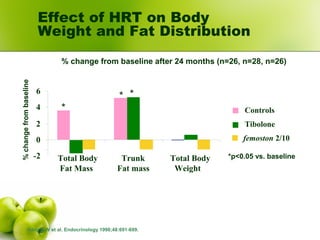
Weight Gain and Android Fat
Distribution in Menopause
% change from baseline after 24 months (n=26, n=28, n=26)
Hänggi W et al. Endocrinology 1998;48:691-699.
Effect of HRT on Body
Weight and Fat Distribution
-2
0
2
4
6
Total Body
Fat Mass
Trunk
Fat mass
Total Body
Weight
Controls
Tibolone
femoston 2/10
*
*p<0.05 vs. baseline
* *
%changefrombaseline
Sequential TherapySequential Therapy
 Mimics the menstrual cycle.
 Regular, monthly periods.
 Periods often lighter.
 Appropriate for perimenopausal women
with irregular bleed.
Continuous Combined RegimeContinuous Combined Regime
 A continuous-combined regime is to
eliminate wihdrawal bleeding.
 Use should be avoided within the first
12 months after the last menstrual
bleed.
 Spottings may occur during the first 3 -
4 months in most women.
 Appropriate for postmenopausal women
who do not wish for any regular
withdrawal bleed.
Duration of SystemicDuration of Systemic
TreatmentTreatment
 Vasomotor symptoms - up to 5 years
and then evaluate as some women do
experience symptoms for more than 5
years.
 Prevention or treatment of
osteoporosis - needs to be continued
for life as BMD falls when treatment is
stopped. However other option should
be discussed as long term HRT is
associated with other risk.
 Premature menopause - usually
advised to continue until the natural age
of menopause ~ 51 years. There after
need to reevaluate what is the endpoint
of treatment.
Treatment of LocalTreatment of Local
SymptomsSymptoms
Treatment is usually long term if not life long
as symptom return on cessation of treatment.
Synthetic oestrogens or CEE should be avoided
as they are well absorbed from the vagina.
The options available are low dose natural
oestrogen e.g vaginal oestriol by cream or
pessary or oestradiol by tablet or ring.
With the recommended dose regimen,
progestogen need not be added for endometrial
protection.
- effective in treating hot flushes and
improvement is usually seen within 4 weeks
with maximum effect achieved by 3 months.
- treatment should be continued for at least 1
year.
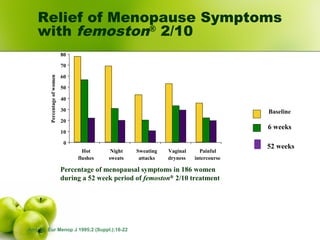
Vasomotor symptomsVasomotor symptoms
Percentage of menopausal symptoms in 186 women
during a 52 week period of femoston®
2/10 treatment
Baseline
6 weeks
52 weeks
0
10
20
30
40
50
60
70
80
Hot
flushes
Night
sweats
Sweating
attacks
Vaginal
dryness
Painful
intercourse
Percentageofwomen
Amy JJ. Eur Menop J 1995;2 (Suppl.):16-22
Relief of Menopause Symptoms
with femoston®
2/10
Urogenital symptoms and sexualityUrogenital symptoms and sexuality
- vaginal dryness, superficial
dyspareunia, urinary frequency and
urgency respond well to oestrogens
- urinary incontinence, however, is
not improved
- reduces the risk of spine, hip and other
osteoporotic fracture.
- need lifelong treatment to be effective in
preventing fracture.
- not recommended as a first-line treatment as
risks outweigh benefits.
- standard dose for bone protection are CEE
0.625mg, oestradiol 1-2mg and transdermal
25-50µg.
OsteoporosisOsteoporosis
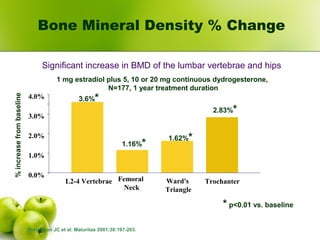
Bone Mineral Density % Change
Stevenson JC et al. Maturitas 2001;38:197-203.
Significant increase in BMD of the lumbar vertebrae and hips
1 mg estradiol plus 5, 10 or 20 mg continuous dydrogesterone,
N=177, 1 year treatment duration
* p<0.01 vs. baseline
0.0%
1.0%
2.0%
3.0%
4.0%
L2-4 Vertebrae Femoral
Neck
Ward's
Triangle
Trochanter
3.6%*
1.16%*
1.62%*
2.83%*
%increasefrombaseline
Prevention and Treatment ofPrevention and Treatment of
OsteoporosisOsteoporosis
 Biphosphonates
- shown to reduce both vertebral and non-
vertebral fractures
- principal side-effect : irritation of upper GIT so
given weekly/monthly to reduce this. Eg -
alandroanate
 SERMs (Raloxifene)
- shown to reduce vertebral fracture.
- does not treat vasomotor symptoms, cause
transient side effects such as hot flushes and
leg cramps.
- Has an equal propensity with HRT to cause
VTE
Prevention and TreatmentPrevention and Treatment
of Osteoporosisof Osteoporosis
 Calcitriol
- active metabolite of vitamin D and facilitates
the intestinal absorption of calcium.
 Calcium
- in postmenopausal women not on HRT 1.5
gram/day and in those on HRT 1.0 gram/day
of elemental calcium is needed to preserve
bone health.
 Vitamin D
- oral supplementation of 700-800IU/day seem
to reduce risk of vertebral and non-vertebral
fractures in ambulatory or institutionalized
elderly people.
Colorectal cancerColorectal cancer
- reduces risk of colorectal cancer by
about one-third
HRT AND Breast cancerHRT AND Breast cancer
- risk of breast cancer is dependent on
the regimen prescribed, greatest with
combined oestrogen-progestrogen
replacement.
- Risk of breast cancer minimal after 5
years of usage
- The WHI found : risk in the oestrogen-
alone group was 23% lower than in the
placebo group.
Nurses' Health Study (January 2006Nurses' Health Study (January 2006))
 Data suggest that timing of hormone
initiation in relation to age of onset
of menopause might influence
coronary risk; women beginning
HT/ET near onset of menopause had
a significantly reduced risk (30%
less) of CHD;
 no significant correlation between
HT/ET and CHD risk was observed
among women who initiated therapy
10 years or more after menopause.
Grodstein F, Manson JE, Stampfer MJ. Hormone therapy and coronary heart
disease: the role of time since menopause and age at hormone initiation.
Effects of unopposed estrogen and risk of invasiveEffects of unopposed estrogen and risk of invasive
breast cancer (Nurses' Health Study, May 2006)breast cancer (Nurses' Health Study, May 2006)
 Data indicate that use of estrogen
alone did not increase the risk of
invasive breast cancer until 20 years
of use and beyond, and risk was
increased at 15 years for estrogen
receptor and progesterone receptor-
positive cancers.
Chen WY, Manson JE, Hankinson SE, et al. Unopposed estrogen therapy and
the risk of invasive breast cancer. Arch Intern Med. 2006;166:1027-1032.
Breast DisorderBreast Disorder
 Benign breast disease - no
convincing evidence to show that the
risk of breast cancer is increased in
patients with benign breast disease
 Previous breast cancer - studies on
systemic HRT showed contradictory
results with some showing adverse
outcome and some showed no further
increase risk. However, low dose
vaginal oestrogen are not
contraindicated for vaginal symptoms.
HRT AND Endometrial cancerHRT AND Endometrial cancer
- unopposed oestrogen therapy increased
the risk of endometrial cancer and risk
is still increased for 5 years or more
after discontinuation of therapy.
- addition of progestogen reduces this
risk but not completely with sequential
progestogens especially if used for more
than 5 years.
- no increase risk is found with combined
continuous regimen.
HRT andHRT and VenousVenous
thromboembolic diseasethromboembolic disease
- highest risk occurs in the first year of
use.
- however, absolute risk is small as VTE
occurs in 1.7 per 1000 in women older
than 50 years who are not taking HRT
and mortality is low (1-2%).
- limited data suggest that transdermal
HRT is associated with a lower risk than
the oral route.
HRT and CANCERHRT and CANCER
Cervical and ovarian cancer -
not contraindicated except for
endometrioid ovarian cancer where
some doubt exist and progestogen
addition is recommended.
Endometrial cancer - need to be
given with progestogen.
Cardiovascular DiseaseCardiovascular Disease
 Hypertension - no evidence shows that oestradiol-
based HRT increases blood pressure or has an adverse
effect in women with hypertension. Rarely CEE may
cause severe hypertension which returns to normal
upon stopping treatment.
 Hyperlipidaemia - depends on type of HRT used.
 Venous thromboembolism - relative contraindication.
If still need to give as benefits outweighed risks then
the transdermal route might be safer (limited evidence)
 HRT and surgery - to stop 4 weeks prior to elective
surgery or to continue HRT with thromboprophylaxis.
Endocrine DiseaseEndocrine Disease
 Diabetes Mellitus - HRT seems to
improve the glycaemic control with
varying results depending on the type
and route of administion.
 Thyroid disease - dose of thyroxine
may need to be increased as oestrogen
can can increase the concentration of
thyroxine-binding globulin.
Non-oestrogen Based TreatmentNon-oestrogen Based Treatment
 Menopausal symptoms
- progestogens such as NET 5mg/day or
megestrol acetate 40mg/day
- Clonidine - 50-75mg bd, of limited
value and effectiveness
- SSRI, gabapentin
 Vaginal atrophy
- lubricants, moisturisers
What are other options?What are other options?
Exercise – yoga, Taichi, meditations
Healthy food – increase fruits and
vegetable intake
Alternative – black cohosh, red
clovers, etc
Case StudiesCase Studies
Case Study 1Case Study 1
 45 year old woman, para 3,
complains of:
 irregular bleeding (not heavy)
 vasomotor symptoms (hot
flushes, night sweats)
What would you advise her ?What would you advise her ?
Case Study 1Case Study 1
1.1. Health ScreenHealth Screen
• Detailed history of general health status including family history
• Physical examination: BP, Anemia, Thyroid, CVS, Lung, Breasts,
Pelvic examination including Pap Smear.
• Blood Examination: Hb, Lipid profiles, FBS, Others if indicated.
• Other investigations: Mammography, BMD (Dexa)
2. Treatment …
If all tests are normal the choices are:
• Combined Cyclical HRT (regular-bleed)
Case Study 1Case Study 1
2. …Treatment
Combined Cyclical HRT (regular-bleed)
• Short-term
• Pregnancy?
Rees M, Purdie DW (2002), Management of the Menopause. Pg 112
Case Study 2Case Study 2
50 year old woman, posthysterectomy 3 years
(ovaries not removed), has menopausal
symptoms. She wants to know what are her
options for:
 hot flushes
 night sweats
 Dryness of vagina
 Dyspareunia
What would you advise her ?What would you advise her ?
Case Study 2Case Study 2
1.1.Health ScreenHealth Screen
• Baseline workup as is case 1
2. Treatment
• If normal mammogram and no contraindication, estrogen
only therapy can be started
• For fast relieve of vaginal symptoms, local application of
vaginal cream can be used for short term
Case Study 2Case Study 2
3. Weigh the benefits and risks
What are my risks ?
• Cardiovascular disease
− no protection
− If coronary artery disease present, higher risk of mortality in
the first year
• Breast Cancer
− Increased risk (MW study)
− No increase in risk (WHI Study)
− Increase mortality from breast cancer (MW Study)
Case Study 2Case Study 2
4. Alternative therapy if there are other risk
factors
What are my options?
• Prozac/Effexor
• Antihypertensives (Aldomet)
• Unproven therapy
− Black Cohosh
− Phytoestrogens
− Advise on spritual exercise yoga, taichi etc
Case Study 3Case Study 3
60 year old woman, has taken HRT
for 10 years is seeking your advice
whether she should stop or continue
taking HRT ?
What would you advise her ?What would you advise her ?
Counseling risk outweigh benefit
Health screening
Offer non pharmacological treatment
now consider HT rather than HRT?
 Nonpharmacological treatment of postmenopausal
symptoms
 Article first published online: 11 JAN 2013
 © 2013 Royal College of Obstetricians and Gynaecologists
Issue
 The Obstetrician & Gynaecologist
Volume 15, Issue 1, pages 19–25, January 2013
Where are we now?Where are we now?
ACOG: State-of-the-Art Guide to HormoneACOG: State-of-the-Art Guide to Hormone
TherapyTherapy
 Combined hormone therapy should not be used for
prevention of diseases such as cardiovascular
disease, due to the small but significant increased
risk of conditions such as breast cancer, heart
attack, stroke, and blood clots;
 Estrogen-alone therapy, used for women who
have had a hysterectomy, should also not be used
for prevention of diseases, due to increased risks
of blood clots and stroke.
Although ET carries fewer risks than combined HT,
women with a uterus should not use estrogen
alone due to their increased risk of uterine cancer;
ACOG: State-of-the-Art Guide toACOG: State-of-the-Art Guide to
Hormone TherapyHormone Therapy
 Hormone therapies are appropriate for the relief
of vasomotor symptoms, so long as a woman has
weighed the risks and benefits with her doctor;
and
 Women on combined HT or ET should take the
smallest effective dose for the shortest possible
time and annually review the decision to take
hormones.
NAMS (North American Menopause Society –NAMS (North American Menopause Society –
Sept 2003)Sept 2003)
 The primary indication for systemic
hormone therapy is moderate and
severe menopausal symptoms: Hot
flashes, night sweats/insomnia,
mood swings
 When treating moderate and severe
urogenital atrophy (vaginal dryness,
dyspareunia, urinary frequency, and
incontinence), local estrogen
preparations are preferred.
 2. HRT for treating menopausal symptoms
 Treatment is justified since the benefits outweigh
the risks.
 4. HRT for managing osteoporosis
 Consider alternative therapies such as calcium,
biphosponates and the selective estrogen receptor
modulators. (SERMs)
 3. HRT for preventing cardiovascular diseases
 3.1 Conventional HRT should not to be used for primary
prevention however a low dose HRT and transdermal
therapy can be considered to be used.
 3.2 HRT should not be used for secondary prevention
against heart disease.
 3.3 Women at risk of cardiovascular disease who wish to
discontinue HRT should consider dietary and lifestyle
changes (weight loss, regular exercise, stop smoking) as
well as the use of drugs to lower cholesterol and blood
pressure.