MENOPAUSE
NIKITA SHARMA
INTRODUCTION
ļ‚” Menopause is derived from the Greek word:
Mens ------ monthly
Pausis-------cessation
ļ‚§ Menopause is a part of a women’s natural ageing process when her
ovaries produce lower level of the estrogen & progesterone and
when she is no longer able to become pregnant.
ļ‚” Menopause is the physiologic cessation of menses associated with
declining ovarian function.
ļ‚” It is usually considered complete after 1 year of amenorrhea
(absence of menstruation).
INTRODUCTION
ļ‚” Menopause is the permanent cessation of menstruation at the end
of reproductive life due to loss of ovarian follicular activity.
ļ‚” Natural menopause is secondary amenorrhea for more than 6
months (12 months) in a woman aged 45 years or over without any
pathological cause.
ļ‚” Average age of menopause = 51 years.
ļ‚” Menopause before the age of 40 years is called premature ovarian
failure (POF)
DEFINITION
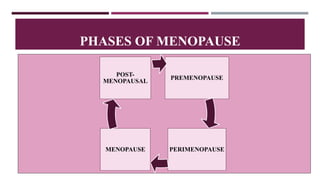
PREMENOPAUSE
PERIMENOPAUSE
MENOPAUSE
POST-
MENOPAUSAL
PHASES OF MENOPAUSE
ļ‚” This phase is the part of the climacteric when menstrual cycle is to be
irregular.
ļ‚” It is the time prior to menopause
ļ‚” It occur before 40 years.
PREMENOPAUSE
ļ‚” This is the period around menopause (40-55 yrs.)
ļ‚” This phase is also known as Climacteric .
ļ‚” In this phase, physiological changes associated with end of
reproductive capacity and terminating with completion of
menopause.
PERIMENOPAUSE
ļ‚” In this phase, end of menstruation occur.
ļ‚” It occurs between the age of 45-55 years.
ļ‚” Average age = 50 yrs.
MENOPAUSE
ļ‚” This phase is the time after which women has experienced 12
consecutive months of amenorrhea without period.
POST-MENOPAUSAL
1. AGE:- around 50 years is average (range = 45-55 yrs.)
2. Genetically predetermined
3. Thinner women have early menopause
4. Cigarette smoking & severe malnutrition will leads to early
menopause
5. Amenorrhea = 12 months
6. Menopausal symptoms
DIAGNOSIS OF MENOPAUSE
ļ‚” Following stoppage of menstruation (Amenorrhea) for 12
consecutive months without any pathology.
ļ‚” As such, a woman is declared to have attained menopause only
retrospectively.
CLINICAL DIAGNOSIS FOR CONFIRMATION
When ovaries are totally depleted of eggs and no amount of
stimulation from the regulating hormones can force them to work.
CAUSES OF MENOPAUSE
OTHER CAUSES
ļ‚” Premature ovarian failure (POF)
ļ‚” Surgeries that removes both ovaries and uterus.
ļ‚” Some types of chemotherapy.
ļ‚” Stress
Usual onset: 49 and 52 years of age.
PHYSIOLOGICAL CHANGES IN
MENOPAUSE
CHANGES IN GENERALAPPEARANCE
SKIN:
Looses its elasticity due to loss of elastin and collagen from the
skin.
Become thin and fine
Weight:
Increases due to irregular food habits due to mood swings.
Hair:
Dry, coarse and hair loss due to decrease level of estrogen.
Voice:
Become deeper due to thickening of vocal cords
Fat:
Increase deposition of fat around the hips, waist & buttocks.
CHANGES IN GENERALAPPEARANCE
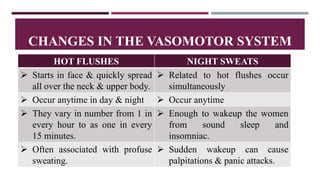
CHANGES IN THE VASOMOTOR SYSTEM
HOT FLUSHES NIGHT SWEATS
 Starts in face & quickly spread
all over the neck & upper body.
 Related to hot flushes occur
simultaneously
 Occur anytime in day & night  Occur anytime
 They vary in number from 1 in
every hour to as one in every
15 minutes.
 Enough to wakeup the women
from sound sleep and
insomniac.
 Often associated with profuse
sweating.
 Sudden wakeup can cause
palpitations & panic attacks.
Cholesterol levels:
Increases in the blood. This leads to gradual rise in the risk of heart
disease & stroke after menopause.
Calcium levels:
Calcium loss from the bone is increased in 1st 5 years after onset of
menopause resulting in loss of bone density.
Bone loss = 3-5%/yr. due to low level of estrogen.
Calcium moves out of bones, leave them weak & liable to
fracture at the smallest stress (osteoporosis).
CHANGES DUE TO METABOLISM OF BODY:
Digestive stress:
More activity of entire digestive system is diminished.
Intestines tends to be sluggish leads to constipation.
Urinary system:
Due to low level of estrogen; tissue lining the urethra & bladder
become drier, thinner & less elastic and causes increase frequency of
passing urine as well as increase tendency to develop UTI.
CHANGES DUE TO METABOLISM OF BODY:
Uterus:
Atrophy of muscles
Small & fibrotic uterus
Cervix:
Smaller appear to flush with vagina
In older women it become impossible to differentiate with vagina
The vaginal & cervical discharge decreases in amount & later
disappears completely.
CHANGES IN GENITAL ORGANS
Ovaries:
smaller & shriveled
Increase amount of androgen secretion leads to secretion of
androstenedione and testosterone.
Which leads to facial hair growth and change in voice
In obese women, there is more fat in the body which leads to more
secretion of androgen & are more prone to endometrial hyperplasia
and endometrial carcinoma.
CHANGES IN GENITAL ORGANS
Vagina:
Mucous membrane become thin
Menstrual index = 10/85/5 (feature of low estrogen)
No glycogen
Absence of doderlein’s bacilli
Dry, alkaline pH
Dyspareunia
CHANGES IN GENITAL ORGANS
Vulva & external genital organs:
Fat in labia majora
Decrease in mons pubis
Sparse pubic hair
Narrow introitus
Breast :
 Become flat in thin built women & shriveled
Remain flabby & pendulous in heavy built women.
CHANGES IN GENITAL ORGANS
Are mainly manifested by:
Frequent headache
Irritability, mood disturbance, aggressiveness, tension
Fatigue, memory loss & problem with concentration
Depression, anxiety & instable mood
Sleepiness, insomnia, phobias, tearfulness ad low self-esteem.
All are occur due to changes in hormonal levels.
PSYCHOLOGICAL CHANGES IN
MENOPAUSE
Diminished change in interest due to;
 Emotional upset
Secondary to dyspareunia
Dry vagina
PSYCHOLOGICAL CHANGES IN
MENOPAUSE
ļ‚” The feeling that a women holds about herself and her social
relationship as well as the symptoms she experiences can be defined
by the culture in which she live.
ļ‚” Social location affects the way women perceive menopause & its
related biological effects.
ļ‚” The way she view menopause.
ļ‚” Ethnicity & geographical location.
SOCIAL CHANGES IN MENOPAUSE
HORMONE REPLACEMENT THERAPY
(HRT)
It is a treatment used to relieve symptoms of the
menopause.
It replaces female hormone (estrogen) that is at a lower level
as women approaches the menopause.
INDICATIONS
Symptomatic women with estrogen deficiency
Premature ovarian failure
Spontaneous/ post surgery
Gonadal dysgenesis
Surgical or radiation menopause
Women demanding HRT as prophylaxis
DRUGS USED IN HRT
ESTROGEN
• PROGESTERONE
TIBOLONE
• RALOXIFENE
BISPHOSPHONATES
SOYA
ANDROGENS
TYPES OF HRT
ESTROGEN & PROGESTERONE
ESTROGEN ONLY
PROGESTIN ONLY
ESTROGEN & PROGESTERONE
Designed for women who have a uterus
Estrogen is given regularly while progesterone is added on
supplementary basis
These 2 hormones are given in combination to prevent
overgrowth of uterine lining.
Estrogen alone may irritate this lining which could lead to
endometrial cancer.
ESTROGEN ONLY
This preparation is given to women who have lost their
uterus due to surgical menopause
Because there is no presence of uterus; the need for
progesterone is not as great.
PROGESTIN ONLY
It is not prescribed very often
It provide excellent relief for women deal with hot flushed.
AVAILABLE PREPARATION FOR HRT
Principle hormone used in HRT – Estrogen for women who
had already removed her uterus.
But if we are giving estrogen only to the women with intact
uterus it will cause endometrial hyperplasia and
carcinoma.
Addition of progestin for last 12-14 days each month can

prevent this problem.
COMMONLY USED ESTROGEN &
PROGESTERONE
• Conjugated estrogen (0.625-
1.25mg/d)
• Micronized estradiol (1-2mg/d)
ESTROGEN
• Medroxyprogesterone acetate (2.5-5mg/d)
• Micronized progesterone (100-300mg/d)
• Dydrogesterone (5-10mg/d)
PROGESTIN
CONJUGATED ORAL ESTROGEN
Dose = 0.3 mg/d having minimum side effects
Dose can be changed, modified & stopped until the control
of symptoms.
Women who had Hysterectomy can be given Conjugated
Equine Estrogen (CEE)- 0.3-0.625mg/d
ESTROGEN & CYCLIC PROGESTIN
It is given to women who have uterus
Estrogen is given continuously for 25 days
Addition of progestin in last 12-14 days.
CONTINUOUS ESTROGEN & PROGESTIN
THERAPY
It prevents endometrial hyperplasia
This therapy may case irregular bleeding
SUBDERMAL IMPLANTS
It needs anesthesia
Implant insertion is done over the anterior abdominal wall,
subcutaneously
E.g. 17 β estradiol implants. 25mg, 50mg or 100mg for 6
months.
PERCUTANEOUS ESTROGEN GEL
1gm of applicator of gel delivering 1mg of estradiol daily.
It is applied on the skin over anterior abdominal wall or
thigh.
Effective blood level of estradiol (90-120pg/ml) can be
maintained.
TRANSDERMAL PATCH
It contains 3.2mg of 17 β estradiol releasing about 50µgof
estradiol in 24hours.
It should be applied below waist line and changed twice in
a week.
VAGINAL CREAM
It is very effective in atrophic vaginitis
Conjugate equine vaginal estrogen cream- 1.25mg/d is
applied.
Women with symptoms of urogenital atrophy, urinary
symptoms & do not like to have systemic HRT, are suiable
for such treatments.
PROGESTIN ONLY
(HRT)
It is given in women with history of Breast carcinoma,
endometrial carcinoma
It is effective in suppressing Hot flushes
It also helps in preventing Osteoporosis
E.g. Medroxyprogesterone acetate = 2.5-5mg/d
TIBOLONE
It is a steroid having weakly estrogenic, progestogenic &
androgenic properties.
It prevent osteoporosis, atrophic changes of vagina & hot
flushes.
It increases Libido
Dose = 2.5mg/d.
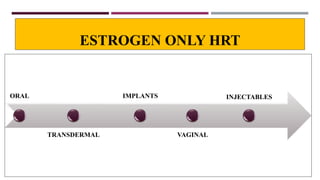
ORAL
TRANSDERMAL
IMPLANTS
VAGINAL
INJECTABLES
ESTROGEN ONLY HRT
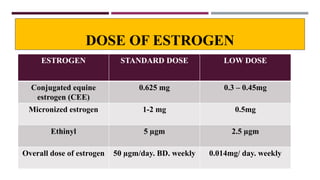
DOSE OF ESTROGEN
ESTROGEN STANDARD DOSE LOW DOSE
Conjugated equine
estrogen (CEE)
0.625 mg 0.3 – 0.45mg
Micronized estrogen 1-2 mg 0.5mg
Ethinyl 5 µgm 2.5 µgm
Overall dose of estrogen 50 µgm/day. BD. weekly 0.014mg/ day. weekly
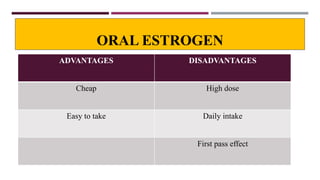
ORAL ESTROGEN
ADVANTAGES DISADVANTAGES
Cheap High dose
Easy to take Daily intake
First pass effect
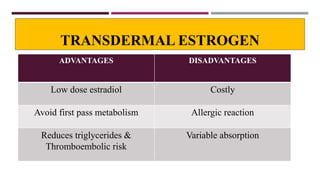
TRANSDERMAL ESTROGEN
ADVANTAGES DISADVANTAGES
Low dose estradiol Costly
Avoid first pass metabolism Allergic reaction
Reduces triglycerides &
Thromboembolic risk
Variable absorption
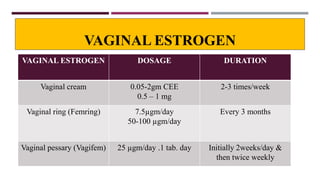
VAGINAL ESTROGEN
VAGINAL ESTROGEN DOSAGE DURATION
Vaginal cream 0.05-2gm CEE
0.5 – 1 mg
2-3 times/week
Vaginal ring (Femring) 7.5µgm/day
50-100 µgm/day
Every 3 months
Vaginal pessary (Vagifem) 25 µgm/day .1 tab. day Initially 2weeks/day &
then twice weekly
DURATION OF HRT
For short period = 3-5years
Reduction of dosage should be done ASAP.
CONTRAINDICATIONS OF HRT
Undiagnosed genital tract bleeding
Estrogen dependent neoplasm in body (uterine fibroids)
History of venous thromboembolism
Active liver disease
Gallbladder disease
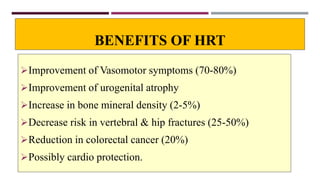
BENEFITS OF HRT
Improvement of Vasomotor symptoms (70-80%)
Improvement of urogenital atrophy
Increase in bone mineral density (2-5%)
Decrease risk in vertebral & hip fractures (25-50%)
Reduction in colorectal cancer (20%)
Possibly cardio protection.
RISKS OF HRT
Dementia &
Alzheimer
disease
Lipid
metabolism
VTE
Breast
cancer
Endometrial
cancer
DISADVANTAGES OF HRT
By giving estrogen & progesterone over a long period is
known to stimulate cell division & this seem to increase the
risk for breast cancer by up to 90%.
HRT increases the risk of heart diseases by 24%
One should use HRT for not more than 5 years.
SURGICAL MENOPAUSE
ļ‚” The ovaries produce estrogen, progesterone & androgens
which are essential to the regulation of the menstrual cycle.
When a hysterectomy occurs, these hormones get suddenly
interrupted & their level falls resulting in symptoms of
menopause. This is termed as surgical menopause.
SURGICAL MENOPAUSE
ļ‚” Since, there is abrupt disruption of hormones after
hysterectomy, the menopausal symptoms are more severe,
more frequent & last longer when compared to natural
menopause.
SYMPTOMS OF SURGICAL MENOPAUSE
ļ‚” Hot flushes & night sweat due to disturbance of central thermostat
located in hypothalamus which is kept stable by normal circulating
estrogen.
ļ‚” Sleepless nights
ļ‚” Vaginal dryness
ļ‚” Itching
ļ‚” Decrease in sexual desire
ļ‚” Dyspareunia
SYMPTOMS OF SURGICAL MENOPAUSE
ļ‚” Depression due to low estrogen level
ļ‚” Thyroid dysfunction
ļ‚” Bladder infection
ļ‚” Urine incontinence
ļ‚” Weight gain
ļ‚” Migraine
ļ‚” Irritability
MANAGEMENT OF SURGICAL MENOPAUSE
1. Estrogen- immediately after surgery to prevent hot flushes
2. Estrogen gel- applied to upper leg or abdomen daily
3. Vaginal ring- for women whose uterus has been removed
4. Vaginal cream- for women having vaginal atrophy, applied locally
on lining of vagina.
5. HRT implants-these are small pellets inserted surgically under the
skin into the fatty layers of abdomen under local
anesthesia & change periodically once in 6 months
MANAGEMENT OF SURGICAL MENOPAUSE
6. HRT patches- these are the small patches which can release
hormones into blood stream transdermally; need to
change twice in a week; possible side effects are- skin
irritation & allergy.
7. Tablets- most common form of HRT. It is for long term use which
needs to be carefully considered.
MANAGEMENT OF SURGICAL MENOPAUSE
8. EXERCISE:
- It is the another form of self-help which are positive therapy.
- One should begin with small but regular walks and then gradually
move over to weight bearing exercises.
- It helps to release endorphins from the brain that send feel good
message to the body.
RISKS OF SURGICAL MENOPAUSE
Cardiovascular disease
Weight loss due to reduced bone density
Gum tissues are affected.
GUIDANCE & COUNSELLING
 It is important to understand the individual’s need and priorities
when providing counseling .
KEY POINTS:
1. The decision – making process
2. Problems reported by women
3. Decision- making and counseling guidelines and supports
GUIDANCE & COUNSELLING
 Women at the menopausal stage need to be supported emotionally;
they may need counselling to be educated about how to manage signs
and symptoms of menopause.
This may also help them to overcome the symptoms of anxiety and
depression.
Certain life style modification is necessary to prevent the occurrence
or minimize the effects of the associated condition.
GUIDANCE & COUNSELLING
Nurse gives following advice to reduce menopausal
symptoms:
 To reduce hot flushes and hot flashes
To reduce vaginal dryness
To control urinary incontinence
To prevent osteoporosis
TO REDUCE THE HOT FLUSHES & HOT
FLASHES
Not too warm, Lower heat.
 Use cotton clothes
 Use the fan
Replace coffee, tea, cola beverages by natural juices
 No smoking
 Learn to relax
Exercise on a regular basis helps to reduce anxiety
Take plenty of fluids.
TO REDUCE VAGINAL DRYNESS
In sexual relations while devoting more time loving
(necking) as this will increase vaginal lubrication naturally.
Using specific lubricants that are sold in pharmacies,
Vaseline or oil.
TO CONTROL URINARY INCONTINENCE
Exercises to strengthen pelvic muscles (Kegal exercise):
When the bladder is empty, try to cut the flow of urine for a
few seconds (the muscles are contracted) and then relax.
Perform this exercise several times a day.
TO PREVENT OSTEOPOROSIS
Physical exercise moderately and regularly, where all the
joints work and thus hinders the process of decalcification of
bone.
A diet rich in calcium, by increasing the intake of dairy
products.
GUIDANCE & COUNSELLING
Losses (fertility, loss of roles, leaving the house by the
children, lost parents, relatives and friends, etc.)
The promotion of social relationships (friends, women’s
groups, associations), to avoid isolation and loneliness.
 Mental health referral if some pathology such as anxiety,
stress, etc.
TO PREVENT GYNECOLOGICAL CANCER
Perform breast self examination.
Annual clinical examination, mammography every two
years.
Exfoliative cervicovaginal cytology.
TO PREVENT CARDIOVASCULAR
DISORDER
ļ‚” Fat diet rich in olive oil helps regulate cholesterol.
ļ‚” Healthy diet rich in fruits and vegetables.
ļ‚” Control of blood pressure to rule out hypertension.
ļ‚” Exercise.
ļ‚” Hormone replacement therapy.
ROLE OF MIDWIFERY NURSE
PRACTITIONER
ASSIGNMENT
Menopause