MENOPAUSE
Presented by:
Megan Handley
Pharm.D. Candidate Class of 2015
University of Arizona College of Pharmacy
OBJECTIVES
Background
Staging of menopause
Hormone therapy
Over the counter options
Non-pharmacological
treatment options
Conclusions
BACKGROUND
 Mean age: 51 years
 95% of women become menopausal between 45 & 55 years of age
 Permanent cessation of menstrual periods (12 months of amenorrhea)
 Perimenopause (transition phase) begins on average 4 years before
the final menstrual period
 Diagnosis of menopausal transition is made in women:
 >45 years old
 Irregular menstrual cycles
 Menopausal symptoms
 Serum follicle-stimulating hormone is
often measured, however the result
offers no additional information
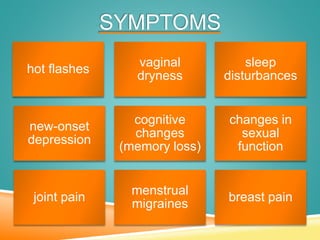
SYMPTOMS
hot flashes
vaginal
dryness
sleep
disturbances
new-onset
depression
cognitive
changes
(memory loss)
changes in
sexual
function
joint pain
menstrual
migraines
breast pain
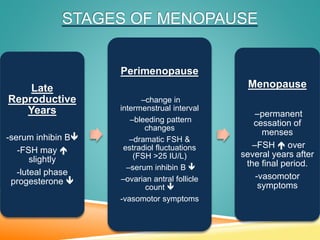
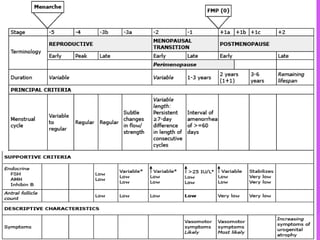
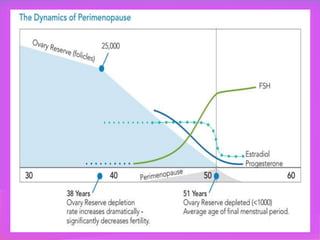
STAGES OF MENOPAUSE
Late
Reproductive
Years
-serum inhibin B
-FSH may 
slightly
-luteal phase
progesterone 
Perimenopause
–change in
intermenstrual interval
–bleeding pattern
changes
–dramatic FSH &
estradiol fluctuations
(FSH >25 IU/L)
–serum inhibin B 
–ovarian antral follicle
count 
-vasomotor symptoms
Menopause
–permanent
cessation of
menses
–FSH  over
several years after
the final period.
-vasomotor
symptoms
HORMONE THERAPY
 Goal: to relieve menopausal symptoms & treat vulvovaginal
atrophy during perimenopause & early menopause
 Indications:
 moderate to severe vasomotor symptoms
 moderate to severe symptoms of vulvar & vaginal atrophy
 prevention of postmenopausal osteoporosis
 Disease prevention:
 Osteoporosis
 Dementia
 Cardiovascular disease
 Risks are plentiful, but short-term use (≤5 years)
does not seem to be associated with significant risk
RISKS OF HORMONE THERAPY
 Endometrial cancer
 Venous thromboembolic disease:
 Increased risk within 1-2 years after initiation of hormone therapy
 Smoking cessation
 Breast cancer
 Increased breast density with progestogens via proliferation of estrogen-dependent
mammary tissue, making it more difficult to detect breast cancer early with a mammogram
 Family history
 Duration of exposure
 Ovarian cancer
 >10 years estrogen therapy
 Cerebrovascular accidents
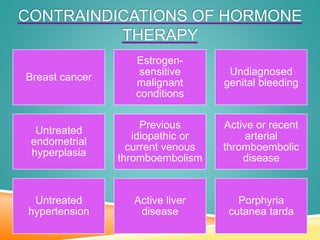
CONTRAINDICATIONS OF HORMONE
THERAPY
Breast cancer
Estrogen-
sensitive
malignant
conditions
Undiagnosed
genital bleeding
Untreated
endometrial
hyperplasia
Previous
idiopathic or
current venous
thromboembolism
Active or recent
arterial
thromboembolic
disease
Untreated
hypertension
Active liver
disease
Porphyria
cutanea tarda
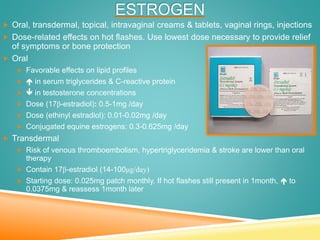
ESTROGEN
 Oral, transdermal, topical, intravaginal creams & tablets, vaginal rings, injections
 Dose-related effects on hot flashes. Use lowest dose necessary to provide relief
of symptoms or bone protection
 Oral
 Favorable effects on lipid profiles
  in serum triglycerides & C-reactive protein
  in testosterone concentrations
 Dose (17β-estradiol): 0.5-1mg /day
 Dose (ethinyl estradiol): 0.01-0.02mg /day
 Conjugated equine estrogens: 0.3-0.625mg /day
 Transdermal
 Risk of venous thromboembolism, hypertriglyceridemia & stroke are lower than oral
therapy
 Contain 17β-estradiol (14-100μg/day)
 Starting dose: 0.025mg patch monthly. If hot flashes still present in 1month,  to
0.0375mg & reassess 1month later
ESTROGEN: LOCAL/VAGINAL
 Indications: atrophy, sexual function, dyspareunia, atrophic vaginitis
 Wash hands before use, insert with vaginal applicator, clean applicator in
warm, soapy water & rinse
 Conjugated estrogens (Premarin cream): Start with 0.5g vaginally twice
weekly (usually 3weeks on /1week off). Do not exceed 2g/day.
 Estradiol
 Estrace cream: 2-4g daily for 1-2weeks, gradually reduce to half initial dose for 1-
2weeks
 Maintenance dose:1g 1-3 times weekly may be used after restoration of vaginal mucosa
 Vagifem tablets: insert one10mcg tablet daily for 2weeks then one tablet twice
weekly
 Estragyn (estrone) cream: 2-4g intravaginally daily
 Continuously or 25days on/5days off.
 Attempts to discontinue or taper should be made
at 3-6month intervals
PROGESTINS
 Intact uterus: need progestin+estrogen to prevent endometrial hyperplasia
 Oral, transdermal, transvaginal, intrauterine
 Adverse effects: mood swings, bloating, fluid retention, sleep disturbance
 Cyclic: 10-14days/month (produces monthly menstrual periods)
 Continuous: progestogen+estrogen daily (amenorrhea, breakthrough bleeding)
 Micronized progesterone: 100mg PO daily or 200mg PO for 10-12days/month
 Norethindrone: 0.35mg PO daily or 5mg PO for 10-12 days/month
 Levonorgestrel (Mirena): intrauterine device releasing 20mcg/day
 Medroxyprogesterone acetate: 2.5mg PO daily or 5-10mg PO for 10-12days/month
 Abnormal bleeding necessitates
careful monitoring of the endometrium
with ultrasonography & biopsy
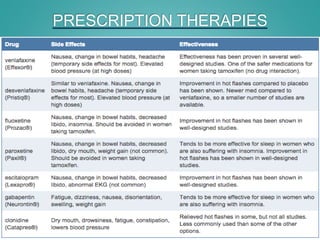
PRESCRIPTION THERAPIES
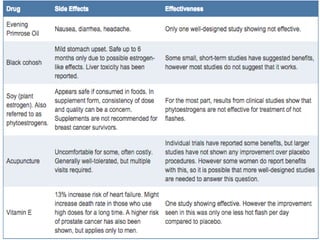
OTC/HERBAL TREATMENTS
 Phytoestrogens: sterol molecules produced by plants, weak estrogenic activity
 Soy
 Inconsistent trial results, no long-term safety & efficacy trials completed
 Food sources preferred (tofu, soy sauce, soybean oil, soy milk)
 Avoid over dosage with supplements
 Women with personal or strong family history of hormone-dependent cancers, thromboembolic or
cardiovascular events should not use soy products
 Black cohosh (Remifemin)
 Trials yielded inconsistent results
 Rare case reports of hepatitis associated with preparations containing black cohosh
 No safety trials have been conducted for longer than 6months
 ProFema: vitamins, minerals, black cohosh, spirulina, kelp, digestive plant enzymes, etc. ($40/month)
 Estroven: vitamins, minerals, natural extracts, isoflavones (soybeans), black cohosh ($15/month)
NON-PHARMACOLOGICAL TREATMENTS
Avoid spicy foods
Avoid stress
triggers
Cool environment
(fans, air
conditioning,
light/layered
clothing)
Relaxation therapy
Cognitive
behavioral therapy
Placebo effect
Weight loss Exercise Hypnosis
ANDROGEN DEFICIENCY
 Symptoms: low libido, decreased sexual response, depression, insomnia,
headache, poor concentration, decreased lean body mass, fatigue
 Adverse effects: acne, hirsutism, voice, deepening, ↓ in high-density
lipoprotein levels
 Variation in normal ranges of serum testosterone levels, DHEA, DHEAS, &
androstenedione. Makes diagnosis of androgen deficiency difficult.
 Patients who continue to have symptoms on estrogen replacement alone
 Use of androgens other than testosterone (DHEA, DHEAS, androstenedione)
cannot be recommended due to uncontrolled amounts of medication in OTC
preparations.
 Methyltestosterone dose not to exceed 2.5mg daily
 Estratest:1.25mg esterified estrogens & 2.5mg methyltestosterone, 0.625mg
esterified estrogens & 1.25mg methyltestosterone
CONCLUSIONS
 Hormone therapy is prescribed during perimenopause & early
menopause for relief of symptoms & treatment of vaginal atrophy
 Progestational agent should be used in women with an intact uterus &
can be administered with estrogen
 Hormone therapy dose may be reduced with increasing age
 Hormone therapy results in benefits on bone protection & possibly
dementia
 Risks of endometrial cancer, breast cancer, ovarian cancer, vascular &
thromboembolic disease with hormone therapy
 Clonidine, antidepressants, & anticonvulsants may have benefit
 OTC preparations have inconsistent trial results & often interact with
other medications
 Androgen deficiency symptoms despite estrogen therapy may warrant
addition of methyltestosterone to estrogen treatment
QUESTIONS?
REFERENCES
 National Institutes of Health. The 2012 hormone therapy position statement of
the North American Menopause Society. Menopause 2012; 19:257.
 American Association of Clinical Endocrinologists medical guidelines for
clinical practice for the diagnosis and treatment of menopause. Endocrine
Practice 2006; 12:315-30.
 Martin KA, Barbieri RL. Treatment of menopausal symptoms with hormone
therapy. UpToDate. 2014. Accessed February 2015.
 Beral V, Million Women Study Collaborators. Ovarian cancer and hormone-
replacement therapy in the Million Women Study. Lancet. 2007;369:1703-
1710.
 Menopausal hormone therapy and cancer risk. American Cancer Society.
2014.http://www.cancer.org/cancer/cancercauses/othercarcinogens/medicaltr
eatments/menopausal-hormone-replacement-therapy-and-cancer-risk.
Accessed February 2015.
 Sattar N, Forouhi NG, Wild RA. C-rective protein and hormone replacement
therapy. Circulation. 2000; 102:e96-7.
 US Food and Drug Administration. Questions and Answers for Estrogen and
Estrogen with Progestin Therapies for Postmenopausal Women.
http://www.fda.gov/Drugs/DrugSafety/InformationbyDrugClass/ucm135339.ht
m5. (Accessed February 2015).
 Anderson GL, Clebowski RT, Aragaki AK, et al. Conjugated equine oestrogen
and breast cancer incidence and mortality in postmenopausal women with
hysterectomy: extended follow-up of the Women’s Health Initiative
randomised placebo-controlled trial. Lancet Oncol. 2012 Mar 6