Cesarean Scar Pregnancy
Aboubakr Elnashar
Benha university Hospital, Egypt
AboubakrElnashar
AboubakrElnashar
1. INTRODUCTION
Define
Prevalence
Pathogenesis
Complications
2. DIAGNOSIS;
DIFFERENTIAL DIAGNOSIS
3. MANAGEMENT
FOLLOW-UP
4. PREVENTION
SUMMARY
1. INTRODUCTION
Define
GS implanted in the myometrium at the site of a
previous CS scar.
The first case
1978.
Terminology
cesarean scar pregnancy
Ectopic pregnancy in a Caesarean scar
cesarean ectopic pregnancy
cesarean scar ectopic.
: MXT as in tubal ectopic pregnancies: failed but disastrous
AboubakrElnashar
Prevalence
Rare
Rising
1. {increased incidence of CS}
72% of CSP occur in women who have had ≥2CS
2. {increased use of TVS}
AboubakrElnashar
AboubakrElnashar
Pathogenesis
Prior CS: fibrous scar tissue with a wedge-shaped
myometrial defect .
Pregnancy: Blastocyst implants on fibrous scar
Multiple CS:
increase scar surface area: increase the risk of
implantation on the scar
AboubakrElnashar
The myometrial defect:
Develops after:
CS
D &C
Myomectomy
Metroplasty
Hysteroscopy
Manual removal of the placenta.
Due to:
1. incomplete healing
2. increased fibrosis
Aboubakr Elnashar
Complications
±devastating
Placenta previa/accreta
Uterine rupture
Massive hge:
increased maternal morbidity and mortality.
AboubakrElnashar
2. DIAGNOSIS
Time of presentation
At any time from implantation to term
More commonly in 1st T.
1. Vag bleeding and abd pain: common
2. Asymptomatic: 1/3
AboubakrElnashar
 Degrees
1. Severe:
 little or no myometrium overlying GS
 usually diagnosed in 1st T
 Hge and ut rupture if untreated.
2. Less severe:
often diagnosed in 2nd and 3rd T as PA
±: normal live births but with increased
maternal morbidity.
AboubakrElnashar
Difficult
Missed in: 15%
D&C for “termination of an early pregnancy”
or D&C for missed abortion:
heavy bleeding
Shock
hemoperitoneum
AboubakrElnashar
Sonography
TA:
 Panoramic view of the pelvis and uterus
Inspection of the interface between the anterior
LUS and bladder. then
TV:
Reference standard in 1st T
Sensitivity: 86.4%
Sagittal view along the long axis of the uterus
through the plane of GS: localize GS within the
anterior LUS.
AboubakrElnashar
Sonographic criteria in 1st T
1. Uterus:
 empty with a clearly visualized endometrium
2. Cervix:
Empty
3. GS:
 within the anterior portion of LUS
at site of the cesarean scar
4.Myometrium between GS and bladder:
Thin or absent: <5 mm in 2/3 of cases.
AboubakrElnashar
5. Doppler
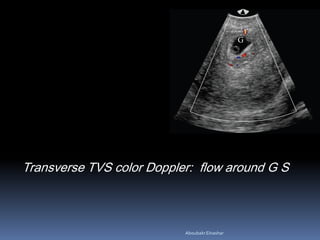
Marked peritrophoblastic color Doppler flow
around GS
Avoid false positive diagnosis: 30-40%
low-impedance (pulsatility <1)
high-velocity flow (>20 cm/s)
Resistive index: < 0.5
Peak systolic to diastolic blood flow ratio: < 3.1

AboubakrElnashar
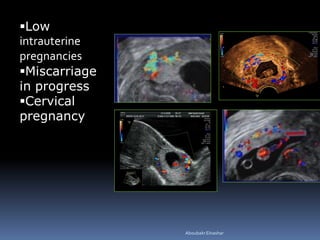
Low
intrauterine
pregnancies
Miscarriage
in progress
Cervical
pregnancy
AboubakrElnashar
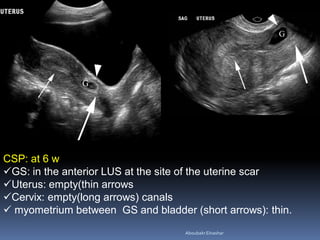
CSP: at 6 w
GS: in the anterior LUS at the site of the uterine scar
Uterus: empty(thin arrows
Cervix: empty(long arrows) canals
 myometrium between GS and bladder (short arrows): thin.
AboubakrElnashar
Transverse TVS color Doppler: flow around G S
AboubakrElnashar
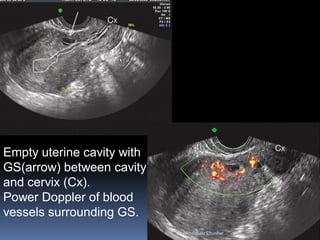
Empty uterine cavity with
GS(arrow) between cavity
and cervix (Cx).
Power Doppler of blood
vessels surrounding GS.
AboubakrElnashar
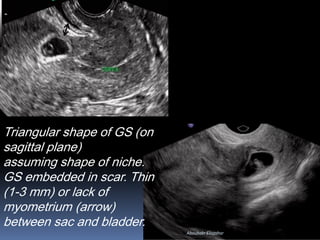
Triangular shape of GS (on
sagittal plane)
assuming shape of niche.
GS embedded in scar. Thin
(1-3 mm) or lack of
myometrium (arrow)
between sac and bladder.
Aboubakr Elnashar
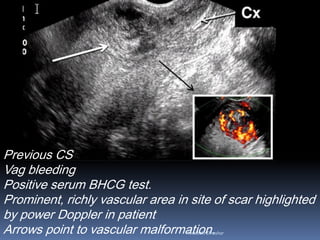
Previous CS
Vag bleeding
Positive serum BHCG test.
Prominent, richly vascular area in site of scar highlighted
by power Doppler in patient
Arrows point to vascular malformation.Aboubakr Elnashar
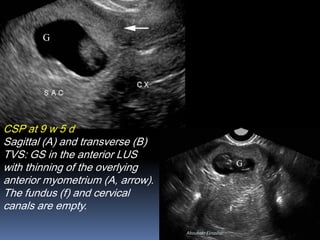
CSP at 9 w 5 d
Sagittal (A) and transverse (B)
TVS: GS in the anterior LUS
with thinning of the overlying
anterior myometrium (A, arrow).
The fundus (f) and cervical
canals are empty.
Aboubakr Elnashar
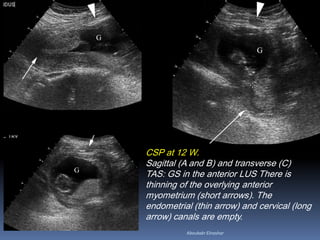
CSP at 12 W.
Sagittal (A and B) and transverse (C)
TAS: GS in the anterior LUS There is
thinning of the overlying anterior
myometrium (short arrows). The
endometrial (thin arrow) and cervical (long
arrow) canals are empty.
Aboubakr Elnashar
MRI
Indication
1. US is equivocal or inconclusive before
intervention or therapy.
2. To measure the lesion volume to help assess
the indication for and success of local MTX tt.
Aboubakr Elnashar
Sagittal, coronal, and transverse sections of T1-
and T2-weighted sequences:
1. GS embedded in the anterior LUS
2. Pelvic anatomy
intraoperative orientation
myometrial invasion and bladder involvement
T1: fat: bright . fluid: dark
T2: fat: intermediate-bright. fluid: bright
AboubakrElnashar
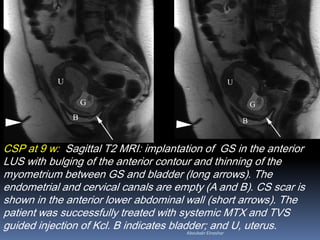
CSP at 9 w: Sagittal T2 MRI: implantation of GS in the anterior
LUS with bulging of the anterior contour and thinning of the
myometrium between GS and bladder (long arrows). The
endometrial and cervical canals are empty (A and B). CS scar is
shown in the anterior lower abdominal wall (short arrows). The
patient was successfully treated with systemic MTX and TVS
guided injection of Kcl. B indicates bladder; and U, uterus.Aboubakr Elnashar
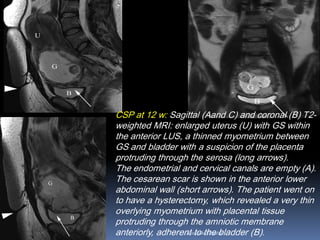
CSP at 12 w: Sagittal (Aand C) and coronal (B) T2-
weighted MRI: enlarged uterus (U) with GS within
the anterior LUS, a thinned myometrium between
GS and bladder with a suspicion of the placenta
protruding through the serosa (long arrows).
The endometrial and cervical canals are empty (A).
The cesarean scar is shown in the anterior lower
abdominal wall (short arrows). The patient went on
to have a hysterectomy, which revealed a very thin
overlying myometrium with placental tissue
protruding through the amniotic membrane
anteriorly, adherent to the bladder (B).Aboubakr Elnashar
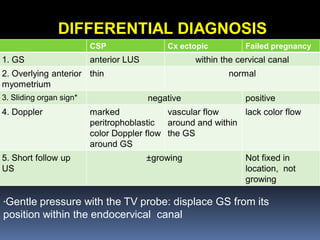
DIFFERENTIAL DIAGNOSIS
Failed pregnancyCx ectopicCSP
within the cervical canalanterior LUS1. GS
normalthin2. Overlying anterior
myometrium
positivenegative3. Sliding organ sign*
lack color flowvascular flow
around and within
the GS
marked
peritrophoblastic
color Doppler flow
around GS
4. Doppler
Not fixed in
location, not
growing
±growing5. Short follow up
US
*Gentle pressure with the TV probe: displace GS from its
position within the endocervical canal
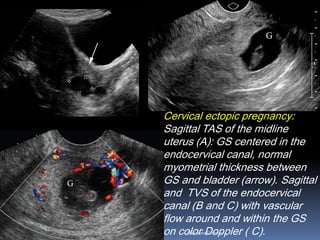
Cervical ectopic pregnancy:
Sagittal TAS of the midline
uterus (A): GS centered in the
endocervical canal, normal
myometrial thickness between
GS and bladder (arrow). Sagittal
and TVS of the endocervical
canal (B and C) with vascular
flow around and within the GS
on color Doppler ( C).Aboubakr Elnashar
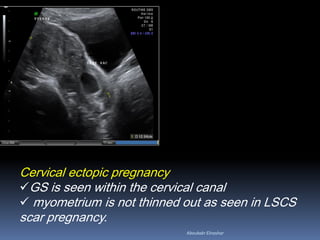
Cervical ectopic pregnancy
GS is seen within the cervical canal
 myometrium is not thinned out as seen in LSCS
scar pregnancy.
Aboubakr Elnashar
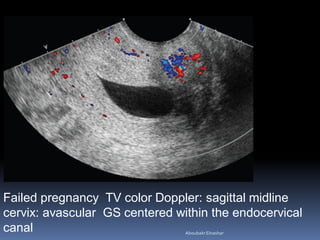
Failed pregnancy TV color Doppler: sagittal midline
cervix: avascular GS centered within the endocervical
canal AboubakrElnashar
3. MANAGEMENT
Objective
 eliminating GS
preserving fertility
No universal tt guidelines
No clear conclusion:
most effective
 least or no complications.
AboubakrElnashar
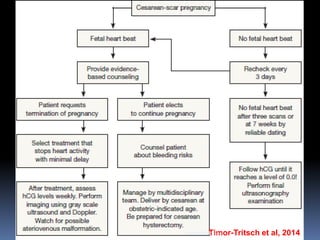
Timor-Tritsch et al, 2014AboubakrElnashar
 Treatment should be individualized, based on
1. Patient’s age
2. Number of children.
3. Number of previous CS
4. Anterior uterine wall thickness
{when the trophoblast reaches the bladder-
uterine space: Non surgical tt}
5. Expertise of the clinicians
AboubakrElnashar
Gynecologic surgeons:
laparoscopy, and hysteroscopy or
laparotomy
Obstetricians, radiologists, and IVF specialists:
IM MTX or
US local MTX (or Kcl)
UAE: occasionally
Aboubakr Elnashar
Counseling of the patient
Immediate and decisive action to prevent further
growth of the embryo or fetus.
Options:
1. Continuation of the pregnancy
Successful births
uneventful term pregnancy: poor.
Hysterectomy rate: 71%
{increased risk of placenta previa/accreta and
massive hge}
AboubakrElnashar
2. Termination of the pregnancy in 1st T
Substantial hge: 20%-40%
Hysterectomy: substantially lower.
Termination: Recommended particularly when
Early evidence of progression toward the abdominal
cavity or bladder
{increased risk of life-threatening complications and
loss of fertility}.
AboubakrElnashar
Potential complications
751 cases reviewed, 21.8% resulted in major surgery or interventional
radiology procedures (primary or emergency). The total planned primary
(nonemergency) interventions performed were 66 (8.7%), which included 3
hysterectomies, 14 laparotomies, and 49 uterine artery embolizations or
ligations. There were 98 (13.0%) emergency interventions, which included 36
hysterectomies, 40 laparotomies, and 22 uterine artery embolizations or
ligations. (Timor-Tritsch et al, 2014).
(Immediate or delayed): Need
secondary tt for blood loss ≥200 mL or
blood transfusion.
Complications are most often when the following
tt used alone:
• Single IM MTX
• D&C
• UAE AboubakrElnashar
lowest complication rate:
1. Local and US directed MTX injection with or
without additional IM MTX
2. Surgical excision by hysteroscopic guidance
AboubakrElnashar
Management approaches
I. Surgical: Excision
Laparotomy or
Hysterectomy, or
Laparoscopic or
Hysteroscopic followed by D&C
II. Minimally invasive
local injection of MTX or Kcl or
UAE in combination with IM. MTX
Medical tt alone: not recommended
Aboubakr Elnashar
 Medical
1. Systemic, single-dose MTX
1 mg/kg or 50 mg/m2 of body surface area.
complication rate: 64.6%
{second tt when the fetal heart beat did not cease after
several days}
High failure rate {slow action and questionable
ability to stop cardiac activity and placental
expansion}.
The expected result can take days, and all the while GS, the
embryo or fetus, and its vascularity are growing. Secondary
tt has to address a larger gestation with more abundant
vascularization.
Aboubakr Elnashar
Systemic MTX as a single tt should be avoided.
1. Waiting days for its effect to stop the heart beats, which
may not happen.
2. It also led to the additional growth of the embryo/fetus as
well as the vascularization
of GS
3. Wastes precious time
Aboubakr Elnashar
2. Systemic, multidose, sequential MTX
Two to three IM (1 mg/kg BW or 50 mg/mm2 of surface
area) at an interval of 2 or 3 days over the course of a week.
Cumulative adverse effects on the liver and bone
marrow
Success rate: 75%
 Hysterectomy: 6%
Best results: βHCG ≤ 5000 mU/mL.
Fibrous tissue within the scar around GS can
delay systemic MTX absorption into GS.
Aboubakr Elnashar
Minimally invasive.
1. Intragestational-sac injection of MTX or Kcl,
with US guidance
 Indications
 hemodynamically stable
 unruptured CSP
 ≤8w gestation
 myometrial thickness between GS and bladder.:
≤ 2 mm
AboubakrElnashar
Approach:
 TV approach is favored over TA
1. better visualization of the needle
2. shorter distance to reach the sac
3. decreased risk of bladder injury
 TAS guidance:
slighter higher complication rate (15%) than those
using TVS guidance.
AboubakrElnashar
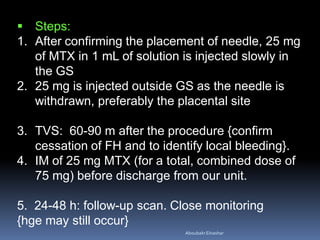
 Steps:
1. After confirming the placement of needle, 25 mg
of MTX in 1 mL of solution is injected slowly in
the GS
2. 25 mg is injected outside GS as the needle is
withdrawn, preferably the placental site
3. TVS: 60-90 m after the procedure {confirm
cessation of FH and to identify local bleeding}.
4. IM of 25 mg MTX (for a total, combined dose of
75 mg) before discharge from our unit.
5. 24-48 h: follow-up scan. Close monitoring
{hge may still occur}
AboubakrElnashar
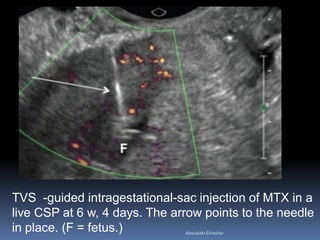
TVS -guided intragestational-sac injection of MTX in a
live CSP at 6 w, 4 days. The arrow points to the needle
in place. (F = fetus.) AboubakrElnashar
Advantages
No anesthesia.
Complications: fewest :10.8%
most effective intervention
decrease the need for additional interventions
provides a higher concentration of the
embryocide locally
avoidance of systemic side effects
more rapid interruption of the pregnancy.
AboubakrElnashar
Aspiration of gestational sac fluid,
injection of methotrexate in the sac,
injection of homeostatic agent and pituitrin in the
uterine muscle layer, and
injection of triple anti-inflammatory drugs around
the uterus in 12 patients with CSP. (Kong et al, 2014)
Ultrasonography-guided multidrug interventional
therapy for CSP is a new, safe, effective, minimally
invasive method.
2. Use of a Foley balloon catheter
Indications:
1. Alone: (usually in gestations of 5–7 w) in the
hope of stopping the evolution of the pregnancy
by placing pressure on a small GS.
2. In conjunction with another tt
3. Backup if bleeding occurs.
French-12 size 10-mL silicone balloon catheter, or
French-14 catheter with a 30-mL balloon
AboubakrElnashar
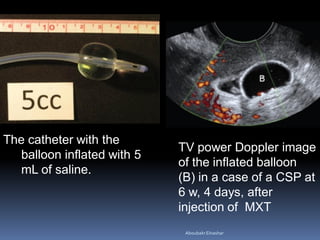
The catheter with the
balloon inflated with 5
mL of saline.
TV power Doppler image
of the inflated balloon
(B) in a case of a CSP at
6 w, 4 days, after
injection of MXT
AboubakrElnashar
Steps:
GA: not required.
TAS guidance Or TVS guidance
{allow for more precise placement and assess the
pressure, avoiding over inflation of the balloon}
Catheter is kept 24 to 48 h,
with the outer end of the catheter fastened to the
patient’s thigh.
Antibiotics
Reevaluate after 48H
Aboubakr Elnashar
3. UAE, alone or in combination
 Indication:
1. As a rescue procedure in the case of significant
bleeding or an A-VM
2. Concurrent with MTH
Not as a primary tt
{delay between tt and effect allows the gestation to
grow and vascularity to increase}
Disadvantages:
1. GA
2. Complication rate: 47%
3. Not the best 1st -line tt
Aboubakr Elnashar
Surgical excision
laparoscopy or laparotomy may be best tt
No response to conservative medical tt
Patient late to present.
Allows for revision of the CS scar with new uterine
closure that may minimize risk of recurrence.
Risks
postoperative adhesions: impair future fertility
increased size of surgical wounds
longer hospital stay and recovery
increased risk of future placenta previa/accreta.
AboubakrElnashar
AboubakrElnashar
1. Excision by laparotomy, alone or in
combination with hysteroscopy
18 cases:
5 complications
and only when used in an emergency situation.
Aboubakr Elnashar
2. Laparoscopic excision
Complication rate: 30.6%
Laparoscopy combined with hysteroscopy:
Complication rate: 20%
Aboubakr Elnashar
3. Hysteroscopy, alone or in combination
complication rate: 13.8%.
Hysteroscopy combined with TA US guidance:
9 cases: no complications.
reasonable operative solution
Hysteroscopy combined with mifepristone:
complication rate:17%.
Aboubakr Elnashar
4. Suction aspiration or D&C, alone or in
combination
Isolated D & C should be avoided.
1. Trophoblastic tissue and villi are implanted
within the myometrium: D &C is unlikely to expel
the GS without rupturing the uterine wall or
damaging the bladder
2. : massive bleeding: emergency laparotomies:
loss of the uterus.
3. {exposed vessels in the cervical scar tissue
bleed {no muscle grid to contract and contain
the profuse bleeding}.
4. Complication rate: 62% (29%–86%).
bleeding complications, necessitating 3rd -line tt that
almost always was surgical. AboubakrElnashar
 MTX followed by suction curettage:
Mean blood loss: 707 mL (100–2,000 mL)
tt failure:
3 out of 45 despite insertion of a Foley balloon
catheter.
If D&C is still the preferred tt of choice,
blood products should be available
balloon catheter should be inserted in the cervix
Preoperative determination of CSP implantation depth and
extent is important in selecting candidates for surgical
treatment. Primary single-step surgical evacuation was
successful in most patients with superficial implantation, but
patients should be informed of the possibility of salvage
interventions before undergoing surgical evacuation (Kong et
al, 2014).
Aboubakr Elnashar
FOLLOW-UP
{Placenta is implanted mostly within fibrous
tissue, absorption of the GS is slow after med tt}
1. 9 w to obtain clearance of βHCG
2. 3 months for clearance of GS on TVS
 1. βHCG: weekly until it is undetectable
2. TVS: Monthly to evaluate the size of retained
products of conception
AboubakrElnashar
3. SIS:
in a nonpregnant patient
uterine wall integrity
size of the cesarean scar
which may relate to the possibility of uterine scar
complications in future pregnancies.
4. Early TVS
After CSP
After CS
to confirm an intrauterine location of the new
gestation.
Aboubakr Elnashar
5. Avoiding pregnancy
No guidelines
12 to 24 months.
6. Repair of scar before future pregnancies.
not known whether required or not
Severely deficient uterine scars: 10% of women
who have had prior CS, but CSP are much more
rare.
Aboubakr Elnashar
Outcomes
Uneventful viable pregnancies have been
reported after all modalities of conservative
management.
Recurrence rate: 5%
IU pregnancy: 95%
spontaneous pregnancy: 88%
Normal pregnancy: 65%
Spontaneous abortion: 35%
higher than expected
AboubakrElnashar
4. PREVENTION OF CSP
1. Surgical repair of the uterine dehiscence (niche)
in patients with previous CS while not pregnant.
Ben Nagi et al reported on a successful surgical repair
Donnez et al: hysteroscopic repair
Klemm et al: laparoscopic-assisted vaginal repair
Yalcinkaya et al: robotic-assisted laparoscopic repair
 More research is necessary before making
recommendations for such surgical tt to prevent CSP.
Aboubakr Elnashar
2. Specific surgical technique
single- or double-layer closure of the incision
can minimize or avoid a CSP
Aboubakr Elnashar
SUMMARY
 CSP
 An uncommon but potentially life-threatening
 The incidence is rising as CSR is rising.
 Precursor of morbidly adherent placenta
 Do not confuse CSP with ectopic pregnancy
 Early diagnosis is important. TVS is the most
effective and preferred diagnostic tool.
 A key first step: Determine whether heart activity is
present?
AboubakrElnashar
 If heart activity is documented: Counsel the patient:
inform the patient of the risks of pregnancy
continuation.
 If continuation: an additional counseling session:
risks
 If termination: a reliable tt that stops fetal heart beat
without delay.
 Avoid single tts unlikely to be effective:
 D&C
 suction curettage
 single-dose IM MTX, and
 UAE
AboubakrElnashar
Consider combination treatments: best results.
direct injection of MTX or Kcl into GS with TVS
guidance.
Keep a catheter at hand.
At the time of discharging after a CS: in a future
pregnancy, an early visit for TVS is important.
AboubakrElnashar
ThankYou
https://www.facebook.com/groups/
227744884091351/
AboubakrElnashar
(Timor-Tritsch et al, 2012).
Timor-Tritsch et al (2012.)
AboubakrElnashar
Management
31 primary approaches:
systemic therapy
local injection
surgical aspiration of GS
hysteroscopic, laparoscopic, and open removal.
AboubakrElnashar
 Intracervical vasopressin should also be
considered.
AboubakrElnashar
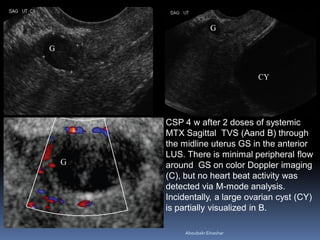
CSP 4 w after 2 doses of systemic
MTX Sagittal TVS (Aand B) through
the midline uterus GS in the anterior
LUS. There is minimal peripheral flow
around GS on color Doppler imaging
(C), but no heart beat activity was
detected via M-mode analysis.
Incidentally, a large ovarian cyst (CY)
is partially visualized in B.
AboubakrElnashar
AboubakrElnashar
ArchGynecol Obstet. 2014 Dec 23. [Epub ahead of print]
Ultrasonography-guided multidrug stratification interventional therapy
for cesareanscar pregnancy.
Kong D1, Dong X, QiY.
Author information
Abstract
PURPOSE:
To explore the clinical value of ultrasonography-guided multidrug stratification
interventional therapy for cesarean scar pregnancy (CSP).
METHODS:
Aspiration of gestational sac fluid, injection of methotrexate in the sac, injection of
homeostatic agent and pituitrin in the uterine muscle layer, and injection of triple
anti-inflammatory drugs around the uterus in 12 patients with CSP.The lesion
volume, serum β-hCG level, and blood flow were observed.
RESULTS:
The mean β-hCG level continued to decrease posttreatment, and the greatest
reduction occurred in week 1.The mean number of days needed for serum β-hCG
values to decrease to normal level was 39.1 ± 10.1 days. Mass volumes reduced and
the mean number of days for the masses to disappear was 24.6 ± 14.1 days.The
blood flow around the lesions continued to decrease.
CONCLUSIONS:
Ultrasonography-guided multidrug interventional therapy for CSP is a new, safe,
effective, minimally invasive method.
AboubakrElnashar
Ultrasound Med. 2014 Sep;33(9):1533-7. doi: 10.7863/ultra.33.9.1533.
Heterotopic cesarean scar pregnancy: diagnosis, treatment, and
prognosis.
OuYang Z1, Yin Q2, Xu Y2, Ma Y2, Zhang Q2, Yu Y2.
Author information
Abstract
Heterotopic cesarean scar pregnancy is a rare, life-threatening form of
ectopic pregnancy. To provide information regarding the clinical
manifestations, diagnosis, management, and prognosis of this condition,
we reviewed all cases reported in the English literature. All literature on
heterotopic cesarean scar pregnancy was retrieved by searching the
PubMed database and tracking references of the relevant literature. Full
texts were reviewed, and clinical manifestations, diagnostic methods, and
the relationship between the treatment and prognosis were summarized. A
total of 14 patients with heterotopic cesarean scar pregnancies were
identified, including 6 spontaneous pregnancies and 8 following in vitro
fertilization-embryo transfer. Gestational ages at diagnosis ranged from 5
weeks to 8 weeks 4 days. Only 5 cases presented with vaginal bleeding,
and the others were asymptomatic. All 14 cases were diagnosed by
transvaginal sonography. One patient with no future fertility requirements
underwent pregnancy termination by methotrexate. Of the remaining 13
patients who desired to preserve their intrauterine gestations, 10 were
AboubakrElnashar
Fertil Steril. 2014 Oct;102(4):1085-1090.e2. doi:
10.1016/j.fertnstert.2014.07.003. Epub 2014 Aug 11.
Outcomes of primary surgical evacuation during the first trimester in
different types of implantation in women with cesarean scar pregnancy.
Cheng LY1, Wang CB1, Chu LC1, Tseng CW1, Kung FT2.
Author information
Abstract
OBJECTIVE:
To assess the efficacy and safety of primary surgical evacuation therapy
for cesarean scarpregnancy (CSP) of the first trimester, and to evaluate its
possible prognostic factors.
DESIGN:
Retrospective consecutive cohort study.
SETTING:
Tertiary care university hospital.
SUBJECT(S):
A cohort of patients with CSP and clear ultrasound images who underwent
primary surgical evacuation from January 2000 to December 2012.
INTERVENTION(S):
Patients fulfilling the ultrasound criteria of CSP were further classified into
superficial and deep groups according to their implantation locations and
extents. The final decision on the method of treatment, including
methotrexate chemotherapy, surgical evacuation, and others, was made by
I. All are correct regarding CS scar
pregnancy (CSP) except:
1.Incidence is rising
2.Asymptomatic: in 1/3 of cases
3.Time of presentation is commonly 2nd trimester
4.Diagnosis is missed in 14% of cases
AboubakrElnashar
II. Sonographic criteria of CSP include
all except
1. Empty uterus with a clearly visualized
endometrium
2. Empty cervical canal
3. Gestational sac:
 within the anterior portion of lower uterine
segment
at site of the cesarean scar
4. Sliding organ sign is positive
AboubakrElnashar
III. For treatment of CSP, all are correct
except
1.Anterior uterine wall thickness is important
2.With pregnancy continuation, hysterectomy
rate is 17%
3.Termination of the pregnancy in first
trimester is recommended
4.Immediate and decisive action is
recommended
AboubakrElnashar
IV. All are correct regarding CSP treatment
except:
1. Complications are most often when single
IM Methotrexate or D&C
2. Complications are at lowest rate with
Local and US directed MTX injection with
or without additional IM MTX
3. Use of a Foley balloon catheter is not
recommended
4. laparoscopy or laparotomy with excision
of the pregnancy may be best treatment
AboubakrElnashar
V. For follow up after treatment of CSP
all are correct except
1. 5 w are required to obtain clearance of
βHCG
2. TVS is done monthly to evaluate the size
of retained products of conception
3. Avoiding pregnancy for 12 to 24 months.
4. In a future pregnancy, an early visit for
TVS is important.
AboubakrElnashar