ANTI ARRHYTHMIC
DRUG THERAPY
Dr.Vinay verma group:512
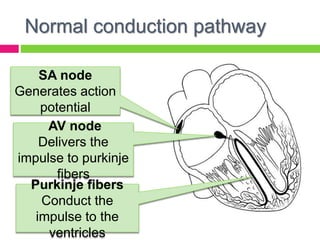
Normal conduction pathway
SA node
Generates action
potential
AV node
Delivers the
impulse to purkinje
fibers
Purkinje fibers
Conduct the
impulse to the
ventricles
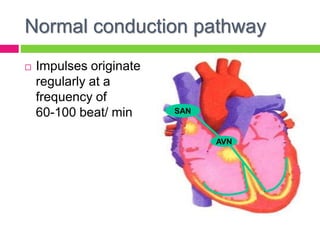
SAN
AVN
Impulse conductionNormal conduction pathway
 Impulses originate
regularly at a
frequency of
60-100 beat/ min
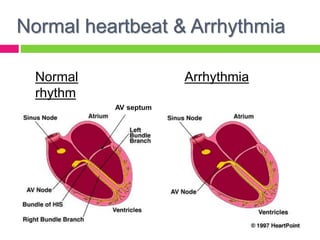
Normal heartbeat & Arrhythmia
Normal
rhythm
Arrhythmia
AV septum
Management of Arrhythmia
 Pharmacological therapy (Antiarrhythmic
Drugs)
 Cardioversion
 Pacemaker therapy
 Surgical therapy e.g. aneurysmal excision
 Interventional therapy “ablation”
Antiarrhythmic Drugs
Pharmacologic rationale & Goal
 The ultimate goal of antiarrhythmic drug
therapy:
 Restore normal sinus rhythm and conduction
 Prevent more serious and possibly lethal
arrhythmias from occurring.
 Antiarrhythmic drugs are used to:
 Decrease conduction velocity
 Change the duration of the effective refractory
period (ERP)
 Suppress abnormal automaticityShrivatsa U, Wadhani M, Singh AB; Mechanisms of antiarrhythmic drug action & their clinical relevance for
controlling disorders of cardiac rhythm; Curr Cardiol Rep 2002;4;401
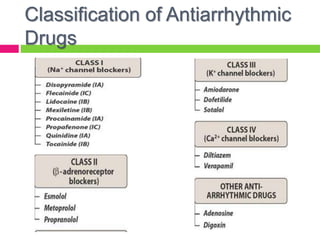
Classification of Antiarrhythmic
Drugs
Classified a/c to Vaughan William into four
classesClass Mechanism Action Notes
I
Na+ channel
blocker
Change the slope of phase 0
Can abolish
tachyarrhythmia
caused by reentry
circuit
II β blocker
↓heart rate and conduction
velocity
Can indirectly alter
K and Ca
conductance
III
K+ channel
blocker
1. ↑action potential duration
(APD) or effective refractory
period (ERP).
2. Delay repolarization.
Inhibit reentry
tachycardia
Ca++ channel Slowing the rate of rise in phase
↓conduction
Classification of Antiarrhythmic
Drugs
Treatment of tachyarrhythmias:
 Class I drugs (Membrane stabilizing drugs) :
Mechanism:
 Class I drugs block fast Na+ channels, thereby
Reducing the rate of phase 0
depolarization
Prolonging the effective refractory period
Increasing the threshold of excitability
Reducing phase 4 depolarization
 These drugs also have local anestheticWoosely RL. Antiarrhythmic drugs. Hurst’s The Heart (Ed. Fuster V, Alexander RW, O’Rourke RA,
et al.) 10th edition.2001;1:899–924
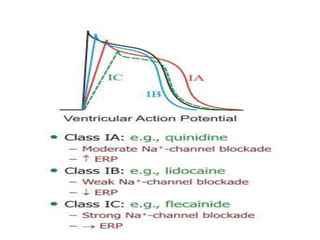
Class IA
1. Quinidine
 Alkaloid – cinchona , dextro isomer of quinine.
 Blocks sodium channel & potassium channel
also
 Anti-muscarinic and Alpha blocking action
 Administered orally & is rapidly absorbed from
gastrointestinal tract
 Hydroxylated in the liver
 t1/2 of approximately 5—12 hours, longer in
hepatic or renal disease & in heart failure
 Bitter and irritant
 Inhibitor of CYP P450 system.
1. Quinidine
 ↑↑ plasma conc of digoxin by displacing it from
tissue binding sites & decreasing its renal &
biliary clearance.
 Uses:
 Atrial fibrillation
 Ventricular tachycardia
 Adverse effects :
 GIT : Diarrhea, nausea, vomiting and
cinchonism
 Thrombocytopenia
 Precipitate torsade de pointes by prolonging
1. Quinidine
 Drug interactions
 Increases digoxin plasma levels &risk of
digitalis toxicity
 t1/2 reduced by agents that induce drug-
metabolizing enzymes (phenobarbital,
phenytoin)
 May enhance the activity of coumarin
anticoagulants & other drugs metabolized by
hepatic microsomal enzymes
 Cardiotoxic effects exacerbated by
2. Procainamide
 Like quinidine, but
 Safer to use intravenously
 Produces fewer adverse GI effects
 Acetylated in liver to N-acetylprocainamide
(NAPA)
 Eliminated by the kidney (t ½ -3 – 5 hrs)
 More likely than quinidine to produce severe or
irreversible heart failure
 Adverse effects
 SLE like syndrome consisting of arthralgia and
arthritis specially in slow acetylators
Class IB
1. Lidocaine:
 Least cardiotoxic : (t ½ - 1.5 - 2 hrs)
 Block inactivated Na channels : preferred for
partially depolarized cells in ischemic area
 High first pass metabolism – not given orally
 Used in:
 Ventricular arrhythmia
 Digoxin induced arrhythmia
 Main toxicity:
Neurological – drowsiness, nystagmus &
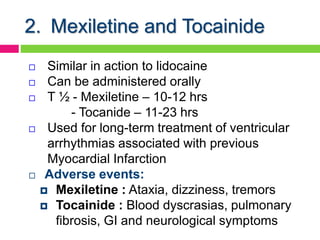
2. Mexiletine and Tocainide
 Similar in action to lidocaine
 Can be administered orally
 T ½ - Mexiletine – 10-12 hrs
- Tocanide – 11-23 hrs
 Used for long-term treatment of ventricular
arrhythmias associated with previous
Myocardial Infarction
 Adverse events:
 Mexiletine : Ataxia, dizziness, tremors
 Tocainide : Blood dyscrasias, pulmonary
fibrosis, GI and neurological symptoms
Class IC
 Class of potent Na channel blocker
 Drugs of this class have negative inotropic effect
 High pro-arrhythmogenic potential – sudden
death
Class IC
1.Flecainide
 Orally active antiarrhythmic
 Metabolized by microsomal enzymes (t ½ - 20
hrs)
 Used for ventricular tachyarrhythmias &
maintenance of sinus rhythm in patients with
paroxysmal atrial fibrillation and/or atrial flutter
& WPW
 C/I in pts with structural heart disease
 Adverse events :
 Heart failure, dizziness, headache , Blurred
2. Propafenone
 Spectrum of action similar to that of quinidine
 Possesses β-adrenoceptor antagonist activity
 Metabolized by hepatic microsomal enzymes
 T ½ - 2 – 10 hrs
 Approved for treatment of supraventricular
arrhythmias and suppression of life-threatening
ventricular arrhythmias
 C/I in structural heart disease
 Adverse events:
 Nausea, Vomitting, altered taste
Class II
 They Are β-adrenoceptor antagonists,
including propranolol
 Act by reducing sympathetic stimulation
 Inhibit phase 4 depolarization
 Depress automaticity
 Prolong AV conduction
 Decrease
 Heart rate
 Contractility
Class II
 Major drugs
Propranolol, a nonselective β-adrenoceptor
antagonist
Acebutolol & esmolol, more selective β1-
adrenoceptor antagonists
Used to treat ventricular arrhythmias
Propranolol, metoprolol, nadolol, and
timolol frequently used to prevent recurrent
MI
Class II
 Absorption and elimination:
 Propranolol: oral, iv
 Esmolol: iv only (very short acting T½, 9 min)
 Cardiac effects
  APD and refractory period in AV node to
slow AV conduction velocity
  decrease phase 4 depolarization
(catecholamine dependent)
Class II
 Uses:
 Treating sinus and catecholamine dependent
tachyarrhythmias
 Converting reentrant arrhythmias in AV
 Protecting the ventricles from high atrial rates
 Side effects:
 Bronchospasm
 Hypotension
 Don’t use in partial AV block or ventricular
failure
Class III
 Class III drugs:
Prolong action potential duration
Prolong effective refractory period
 Act by:
interfering with outward K+ currents or
slow inward Na+ currents
1. Amiodarone
 Structurally related to thyroxine.
 Net effect:
 Increases refractoriness
 Depresses sinus node automaticity
 Slows conduction.
 Long half-life (14—100 days) ↑ risk of toxicity
 Plasma conc not well correlated with its effects
 After parenteral administration:
 Electrophysiologic effects →within hours
 Effects on abnormal rhythms may not be seen
for several days
1. Amiodarone
 Antiarrhythmic effects may last for weeks or
months after the drug is discontinued
 Uses:
Refractory life-threatening ventricular
arrhythmias in preference to lidocaine
T/t of atrial and/or ventricular arrhythmias
 Adverse effects
 Pulmonary fibrosis
 Skin pigmentation
 Corneal deposits
 Interferes with the thyroid function
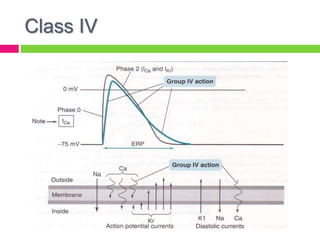
Class IV
 Mechanism
 Class IV drugs selectively block L-type calcium
channels.
 These drugs prolong nodal conduction and effective
refractory period and have predominate actions in
nodal tissues
Class IV
Verapamil
 Phenylalkylamine that blocks both activated and
inactivated slow calcium channels.
 Tissues that depend on L-type calcium channels
are most affected
 Has equipotent activity on the AV and SA nodes
and in cardiac and vascular muscle tissues
 Useful in:
 Supraventricular tachycardia
 Atrial flutter and fibrillation
Verapamil
 Adverse effects:
Negative inotropic action that limits its use
in damaged hearts;
Can lead to AV block when given in large
doses or in patients with partial blockage.
Can precipitate sinus arrest in diseased
patients
Causes peripheral vasodilation.
Miscellaneous Antiarrhythmic
Drugs
 Adenosine
 Acts through specific purinergic (P1)
receptors.
 Causes an increase in potassium efflux and
decreases calcium influx.
 This hyperpolarizes cardiac cells and
decreases the calcium-dependent portion of
the action potential.
 Drug of choice for the treatment of
paroxysmal supraventricular tachycardia,
including those associated with Wolff-
Digoxin
 Mode of action:
Na-K ATPase inhibition
Positive inotrope
Vagotonic
 T ½ - Premature (61hrs), Neonate (35hrs), Infant
(18hrs), Child (37hrs), Adult (35-48hrs )
 Uses:
Supraventricular Tachycardia
Digoxin
 Interactions:
 Coumadin- ↑ PT
 ↑ Digoxin level
 Quinidine, amiodarone, verapamil
 ↓ renal function/renal tubular excretion
(Spironolactone)
 Worse with ↓ K+, ↓ Ca++
Investigational Drugs
 Analogs of Amiodarone are being developed
such as:
 ATI-2001
 Dronedarone
 SR-33589
 Dronedarone:
 Resonable safety profile
 Well characterized pharmacokinetic &
pharmacodynamic profile
 Effective in doses lower than 2000 mg/dayWolbrette D et al ; Dronedarone for the treatment of atrial fibrillation and atrial flutter: Approval and
efficacy ; Vasc Health Risk Manage 2010;6;517
Investigational Drugs
 Azimilide :
 Potassium-channel blocking properties
 Prolongs cardiac AP & refractory periods
 Found to be effective in patients with
symptomatic tachyarrhythmias and ICDs
therapies in recent studies
 Other drugs, such as Ambasilide, are also in
clinical development
 Chromanol 293B is in preclinical testing
Reynolds RM, Josephson ME. Sustained ventricular tachycardiain ischemic cardiomyopathy : current
management. ACC Current Journal Review 2005;14:63-71
Treatment of bradyarrhythmias
 Atropine
 Blocks the effects of acetylcholine.
 Elevates sinus rate and AV nodal and sinoatrial
(SA) conduction velocity, & decreases
refractory period
 Used to treat bradyarrhythmias that
accompany MI
 Adverse effects:
 Dry mouth, mydriasis, and cycloplegia;
 May induce arrhythmias.
T/t of Atrial Flutter/Fibrillation
1. Reduce thrombus formation by using
anticoagulant warfarin
2. Prevent the arrhythmia from converting to
ventricular arrhythmia
 First choice: class II drugs:
 After MI or surgery
 Avoid in case of heart failure
 Second choice: class IV drugs
 Third choice: digoxin
 Only in heart failure of left ventricular
T/t of Atrial Flutter/Fibrillation
3. Conversion of the arrhythmia into normal sinus
rhythm
 Class III:
 IV ibutilide, IV/oral amiodarone, or oral sotalol
 Class IA:
 Oral quinidine + digoxin (or any drug from the 2nd
step)
 Class IC:
 Oral propaphenone or IV/oral flecainide
 Use direct current in case of unstable
hemodynamic patient
Fuster V et al; ACC/AHA/ESC Guidelines for the management of patients with atrial fibrillation. Circulation
T/t of Ventricular Arrhythmia
 Premature ventricular beat (PVB)
 First choice: class II
 IV followed by oral
 Early after MI
 Second choice: amiodarone
 Avoid using class IC after MI  ↑ mortality
T/t of Ventricular Tachycardia
 First choice: Lidocaine IV
 Repeat injection if needed
 Second choice: procainamide IV
 Adjust the dose in case of renal failure
 Third choice: class III drugs
 Especially amiodarone and sotalol
Grant AO, Recent advances in the treatment of arrhythmia. Circ J 2003;67;651
Thank You