


















































LABORATORY
INVESTIGATIONS IN
COAGULATION
DISORDERS
PRESENTER : DR. HAJRA K. MEHDI
MODERATOR : DR. S. DAS
CONTENTS
 INTRODUCTION
 SPECIMEN COLLECTION AND PROCESSING
 LABORATORY INVESTIGATIONS OF COAGULATION
SYSTEM
 SCREENING TESTS
 CONFIRMATORY TESTS
 TESTS TO EVALUATE CIRCULATING INHIBITORS
 LAB INVESTIGATIONS FOR FIBRINOLYTIC SYSTEM
 AUTOMATION
 SUMMARY
 REFERENCES
INTRODUCTION
 Hemostasis is a process by which the body prevents
loss of blood from the vascular system and maintains it
in a fluid state.
 Involves a series of complex and regulated events
linking platelets , vascular endothelial cells and
coagulation factors.
Hemostasis includes
 Primary hemostasis
 Secondary hemostasis
Coagulation
factors
Phospholipids
CA2+
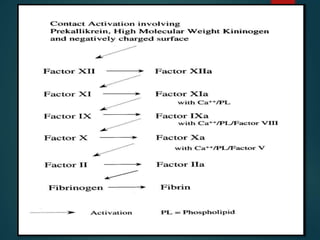
Factor XIIa, XIa
Kallikrein
T-PA
U-PA
FIBRINOLYSISCLOTTING
ACTIVATORS
INHIBITORS
AT
Protein C, S
TFPI
α2Macroglobulin
α1Antitrypsin
C1 Inactivators
Heparin Cofactor
PAI- 1,2,3
α2- antiplasmin
α2- macroglobulin
TAFI
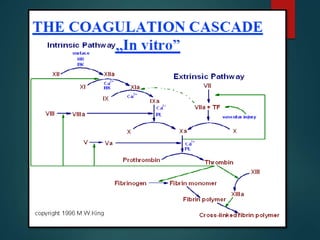
THE COAGULATION SYSTEM
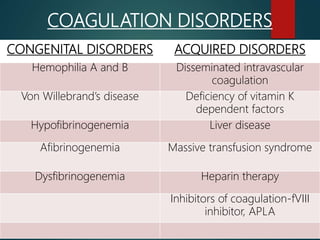
COAGULATION DISORDERS
CONGENITAL DISORDERS ACQUIRED DISORDERS
Hemophilia A and B Disseminated intravascular
coagulation
Von Willebrand’s disease Deficiency of vitamin K
dependent factors
Hypofibrinogenemia Liver disease
Afibrinogenemia Massive transfusion syndrome
Dysfibrinogenemia Heparin therapy
Inhibitors of coagulation-fVIII
inhibitor, APLA
SPECIMEN COLLECTION AND
PROCESSING
 Whole blood is aseptically collected by venipuncture.
 Anticoagulant of choice is 3.2% sodium citrate.
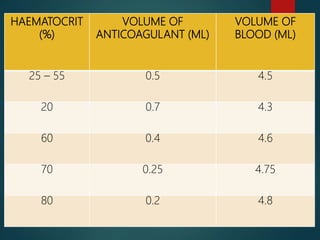
 Volume of anticoagulant necessary for a 5 ml blood
sample adjusted according to the hematocrit value.
 One may also choose to keep the anticoagulant volume of
0.5 ml constant and adjust the volume of added blood
according to the hematocrit.
 The volume of blood to be added (to 0.5 ml of 0.109M
citrate) is calculated from the formula:
(60 - hematocrit)/100 × 4.5
HAEMATOCRIT
(%)
VOLUME OF
ANTICOAGULANT (ML)
VOLUME OF
BLOOD (ML)
25 – 55 0.5 4.5
20 0.7 4.3
60 0.4 4.6
70 0.25 4.75
80 0.2 4.8
SPECIMEN PROCESSING
 Citrated whole blood is centrifuged to obtain plasma
for coagulation testing.
Platelet Poor Plasma:
 Blood sample is centrifuged at a minimum of 1700rpm
for at least 10 minutes (2500rpm for 15min) preferably
at 4°C in a refrigerated centrifuge.
 Open the samples at RT, separate and store the plasma
sample at 4°C as quickly as possible.
 When RT >25°C then labile coagulation proteins may
be affected, a refrigerated (4°C) centrifuge should be
used.
 Platelet poor plasma <10× 109/l
Samples for Immediate Testing:
 Samples should be tested within 4 hours of sample
collection when possible.
 Longer storage should be avoided for screening tests
and clotting factor assays.
 Samples for factor assays should be stored at 4°C
testing.
 Samples for screening tests and assay of factor VII
should be maintained at room temperature to avoid the
possibility of cold activation.
SPECIMEN PROCESSING
Deep Freezing of Plasma:
 Samples can be frozen for testing at a later stage.
 Storage at -70°C or lower is preferable (better) but
at -35°C is adequate for most tests.
 Storage at -20°C is usually inadequate.
 Double centrifugation should be used if samples are
frozen prior to analysis for lupus anticoagulant.
 Freezing and thawing is best avoided before APTT
determinations, since results obtained by some
can be affected.
SPECIMEN PROCESSING
1. SCREENING TESTS
 Prothrombin time
 Activated partial thromboplastin time
 Thrombin time
2. CONFIRMATORY TESTS FOR FACTOR ABNORMALITIES
 Reptilase time
 Mixing tests.
 Fibrinogen assay (modified Claus Assay)
LABORATORY INVESTIGATIONS OF
COAGULATION SYSTEM
 Platelet neutralizing procedure
 Lupus anticoagulant & antiphospholipid antibodies
TESTS TO EVALUATE CIRCULATING
INHIBITORS
 Detection of FDPs using latex agglutination method
 D-dimer test
 Euglobin clot lysis
LAB INVESTIGATIONS OF
FIBRINOLYTIC SYSTEM
SCREENING TESTS
PROTHROMBIN TIME
Principle:
 Measures the time for fibrin formation.
 Reflects the overall efficiency of the extrinsic system.
 Sensitive to changes in factor V, VII and X, and less so
to factor II (prothrombin).
 It is also unsuitable for detecting minor changes in
fibrinogen level
 May be abnormal if the fibrinogen level is very low or if
there is an inhibitor present.
 The sensitivity of the test is influenced by the reagent
and technique used and it is important to establish a
reference range locally.
REAGENTS
- Platelet poor plasma from the patient.
- Control plasma sample.
- Thromboplastin (this may contain calcium chloride).
- Calcium chloride – 0.025 mol/lit (only required if
thromboplastin reagent does not contain calcium).
INR
 INR – International Normalized Ratio.
 Was established by WHO and the international
committee on thrombosis and hemostasis on reporting
the result of PT.
 INR = (PT of Patient/Control PT)ISI
 Anticoagulant therapy control = 2.0-3.0
ISI
 International Sensitivity Index.
 Given by manufacturer.
 Reflects reagent sensitivity to different Vitamin K
dependent factor Deficiency.
RESULTS
Results can be expressed in
1. Mean of duplicate recordings in secs
2. INR = (PT of Patient/Control PT)ISI
NORMAL RANGE
 With rabbit thromboplastin : 11-16 secs
 With recombinant human thromboplastin : 10- 12 secs.
CAUSES OF PROLONGED PT
 Administration of oral anticoagulants drugs (vitamin K
anticoagulants).
 Liver diseases
 Vitamin K deficiency
 DIC
 Previously underdiagnosed factor VII, X, V or prothrombin
deficiency or defect.
ACTIVATED PARTIAL
THROMBOPLASTIN TIME
Principle:
 Measures the clotting time of plasma after the activation of
contact factors but without added tissue thromboplastin.
 Indicates the overall efficiency of the intrinsic pathway.
 It is also sensitive to circulating anticoagulants (inhibitors)
and heparin.
 Depends on contact factors, factors VIII, IX as well as X, V,
prothrombin and fibrinogen.
REAGENTS
 Platelet poor plasma
 Kaolin 0.5gm in 100ml barbitone buffered saline, pH 7.4
 Other can be used like silica, celite or elagic acid can
be used.
 Phospholipid
 Calcium chloride 0.025M
METHOD
1. Mix equal volumes of phospholipid reagent and the kaolin
kaolin suspension and leave in a glass tube in the water bath
at 37 degree.
2. Place 0.1ml of plasma into a new glass tube.
3. Add 0.2ml of kaolin-phospholipid solution, mix the
contents and start the stopwatch simultaneously.
4. Leave at 37 degrees for 10mins with occasional shaking.
5. At exactly 10mins, add 0.1ml of pre-warmed CaCl2 and
start a second stopwatch.
6. Record the time taken for the mixture to clot.
7. Repeat the test on both the patient and the control plasma
atleast once.
INTERPRETATION
Normal range: 30 – 40 seconds
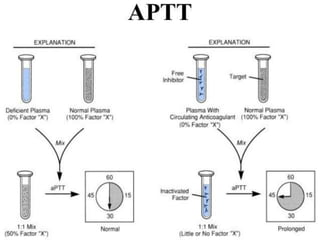
 A prolonged APTT with a normal PT indicates a possible
deficiency of factor VIII, IX, XI, XII, high molecular weight
kininogen, prekallikrein or the presence of an inhibitor.
 Example: APTT control : 35 sec
test : 60 sec
 If 50:50 mix : 42 sec – this is a good correction, i.e.
factor deficiency
60 – 42 = 18, 60 – 35 = 25,
25/2 = 12.5, 18 > 12.5
 If 50:50 mix : 52 sec – this is a poor correction, i.e.
probably an inhibitor is present.
60 – 52 = 8, 8 < 12.5
CAUSES OF PROLONGED APTT
 DIC
 Liver diseases
 Massive transfusion with stored blood.
 Administration of heparin or contamination with heparin.
 A circulating anticoagulant.
 Deficiency of coagulation factor other than factor VII.
THROMBIN TIME
Principle:
 The thrombin time reflects the reaction between thrombin
and fibrinogen.
Thrombin
Fibrinogen Fibrin
 Thrombin is added to the plasma and the clotting time is
measured.
 The Thrombin time is affected by the concentration and
reaction of fibrinogen, and by the presence of inhibitory
substances, including fibrinogen/FDP and heparin.
REAGENTS
 Platelet poor plasma.
 Thrombin solution which induces clotting of normal
plasma in about 15 seconds.
Normal range: 15 – 19 secs
METHOD – MANUAL
1. Pipette 0.2 ml test and control plasma into separate
glass clotting tubes.
2. Warm to 37oC.
3. Add 0.1 ml thrombin solution to each tube.
4. Start stopwatch for each tube.
5. Measure the clotting time and observe the nature of
clot.
6. Repeat procedure for patient and control plasma.
CAUSES OF PROLONGED TT
 Hypofibrinogenaemia as found in DIC and, more rarely, in
a congenital defect or deficiency.
 Raised concentrations of FDP, as encountered in DIC or
liver disease.
 Extreme prolongation of the TT is nearly always a result of
the presence of unfractionated heparin.
 Dysfibrinogenaemia, either inherited or acquired, in liver
disease or in neonates.
 Hypoalbuminaemia.
 Paraproteinemia.
CONFIRMATORY TESTS
REPTILASE OR ANCROD TIME
 Reptilase: Bothrops atrox
 Ancrod: Agkistrodon rhodostoma
Principle
 It is a serine protease, a thrombin like enzyme.
 Cleaves fibrinopeptide A from fibrinogen (thrombin
cleaves both A &B).
Method
 Addition of reptilase to platelet poor plasma initiates
clot formation.
 Clot formation detected by optical/ electromechanical
methods.
CAUSES OF PROLONGED RT/AT
Reference interval- 18-22 seconds
 Hypofibrinogenemia
 Dysfibrinogenemia
 FDPs
 Other circulating anticoagulants
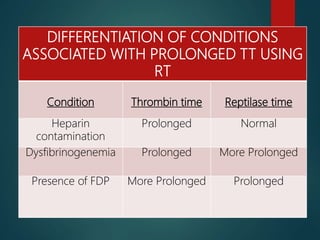
DIFFERENTIATION OF CONDITIONS
ASSOCIATED WITH PROLONGED TT USING
RT
Condition Thrombin time Reptilase time
Heparin
contamination
Prolonged Normal
Dysfibrinogenemia Prolonged More Prolonged
Presence of FDP More Prolonged Prolonged
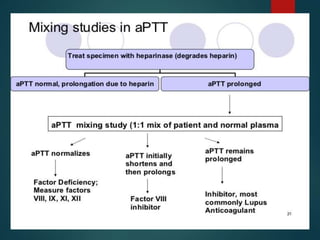
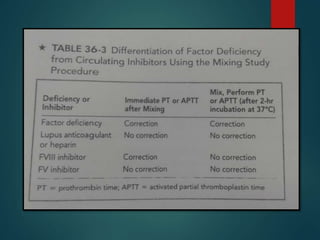
MIXING TESTS
 Plasma samples found to have abnormal screening tests,
i.e. PT/APTT, can be further investigated to determine the
cause of the abnormality.
 To differentiate a factor deficiency from the presence of a
circulating inhibitor.
 Information on the nature of the defect can usually be
obtained by mixing experiments.
The agents which can be used for
mixing tests are as follows
 Normal plasma
 Aged plasma
 Adsorbed plasma
 Factor VIII deficient plasma
 Factor IX deficient plasma
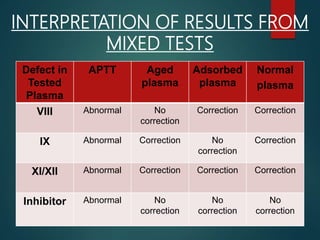
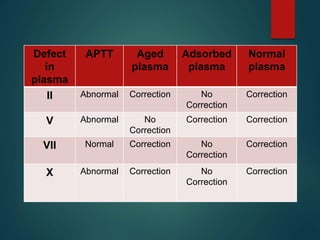
INTERPRETATION OF RESULTS FROM
MIXED TESTS
Defect in
Tested
Plasma
APTT Aged
plasma
Adsorbed
plasma
Normal
plasma
VIII Abnormal No
correction
Correction Correction
IX Abnormal Correction No
correction
Correction
XI/XII Abnormal Correction Correction Correction
Inhibitor Abnormal No
correction
No
correction
No
correction
Defect
in
plasma
APTT Aged
plasma
Adsorbed
plasma
Normal
plasma
II Abnormal Correction No
Correction
Correction
V Abnormal No
Correction
Correction Correction
VII Normal Correction No
Correction
Correction
X Abnormal Correction No
Correction
Correction
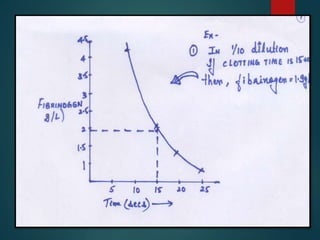
FIBRINOGEN (MODIFIED CLAUSS
ASSAY)
Principle
 Dilutions of a standard normal plasma with known
fibrinogen content are prepared in glyoxaline buffer.
 The clotting time is measured after the addition of
thrombin.
 A graph of clotting times against the fibrinogen
concentration is constructed.
Reagents
 Reference plasma with known fibrinogen concentration
 Thrombin >30u/ml (concentration may vary according
source)
 Imidazole buffer (glyoxaline) pH 7.35
 Normal range : 1.5 – 3.5 g/L
TESTS TO EVALUATE CIRCULATING
INHIBITORS
CLOTTING FACTOR INHIBITOR SCREEN
BASED ON PT/APTT
Principle
 Coagulation inhibitors affecting the PT/APTT may be
immediate acting or time dependent.
 Test plasma containing an immediate-acting inhibitor will,
when mixed with normal plasma, show little or no
correction of the clotting time.
 Plasma with time-dependent inhibitors, on the other hand,
requires a period of incubation with normal plasma before
inhibitors can be detected
LUPUS ANTICOAGULANT AND
ANTIPHOSPHOLIPID ANTIBODIES
 The criteria for presence of lupus anticoagulants are as follows:
1. Prolongation of a phospholipid-dependent coagulation test;
2. Evidence of an inhibitor demonstrated by mixing studies;
3. Phospholipid dependency of the inhibitor.
PROCEDURE : 3 STEP
 1st step- Clotting assay like APTT screening tests like
Dilute Russell's Viper Venom Time (DRVVT)
Low-phospholipid APTT
 2nd step- Mixing studies
This distinguishes a factor deficiency from presence of
inhibitor.
 3rd step - Accomplished by either reducing or adding an
excess of phospholipid to the test system
This is done using Platelet neutralizing procedure.
 The confirmatory test cut off is the value corresponding to
the mean of the individual percentage corrections as
follows:
 % correction = [(screen CT – Confirm CT)/Screen CT] x 100
 The result is confirmation of LA if the % correction is above
the cutoff value obtained.
LAB INVESTIGATIONS OF
FIBRINOLYTIC SYSTEM
DETECTION OF FIBRIN DEGRADATION
PRODUCTS USING A LATEX
AGGLUTINATION METHOD
Principle
 A suspension of latex particles is sensitized with specific
antibodies to purified FDP.
 The suspension is mixed on a glass slide with a dilution of
the serum to be tested.
 Aggregation indicates presence of FDPs.
 Hence, by testing different dilutions of the unknown
sample , a semi quantitative assay can be performed.
Conditions with the range between
10 – 40μ g /ml are:
 Acute venous thromboembolism
 Acute MI
 Severe pneumonia
Very high levels are seen in:
 DIC
 Thrombolytic therapy with streptokinase
D-DIMER TEST
Principle
 D-dimer is a marker specific for plasmin degradation of
fibrin.
 Its an FDP generated from FXIIIa crosslinked fibrin.
 Latex beads are coated with a monoclonal antibody
directed specifically against fibrin D dimer in human
plasma or serum.
Reagents
 Latex suspension
 Dilution buffer
 Positive & negative control
METHOD
 Undiluted plasma is mixed with one drop of latex
suspension on a glass slide. Gently rock the slide for the
length of time mentioned in the kit.
 If agglutination is observe then dilute the plasma until
agglutination can no longer be seen.
INTERPRETATION
 Agglutination with undiluted plasma - D-dimer >
200mg/L
 The D-dimer value can be quantified by multiplying
reciprocal of the highest dilution showing a positive
result by 200 to give a value in mg/L.
NORMAL RANGE : <200 mg/L.
EUGLOBIN LYSIS TEST
Principle
 When plasma is diluted & acidified, the precipitate
(euglobin) that forms contains plasminogen activator,
plasminogen & fibrinogen.
 Plasminogen inhibitors are left out in the solution.
 The precipitate is redissolved, fibrinogen is clotted with
thrombin & the time for clot lysis is measured.
Reagents
 Acetic acid – 0.01%
 Bovine thrombin – 10 U/ml
 Fresh PPP from patient & control
 Glyoxaline buffer
 NORMAL RANGE : 90 – 240 Min
 Abnormal values
Increased Decreased
Pregnancy Disseminated malignancies
Obese Cirrhosis.
Post- op
MI
AUTOMATION IN COAGULATION
STUDIES
 Introduced in early 20th century.
 Initial instruments were based on detection of clot
formation:
Coaguloviscometer
Nephelometer
Photoelectric technique
 The 2 principles of clot based detection currently used
are electromechanical and optical density.
Electromechanical instruments
 BBL Fibrosystem
 American Bioproducts STArt 4 Clot Detection Instrument
Optical Density Instruments
 Organon Teknika Coag-A-Mate XM
 Chromogenic / Clot detection instruments
ADVANTAGES
 Faster and more accurate
 In case of an abnormal result can cross check
 Can avoid the problem of inter-observer variation
DISADVANTAGES
 Availability of reagents
 High cost of reagents
 Strict Quality Control
 Availability of well trained technicians
QUALITY CONTROL
REFERENCES
1. McKenzie Shirlyn B. Clinical laboratory Hematology; 2nd
edition,2004.
2. Wintrobe’s hematology,10th edition,2nd volume
3. Text book of Hematology- Tejinder Singh
4. Robbins and Cotrans;Pathologic basis of diseases, 8th
edition
5. Dacie and Lewis Practical Hematology 11th edition.
Laboratory investigations in coagulation disorders