Dr R Amita
Assistant Professor
Dept of Transfusion Medicine
Anti coagulants and Blood
Preservatives
Unknown Roman poet
43 BC
 From ancient times, blood was called “living force” of the
body.
 Greeks and romans committed suicide by letting out blood
 Early times, man recognised that loss
of blood is associated with weakness
and disease
 Lost blood replaced by direct drinking
blood from young & healthy animal
or man
19th
Century
20th
Century
Albert Hustin and Luis Agote
discover that
adding sodium citrate to blood
will prevent it from Clotting
ANTI COAGULATION!!!
Francis Peyton Rous and J R Turner
added glucose to sodium citrate;
allowed blood to be STORED for
sometime before transfusing
BLOOD PRESERVATION!!!
Anticoagulants and blood
preservatives
 Anticoagulant- any substance that prevents blood clotting
 Preservative- any substance added to a specimen to
prevent changes in the constituents of a specimen
 In vivo, RBCs are carried and protected by the plasma,
– Optimum temperature, pH, glucose, disposal of metabolic
waste
– life span is 120 days
Storage lesions
 A set of biochemical &biomechanical changes which occur during
storage leading to decreased viability of the cell & its
physiological functions .
 RBCs:
– decreased ATP and 2,3DPG levels, pH- acidic
– poor functioning of Na-K+ Pump-accumulation of K+ in stored blood
– Oxidative damage with change in the structure of Band3 and Lipid
peroxidation
– Loss in membrane lipids affects deformability and osmotic fragility
– Morphological changes-Disc changes to echinocytes & to spherocytes
 Platelets:
– Loss of discoid shape, microscopic platelet aggregate formation,
fragmentation, appearance of disintegrated, ‘balloon’ forms
To ensure that blood retains its in vivo
environment
 Anticoagulants
 Preservative
 Characteristics of blood bag
 Storage temperature
 Shipping/transport conditions
Anticoagulants and blood preservatives
• To ensure the viability and stability of the products
• To inhibit growth of microorganisms
• To prevent clotting of the product
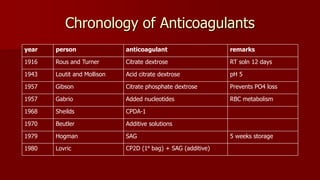
Chronology of Anticoagulants
year person anticoagulant remarks
1916 Rous and Turner Citrate dextrose RT soln 12 days
1943 Loutit and Mollison Acid citrate dextrose pH 5
1957 Gibson Citrate phosphate dextrose Prevents PO4 loss
1957 Gabrio Added nucleotides RBC metabolism
1968 Sheilds CPDA-1
1970 Beutler Additive solutions
1979 Hogman SAG 5 weeks storage
1980 Lovric CP2D (1⁰ bag) + SAG (additive)
Citrate
 Calcium-chelating agent
 Prevents coagulation by
interfering with calcium-
dependent steps in the
coagulation cascade
Citrate dextrose
 The dextrose provide
nutrient for red cells
Disadv:
 dilution 1:3
 Cannot be heat sterilized
 Risk of infection
Acid-citrate-dextrose
 Citric acid, sodium citrate, and dextrose
(pH 5)
 Shelf life of 21 days
 Acid pH does not help in maintaining
2,3-DPG levels
 Prevents caramelization of sugar
 First used in 1:4 ratio but later
concentrated to use in 1:7 ratio
 Used in apheresis procedure
Citrate-phosphate-
dextrose
 Alkaline pH and PO4
help in maintaining 2,3-
DPG
 Shelf life of 28 days
 CPD is commonly used
Added Nucleotides
 ADENOSINE : Restores ATP, but
marked hypotensive effect.
 INOSINE : generates ATP, but
hypoxanthine formed degrades
to uric acid
 GUANOSINE: Used in PAGGS-M
which provides 7 weeks of RBC
storage with recovery of 74 %
Citrate-phosphate-dextrose-
adenine (CPDA-1)
 Improved ATP synthesis
 Longer shelf life (35
days)
 Disadv: uric acid stones
Citrate Phosphate Dextrose
Adenine 2 (CPDA 2)
 PRC stored in CPDA - 1
ran out of glucose very
soon compared to CPD
 CPDA -2 contains more
glucose than CPDA-1
 Disadv: plasma and
platelets loaded with
sugar
CP2D
 100% more glucose than
CPD and 60% more than
CPDA-1
 used with an additive
solution (AS3): doesnt
contain glucose
Blood : Anticoagulant Ratio
 Volume of anticoagulant –preservative solution is 1/7 the
volume of collected blood
 14 ml of CPD/CPDA is used in preserving 100 ml blood
 63 ml for a 450 ml collection
 49 ml for 350 ml collection
 At the end of the collection , venous blood (pH 7.35)
mixed with anticoagulant-preservative solution (pH 5.0 to
5.6) with resulting pH of 7.05 in the mixture.
Additive Solutions:
 Need- With advent of component therapy , PRC usage increased (in 1970s).
 40%Adenine and glucose present in anticoagulants was removed in
preparation of RBC.
 Remaining RBC became more viscous and difficult to infuse in emergency
situation and decreased viability particularly in last 2 weeks of storage.
 Use of additive solutions allowed maximum recovery of plasma and
preparation of RBC units with final haematocrit of about 60%
 1stGeneration: SAG and BAGP-M 2ndGeneration: SAG-M and PAGGS-M
 3rd Gen: AS-1 and PAGGG-M 4thGen: AS-2 and Erythrosol-1
 5th Gen: AS-3 and Erythrosol-2 6th Gen: Erythrosol-81 7th Gen: EAS-64
 SALINE-ADENINE GLUCOSE (SAG ): maintains 83% viability after 35 days storage
 MANNITOL : acts as a membrane stabilizer and reduces hemolysis to acceptable levels
 BICARBONATE ADENINE GLUCOSE PHOSPHATE MANNITOL (BAGP-M)
 ERYTHROSOL-1: Uses half strength citrate (0.5 CPD)
 ERYTHROSOL-2: Uses full strength CPD and alkaline solution with disodium phosphate Solution. 7
week storage
 EAS -81 EXPERIMENTAL ADDITIVE SOLUTION
 PHOSPHATE ,ADENINE, GLUCOSE, GUANOSINE, SODIUM CHLORIDE, MANNITOL (PAGGS-M)
 Advantages
– Increased level of ATP and red cell viability
– Increase in shelf life of red cells to 42 days
– Extraction of more plasma/platelet rich plasma for optimal production of platelets, factor VIII yields
and FFP
 Disadvantage
– do not maintain 2,3DPG throughout the storage time Therefore , blood stored in additive solutions
is not given routinely to newborn infants
Rejuvenation Solutions
 Stored RBCs, even at the end of their allowable shelf-life can be
rejuvenated with FDA – approved rejuvenation solution.
 PIPA (Sodium Pyruvate, Inosine, Adenine, Dibasic Sodium Phosphate
and Monobasic Sodium Phosphate)
 Increases 2,3 DPG & ATP levels in stored RBCs.
 Added at any time between 3 days post collection and 3 days after
expiry
 Added directly to PRC, mixed and incubated at 37⁰C for 1 hour and
washed with saline (2 litres of unbuffered 0.9% Nacl ) and kept at 2-
6⁰C
 Rejuvenated RBCs should be transfused within 24 hours after washing
 Used in autologous donations/rare blood groups
Cryopreservation
 Process of preserving biologic structure and/ function of
living systems by freezing and storage at ultra low
temperatures
 Cryoprotectants
 Nonpenetrating : viscous solution,reduce optimum cooling
velocity.
– Eg: Lactose ,Sucrose, Albumin, Hydroxyl Ethyl Starch(HES),
Polyvinyl Pyrrolidone (PVP)
 Penetrating :Prevent damage during slow freezing and
thawing. Eg: Glycerol , DMSO
Cryoinjury:
 Fatal effects of freezing
– Intracellular ice crystal formation
– Denaturation of proteins by high solute concentrations
– Osmotic stress during the freezing and thawing process
 AUDREY SMITH (1950) Mother of cryobiology
 Glycerol prevents freezing injury human RBC
– Relatively nontoxic
– Readily permeates cell at 37⁰C
 Add slowly with vigorous shaking.
 Frozen red cells stored for 10 years
 Frozen RBC has to be deglycerolized before transfusion
 Shelf life of thawed RBC is 24 hours
Platelets
 Stored at 22-24⁰C in platelet agitator cum incubator
 Continuous gentle agitation must be maintained on a flat bed agitator: if not
rapid fall in pH due to lactate and decrease in O2 consumption
 pH: above 6.0 Plasma (50-60 ml) is needed for storage
 Shelf life extended from 3 days to 5 days (1981) at room temperature due to
improved platelet storage bags that allowed more efficient gas exchange.
 ANTICOAGULANTS:
 Platelet viability best preserved with fresh heparinized blood
 EDTA : Preserves platelet integrity Disadv: Cardiotoxic , rapidly removed from
circulation
 Citrate-phosphate Dextrose (CPD or CP2D)
 Apharesis platelets : collected into solutions containing citric acid , trisodium
citrate and dextrose. pH 5, prevents clumping of platelets
Platelet Additive Solutions(PAS):
 Synthetic mediums introduced to replace a significant portion of
plasma volume in a platelet component
 PAS being used in Europe since 1991
 Primary Ingredients
– Citrate- anticoagulant
– Acetate- substrate for oxidative metabolism
– Sodium chloride- isotonicity and osmotic strength
– Phosphate-stimulate glycolysis and maintain of pH
– Magnesium/Potassium- decreases platelet activation , improves
morphology score , decreases lactate production
 Tulli’s solution, Tyrode’s medium, Plasma- Lyte A
 Adv: Reduction of allergic reactions and febrile transfusion reactions
– Facilitates ABO incompatible platelet transfusions
– Plasma can be diverted to other uses such as fractionation
– PAS supports 7 days storage of platelets
– Reduced levels of anti-HLA, HNA antibodies and TRALI
Storage Of Platelets In Frozen State
Best results found using DMSO (Dimethyl sulfoxide ) as cryoprotective agent
Stored satisfactorily in liquid nitrogen (-196c) or at -80c deep freeze
Approved Preservative Solutions (FDA)
 ACD - approved for collection of RBC, platelets & FFP
 CPD- approved for 21 days storage
 CP2D- approved for 21 days storage
 CPDA-1- approved for 35 days storage
 Additive Solutions
– Adsol (AS-1)-Fenwal Laboratories
– Nutricel(AS-3)-Medsep Corporation
– Optisol (AS-5) Terumo Corporation
– SAG-M with CPD
 REJUVENATION SOLUTIONS
– Rejuvesol (Cytosol Laboratories)
– PIPA(Phosphate , Inosine, Pyruvate , Adenine )
 PLATELET ADDITIVE SOLUTION Intersol-FDA
Transportation & Storing of Blood &
Blood Components Prior to Transfusion
 Blood Cold Chain
– System for storing & transporting blood & blood
components
– Maintenance of correct temperature at all times from
collection from donor to administration to the patient.
– Blood bank refrigerators ,Plasma freezers, platelet
agitator cum incubators, blood transport boxes
 Any break in the blood cold chain: increased risk to
the recipients
WHOLE BLOOD AND RED CELLS
 Storage at a temperature between +2 degree C to +6
degree C in a blood bank refrigerator.
 Blood bank refrigerators: in built temperature monitoring,
alarm devices and a cooling fan
 Shelf life ranges from 35- 42 days.
 Issue of whole blood & red cells:
– blood transport box or insulator carrier
– temperature <10 degree C
– should be transfused within 30 min of taking out from BbR
Fresh Frozen Plasma and Cryoprecipitate
 Stored at -40⁰ C or colder
 Shelf life one year
 Thawed before transfusion (plasma thawing bath at 30 - 37⁰C )
 Once thawed, FFP and CP should be infused within 30 minutes.
 Transported in a blood transport box, temperature between 2 to
6⁰C.
 If not immediately required, keep at 2 to 6⁰C & transfused within
24hrs (FFP) and 4hrs (CP)
 Once thawed, do not refreeze FFP or CP.
Platelets – Platelet Rich Plasma (Prp)/Platelet
Concentrate (Pc)
 Platelets should be prepared within 8 hrs of phlebotomy
 Whole blood for separation of platelets should be kept at 20-
24⁰C
 Stored at 22 -24⁰C in platelet agitator cum incubator
 Shelf life : 5 days
 Transported in a blood transport box, temperature 22 -24⁰C
 Never refrigerate
 Transfuse as soon as possible.