PRESENTED BY –DR. BISWAJEETA SAHA
Normal hemostasis
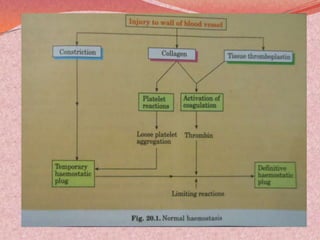
 Mechanism by which bleeding from an injured vessel is
arrested by formation of a thrombus.
 Functions-
 To maintain the blood in fluid state
 To prevent clots in intact vessels
 To arrest bleeding in injured vessels
 Components-
 Blood vessels
 Platelets
 Plasma coagulation factors
 Fibrinolytic system
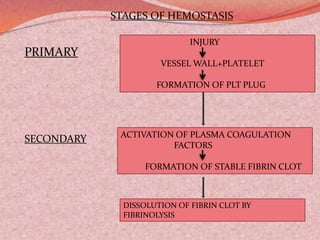
STAGES OF HEMOSTASIS
INJURY
VESSEL WALL+PLATELET
FORMATION OF PLT PLUG
ACTIVATION OF PLASMA COAGULATION
FACTORS
FORMATION OF STABLE FIBRIN CLOT
PRIMARY
SECONDARY
DISSOLUTION OF FIBRIN CLOT BY
FIBRINOLYSIS
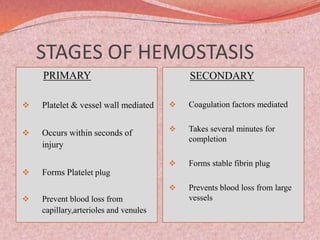
STAGES OF HEMOSTASIS
PRIMARY
 Platelet & vessel wall mediated
 Occurs within seconds of
injury
 Forms Platelet plug
 Prevent blood loss from
capillary,arterioles and venules
SECONDARY
 Coagulation factors mediated
 Takes several minutes for
completion
 Forms stable fibrin plug
 Prevents blood loss from large
vessels
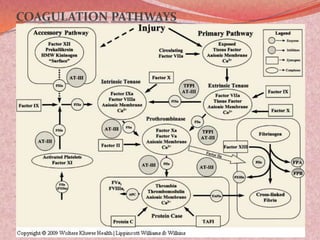
COAGULATION PATHWAYS
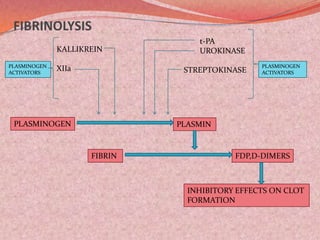
FIBRINOLYSIS
PLASMINOGEN PLASMIN
FIBRIN FDP,D-DIMERS
INHIBITORY EFFECTS ON CLOT
FORMATION
PLASMINOGEN
ACTIVATORS
KALLIKREIN
XIIa PLASMINOGEN
ACTIVATORS
t-PA
UROKINASE
STREPTOKINASE
CAUSES OF BLEEDING
1.Vessel wall disorders
2.Platelet disorders: quantitative or functional.
3.Coagulation factor: deficiency or inhibitors.
4.Combination of these.
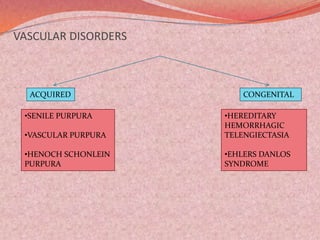
VASCULAR DISORDERS
ACQUIRED CONGENITAL
•SENILE PURPURA
•VASCULAR PURPURA
•HENOCH SCHONLEIN
PURPURA
•HEREDITARY
HEMORRHAGIC
TELENGIECTASIA
•EHLERS DANLOS
SYNDROME
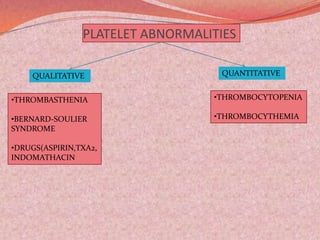
PLATELET ABNORMALITIES
QUALITATIVE QUANTITATIVE
•THROMBASTHENIA
•BERNARD-SOULIER
SYNDROME
•DRUGS(ASPIRIN,TXA2,
INDOMATHACIN
•THROMBOCYTOPENIA
•THROMBOCYTHEMIA
DISORDERS OF COAGULATION
 HEREDITARY
 HEMOPHILIA A(factor VIII deficiency)
 HEMOPHILIA B(factor IX deficiency)
 von WILLEBRAND DISEASE
 DISORDERS OF FIBRINOGEN-
HEREDITARY AFIBRINOGENAEMIA
HYPOFIBRINOGENAEMIA
DYSFIBRINOGENAEMIA
 ACQUIRED
 DISSEMINATED INTRAVASCULAR COAGULATION(DIC)
 LIVER DISEASE
 VIT K DEFICIENCY
 MASSIVE TRANSFUSION OF STORED BLOOD
 ACQUIRED INHIBITORS OF COAGULATION
 HEPARIN OR ORALANTICOAGULANT THERAPY
 RENAL DISEASE
DIAGNOSIS OF BLEEDING DISORDERS
 HISTORY
 CLINICAL EXAMINATION
 LABORATORY INVESTIGATIONS
APPROACH TO A PATIENT OF BLEEDING
DIATHESIS
, 1.Clinical evaluation: History.
Clinical features.
2.Laboratory approach:First line screening tests.
Second line specific tests.
CLINICAL EVALUATION
HISTORY: Age of first manifestation,
Family history of bleeding,
Spontaneous or after trauma,
Time of manifestation after injury,
Ease with which bleeding is controlled,
Drug history.
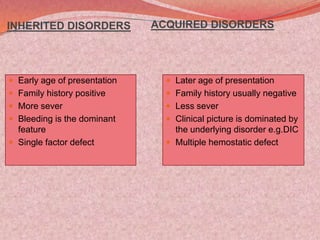
INHERITED DISORDERS
 Early age of presentation
 Family history positive
 More sever
 Bleeding is the dominant
feature
 Single factor defect
ACQUIRED DISORDERS
 Later age of presentation
 Family history usually negative
 Less sever
 Clinical picture is dominated by
the underlying disorder e.g.DIC
 Multiple hemostatic defect
Findings Disorders of
Platelet
Disorders of
Coagulation
i) Petechiae
ii) Superficial
ecchymosis
iii) Deep dissecting
hematomas
iv) Haemarthrosis
v) Bleeding from the
superficial cuts &
scratches.
vi) Positive family
history
vii) Bleeding from
mucous membrane
Characteristic
Characteristic,
usually small &
multiple
Rare
Rare
Persistent often
profuse
Rare
Prominent
Rare
Common, usually
large & solitary
Characteristic
Characteristic
Minimal
Common
May occur
LABORATORY METHODS
PREANALYTICAL VARIABLES
Collection of Sample
 Plastic or polypropylene syringes should be used.
 Venous blood is preferred over capillary blood.
 Don`t use pressure cuff or use for <1 min.
 Blood sample from a indwelling line or catheter should not be
used.
 Mix thoroughly with anticoagulant by inverting the container
several times.
 Keep the sample on crushed ice until delivered to the laboratory.
Anticoagulation
 Most commonly: Trisodium citrate (1:9).
 Unacceptable: Oxalate,Heparin, EDTA.
Centrifugation: Preparation of Platelet Poor Plasma(PPP)
 Centrifuged at 4000 rev/min at 4 C (for most of the tests) and at
room temp. for Platelet function testing, LAC and APCR tests.
 PPP should be kept at room temp. for PT,LAC & factor VII assay,and
at 4 C for other assay.
 Platelet count should be <10,000/mm, it is best achieved by double
centrifugation or filtration through a 0.2micron filter.
End-point detection
 Detecting clot formation as the end-point depends on the rate of its
formation: the shorter the clotting time the more opaque is the clot and the
easier to detect.
 A slowly forming clot appear as mere fibrin wisp, which are difficult to detect
by eye or machine.
 Always try to adopt a uniform convention in detecting the end point.
 Automated analyser are not always correct, they may be spurious.
 The Coagulometer must detect long clotting times reliably and reproducibly.
Different techniques used:
 Electromechanical
 Photo optical
 Electrochemical etc.
LABORATORY INVESTIGATIONS
TESTS FOR COAGULATION FACTORS
I. Prothrombin Time(PT)
II. Activated Partial Thromboplastin
Time(APTT)
III. Thrombin Time(TT)
IV. Fibrinogen assay
 TESTS FOR PLATELET
I. Platelet count
II. Bleeding Time(BT)
PROTHROMBIN TIME(PT)
Significance
 Reflects overall activity of the Extrinsic Pathway.
 Most sensitive to changes in Factor V,VII,X.
 Lesser to Factor I & II.
Principle
Platelet poor plasma+Tissue Thromboplastin+Calcium
In Presence of F VII Extrinsic pathway is activated & clot
formed
Normal Range
11 to 16 seconds(with rabbit thromboplastin)
10-12 seconds(with human thromboplastin)
Interpretation
Causes of prolonged PT
1. Deficiency of Factor VII,X,V,II,I
2. Vit K deficiency
3. Liver disease esp.Obstructive Jaundice
4. Oral anticoagulants
5. DIC
ACTIVATED PARTIAL THROMBOPLASTIN TIME
(APTT)
Significance
 Reflects efficiency of Intrinsic Pathway.
 Sensitive to changes in Factor VIII,IX,XI,XII.
 Also sensitive to heparin & circulating anticoagulants.
Principle
The test measures the clotting time of plasma after the activation of contact
Factors(Kaolin/Silica/Ellagic acid) and the addition of phospholipid and
CaCl2, but without added tissue thromboplastin.
So it indicates the overall efficiency of the Intrinsic pathway
Normal range
26 to 40 seconds.
Interpretation
Causes of prolonged APTT
1. Deficiency of Factor VIII(Hemophilia A).
2. Deficiency of Factor IX(Hemophilia B).
3. DIC.
4. Heparin therapy.
5. Circulating anticoagulants.
6. Liver disease.
7. Massive transfusion of plasma depleted stored
blood.
THROMBIN TIME(TT)
Significance
Asses the final step of coagulation i.e. conversion of
fibrinogen to fibrin in presence of thrombin.
Bypasses Extrinsic & Intrinsic pathway.
Principle
Thrombin is added to plasma and the clotting time is
measured.TT is affected by the concentration and reaction
of fibrinogen and by the presence of inhibitory substances
including fibrinogen/fibrin degradation products(FDPs) and heparin.
Normal range
A patient’s TT should be within 2 s of the control
(i.e. 15–19 sec). Times of 20 s and longer are definitely abnormal.
Interpretation
Causes of prolonged TT
1. Disorders of fibrinogen-
Afibrinogenaemia.
Hypofibrinogenaemia.
Dysfibrinogenaemia.
2. Presence of FDP- DIC or Liver disease.
3. Unfractioned heparin therapy.
4. Hypoalbuminaemia.
5. Paraproteinaemia.
.
Fibrinogen Assay
Usually done by CLAUSS TECHNIQUE.
Principle
Diluted plasma is clotted with a strong thrombin solution.
The plasma must be diluted to give a low level of any inhibitors(e.g.
FDPs and heparin).
A strong thrombin solution must be used so that the clotting time
over a wide range is independent of the thrombin concentration.
Normal range
1.8 to 3.6 g/l
Interpretation
Sensitive to inherited Dysfibrinogenaemia.
Insensitive to Heparin unless the level is very high(>0.8µ/µl).
High level of FDP(>190µg/ml)may also interfare with the result.
Platelet count & Bleeding Time
Platelet count must be done in a suspected bleeding disorder.
PBS must be examined for size & staining properties of plt.
BLEEDING TIME(BT)
Significance
Assess Primary Hemostatic defect(vessel wall or platelet).
Dependent on adequate functioning of plt. & Bl.Vs.
Methods
I. Ivy’s
II. Duke’s-not recommended.
III. Template
Range
Ivy’s method: 2 to 7 mins.
Template method: 2.5 to 9.5 mins.
Interpretation
Causes of prolonged BT
I. THROMBOCYTOPENIA.
II. VWD.
III. PLATLET FUNCTION DISORDER.
IV. DISORDERS OF BLOOD VESSEL.
DIAGNOSIS OF VESSEL WALL DISORDER
 LABORATORY TESTS: TPC,PT, APTT,TT are usually normal.
The only test of any use is BT.
BT may be normal or increased.
HESS` CAPILLARY FRAGILITY TEST:
Cuff is wrapped in upper arm and pressure is maintained midway
b/w systolic and diastolic BP for 15 minutes.
4 cm below the elbow joint, a circle of 2.5 cm diameter is drawn on
the anterior aspect of forearm.
Upto 10 new hemorrhagic spots are normal.
But >20 new spots are always pathological.
 This is positive in increased capillary fragility, ITP.
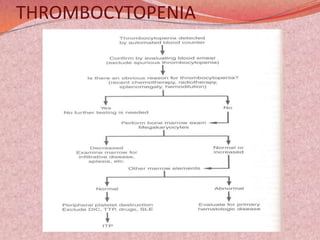
THROMBOCYTOPENIA
SECOND LINE INVESTIGATIONS
Relevant second line investigations are carried out with each
of the patterns of abnormalities in first line tests.
1
PT-N
APTT-N
TT-N
FIBRINOGEN-N
PLATELET-N
Interpretation
1. Normal hemostasis.
2. Disorders of platelet function(cong or acquired).
3. Vascular disorders of hemostasis.
4. Factor XIII deficiency.
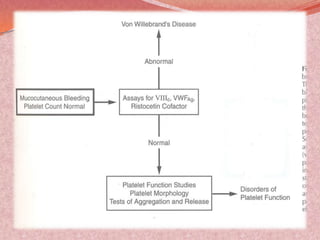
5. Mild von Willebrand disease.
6. Disorder of fibrinolysis.
7. Administration of LMWH.
SECOND LINE INVESTIGATIONS
 Clot solubility test.
 Specific factor assay for suspected factor
deficiency(factor XIII).
 PFA 100 system.
CLOT SOLUBILITY TEST
PRINCIPLE—
Fibrin clot in presence of factor XIII & thrombin is stable as
A result of cross- linking.
But in absence of factor XIII clot dissolves rapidly.
Interpretation—
CLOT NOT DISSOLVED IN 24HRS-
F XIII PRESENT
CLOT DISSOLVES –
F XIII ABSENT
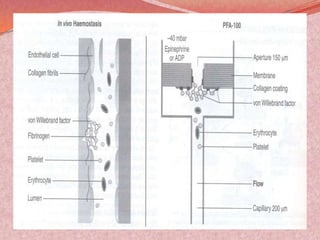
PLATELET FUNCTION ANALYZER(PFA)100
 In vitro system for measuring plt- vwf fuction.
 Assesses both plt adhesion & aggregation
 More sensitive than BT to asses Primary hemostasis.
 The membrane is coated with collagen & epinephrine or
collagen & ADP.
 It reproduces platelet vwf function under high shear rate.
 Time req. for closure of full aperture is closure time
 Normal closure time: 1 to 3 mins.
 Interpretation:-
Thrombocytopenia.
von Willebrand Disease.
Plt. Function abnormality.
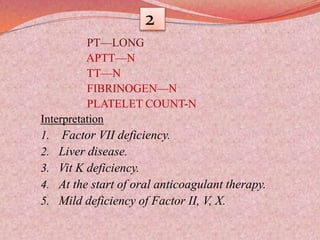
2
PT—LONG
APTT—N
TT—N
FIBRINOGEN—N
PLATELET COUNT-N
Interpretation
1. Factor VII deficiency.
2. Liver disease.
3. Vit K deficiency.
4. At the start of oral anticoagulant therapy.
5. Mild deficiency of Factor II, V, X.
SECOND LINE INVESTIGATIONS
1. Mixing test.
2. Factor VII assay.
3. Liver function test.
3
PT—N
APTT—LONG
TT—N
FIBRINOGEN—N
PLT COUNT--N
Interpretation
1. Congenital deficiency of F VIII, FIX,prekallikrein or HMWK.
2. von Willebrand disease.
3. Heparin-either pt. Is on t/t or contaminated sample.
4. Circulating anticoagulants-
Specific (Anti factor VIII).
Non-specific(Antiphospholipid Ab).
Second line investigations
1. Mixing test.
2. Factor VIII & factor ix assay.
Mixing study
CORRECTION TEST USING PT or APTT
PRINCIPLE
 Unexplained prolongation of PT or APTT can be investigated
with simple correction test by mixing the pt`s plasma with
normal plasma.
 Correction (should be within few seconds) indicates a possible
factor deficiency, whereas failure to correct suggests the presence
of an inhibitor.
METHOD
 Perform a PT and/or APTT on control, patient`s,and a 50:50
mixture of the control and pt`s plasma.
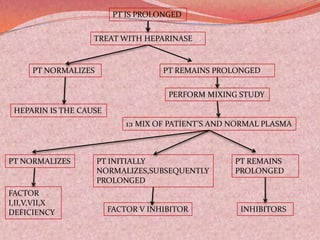
PT IS PROLONGED
TREAT WITH HEPARINASE
PT NORMALIZES
HEPARIN IS THE CAUSE
PT REMAINS PROLONGED
PERFORM MIXING STUDY
1:1 MIX OF PATIENT’S AND NORMAL PLASMA
PT NORMALIZES PT INITIALLY
NORMALIZES,SUBSEQUENTLY
PROLONGED
PT REMAINS
PROLONGED
FACTOR
I,II,V,VII,X
DEFICIENCY FACTOR V INHIBITOR INHIBITORS
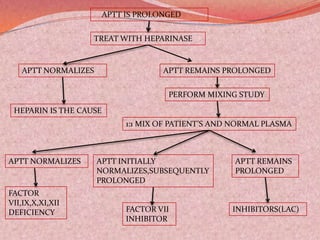
APTT IS PROLONGED
TREAT WITH HEPARINASE
APTT NORMALIZES
HEPARIN IS THE CAUSE
APTT REMAINS PROLONGED
PERFORM MIXING STUDY
1:1 MIX OF PATIENT’S AND NORMAL PLASMA
APTT NORMALIZES APTT INITIALLY
NORMALIZES,SUBSEQUENTLY
PROLONGED
APTT REMAINS
PROLONGED
FACTOR
VII,IX,X,XI,XII
DEFICIENCY FACTOR VII
INHIBITOR
INHIBITORS(LAC)
CORRECTION TEST USING TT
PRINCIPLE
 The tests use certain physiochemical properties of reagents to bind to inhibitors
or abnormal molecules and normalise the prolonged TT.
INTERPRETATION
TT of test plasma corrected with Interpretation
Saline Normal plasma ProtaminSO4 Toluidine blue
No Yes No No Deficiency
No Variable No Yes Dysfibrinogenemia
of liver disease
No Variable Yes No High level of FDP
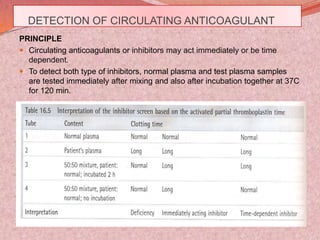
DETECTION OF CIRCULATING ANTICOAGULANT
PRINCIPLE
 Circulating anticoagulants or inhibitors may act immediately or be time
dependent.
 To detect both type of inhibitors, normal plasma and test plasma samples
are tested immediately after mixing and also after incubation together at 37C
for 120 min.
4
PT—LONG
APTT—LONG
TT-N
FIBRINOGEN—N
PLT COUNT—N
Interpretation
1. Vit k def.
2. On oral anticoagulants.
3. Liver dis.
4. Rare congenital or acq. Deficiency of factor v,x,ii .
5. Combined factor V+VIII deficiency.
Second line investigations
1. Mixing test.
2. Specific factor assay.
3. Liver function test.
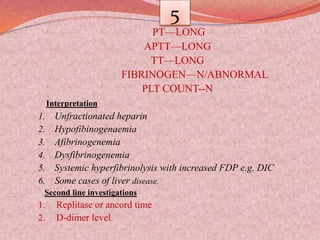
5
PT—LONG
APTT—LONG
TT—LONG
FIBRINOGEN—N/ABNORMAL
PLT COUNT--N
Interpretation
1. Unfractionated heparin
2. Hypofibinogenaemia
3. Afibrinogenemia
4. Dysfibrinogenemia
5. Systemic hyperfibrinolysis with increased FDP e.g. DIC
6. Some cases of liver disease.
Second line investigations
1. Replitase or ancord time
2. D-dimer level.
REPTILASE OR ANCORD TIME
 REPTILASE & ANCORD are purified enzymes from
snake.
 May be used to replace Thrombin in TT test.
 Snake venom is not inhibited by heparin-
 Normal time for clotting in presence of Heparin.
 Clotting time will be prolonged in presence of raised
FDPs/decreased Fibrinogen.
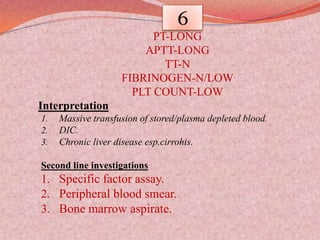
6
PT-LONG
APTT-LONG
TT-N
FIBRINOGEN-N/LOW
PLT COUNT-LOW
Interpretation
1. Massive transfusion of stored/plasma depleted blood.
2. DIC.
3. Chronic liver disease esp.cirrohis.
Second line investigations
1. Specific factor assay.
2. Peripheral blood smear.
3. Bone marrow aspirate.
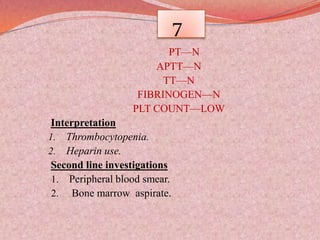
7
PT—N
APTT—N
TT—N
FIBRINOGEN—N
PLT COUNT—LOW
Interpretation
1. Thrombocytopenia.
2. Heparin use.
Second line investigations
1. Peripheral blood smear.
2. Bone marrow aspirate.
8
PT—LONG
APTT—LONG
TT—LONG
FIBRINOGEN—LOW
PLT COUNT—LOW
Interpretation
1. DIC
2. Acute liver necrosis with DIC.
Second line investigations
FDP or D-Dimer assay.
FDP ASSAY
Plasminogen
Plasmin
Fibrinogen/ FDP X,Y,D,E
Fibrin
Principle
A Suspension of latex particles sensitized with specific Ab to
FDP fragments D & E.
Suspension mixed on a glass slide with a dilution of test serum.
Agglutination indicates presence of FDPs.
Interpretation of FDP Assessment
Agglutination with 1in 5 dilution:-FDP >10µg/ml
Agglutination with 1 in 20 dilution:-FDP>40µg/ml
Normal range- <10 µg/ml
10-40 µg/ml- Acute myocardial Infarction.
Acute venous thromboembolism.
Acute pneumonia.
>40 µg/ml- DIC.
Thrombolytic therapy with Streptokinase .
D-DIMER ASSAY
Identical to FDP except latex particles are coated with a
Monoclonal Antibody specifically directed against
Fibrin D-dimer in human.
Normal range <200mg/l.
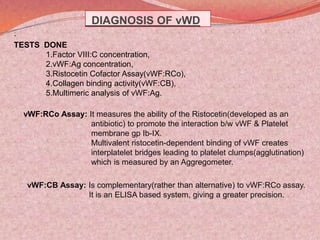
DIAGNOSIS OF vWD
.
TESTS DONE
1.Factor VIII:C concentration,
2.vWF:Ag concentration,
3.Ristocetin Cofactor Assay(vWF:RCo),
4.Collagen binding activity(vWF:CB),
5.Multimeric analysis of vWF:Ag.
vWF:RCo Assay: It measures the ability of the Ristocetin(developed as an
antibiotic) to promote the interaction b/w vWF & Platelet
membrane gp Ib-IX.
Multivalent ristocetin-dependent binding of vWF creates
interplatelet bridges leading to platelet clumps(agglutination)
which is measured by an Aggregometer.
vWF:CB Assay: Is complementary(rather than alternative) to vWF:RCo assay.
It is an ELISA based system, giving a greater precision.
DIAGNOSIS OF DIC
• Finding a prolonged PT and APTT with a reduced TPC & Fibrinogen level is usually
DIC, until proven otherwise.
• The diagnosis of DIC is made by the presence of a confirmatory test that shows the
simultaneous presence of thrombin and plasmin formation.
D-dimer Assay:
• It is the best test for diagnosing DIC. Value >2000ng/ml is consistent with DIC.
• It is the confirmatory test that shows that both thrombin and plasmin have been
formed.
• It measures plasmin-cleaved, insoluble,cross-linked fibrin that originally arose from
thrombin cleavage of fibrinogen.
• D-dimer assay is characteristic but not pathognomonic for DIC.
FDP Assay:
• FDPs only indicate plasmin-cleaved fibrinogen, soluble fibrin or insoluble fibrin.
• It does not indicate plasmin-cleaved,insoluble,cross-linked fibrin.
Fibrin monomer assay:
• Fibrin monomer is the large molecular mass of fibrinogen that remains after release of
fibrinopeptide A & B.
• Elevated in early stage, but can be absent in sever DIC. Hence unreliable.