FETAL GROWTH RESTRICTION
Short for Gestational Age
• A fetus that has been unable to achieve a specific biometric or
estimated weight threshold by a specific gestational age is
called a short for gestational age (SGA) fetus.
• Using the WHO cut-off, the term SGA is used when the
newborn baby’s weight is below the 10th percentile for its
gestational age (ACOG).
– Constitutionally small and healthy fetuses (50-70% of
SGA)
– Fetuses with growth restriction
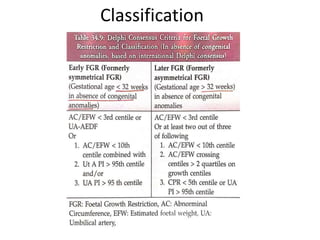
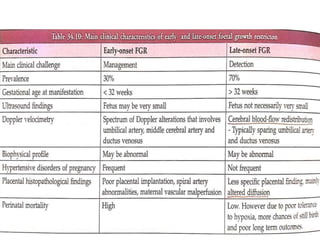
• Early Onset FGR <32 weeks
• Late Onset FGR >32 weeks
• Incidence: About 3-10% infants are growth restricted;
12-40 % in twin gestation.
Definition
FGR is a pathological condition defined as failure
of a fetus to reach its genetic growth potential
in utero putting it at risk of perinatal mortality
and morbidity.
Smallness is defined as estimated fetal weight
(EFW) or abdominal circumference (AC) less
than the 10th centile and severe SGA as EFW
or AC less than 3rd centile.
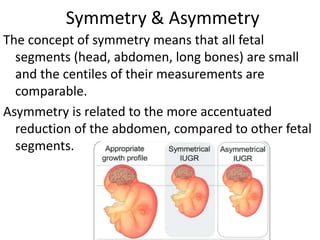
Symmetry & Asymmetry
The concept of symmetry means that all fetal
segments (head, abdomen, long bones) are small
and the centiles of their measurements are
comparable.
Asymmetry is related to the more accentuated
reduction of the abdomen, compared to other fetal
segments.
Classification
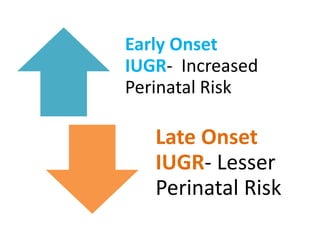
Early Onset
IUGR- Increased
Perinatal Risk
Late Onset
IUGR- Lesser
Perinatal Risk
Etiology
• Fetal Factors
– Chromosomal abnormality
– Genomic Imprinting
– Congenital Malformations
– Congenital Infections
– Multiple Gestation
• Maternal Factors
– Pre eclampsia, chronic/essential HTN
– Renal Disease
– Diabetes with vasculopathy
– APLA,SLE
– Thrombophilia
– Severe or Cyanotic Heart Disease
– Asthma
– Hemoglobinopathy
– Smoking, alcoholism, substance abuse
– Therapeutic agents like anticancer drugs
– Malnutrition
• Placental factors
– Confined Placental Mosaicism
– Placenta previa
– Abruption
– Infarction
– Placenta accreta
– Hemangioma
– Circumvallate placenta
– Abdominal Pregnancy
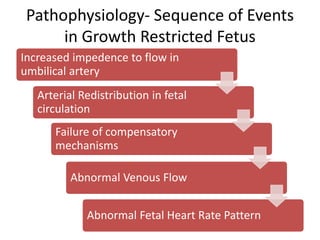
Pathophysiology- Sequence of Events
in Growth Restricted Fetus
Increased impedence to flow in
umbilical artery
Arterial Redistribution in fetal
circulation
Failure of compensatory
mechanisms
Abnormal Venous Flow
Abnormal Fetal Heart Rate Pattern
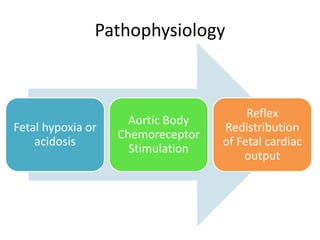
Pathophysiology
In the early stages of hypoxia, the fetus uses
adaptive techniques such as
– growth reduction,
– Decreased fetal movements,
– And vascular redistribution
to reduce its oxygen requirement, in an attempt
to prevent hypoxic injury.
There is stimulation of erythropoiesis with an
increase in hematocrit.
Pathophysiology
Fetal hypoxia or
acidosis
Aortic Body
Chemoreceptor
Stimulation
Reflex
Redistribution
of Fetal cardiac
output
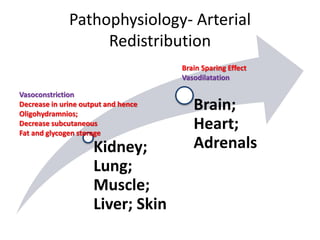
Pathophysiology- Arterial
Redistribution
Kidney;
Lung;
Muscle;
Liver; Skin
Brain;
Heart;
Adrenals
Brain Sparing Effect
Vasodilatation
Vasoconstriction
Decrease in urine output and hence
Oligohydramnios;
Decrease subcutaneous
Fat and glycogen storage
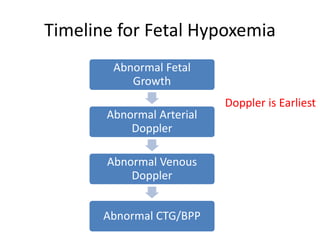
Timeline for Fetal Hypoxemia
Abnormal Fetal
Growth
Abnormal Arterial
Doppler
Abnormal Venous
Doppler
Abnormal CTG/BPP
Doppler is Earliest
Risk Factors
MAJOR
• Previous SGA
• Previous Stillbirth
• Chronic HTN/ Pre eclampsia
• Renal Impairment
• APLA
• Threatened abortion with heavy
bleeding
• Unexplained APH
• Low Maternal weight gain
• Paternal SGA
• Maternal age >= 40 years
• Smoker > 11 cigarettes per day
• Fetal Echogenic Bowel on USG
• PAPP-A < 0.4 MOM
• Daily vigorous Exercise
MINOR
• Age >= 35 years
• BMI <20 or >25
• Nulliparity
• IVF Singleton Pregnancy
• Low fruit intake Prepregnancy
• Caffeine >300mg per day
• Interpregnancy Interval <6
months or >60 months
• Placental abruption
Complications
Early Neonatal Complications
Metabolic
Hypothermia
Hypoglycemia
Hypocalcemia
Polycythemia
Hyperviscosity Syndrome
Complications Due to Asphyxia
HIE
Persistent Fetal Circulation
MAS
NEC
Pulmonary Hemorrhage
Electrolyte Imbalance
Metabolic Acidosis
Late Neonatal Complications
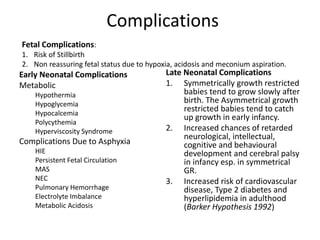
1. Symmetrically growth restricted
babies tend to grow slowly after
birth. The Asymmetrical growth
restricted babies tend to catch
up growth in early infancy.
2. Increased chances of retarded
neurological, intellectual,
cognitive and behavioural
development and cerebral palsy
in infancy esp. in symmetrical
GR.
3. Increased risk of cardiovascular
disease, Type 2 diabetes and
hyperlipidemia in adulthood
(Barker Hypothesis 1992)
Fetal Complications:
1. Risk of Stillbirth
2. Non reassuring fetal status due to hypoxia, acidosis and meconium aspiration.
Prediction and Screening
1. History
• Maternal Characteristics like age, parity, Ethnicity,
Nulliparity, social deprivation, unmaried status, low pre
pregnancy weight, intense daily exercise,
• Maternal Medical History like Diabetes with vascular
disease, Chronic HTN, renal impairment esp associated with
HTN, APLA
• Paternal medical history like Paternal SGA
• Past Obstetric History like previous SGA, previous stillbirth,
previous pre eclampsia, interpregnancy interval,
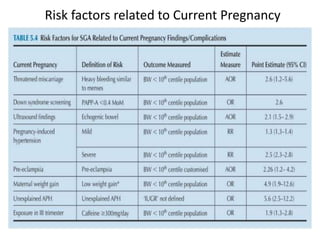
– Previous SGA is associated with 6 fold increase risk for SGA
• Trimester History: heavy vaginal bleeding during first
trimester similar to menses
• Substance abuse, smoking, caffeine intake
Risk factors related to Current Pregnancy
Prediction and Screening
2. Examination
• Weight
• SFH
• Fundal height by palpation
• Girth of the abdomen
3. Maternal Serum Screening
AFP, uE3, hPL, HCG
PAPP-A <0.4 MOM in the first trimester is also used
as a predictor for FGR later on.
Prediction and Screening
4. Ultrasound Markers- Fetal echogenic bowel
and abnormal uterine artery doppler
velocimetry in second trimester.
The combination of unexplained elevated AFP
with abnormal uterine artery doppler
velocimetry or echogenic bowel is a better
predictor of adverse perinatal outcome.
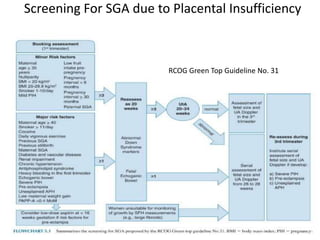
Screening For SGA due to Placental Insufficiency
RCOG Green Top Guideline No. 31
Prediction and Screening
Uterine artery (UtA) doppler directly reflects
the involvement of trophoblastic invasion and
can be used as a screening tool for all high risk
pregnancy for the prediction of pregnancy
outcome.
UtA doppler assessment at 20-24 weeks
gestation may be offered in women who have
one major or three or more minor risk factors
for SGA.
Diagnosis- Clinical Examination
• If the height of the uterus is less than 4 weeks
or more than the estimated gestation, FGR
should be suspected.
• SFH The uterine height in cm coincide with the
weeks of gestation between 18 and 30 weeks.
• Static or falling maternal weight after 20
weeks may indicate FGR
• Static or falling abdominal girth measured at
umbilicus may indicate FGR
Diagnosis- Ultrasound Biometry
An AC within normal range for gestational age rules
out FGR while an AC of <5th percentile is highly
suggestive of FGR (ACOG 2000)
The RCOG green top guideline suggests fetal AC or
EFW <10th percentile of GA as recommended cut
off for SGA.
AC is the most sensitive parameter to diagnose
FGR.
Diagnosis
Biophysical tests such as amniotic fluid volume,
cardiotocography and Biophysical profile
scoring have been shown to be poor
diagnostic tests for FGR.
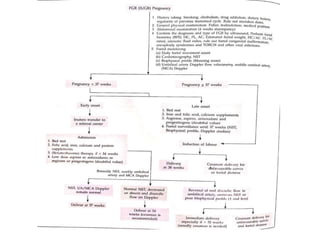
Fetal Surveillance
1. Fetal Biometry
Serial assessment of fetal biometry can identify
worsening of growth velocity in fetuses
diagnosed as SGA.
Fetal USG biometry is performed every 2-3 weeks.
Patient can be followed up on OPD basis.
2. Doppler Assessment
Two weekly (weekly in severe SGA) doppler of UA is
recommended as the primary modalily of FWB.
This is increased to twice a week in a
compromised UA doppler with present diastolic
flow and daily with absent diastolic flow.
Fetal Surveillance
3. Amniotic Fluid Volume
Single deepest vertical pocket <2cm should be used
for diagnosing oligohydramnios.
Decreased AF volume may signify placental
insufficiency or fetal anomalies.
Antepartum AFI <= 5 is associated with increased
risk of caesarean section for fetal Distress and an
APGAR <7 at 5 minutes.
A low or marginal AFI should be followed by more
frequent surveillance. AFI <=5 should prompt
consideration for delivery.
Fetal Surveillance
4. Biophysical Profile Score includes four acute fetal
variables, each score 2
a) Breathing movements
b) Gross body movements
c) Cardiotocoraphy
d) Amniotic fluid volume
Score <=4 are considered abnormal
Recent studies on preterm SGA suggest BPP as poor
predictor of fetal acidemia, hence should not be
used for fetal surveillance in preterm SGA.
Fetal Surveillance
5. Cardiotocography
CTG should not be used as the only surveillance
tool
Computerised CTG should be preferred to
conventional CTG
Interpretation should be based on short term
fetal heart rate variability.
Interventions in Preterm SGA
Women with POG 24 to 35+6 weeks gestation,
where delivery is being considered, should
receive a single course of antenatal
corticosteroids to accelerate fetal lung maturity
and reduce neonatal death and morbidity
Maternal administration of Magnesium Sulphate
have been shown to have neuroprotective effect
and to reduce the incidence of cerebral palsy
among preterm infants <30 weeks.
Prevention of SGA
• Aspirin started at <16 weeks POG in women at
risk of developing pre eclampsia
• Smoking cessation
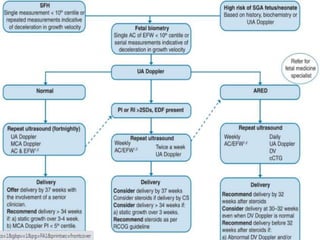
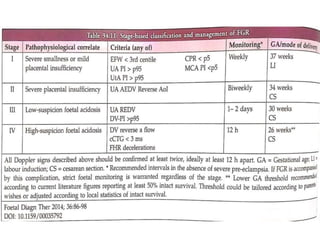
Timing of Delivery
The timing of delivery remains a critical issue.
The risk of prolonging pregnancy(i.e stillbirth)
has to be weighed against the risk of
prematurity.
Gestational age is critical in decision making.
The other critical issue in decision making is the
interpretation of surveillance tests that are
used to predict perinatal outcome.
The Role of Doppler
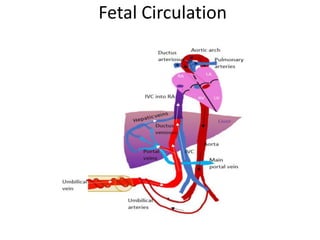
Fetal Circulation
Doppler Indices
Peak Systolic Velocity
Peak Diastolic Velocity
Systolic to Diastolic Ratio:-
Systolic peak velocity/Diastolic peak velocity
Pulsatility Index:-
Systolic-End diastolic peak velociy Mean Velocity
Resistence Index
Systolic-End Diastolic peak velocity Systolic peak
velocity
Cerebroplacental Ratio
MCA PI/UA PI
Uterine Artery Doppler
• Uterine artery doppler reflects trophoblastic invasion and placental
development.
• Uterine artery doppler between 20 and 24 weeks has a moderate
predictive value in the predicition of FGR.
• Women with abnormal UtA doppler >p95 or early diastolic notching
should be followed up with serial fetal growth and well being scan
from 26 weeks to 28 weeks.
• UtA doppler resistence profile that is high, with PI >95th centile or
persistently notched, or both, indentifies women who are at risk for
pre eclampsia and FGR. It has a sensitivity of 85% when done
between 22 and 23 weeks.
• Low dose aspirin initiated this late in pregnancy does not improve
placental function.
• A marked reduction in early onset pre eclampsia and FGR is seen in
high risk women identified on the basis of high risk factors like
maternal history, mean arterial ptressure, UtA doppler at 11-13
weeks, PAPP-A and treated with 100-150 mg aspirin in the evening
started at less than 16 weeks till 36 weeks.
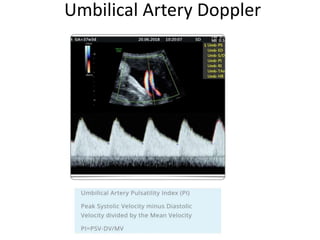
Umbilical Artery Doppler
Umbilical artery doppler reflects placental function and indicates the
degree of placental insufficiency
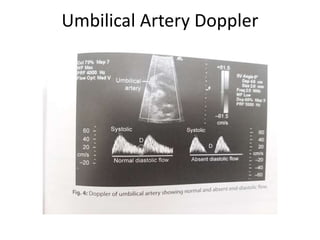
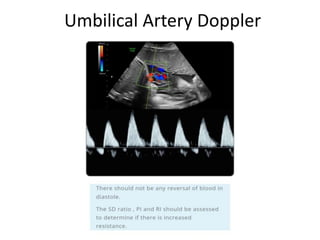
In the normal fetus, Doppler of UA shows presence of diastolic flow by
15 weeks. As the placental resistence decreases with advancing
gestation due to trophoblastic invasion, diastolic flow increases.
This is manifested as decrease in SD ratio or PI. Thus the UA shows a
waveform with continuous flow during systole and diastole.
In a growth restricted fetus with decreased placental perfusion and
increasing resistence to flow, the SD ratio, PI and RI show and
increasing trend. Gradually the diastolic flow ends (AEDV) and then
reverses (REDV).
High UA PI (above p95) indicates placental insufficiency
Positive EDF >=50%
Absent EDF >=70%
Reverse EDF >=90%
AEDV and REDV are associated with increased perinatal morbidity and
mortality and if identified, urgent intervention with steroid
administration for fetal lung maturity, increased surveillance and
delivery is required even in preterm fetus.
Umbilical Artery Doppler
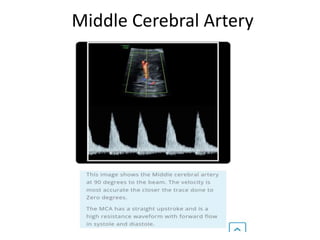
Middle Cerebral Artery
MCA Doppler shows how the fetus is coping.
In the normal fetus, MCA is characterized by higher impedance to flow
as compared to UA and hence it exhibits low amplitude of diastolic
flow in the normal circumstances.
The flow increases in a hypoxic fetus due to cerebral vasaodilatation
which occurs as an adaptive mechanism known as the brain sparing
effect, resulting in a decreased PI value.
Therefore, reduced MCA PI and CPR are early predictors of fetal
hypoxemia in SGA fetus.
The MCA PI <5th centile or CP ratio <5th centile is a moderate predictor
of acidosis at birth in a term SGA and should be used to time
delivery even in a normal UA doppler
In a preterm fetus less than 32 weeks MCA doppler has limited value
and should not be used to predict outcome.
Middle Cerebral Artery
• The brain sparing effect may develop in 2 scenarios
– In Early onset SGA, where UA are already abnormal for the
worsening of placental circulation.
– In late onset SGA, where UA is typically normal because
fetal metabolic needs are greater than placental capacity
even in the absence of placental insufficiency.
• Predictive ability for adverse perinatal outcome is
greater in the latter scenario.
• According to these findings, the development of brain
sparing effect should be considered for the time to
deliver in late onset SGA (32-34 weeks POG), where UA
is normal.
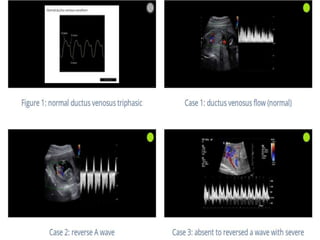
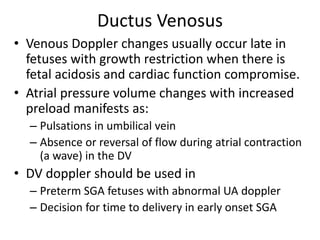
Ductus Venosus
• Venous Doppler changes usually occur late in
fetuses with growth restriction when there is
fetal acidosis and cardiac function compromise.
• Atrial pressure volume changes with increased
preload manifests as:
– Pulsations in umbilical vein
– Absence or reversal of flow during atrial contraction
(a wave) in the DV
• DV doppler should be used in
– Preterm SGA fetuses with abnormal UA doppler
– Decision for time to delivery in early onset SGA