

















DR BHARTI PANT
GAHTORI
Defining disorders of growth requires relating a
given achieved growth to an expected growth.
Within genetically set limits, the actual fetal growth
judged by Fetal weight is determined by the
- genetic growth potential which varies from race to
race and individual to individual ,
- the health of the fetus with good fetal circulation,
- the capacity of the mother to supply adequate
quality
and quantities of substrates ( O2 , glucose,
aminoacids
etc) required for growth,
 With a prevalence of the 5–8% in the general
population, IUGR can complicate 10% to 15% of
all pregnancies .
- However, only 20–30% of these fetuses are
small because of a pathological restriction of their
growth (PFGR) and a majority are normal SGA
-IUGR represents the second cause of perinatal
mortality, after prematurity
-It is related to an increased risk of perinatal
complication as hypoxemia, low Apgar scores,
and cord blood acidemia, with possible negative
effects for neonatal outcome.
-It is associated with increased risk of
neurological, cardiovascular and metabolic
In practice, due to error in estimating gestational age, inaccuracy
in weight estimation, and variation in true genetic potential, there
will be no cut off that correctly separates normal and abnormal
IMPORTANT TERMS IN FETAL GROWTH
DISORDER
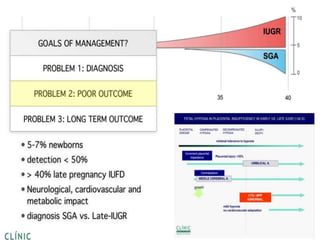
SGA simply refers to a weight for gestation
below a given threshold, but a significant
proportion of smallness is due to
constitutional or physiological causes, The
most commonly used definition of SGA is a
birth weight below the 10th percentile for
gestational age.
IUGR SIGNIFIES THE PATHOLOGICAL CAUSE OF
SAME CUTOFF
Endocrine regulation of fetal growth –
IGF -1 IGF -2
Placental regulation of fetal growth –
Implantation and early placentation play
crucial role
Genomic imprinting and fetal growth
-Placental insufficiency 75–80%
-Maternal conditions not associated with
placental insufficiency 5%
-Fetal chromosome abnormalities 5%
-Multifactorial fetal abnormalities 2–3%
-Fetal infections 1%
1. Associated with placental vascular insufficiency:
-Preeclampsia
-Chronic hypertension
- Chronic renal disease
- Connective tissue disorder
-Diabetes with vascular lesions
-Sickle cell anemia
-Cardiac disease class III or IV
-Multiple gestation
-Autoimmune diseases, including: APS
-Genetic disorders, including: phenylketonuria.
2. Not associated with placental insufficiency
-Severe malnutrition
-Smoking
-Alcohol ingestion and recreational drugs
-Hemoglobinopathies
Alterations in the uteroplacental and fetal–placental
circulations
• Abnormal trophoblast invasion:
• pre-eclampsia
• placenta accreta.
• Infarction ,villitis , hemorragic endovasculitis,
• Abruption
• Placental location: placenta praevia.
• Tumours: chorioangiomas ,placental
haemangiomas
• Abnormal umbilical cord or cord insertion: two-
Lack of substrate and inability to reach genetic
potential
• Genetic abnormalities, including:
• trisomy 13, 18, or 21
• turner’s syndrome
• triploidy.
• Congenital abnormalities, including:
• cardiac, e.g. TOF, transposition of the great vessels
• gastroschisis.
• Congenital infection, including:
• CMV
• rubella
• toxoplasmosis.
• Multiple pregnancy
-Type I or symmetric FGR corresponds to fetuses
that are symmetrically small and have normal H/A
and F/A ratios.
Type II or asymmetric FGR corresponds to fetuses
that have an AC that is smaller than the HC and the
FL resulting in abnormally high H/A and F/A ratios.
Type III or intermediate FGR corresponds to fetuses
that are initially symmetric but become asymmetric
later in the pregnancy.
“Intrinsic”- FGR occurs when the fetuses are
small due to fetal conditions such as viral
infections or chromosomal abnormalities.
“Extrinsic” -FGR occurs when the growth failure
is due to an element outside of the fetus such as a
placental condition or a maternal disease.
“Combined”- FGR occurs when there are extrinsic
and intrinsic factors causing the growth failure
and
“Idiopathic” -FGR when the cause of the fetal
BASED ON DOPPLER FINDINGS NOT BIRTHWEIGHT
SOLELY
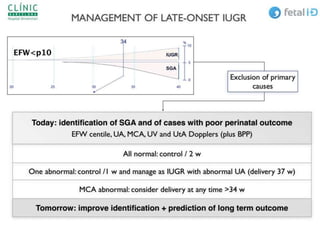
1) Small for gestational age (SGA) refers to those
small fetuses with no discernible pathology and
with normal umbilical artery and middle cerebral
artery Doppler results;
2) Growth-restriction refers to small fetuses with
recognizable pathology and abnormal Doppler
studies; and
3) Idiopathic growth restriction applies to small
fetuses with no discernable pathology and
abnormal Doppler studies.28
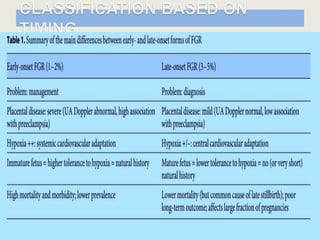
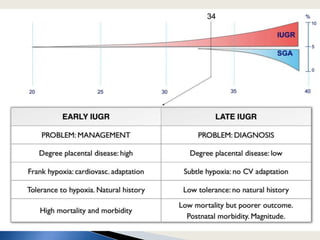
 Early-onset FGR represents 20–30% of all FGR
and is associated with gestational
hypertension and/or pre-eclampsia in up to
70%.
Late-onset FGR, which represents
approximately 70–80% of cases of FGR, shows
a weaker association with hypertensive
disorders of the pregnancy, roughly 10%
1) Maternal socio-economic condition and nutritional
status
2) Maternal smoking , alcohol intake , teratogen intake or
substance abuse in past and present
3) Previous history of growth restriction or still birth
- 50% increased risk of severe growth restriction
- Stillbirths before 32 weeks’ gestation have a
particularly strong association with IUGR.
4) Medical disorders
5) Diabetes -Preeclampsia is observed in 15-20% of
pregnancies complicated by type 1 diabetes mellitus
without nephropathy and approximately 50% in the
presence of nephropathy.
6) Low PAPP-A , two vessel cord and multiple pregnancy
7) IVF pregnancy
Biochemical markers. In the first trimester, an
unexplained low pregnancy-associated plasma protein
A or human chorionic gonadotropin (hCG) is
associated with an increased risk of placental-related
diseases such as IUGR or preeclampsia.
Early growth restriction. Low first-trimester
measurement of crown-rump length in pregnancies
dated by the last menstrual period is also linked with
FGR.
Slow growth between the first and second trimester is
able to identify a subgroup of slow-growing babies that
are at increased risk of perinatal death before 34
weeks’ gestation, in most cases with growth restriction.
Biochemical markers - an unexplained elevation of
serum alpha-fetoprotein, hCG, or inhibin-A is also
associated with these adverse outcomes.
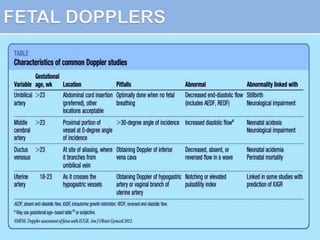
Uterine artery Dopplers -. Uterine Doppler
evaluation in the second or first trimester has
been proposed as a screening tool for early-onset
IUGR,with detection rates of about 75% and 25%,
respectively, for a false-positive rate of 5-10%.
These sensitivities are higher for predicting early
IUGR associated with preeclampsia and lower for
late IUGR.
SCREENING IN SECOND
TRIMESTER
Different strategies combining maternal risk
factors, blood pressure, and biochemical
markers have been published with detection
rates greater than 90% for early-onset
preeclampsia and associated IUGR
Serial fundal height assessment
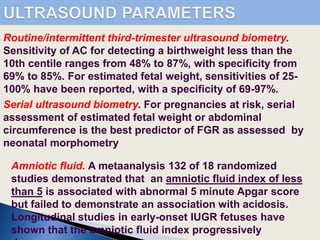
Routine/intermittent third-trimester ultrasound
biometry
Serial ultrasound biometry. For pregnancies at
risk due to past or current situation , serial
assessment of estimated fetal weight or
abdominal circumference is the best predictor of
FGR as assessed by neonatal morphometry.
Therefore, serial biometry is the recommended
gold standard
Serial ultrasound biometry. For pregnancies at risk, serial
assessment of estimated fetal weight or abdominal
circumference is the best predictor of FGR as assessed by
neonatal morphometry
Amniotic fluid. A metaanalysis 132 of 18 randomized
studies demonstrated that an amniotic fluid index of less
than 5 is associated with abnormal 5 minute Apgar score
but failed to demonstrate an association with acidosis.
Longitudinal studies in early-onset IUGR fetuses have
shown that the amniotic fluid index progressively
Routine/intermittent third-trimester ultrasound biometry.
Sensitivity of AC for detecting a birthweight less than the
10th centile ranges from 48% to 87%, with specificity from
69% to 85%. For estimated fetal weight, sensitivities of 25-
100% have been reported, with a specificity of 69-97%.
First, the standard is customized for sex as well as
maternal characteristics such as height, weight,
parity, and ethnic origin based on-one size does not
fit all theory.
Second, pathological factors such as smoking,
hypertension, diabetes, and preterm delivery are
excluded to predict the optimum weight that a baby
can reach at the end of a normal pregnancy.
Third, the term optimal weight and associated
normal range is projected backward for all
gestational age points, using an ultrasound growth
based proportionality curve
It is calculated by computer software
CUSTOMISED GROWTH CHART –
THREE PRINCIPLES
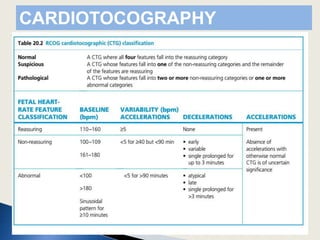
CARDIOTOCOGRAPHY
For the practicing obstetrician, these problems
can be summarized in following five important
questions:
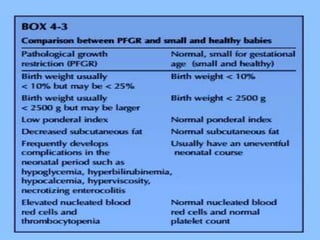
?? How to recognize that the fetus is small
?? How to differentiate between the fetuses that
are small and healthy and the fetuses that have
pathological growth restriction?
?? Which is the appropriate fetal surveillance
method and follow up interval ?
?? How to manage the pregnancies afflicted by
pathological fetal growth restriction (PFGR) as per
their staging of deterioration ?
?? How to optimize the timing and mode of
MANAGEMENT OF IUGR
ANTEPARTUM COMPLICATIONS are an increased
incidence of stillbirth, oligohydramnios, and
antepartum fetal distress.
INTRAPARTUM COMPLICATIONS are fetal
hypoxia, acidosis, and high rate of cesarean
delivery.
NEONATAL COMPLICATIONS are multiple and
include hypoglycemia, hyperbilirubinemia,
meconium aspiration, persistent fetal circulation,
hypoxic-ischemic encephalopathy, hypocalcemia,
OXYGEN – No role
PLASMAVOLUME EXPANDERS – no role
BETA MIMETICS - Larger, well-designed studies are needed
to evaluate the effects of betamimetics on fetal growth.
Since there is potential for adverse effects due to the
pharmacological characteristics of this group of drugs
BED REST IN HOSPITAL- There is not enough evidence to
evaluate the use of a bed rest in hospital policy for women
with suspected impaired fetal growth.
AMNIOINFUSION - Amnioinfusion with saline solution
should be one of the initial steps in the intrapartum
management of the PFGR fetus with decreased amniotic
fluid volume or early MSL.
SILDENAFIL ( NO promoter ) – Phosphodiesterase
inhibitors. The enzyme phosphodiesterase breaks down
cGMP, an enzyme critical to the effect of NO. But sildenafil
- Always determine the correct gestational age . - Patients
with high-risk factors, unreliable dates, and abnormal or
difficult to assess uterine growth are at risk for carrying
small fetuses.
-In the majority of cases the clinical findings and
ultrasound measurements allow only the diagnosis of
“small fetus.” The majority of small fetuses are healthy.
Only a modest proportion of small fetuses are truly
undernourished or PFGR.
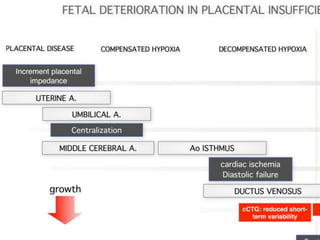
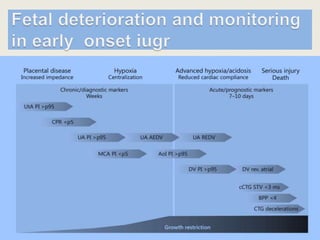
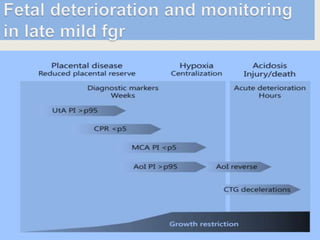
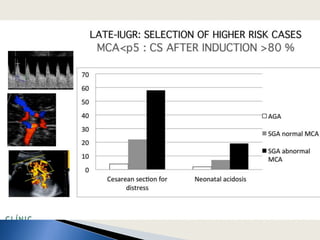
- To distinguish between fetuses that are small and healthy
and PFGR it is necessary to use serial growth charts and
Doppler assessment of the uterine, umbilical, and mid
cerebral artery resistance.Dopplers are not only diagnostic
- Uterine artery, UA, and MCA Doppler do not identify all
PFGR fetuses. Doppler technology is exclusively for the
identification of PFGR because of placental insufficiency.
Small fetal size in the presence of normal uterine,
umbilical, and midcerebral Doppler rules out placental
insufficiency .
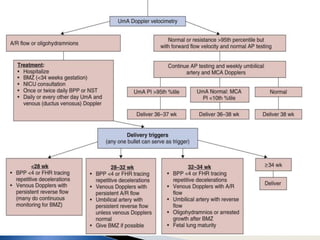
- The most important surveillance tests to follow the
PFGR fetus are the FHR monitoring by CTG and the
umbilical and cerebral Doppler. As long as the FHR
monitoring is normal and the Doppler does not show fetal
decompensation (ADF or RDF) expectant management is
adequate.
- The placentas of all PFGR babies should be examined by
a competent placental pathologist. In many cases the
placenta will provide evidence regarding the etiology of
the problem.
-The earlier in gestation IUGR is detected, the greater the
possibility of developmental problems later in life. The
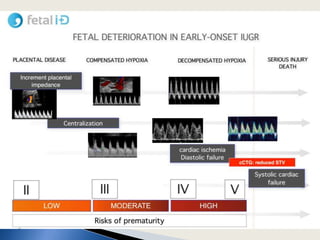
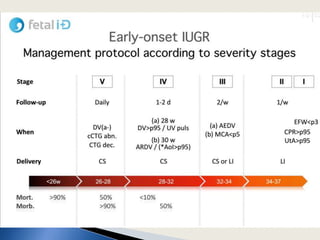
Staging system and management
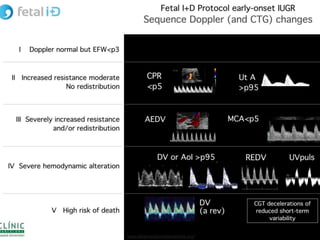
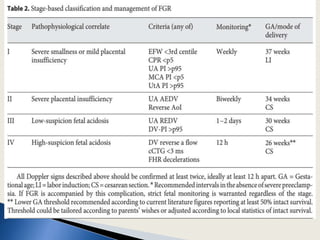
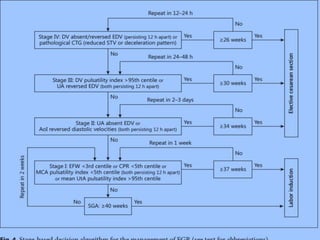
· Stage 0 SGA fetuses have a good prognosis. They are managed as outpatient with Doppler assessment every
2 weeks. If the Doppler remains normal, delivery is recommended at term. If the Doppler becomes abnormal, these
fetuses are managed as Stage I IUGR fetuses.
· Stage I IUGR fetuses are considered to have mild growth restriction, and affected mothers who are without
preeclampsia are usually managed as outpatients. Antenatal corticosteroids should be given at time of diagnosis. In
these fetuses, twice-weekly antenatal testing is recommended. If the non-stress testing (NST) remains reactive and
the AFI remains >5.0 cm, delivery is recommended at 37 weeks’ gestation. If the umbilical artery Doppler becomes
absent, these fetuses should be managed as Stage II IUGR.
· Stage II IUGR fetuses should be managed as inpatients. During hospital admission, the fetuses should undergo
daily antenatal testing with twice-daily NST and daily biophysical profile (BPP). If the NST remains reassuring and
the BPP score remains between 6 and 8 of 8, continuation of expectant management is recommended. In addition,
antenatal corticosteroids should be given at time of diagnosis. Delivery is recommended at 34 weeks. If any of the
aforementioned NSTs become non-reassuring or if the BPP score is 4 of 8 on 2 occasions at least 4 hours apart,
immediate delivery is recommended. Delivery should occur via cesarean delivery because fetuses with an
absent/reversed flow of the umbilical artery will not tolerate labor induction.
· Stage III IUGR fetuses are managed the same as Stage II except for delivery at 32 weeks’ gestation, regardless
of gestational age at time of diagnosis. As with Stage I and II, antenatal corticosteroids should be given at time of
diagnosis.
The advantage of the above scoring system is its simplicity. Only fetal biometry, sonographic interrogation of three
fetal vessels, and the amniotic fluid index are needed. It also allows classification of all small fetuses. Of note is that
if the umbilical artery and middle cerebral artery Doppler is normal, it is determination of flow velocity waveforms of
the ductus venosus is unnecessary because it will be normal as well. The presence of IUGR in the setting of
preeclampsia should not deter standard management of preeclampsia.
It is important to note the rate of mortality in the staging system.29 No deaths occurred in Stage 0 or Stage I fetuses,
whereas the mortality for stage III fetuses is high (50% if there was reversal of flow in the ductus venosus; 85%
mortality was observed when reversal of flow in the ductus venosus was present in combination with one of the other
parameters that characterize stage III), whereas the mortality in stage II IUGR fetuses was intermediate between
stages I and III (Figure 4). Also, studies have shown that fetuses can survive for days or weeks with reversal of flow
in the ductus venosus.29 A recent preliminary study reported that fetuses with reversal of flow in the ductus venosus
will not necessarily be acidemic at birth.30 In addition, the majority of affected pregnancies have an AFI <5 cm before