


























FETAL GROWTH RESTRICTION
POOJA SANALKUMAR
INTRODUCTION
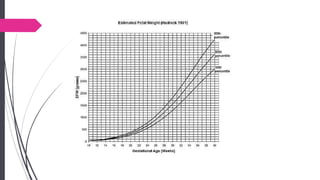
 A condition where fetal weight is below 10th percentile or 2SD for the
gestational age.
 Fetus fails to reach its genetic growth potential  fetus is SMALL for
GESTATIONAL AGE (SGA)  increased risk of perinatal morbidity and
mortality.
 Incidence: 3-10% of infants.
NORMAL GROWTH
In 3 phases
1. Cellular hyperplasia phase:
 increase in cell number.
 lasts for first 16 weeks of gestation.
2. Phase of concomitant hyperplasia & hypertrophy:
 increase in cell size and number.
 Between 16 to 32 weeks.
3. Cellular hypertrophy phase:
 Increase in size- fetal glycogen & fat deposition takes place.
 Between 32 weeks to term.
Contin.
Growth rates during 3 phases:
 15 weeks- 5g/day
 24 weeks-15-20g/day
 34 weeks-30-35g/day
CLASSIFICATION
Depending upon onset(32 weeks of gestation)
 Early onset
 Late onset
Depending on pathologic process and time of onset.
 Type I or symmetrical or intrinsic IUGR
 Type II or asymmetrical or extrinsic IUGR
 Intermediate IUGR
CHARACTER SYMMETRICAL IUGR ASYMMETRICAL IUGR
Incidence 20-30% 70-80%
Growth inhibition
Hyperplastic stage - early
pregnancy
Hypertrophic stage - late
pregnancy
No. of cells reduced Normal but reduced in size
Growth parameters
HC/AC & Wt./Lt ratio <10
percentile
HC/AC ratio altered- Head sparing
effect
Ponderal index normal Low
Associated with
Uterine infections-CMV, rubella,
anemia, chromosomal
abnormalities, maternal
abuse
c/c hypertensive disorder, severe
malnutrition, genetic mutations
Baby size Uniformly small
Head – normal, rest of body- thin
& small
TYPE I or SYMMETRICAL or INTRINSIC IUGR
 Anthropometric measurements below 10 percentile for gestational age.
 Causes: TORCH infections, chromosomal disorders & congenital
malformations.
 25% severe early IUGR have aneuploidy.
TYPE II or ASYMETRICAL or EXTRINSIC IUGR
 Characterized by relatively greater decrease in abdominal size than head
circumference.
 D/t uteroplacental insufficiency- redistribution of blood flow to vital
organs(brain sparing effect), head growth remains normal while
abdominal girth slows down.
 Leads to chronic hypoxia and fetal death.
INTERMEDIATE IUGR
 Combination of type I & type II
 5-10% of IUGR.
ETIOLOGY
1. MATERNAL FACTORS
2. FETAL FACTORS
3. PREGNANCY COMPLICATIONS
1.MATERNAL FACTORS
 Extremes of maternal age.
 Hypertension and vascular disease
 Constitutionally small mothers
 Chronic maternal hypoxia: d/t pulmonary disease, cyanotic
heart disease & severe anemia
 Prothrombotic disorder: antiphospholipid syndrome
 Maternal malnutrition
MATERNAL
FACTORS
 Infection: CMV, Toxoplasmosis, Varicella-Zoster, Malaria
 Substance abuse & cigarette smoking
 Teratogens: Folate antagonists, antineoplastic agents,
anticonvulsants.
 History of IUGR in previous pregnancies.
 Assisted reproductive technologies
2. FETAL FACTORS
 Congenital malformations
 Fetal infections: CMV, HIV, toxoplasma, etc.
 Chromosomal abnormalities: trisomy 21 & trisomy 18
 Genetic: agenesis of pancreas, galactosemia, phenylketonuria.
3. PREGNANCY COMPLICATIONS
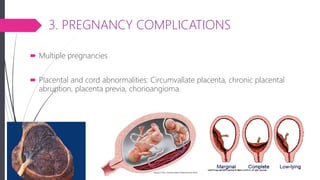
 Multiple pregnancies
 Placental and cord abnormalities: Circumvallate placenta, chronic placental
abruption, placenta previa, chorioangioma.
RISK FACTORS
MAJOR RISK FACTORS
 Maternal age >40 years
 Smoker > 11 cigarettes per day
 Cocaine
 Daily vigorous exercise
 Previous SGA baby
 Previous stillbirth
 Maternal SGA
 C/c HTN
 Diabetes & vascular diseases
 Renal impairment
 Antiphospholipid syndrome
 Echogenic bowel
 preeclampsia
 Severe pregnancy induced HTN
 Low maternal weight
 PAPP-A <0.4 MoM
MINOR RISK FACTORS
 Maternal age > 35 years
 Nulliparity
 BMI <20
 BMI 25-29.9
 Smoker 1-10 per day
 Low fruit intake per day
 Preeclampsia
 Pregnancy interval < 6 months
 Paternal SGA
COMPLICATIONS
FETAL COMPLICATIONS
 Antenatal: c/c fetal distress, hypoxia & acidosis, fetal death
 After birth:
 Asphyxia and RDS
 Hypoglycemia
 Meconium aspiration syndrome
 Hypothermia
 Pulmonary h’age
 Polycythemia
 Hyperviscosity syndrome
 Necrotizing enterocolitis
 Intraventricular h’age
DIAGNOSIS OF IUGR
DIAGNOSIS OF IUGR
1. SCREENING:
 Accurate knowledge of gestational age
 Past history of IUGR & any maternal complication
 On obstetric palpation, height of uterus <4 weeks or more for the
gestational age.
 Uterine fundal height: serial fundal height measurements throughout
pregnancy.
2. DIAGNOSIS: Ultrasound measurements:
 Fetal biometry: fetal parietal diameter(BPD), femur length (FL) &
abdominal circumference(AC) are measured.
 AC diameter is considered to be correlated with fetal weight.
 Increase in AC of <10mm over a 2 week period is suggestive of IUGR.
 Body proportions: HC/AC ratio, FL/AC ratio & ponderal index for
asymmetric IUGR.
 HC/AC ratio: size of liver is disproportionately smaller than head
circumference or length of femur
 Amniotic fluid volume: Oligohydramnios d/t ↓ fetal urine production.
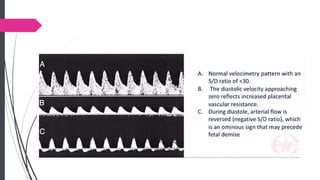
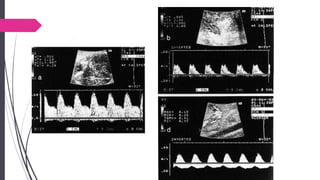
 Doppler velocimetry: abnormal umbilical artery Doppler velocimetry-
increased systolic-diastolic ratio, absent or reverse end-diastolic flow.
 In Hypoxic fetus, ratio of MCA S/D value to umbilical a. S/D value reflects fetal
compromise.
MANAGEMENT
1. BEFORE 37 WEEKS OF GESTATION
 Exclude any fetal malformations
 Monitor fetal growth & well-being
MEDICAL INTERVENTION
 Adequate BED REST in left lateral position- increase uteroplacental flow.
 Maternal OXYGEN THERAPY
 Pharmacotherapy: low dose aspirin, beta mimetics, heparin, calcium channel
blockers
 Treating associated MATERNAL CONDITIONS: anemia, hypertension
 High protein diet
ASSESSMENT OF FETAL GROWTH
 CLINICAL ASSESSMENT – maternal wt. and uterine growth charts (weekly)
 ULTRASOUND ASSESSMENT: fetal parameters(BPD, HC, FL, AC) are
measured every 10 -14 days
ASSESSMENT OF FETAL WELL-BEING
 NON-STRESS TEST: based on the principle that fetal heart rate
accelerates temporarily in response to fetal movements.
 DAILY FETAL MOVEMENT COUNT: regular & frequent fetal movements.
 BIOPHYSICAL PROFILE (MANNING’S)
OBSTETRIC INTERVENTION
 Indications of delivery of IUGR:
 Arrest of growth over 2-4 week interval.
 Low BPP score
 Oligohydramnios at >34 weeks determined by tests of fetal well being
 REDF
 Indications of delivery at 37 weeks in IUGR:
 Mild or uncomplicated IUGR
 End diastolic flow is present
 Reassuring antepartum fetal testing
AT 37 WEEKS OR MORE
 Mild IUGR & fetus is not under stress, labour can be induced and vaginal
delivery can be attempted.
 Severe IUGR: cesarean section
INDICATIONS FOR CESAREAN SECTION
 Severe preeclampsia
 Malpresentations
 Fetal compromise
 ARED flow
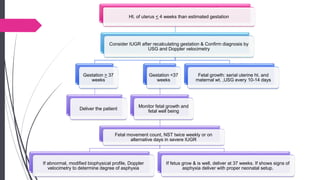
Ht. of uterus < 4 weeks than estimated gestation
Consider IUGR after recalculating gestation & Confirm diagnosis by
USG and Doppler velocimetry
Gestation > 37
weeks
Deliver the patient
Gestation <37
weeks
Monitor fetal growth and
fetal well being
Fetal movement count, NST twice weekly or on
alternative days in severe IUGR
If abnormal, modified biophysical profile, Doppler
velocimetry to determine degree of asphyxia
If fetus grow & is well, deliver at 37 weeks. If shows signs of
asphyxia deliver with proper neonatal setup.
Fetal growth: serial uterine ht. and
maternal wt. ,USG every 10-14 days
THANK YOU
Daily fetal movements count
Methods:
 Mother records the time taken each day to feel 10 movements.
 Normally, its perceived in 2-3 hours.
 Failure to perceive 10 movements in 12hrs. Time needs assessment by
biophysical methods.
 Monitoring number of movements made by the fetus in one hour.
 Done on full stomach & preferably at the same period of time everyday.
Non-stress test
 Normal/Reactive non stress test- 2 or more acceleration pf heart rate
(15beats or more) each lasting for >15 secs. with fetal movements within 20
mins. of testing.
 To account for fetal sleep cycles, recording may be done for 40 mins.
Before concluding insufficient fetal reactivity.
 Non-reactive: if there is no fetal movements or fetal accelerations for a
period of 40 mins.
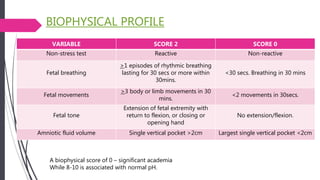
BIOPHYSICAL PROFILE
VARIABLE SCORE 2 SCORE 0
Non-stress test Reactive Non-reactive
Fetal breathing
>1 episodes of rhythmic breathing
lasting for 30 secs or more within
30mins.
<30 secs. Breathing in 30 mins
Fetal movements
>3 body or limb movements in 30
mins.
<2 movements in 30secs.
Fetal tone
Extension of fetal extremity with
return to flexion, or closing or
opening hand
No extension/flexion.
Amniotic fluid volume Single vertical pocket >2cm Largest single vertical pocket <2cm
A biophysical score of 0 – significant academia
While 8-10 is associated with normal pH.