D.G.F. CME ON
Fetal growth restriction:
Evidence based management
29TH
JANUARY 2018 at WOOD APPLE DELHI
Contributors
Dr. Kiran Aggarwal Dr. Sharda Jain Dr. Jyoti Agarwal
PART
ONE
DR KIRAN AGGARWAL
DIRECTOR PROFESSOR
LADY HARDINGE MEDICAL COLLEGE AND ASSOCIATED
HOSPITALS
Part 1
Fetal Growth Restriction
• Definition: Less than 10th
percentile weight for gestational age on a
singleton growth curve defined as small for gestational age.(SGA)
a. Constitutionally small fetus who has achieved its normal growth
potential
b. Small fetus with growth restriction with increased risk of perinatal
morbidity and mortality
c. Fetus who is not small but has not achieved its genetic potential
Constitutionaly small fetus
Modest smallness 5th
till 10th
percentiles.
Normal growth velocity across gestation.
Normal physiology i.e. normal amniotic fluid volume and umbilical
artery Doppler. abdominal circumference growth velocity above
lowest decile and appropriate size in terms of maternal
characteristics( height weight race and ethnicity).
Lower threshold (< 3rd
percentile) may help distinguish small fetus at
increased risk of adverse outcome from the small fetus at low risk.
(PORTO Trial AJOG, 2013)
Diagnosis of FGR
• Sonographic estimation of fetal weight is the single best
morphometric test to screen for and diagnose fetuses with weight less
than 10th
centile.
• Other test like AC HC and ratios may overlook symmetrical FGR.
• AC is the most sensitive single morphometric indicator of FGR.
Sens, spec, positive and negative predictive values of 61, 95, 86, 83 %.
• Measurement of AC was more predictive of asymmetric FGR than
head circumference or BPD or combination of AC with either of these.
The optimal time to screen for FGR was 34 wks app.
• Biochemical markers of hypoxia and acidemia are more common
when the AC is below the 5th
percentile.
Fetal weight estimations
• WHO charts for fetal growth and common ultrasound biometric
measurements based on longitudinal data derived from 10 countries.
• Equations that use AC, BPD, FL seem to provide the most accurate
estimates of fetal weight.
• EFW performed within one to two weeks of delivery is more predictive
than when performed earlier in gestation.
• The sensitivity of EFW for predicting FGR and adverse outcome is
highest for infants with birth weight <3rd
centile.
• Customised charts take care of maternal variables like parity ethnicity
height, weight , age and fetal gender.
USG parameters
• Growth velocity use of any parameter requires exact dating. If
unavailable serial sonographic examinations at two week intervals
should be done.
• HC/AC ratio for asymmetric FGR decreases linearly through out
pregnancy and a ratio greater than 2 SD above the mean for GA is
considered abnormal.
• FL/AC ratio is independent of GA in normally grown fetuses in last
half of pregnancy however not good for symmetric FGR.
• Ponderal index poor correlation between fetal and neonatal PI.
Transverse cerebellar diameter
• Transverse cerebellar diameter not affected in FGR may serve as and
independent indicator of GA against which other potential deviations
of growth may be compared.
• TCD /AC ratio exceeding 2SD above the mean is predictive of
asymmetrical growth restriction.
• The status of the TCD/AC ratio as a predictor of FGR remains
controversial due to limited data from large and controlled studies.
Amniotic fluid volume
• Amniotic fluid volume; decreased urine production due to hypoxia
induced redistribution of blood flow to vital organs at the expense of
less vital organs such as kidney.
• r/o ruptured membranes, congenital genitourinary anomalies or
prolonged pregnancy
• Oligohydramnios with EFW <3rd
percentile is predictive of adverse
outcome.
Assessment
Maternal, placental or fetal proceses.
Complete history, physical examination to assess for maternal
disorders.
Obstetrical imaging and laboratory evaluations for fetal and placental
aetiologies.
Detailed fetal anatomic survey for congenital anomalies and 20-60%
of malformed infants are SGA.
Anomalies ass with FGR include omphalocele diaphragmatic hernia
skeletal dysplasia and some congenital heart defects.
Fetal echocardiogram is indicated if level II USG suggest any cardiac
abnormality.
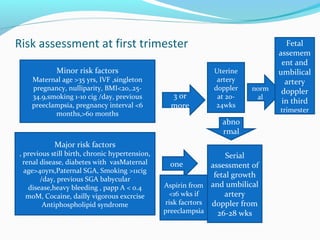
Risk assessment at first trimester
Minor risk factors
Maternal age >35 yrs, IVF ,singleton
pregnancy, nulliparity, BMI<20,.25-
34.9,smoking 1-10 cig /day, previous
preeclampsia, pregnancy interval <6
months,>60 months
Major risk factors
, previous still birth, chronic hypertension,
renal disease, diabetes with vasMaternal
age>40yrs,Paternal SGA, Smoking >11cig
/day, previous SGA babycular
disease,heavy bleeding , papp A < 0.4
moM, Cocaine, dailly vigorous excrcise
Antiphospholipid syndrome
3 or
more
one
Uterine
artery
doppler
at 20-
24wks
Serial
assessment of
fetal growth
and umbilical
artery
doppler from
26-28 wks
norm
al
Fetal
assemem
ent and
umbilical
artery
doppler
in third
trimester
abno
rmal
Aspirin from
<16 wks if
risk facrtors
preeclampsia
Pregnancy assessment
• Accurate assessment of gestational age.
• Assessment of risk factors
• Symphysial fundal height measurement:
• fundal height in cms that is at least three cm below the GA in weeks ( 13-86%
sensitivity).
• Serial measurement of symphysis fundal height (SFH) is recommended at each
antenatal appointment from 24 weeks of pregnancy as this improves prediction of
a SGA neonate
• Abdominal palpation: clinical assessment of fetal size by abdominal palpation does
not perform well as a test for detecting FGR ( 30-50% sensitivity).(rcog 2013)
• Serial ultrasound measurement of fetal size and assessment of wellbeing with umbilical
artery Doppler should be offered in cases of fetal echogenic bowel..
Fetal genetic studies
 Offer referral for a detailed fetal anatomical survey and uterine artery
Doppler by a fetal medicine specialist if severe SGA is identified at the 18–20
week scan.
 Cell free DNA followed by fetal karyotype/microarray should be offered in
severely SGA fetuses with structural anomalies and in those detected before 23
weeks of gestation, especially if uterine artery Doppler is normal.
 No structural abnormalities but presence of soft ultrasound markers
associated with an increased risk of aneuploidy such as thickened nuchal fold,
choroid plexus cyst and abnormal hand positioning.
 If FGR after 24 wks, asymmetric, and anatomy is normal no need for screening
for genetic abnormalities.
Work up for infection
If infection is suspected clinically because of maternal history,
examination or fetal USG findings maternal serum should be
examined for seroconversion.
Cytomegalovirus, toxoplasmosis. rubella and varicella.
Amniotic fluid DNA testing if indicated
Sonographic markers for fetal infection are often nonspecific but
include echogenicity and calcification of brain and or liver and
hydrops
Malaria can also cause FGR
Serological screening for congenital cytomegalovirus (CMV) and
toxoplasmosis infection should be offered in severely SGA fetuses.
Testing for syphilis and malaria should be considered in high risk
populations.(RCOG 2014)
Thrombophilia
Inherited thrombophilic disorders screening is not recommended as
association with FGR is weak.
Antiphospholipid syndrome acquired thrombophilia is clearly
associated with FGR.
Sequence of doppler and biophysical changes in
FGR
Reduction in umbilical venous flow is initial hemodynamic change.
Venous flow is redistributed away from fetal liver and towards the
heart. Liver size decreases and abdominal circumference lags which is
the first biometric sign of fetal growth restriction.
Umbilical artery doppler index increases and diminished diastolic
flow due to increased resistance in the placental vasculature.
Brain sparing effect
Middle cerebral artery doppler index decreased, increased end
diastolic flow preferential perfusion of the brain
Increasing placental resistance absent and then reversed end diastolic
flow in the umbilical artery.
MCA doppler index normalizes or abnormal increases as diastolic flow
falls due to loss of brain sparing hemodynamic changes
Cardiac decompensation
MCA doppler index normalizes or abnormal increases as diastolic flow
falls due to loss of brain sparing hemodynamic changes.
Cardiac performance deteriorates due to chronic hypoxia and
nutritional deprivation absent or reversed end diastolic flow in the
ductus venousus and pulsatile umbilical venous flow may develop.
These may be the preterminal events.
NST becomes nonreactive BPP score falls and late decelerations
accompany contractions.
MANAGEMENT
For structurally and chromosomally normal fetuses. Mostly by
uteroplacental insufficiency.
Serial ultrasound evaluation of fetal growth, fetal behaviour (BPP)
impedance to blood flow doppler velocimetry
Identify those fetuses at highest risk inutero and will benefit from
preterm delivery.
management
Hospitalisations: on case to case to basis where intensive monitoring
is needed. Provides monitoring as in REDF interventions promptly but
no evidence that bed rest improves fetal growth or outcome.
Growth velocity use of any parameter requires exact dating. If
unavailable serial sonographic examinations at two-four week
intervals should be done. For mild FGR longer interval and for
moderate or severe shorter interval.
Nonstress test and biophysical profile
BPP evaluates both acute and chronic fetal physiologic parameters, is
easy and fetal death within one week of a normal test score is rare.
If NST is used amniotic fluid volume assessment should also be
performed weekly. chronic placental insufficiency results in both FGR
and oligohydramnios.
If doppler indices are normal normally NST and BPP are not needed.
In other FGR weekly,
if with oligohydramnios, preeclampsia .decelerating fetal growth,
severe FGR increased doppler index twice per week.
For absent or reversed diastolic flow daily.
Umbilical artery Doppler
Not for screening and diagnosis of FGR. It is for evaluation and
management of suspected FGR..
abnormal doppler is:pulsatility index >95th
centile or AREDF
Combination of EFW less than 10th
percentile and abnormal umbilical
artery doppler is highly predictive of FGR and is best tool available for
identifying the growth restricted fetus at risk of adverse outcome.
Weekly doppler of umbilical artery if FGR.
If follow up normal then two weekly doppler esp if weight >5 th
centile,and normal growth and amniotic fluid.
If PI > 95 th percenile then weekly
If absent or reversed it is a sign of impendiing fetal CVS and metabolic
derangements.
Doppler studies
Fetal cerebral arteries in normal pregnancies has a high resistance
flow, with FGR increased flow causes increased end diastolic velocities
and decreased s/d ratio. High placental impedance precedes the onset
of the redistribution reflex.( brain sparing).
Cerebroplacental ratio: it is the MCA PI divided by the umbilical
artery PI. Low CPR indicates fetal blood flow distribution and is
predictive of adverse neonatal outcome.
Low CPR with abnormal UA doppler values predicts adverse neonatal
outcome, cesarean delivery for fetal distress.( PORTO TRIAL).
Venous doppler assessment
 It is for monitoring of fetal well being and is used for prediction of stillbirth
and acidemia over use of umbilical artery doppler alone.
 In normal pregnancies flow is forward and uniform.
 Absent or reversed a wave or pulsatile umilical venous flow are late findings
occurring two weeks after arterial changes.
 Its abnormalities constitute a late circulatory finding and impending acidemia
and death.
 Fetal survival of more than a week is difficult. TRUFFLE trial showed no
immediate neonatal benefit from delaying till DV abnormalities and only a
marginal two year neurodev benefit.(LANCET 2015)
DOPPLER STUDIES AND 3D USG
 Fetal descending aorta.
Normal flow is pulsatile with a minimal end diastolic component. Elevated
pulsatility index is associated with both FGR and adverse outcomes.
Absent EDF in descending aorta for prediction of FGR with FHR
abnormalities sensitivity and specificity is 85 and 80 %.
These pregnancies are with higher rates of CS, right ventricular failure and
perinatal mortality
 Three dimensional ultrasound measurement of thigh femur or humerus
volume measurement: simple more accurate than two dimensional techniques
but is not widely assessed and available.
MANAGEMENT
 When umbilical artery Doppler flow indices are normal it is reasonable to
repeat surveillance every 14 days.
 More frequent Doppler surveillance may be appropriate in a severely SGA
fetus. When umbilical artery Doppler flow indices are abnormal (pulsatility or
resistance index > +2 SDs above mean for gestational age) and delivery is not
indicated repeat surveillance twice weekly in fetuses with end–diastolic
velocities present and daily in fetuses with absent/reversed end–diastolic
frequencies.
 CTG should not be used as the only form of surveillance in SGA fetuses.
Interpretation of the CTG should be based on short term fetal heart rate
variation from computerised analysis.
MANAGEMENT
 Ultrasound assessment of amniotic fluid volume should not be used as the
only form of surveillance in SGA fetuses. Interpretation of amniotic fluid
volume should be based on single deepest vertical pocket.
 Biophysical profile should not be used for fetal surveillance in preterm SGA
fetuses
 In the preterm SGA fetus, middle cerebral artery (MCA) Doppler has limited
accuracy to predict acidaemia and adverse outcome and should not be used to
time delivery.
 In the term SGA fetus with normal umbilical artery Doppler, an abnormal
middle cerebral artery Doppler (PI < 5th centile) has moderate predictive
value for acidosis at birth and should be used to time delivery.
 Ductus venosus Doppler has moderate predictive value for acidaemia and
adverse outcome. Ductus venosus Doppler should be used for surveillance in
the preterm SGA fetus with abnormal umbilical artery Doppler and used to
time delivery
ANTENATAL STEROIDS
One course between 24-34 weeks of gestation in the week
before delivery is expected. The steroids in babies with
absent end DF often show slight improvement in blood
flow and very sick ones don’t.
Maternal interventions
Any intervention in healthy women doesn’t help growth of FGR
fetuses.
Maternal nutritiional supplements, oxygen therapy plasma volume
expansion low dose aspirin bed rest and anticoagulation doesn’t help.
Use of phosphodiesterase 5 enzyme inhibitor like sildenafil or a statin
may be promising but under investigation.
Antihypertensives doesn’t help
Cessation of smoking is of value
Timing of delivery
 Growth restriction intervention trial (GRIT)
 Disproportionate intrauterine growth intervention trial at term (DIGITAT)
 Trial of randomized umbilical and fetal flow in europe(TRUFFLE)
 DECISION: gestational age, doppler of umbilical artery , biophysical score, ductus
venosus doppler, and other high risk factors.
 Greatest risk before 32 weeks and between 26-29 weeks of gestation each day in
utero improves suvival 1-2%.
 Abnormal ductus venosus doppler deliver immediately
 REDF > or equal to 32 weeks deliver
 AEDF > or equal to 34 deliver
 REDF <32 OR AEDF<34 weeks regardless of presence or absence of
oligohydramnios , daily BPP delay till 32 weeks ( REDF) and 34 wks (AEDF), till
BPP is normal, if ductus venosus abnormal or BPP abnormal then deliver.
 Decreased diastolic flow , BPS twice a week deliver at 37 weeks if with oligoamnios
preeclampsia or weight <5th
centile.
 Normal umbilical artery doppler if in absence of risk factors deliver at 39-40 weeks
Method of delivery
 Unfavourable cervix is not a reason to avoid induction.
 In the SGA fetus with umbilical artery AREDV delivery by caesarean section is
recommended
 if NST and BPP is normal antenatally trial of labor with continuous
intrapartum monitoing is reasonable.
 In the SGA fetus with normal umbilical artery Doppler or with abnormal
umbilical artery PI but end–diastolic velocities present, induction of labour
can be offered but rates of emergency caesarean section are increased and
continuous fetal heart rate monitoring is recommended from the onset of
uterine contractions.
 Early admission is recommended in women in spontaneous labour with a
SGA fetus in order to instigate continuous fetal heart rate monitoring
consequences
Mother with SGA may develop IHD
Babies may have obesity, metabolic dysfunction
hypertension and CAD.
RECURERENCE RISK: risk of nonanomalous SGA <5th
centile in second pregnancy is 23%
Prevention in subsequent pregnancies: treat cause,
address smoking, alcohol, malaria, nutritional, low dose
aspirin in women with high risk of preeclampsia
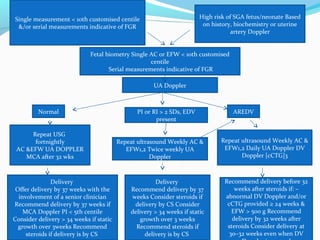
Single measurement < 10th customised centile
&/or serial measurements indicative of FGR
High risk of SGA fetus/neonate Based
on history, biochemistry or uterine
artery Doppler
Fetal biometry Single AC or EFW < 10th customised
centile
Serial measurements indicative of FGR
UA Doppler
Normal PI or RI > 2 SDs, EDV
present
AREDV
Repeat USG
fortnightly
AC &EFW UA DOPPLER
MCA after 32 wks
Delivery
Offer delivery by 37 weeks with the
involvement of a senior clinician
Recommend delivery by 37 weeks if
MCA Doppler PI < 5th centile
Consider delivery > 34 weeks if static
growth over 3weeks Recommend
steroids if delivery is by CS
Repeat ultrasound Weekly AC &
EFW1,2 Twice weekly UA
Doppler
Delivery
Recommend delivery by 37
weeks Consider steroids if
delivery by CS Consider
delivery > 34 weeks if static
growth over 3 weeks
Recommend steroids if
delivery is by CS
Repeat ultrasound Weekly AC &
EFW1,2 Daily UA Doppler DV
Doppler [cCTG]3
Recommend delivery before 32
weeks after steroids if: –
abnormal DV Doppler and/or
cCTG provided ≥ 24 weeks &
EFW > 500 g Recommend
delivery by 32 weeks after
steroids Consider delivery at
30–32 weeks even when DV
THANK YOU
Join Delhi Gynaecologist forum
East , South , West , North, Central
Head Office : 11 Gagan vihar near karkari morh
flyover Delhi – 51
www.delhigynaecologistforum.com