2ND UNIT
ANTI-HYPERTENSIVE AGENTS
Prepared by
G. Nikitha, M.Pharmacy
Assistant Professor
Department of Pharmaceutical Chemistry
Sree Dattha Institute Of Pharmacy
Hyderabad
1
Subject: Medicinal Chemistry-II
Year: B.Pharmacy 3rd Year
Semister: 1st Semister
CONTENTS
 Introduction.
 Types of Hypertension
 Ideal Characteristics
 Classification
 Mechanism of action .
 SAR.
 Structure
 Synthesis.
 Adverse Drug Reactions .
 Uses.
 References
2
INTRODUCTION
 Hypertension is defined as an increase in the arterial blood pressure
above normal.
 It is the most common disorder affecting the heart and blood vessels.
 The blood pressure (Bp) is said to be normal, if the systolic Bp is
120mm Hg and diastolic is 80mm Hg i.e, 120/80 mm Hg.
 An individual is said to be pre hypertensive if systolic pressure is
121-139 mm Hg or diastolic pressure is 81-89 mm Hg.
 An individual is said to be hypertensive if his systolic pressure is ≥
140 mm Hg or diastolic pressure is ≥ 90 mm Hg.
3
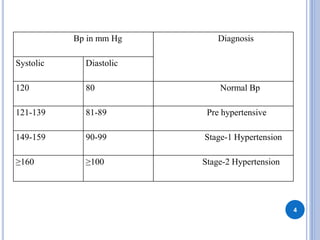
Bp in mm Hg Diagnosis
Systolic Diastolic
120 80 Normal Bp
121-139 81-89 Pre hypertensive
149-159 90-99 Stage-1 Hypertension
≥160 ≥100 Stage-2 Hypertension
4
TYPES OF HYPERTENSION
Hypertension is divided into two types.
1. Primary (Essential) Hypertension:
 In majority of cases, hypertension is of unknown cause and is known
as primary or essential hypertension. Even though a definite cause is
not known in primary hypertension the following factors may
contribute to the elevation of Bp.
a. Dietary intake of more sodium and less potassium.
b. Decrease in vascular synthesis of nitric oxide that is responsible for
vasodilatation.
c. In some cases, primary hypertension may be hereditary.
d. Advancement of age may also be responsible for primary
hypertension.
5
2. Secondary Hypertension:
 In some cases, hypertension may be secondary to other diseases.
a. Endocrine Disorder
b. Kidney Disorder
c. Muscular Disorder
6
IDEAL CHARACTERISTICS
 It should have specific site of action.
 It should control blood pressure
 It should be stable in light and heat
 It should not cause cardial, renal or cerebral damage
 It should be inexpensive
7
CLASSIFICATION
 The potential of a substance or drug to lower the blood pressure to
less than 140/90 mm Hg in hypertension patients is termed as
antihypertension activity.
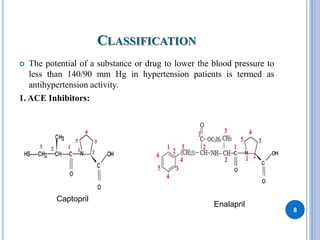
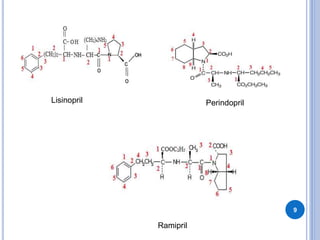
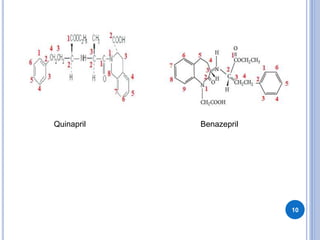
1. ACE Inhibitors:
8
Captopril
Enalapril
9
Lisinopril Perindopril
Ramipril
10
Quinapril Benazepril
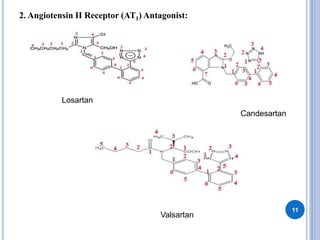
2. Angiotensin II Receptor (AT1) Antagonist:
11
Losartan
Candesartan
Valsartan
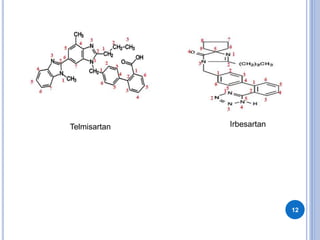
12
Telmisartan Irbesartan
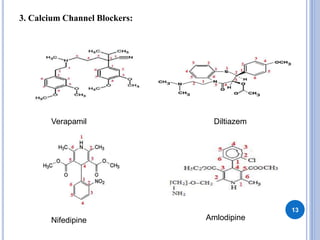
3. Calcium Channel Blockers:
13
Verapamil Diltiazem
Nifedipine Amlodipine
14
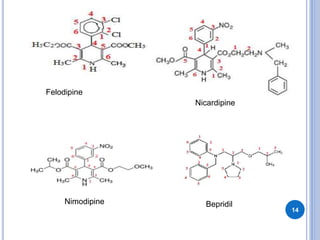
Felodipine
Nicardipine
Nimodipine Bepridil
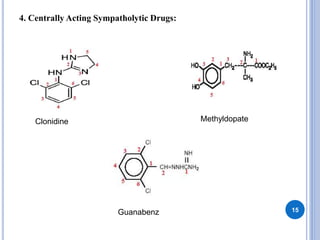
4. Centrally Acting Sympatholytic Drugs:
15
Clonidine Methyldopate
Guanabenz
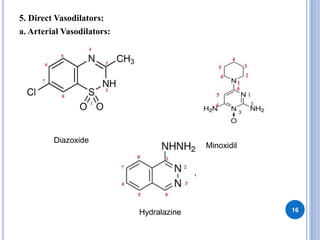
5. Direct Vasodilators:
a. Arterial Vasodilators:
16
Diazoxide
Minoxidil
Hydralazine
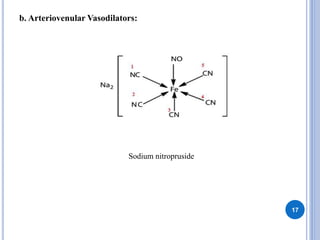
b. Arteriovenular Vasodilators:
17
Sodium nitropruside
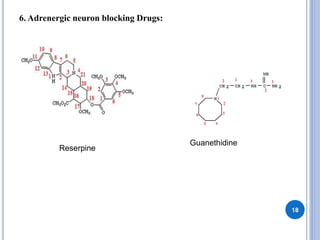
6. Adrenergic neuron blocking Drugs:
18
Reserpine
Guanethidine
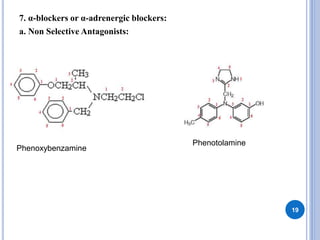
7. α-blockers or α-adrenergic blockers:
a. Non Selective Antagonists:
19
Phenoxybenzamine
Phenotolamine
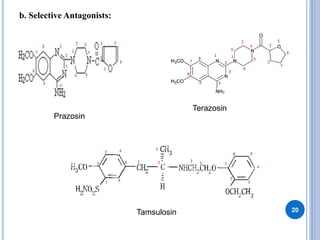
b. Selective Antagonists:
20
Prazosin
Terazosin
Tamsulosin
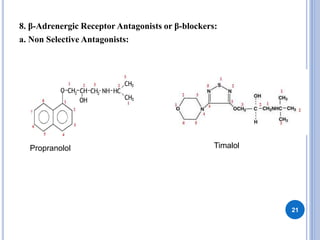
8. β-Adrenergic Receptor Antagonists or β-blockers:
a. Non Selective Antagonists:
21
Propranolol Timalol
22
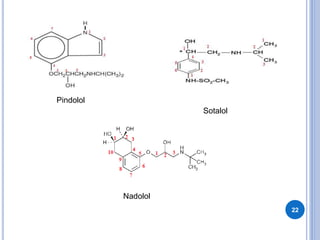
Pindolol
Sotalol
Nadolol
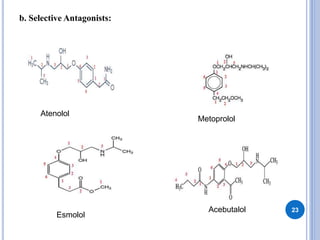
b. Selective Antagonists:
23
Atenolol
Metoprolol
Esmolol
Acebutalol
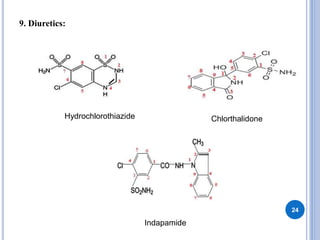
9. Diuretics:
24
Hydrochlorothiazide Chlorthalidone
Indapamide
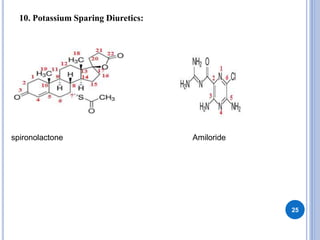
10. Potassium Sparing Diuretics:
25
spironolactone Amiloride
ACE INHIBITORS
26
 Angiotenion antagonists block the actions of angiotension II either
by inhibiting its synthesis (ACE inhibitors) or by inhibiting its action
at the receptors (angiotension II receptor antagonists).
27
Mechanism of Action:
Angiotension Converting Enzyme (ACE) is involved in the
1. Conversion of Angiotenion I to Angiotenion II which is a potent
vasoconstrictor. Angiotenion II stimulates the synthesis of
aldosterone which causes increased reabsorption ofsodium and water
fluid retention cardiac output blood pressure.
2. Degradation of bradykinin which is a potent vasodilator.
Thus, the inhibition of ACE by ACE inhibitors leads to
vasodilatation followed by decrease in Bp due to decreased
formation of Angiotenion II which in turn leads to reduced
aldosterone synthesis and increase bradykinin levels.
28
SAR:
1. Presence of carboxylic acid on N-ring is essential for the compound.
2. Presence of larger nitrogen containing heterocyclic rings will
enhance the potency of the compound by increasing its lipophilicity.
3. The zinc binding groups are essential for stabilization they may be
either sulfhydryl (-CH2SH) as in captapril, caroxylate ( ) as in
Lisinopril or phosphate ( ) groups as in fosinopril.
29
4. Presence of sulfuhydryl group leads shorter duration of action
because it facilitates the formation of dimmers and disulfides eg:
Captopril
5. Presence of carboxylate or phosphinate group facilitates the
esterification process, thus producing orally active prodrugs. R1 is
generally a methyl group to resemble the side chain of alanine.
6. When R1 is n-butylamine in dicarboxylate containing compounds it
resembles the lysine side chain and the compound is orally active
thus eliminating the need for it to be a Prodrug eg: Lisinopril.
7. When the stereochemistry of the drug (ACE inhibitors) is in
accordance with the stereochemistry of L-amino acid in normal
substrate the drug exhibits maximum activity.
30
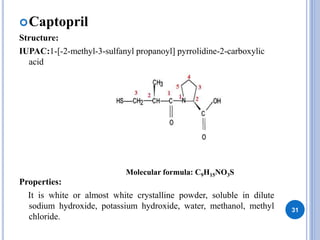
Captopril
Structure:
IUPAC:1-[-2-methyl-3-sulfanyl propanoyl] pyrrolidine-2-carboxylic
acid
Properties:
It is white or almost white crystalline powder, soluble in dilute
sodium hydroxide, potassium hydroxide, water, methanol, methyl
chloride.
31
Molecular formula: C9H15NO3S
Pharmacokinetics:
 It is well absorbed oral administration. Food delays the absorption of
captopril but not other drugs. Therefore captopril should be taken
one hour before meal. Captopril has faster onset of action but lesser
duration of action compared to Enalapril and Lisinopril. It is
metabolized in the liver and excreted in urine.
Adverse Drug Reactions:
 dry cough (should go away after you stop taking captopril),
 dizziness, shortness of breath, skin rash,
 a change in the way that foods taste
 Head ache, nausea, bowel upset
 Fetal toxicity, neutropenia (abnormal decrease in neutrophil count),
Angioedema (swelling of lips, tongue)
 Acute renal failure, in patients with renal artery stenosis.
 Weight gain
 Hypotension is seen in CHF patients and patients on diuretics.
32
Therapeutic Uses:
 Used in the treatment of hypertension, congestive heart failure
(CHF) and left ventricular (LV) dysfunction.
 Used in the treatment of myocardial infarction.
 Used in the treatment of diabetic and non-diabetic nephropathy.
 It is also used to treat kidney disease in people with diabetes.
Dose:
 25-50 mg b.i.d orally.
33
 Enalapril
Structure:
IUPAC:1-[-2-{-1-ethoxy-1-oxo-4-phenylbutan-2-yl] amino}
propanoyl]pyrrolidine-2-carboxylic acid
Properties:
White or off white crystalline powder, soluble in water, alcohol,
methanol, insoluble in methylene chloride, Freely soluble in DMF. 34
Molecular formula: C20H28N2O5
Pharmacokinetics:
 Oral route of administration, metabolized in the liver as it is a
Prodrug which is metabolically transformed into enalaprilat, mainly
eliminated through renal excretion, where approximately 94% of the
total dose is excreted via urine or feces as either enalaprilat or
unchanged parent compound.
Adverse Drug Reactions:
 Dizziness, head ache
 weakness
 skin rash
 cough, nausea, blurred vision
 disturbance in taste, hypotension, branchaspasm
35
Therapeutic Uses:
 Enalapril oral tablet is used to treat high blood pressure, heart
failure, and asymptomatic left ventricular dysfunction.
 Enalapril may be used as part of a combination therapy. That means
you need to take it with other drugs.
Dose:
 5-20 mg OD Orally.
36
Lisinopril
Structure:
IUPAC:6-amino-2-{[-1-carboxy-3-phenylpropyl] amino}
hexanoyl]pyrrolidine-2-carboxylic acid
Properties:
White crystalline powder, insoluble in acetone, ethanol, soluble in
water, sparingly soluble in methanol.
37
Molecular formula: C21H31N3O5
Pharmacokinetics:
 Oral route of administration, it is not metabolized and is excreted as
the unchanged drug, entirely eliminated exclusively in the urine.
Adverse Drug Reactions:
 Headache, dizziness, nausea, vomiting
 persistent cough
 low blood pressure, chest pain
 diarrhea, loss of appetite, stomach pain,
 Skin irritation
38
Therapeutic Uses:
 Lisinopril oral tablet is used to treat high blood pressure and heart
failure. It’s also used to improve your chance of survival after a heart
attack.
 This drug may be used as part of a combination therapy. That means
you may need to take it with other drugs.
Dose:
 5-40 mg OD Orally.
39
Benazepril hydrochloride
Structure:
IUPAC:3-{[-1-ethoxy-1-oxo-4-phenylbutan-2-yl]amino}-2-oxo-1H-
benzazepin-1-yl]acetic acid hydrochloride
Properties:
White crystalline powder, soluble in water, ethanol, methanol
40
. Hcl
Molecular formula: C24H29ClN2O5
Pharmacokinetics:
 Oral route of administration, metabolized in liver, i.e Cleavage of the
ester group (primarily in the liver) converts benazepril to its active
metabolite; benazeprilat. Benazepril and benazeprilat are conjugated
to glucuronic acid prior to urinary excretion.
Adverse Drug Reactions:
 dizziness, headache, drowsiness, anxiety, lightheadedness,
confusion, fever
 cough, nausea,
 vomiting, constipation,
 tired feeling,
 sleep problems (insomnia),
 flushing (warmth, redness, or tingly feeling),
 Itching or Skin rash.
41
Therapeutic Uses:
 Benazepril is used to treat high blood pressure (hypertension).
Lowering high blood pressure helps prevent strokes, heart attacks,
and kidney problems.
 Benazepril is an ACE inhibitor and works by relaxing blood vessels
so that blood can flow more easily.
Dose:
 20 to 40 mg/day orally as a single dose or in two equally divided
doses.
42
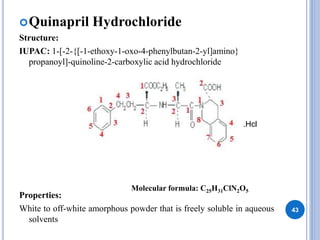
Quinapril Hydrochloride
Structure:
IUPAC: 1-[-2-{[-1-ethoxy-1-oxo-4-phenylbutan-2-yl]amino}
propanoyl]-quinoline-2-carboxylic acid hydrochloride
Properties:
White to off-white amorphous powder that is freely soluble in aqueous
solvents
43
.Hcl
Molecular formula: C25H31ClN2O5
Pharmacokinetics:
 Oral route of administration, metabolized in liver, i.e de-esterified to
the active quinaprilat or dehydrated to form the inactive PD109488.
PD109488 can undergo O-deethylation to form another inactive
metabolite, PD113413, eliminated through urine.
Adverse Drug Reactions:
 Headache, dizziness, fatigue
 coughing, chest pain, low blood pressure (hypotension)
 nausea or vomiting
 stomach pain, diarrhea
 gasping for air
 muscle pain
 skin rash, back pain
44
Therapeutic Uses:
 Quinapril is used to treat high blood pressure and heart failure.
Dose:
 Usual Adult Dose for Hypertension
Initial dose: 10 or 20 mg orally once a day in patients not on
diuretics
Maintenance dose: 20 to 80 mg orally per day, administered as a
single dose or in two equally divided doses
 Usual Adult Dose for Congestive Heart Failure
Initial dose: 5 mg orally twice a day
Maintenance dose: 20 to 40 mg orally per day administered in two
equally divided doses
45
CENTRALLY ACTING
SYMPATHOLYTIC DRUGS
46
 Drugs belonging to this class act by inhibiting the sympathetic
nervous system by central action.
 They stimulate α-adrenergic receptors of the vasomotor centre in
medulla there by reducing non adrenaline release and sympathetic
activity leading to fall blood pressure.
47
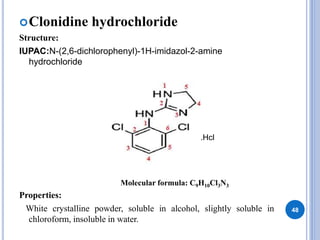
Clonidine hydrochloride
Structure:
IUPAC:N-(2,6-dichlorophenyl)-1H-imidazol-2-amine
hydrochloride
Properties:
White crystalline powder, soluble in alcohol, slightly soluble in
chloroform, insoluble in water.
48
.Hcl
Molecular formula: C9H10Cl3N3
Pharmacokinetics:
 Upon oral administration, Clonidine is rapidly absorbed with nearly
100% bioavailability. It is well distributed in the body and undergoes
partial metabolism in liver. The major route of excretion of both
changed and unchanged Clonidine is through urine and to some
extent through faeces.
Adverse Drug Reactions:
 Nausea, vomiting, constipation, dry mouth, anorexia.
 Itching or burning sensation in eyes.
 Heart failure, bradicardia.
 Drowsiness, anxiety, sleep disturbances, headache, dizziness,
hallucinations.
 Gynaecomastia (excess growth of male mammary glands, raynaud’s
syndrome transient hyperglycaemia.
 upper respiratory tract infection
49
Therapeutic Uses:
 Clonidine is used as an antihypertensive agent for controlling
hypertensive crisis.
 It is used in the prophylactic treatment of migraine, headache,
menopausal flushing.
 It is used to treat glucoma, insomnia, neuropathic pain.
 It is used in growth retardation, as it stimulates the release of growth
hormones from pituitary gland.
Dose:
 An initial dose of 0.1 mg OD gradually increased to 0.3 mg by oral
route.
50
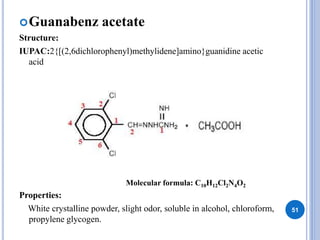
Guanabenz acetate
Structure:
IUPAC:2{[(2,6dichlorophenyl)methylidene]amino}guanidine acetic
acid
Properties:
White crystalline powder, slight odor, soluble in alcohol, chloroform,
propylene glycogen.
51
Molecular formula: C10H12Cl2N4O2
Pharmacokinetics:
 Oral route of administration, metabolized in liver, eliminated
through urine.
Adverse Drug Reactions:
 dry mouth, upset stomach,
 drowsiness, dizziness, headache, coma
 weakness
 decreased sexual ability
 fainting, swollen ankles or feet
 increased or decreased heartbeat, irregular heartbeat
 Respiratory problems, hypotension, frequent urination
 Blurred vision, muscle pain, dry eyes, back pain
52
Therapeutic Uses:
 Guanabenz is used to treat high blood pressure. It is in a class of
medications called centrally acting alpha2A-adrenergic receptor
agonists.
 Guanabenz works by decreasing your heart rate and relaxing the
blood vessels so that blood can flow more easily through the body.
Dose:
 4 to 8 mg orally twice a day, whether used alone or in combination
with a Thiazides diuretic.
 The maximum dose studied is 32 mg twice a day
53
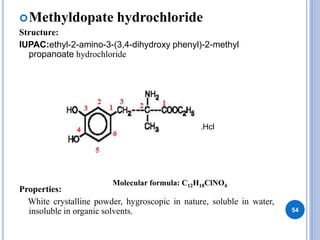
Methyldopate hydrochloride
Structure:
IUPAC:ethyl-2-amino-3-(3,4-dihydroxy phenyl)-2-methyl
propanoate hydrochloride
Properties:
White crystalline powder, hygroscopic in nature, soluble in water,
insoluble in organic solvents. 54
.Hcl
Molecular formula: C12H18ClNO4
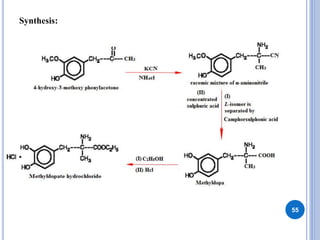
Synthesis:
55
Mechanism of Action:
 It is a Prodrug which converts to an active metabolite α-methyl
noradrenaline in the adrenergic neurons.
 The active metabolite of the drug acts centrally by stimulating α2-
adrenergic receptors in the vasomotor center of the medulla therapy
reducing the sympathetic activity and noradrenaline release leading
to decrease blood pressure.
56
Pharmacokinetics:
 Methyldopate is absorbed rapidly but incompletely after oral
administration. It is transported to the brain by amino acid
transporter where it converted to its active metabolite, α-methyl
noradrenaline. The plasma half life of the drug I 2 hours but the
antihypertensive effect lasts for about 24 hours. The drug is excreted
partly as metabolites (sulphate conjugate) and partly in an
unchanged form in urine.
Adverse Drug Reactions:
 dry mouth
 Drowsiness, headache, depression, night mares, parkinsonism
 weakness
 loss of energy, or fluid retention in legs, feet, arms, or hands
 Hepatotoxicity, constipation
 Sexual impotence, gynecomastia
 Sedation, forgetfulness
57
Therapeutic Uses:
 Methyldopate is used in the treatment of moderate hypertension in
combination with diuretics.
 Since it does not affect renal blood flow and GFR, it is used in
hypertension associated with renal impairment.
 It is especially useful in pregnant women due to its safety and
efficacy.
 However due to its severe adverse effects and availability of other
safer drugs, its use has now declined.
Dose:
 250 mg b.i.d initially gradually increased to 500 mg by oral route.
58
DIRECT VASODILATORS
59
 They act directly on arteries or veins to reduce the blood pressure
which are classified as
60
a. Arterial Vasodilators:
 Diazoxide, Minoxidil, Hydralazine are the potassium channel
openers used as antihypertensive drugs.
 They cause direct relaxation of arteries but not veins.
 However their usage as a single drugs is discouraged because the
relaxation of blood pressure by relaxation of vascular smooth
muscles is opposed by sympathetic activity i.e release of adrenaline,
a vasoconstriction.
61
Diazoxide
Structure:
IUPAC: 7-Chloro-3-methyl-benzothiadiazine 1,1-dioxide
Properties:
White or almost white and fine crystalline powder soluble in dilute
solutions of alkali hydroxides, in dimethylformamide, slightly
soluble in alcohol, but insoluble in water. 62
Molecular formula: C8H7ClN2O2S
Pharmacokinetics:
 It is well absorbed on oral and parental administration. The onset of
action is rapid and duration of action is about 5-20 hours. It is highly
bound to plasma proteins. It undergoes the hepatic metabolism and
renal excretion.
Adverse Drug Reactions:
 Tachycardia, hypotension
 Fluid retension, hyperglycemia, hyperuricaemia (abnormal increase
of uric acid in blood).
 Angina and myocardial infarction occurs in patients with ischemic
heart disease.
 nausea, vomiting, stomach pain, loss of appetite,
 diarrhea, constipation; or decreased sense of taste
63
Therapeutic Uses:
 It is used in hypertensive emergencies as an alternative to sodium
nitropruside.
 It is used to arrest premature labour.
 It is used for temporary treatment of hypoglycaemia secondary to
insulinoma (insulin producing tumours of the β-cells of pancreatic
islets).
Dose:
 150 mg by rapid i.v injection.
64
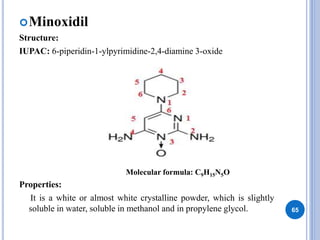
Minoxidil
Structure:
IUPAC: 6-piperidin-1-ylpyrimidine-2,4-diamine 3-oxide
Properties:
It is a white or almost white crystalline powder, which is slightly
soluble in water, soluble in methanol and in propylene glycol. 65
Molecular formula: C9H15N5O
Pharmacokinetics:
 Minoxidil is well absorbed from GIT on oral administration it is
converted to an active metabolite in the liver by glucoronide
conjugation excreted through urine.
Adverse Drug Reactions:
 Headache,
 Fluid retention, Palpitations
 Angina, pulmonary hypertension, cardiac temponade, tachycardia.
 Hypertrichosis (excess hair growth)
66
Therapeutic Uses:
 Minoxidil is used in the treatment of hypertension, unresponsive to
other drugs. It given in combination with β-blockers and diuretics.
 Minoxidil is used in the topical treatment of alopecia (baldness).
Dose:
 1.5 mg OD initially gradually increased to 40 mg by oral route.
67
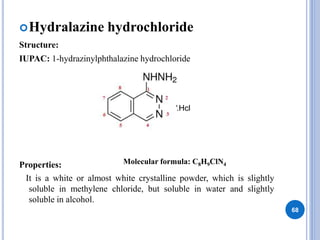
Hydralazine hydrochloride
Structure:
IUPAC: 1-hydrazinylphthalazine hydrochloride
Properties:
It is a white or almost white crystalline powder, which is slightly
soluble in methylene chloride, but soluble in water and slightly
soluble in alcohol.
68
.Hcl
Molecular formula: C8H9ClN4
Pharmacokinetics:
 Hydralazine Hcl is absorbed from GIT on oral administration. It is
metabolized in liver by acetylation. It is excreted as metabolites and
very small amount of the drug is excreted unchanged in urine.
Adverse Drug Reactions:
 Head ache, nausea, vomiting, dizziness, anorexia,
 Diarrhea, nasal congestion, fever
 Skin rashes, palpitation, polyneuritis
 Tachycardia, angina, myocardial ischemia.
 loss of appetite, weight loss, chest pain
69
Therapeutic Uses:
 Hydralazine Hcl is used in the treatment of hypertension, which is
not controlled by diuretics or β-blockers. It is preferred drug in
hypertensive emergencies in pregnant women. It always given in
combination with diuretics and β-blockers.
 Hydralazine Hcl is sometimes used in the management of CHF in
combination with nitrates.
Dose:
 25-50 mg OD by oral route.
70
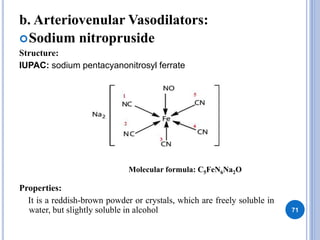
b. Arteriovenular Vasodilators:
Sodium nitropruside
Structure:
IUPAC: sodium pentacyanonitrosyl ferrate
Properties:
It is a reddish-brown powder or crystals, which are freely soluble in
water, but slightly soluble in alcohol 71
Molecular formula: C5FeN6Na2O
Pharmacokinetics:
 I.V route of administration, metabolized in liver i.e sodium
nitropruside is converted to cyanide (CN) and NO by RBC in
the blood vessels. The toxic CN is metabolized in liver (by
rhodanase) to less toxic thiocyanates which is excreted very
slowly in the urine.
Adverse Drug Reactions:
 Headache, nausea, vomiting, convulsions, psychosis, dizziness
 Hypotension, hypothyroidism and methaemoglobinaemia
 abdominal pain, apprehension, sweating, muscle twitching
 palpitations, restlessness,
 retching,
 chest discomfort,
 slow or fast heart rate,
 Rash, flushing or irritation at the infusion site. 72
Therapeutic Uses:
 It is used in the treatment of hypertensive emergencies. It is used
only for a brief period until the blood pressure is lowered.
 To produce controlled hypotension at the time of surgery.
 In acute myocardial infarction to enhance LV function.
Dose:
 500 mg powder dissolved in 500 ml of 5% dextrose in water and
administered at a rate of 0.25-1.5 μg/kg/min by i.v infusion.
73
ADRENERGIC NEURON BLOCKING
DRUGS
74
These drugs inhibit the functioning of sympathetic nervous system
by acting on the postganglionic adrenergic nerve endings.
75
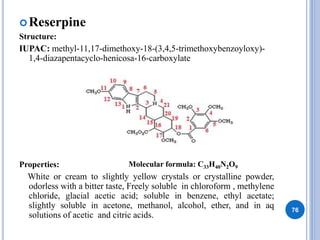
Reserpine
Structure:
IUPAC: methyl-11,17-dimethoxy-18-(3,4,5-trimethoxybenzoyloxy)-
1,4-diazapentacyclo-henicosa-16-carboxylate
Properties:
White or cream to slightly yellow crystals or crystalline powder,
odorless with a bitter taste, Freely soluble in chloroform , methylene
chloride, glacial acetic acid; soluble in benzene, ethyl acetate;
slightly soluble in acetone, methanol, alcohol, ether, and in aq
solutions of acetic and citric acids.
76
Molecular formula: C33H40N2O9
Pharmacokinetics:
 Reserpine is readily absorbed on oral and parenteral route of
administration. The drug entirely metabolized. The antihypertensive
effect persists even after the drug has been completely eliminated
from the body through urine.
Adverse Drug Reactions:
 Diarrhea, gastrointestinal cramps, increased gastric acid secretion,
excessive salivation
 Nasal congestion, sedation, nightmares, mental depression,
gynaecomastia, impotence in males and reduction in fertility in
females and Parkinsonism, thrombocytopenia.
77
Therapeutic Uses:
 Reserpine is used in the treatment of moderate hypertension. It is
used in combination with diuretics. But due to its effects on CNs, its
use has declined.
Dose:
 0.25 mg OD, by oral route.
78
Guanethidine monosulphate
Structure:
IUPAC: 3-[2-(azocan-1-yl)ethyl]guanidine sulphate
Properties:
White crystalline powder, strong characteristic odor, soluble in
water, slightly soluble in alcohol, insoluble in chloroform, ether.
79
Molecular formula: C10H24N4O4S
Pharmacokinetics:
 Oral route of administration. Guanethidine is converted by the liver
to three metabolites, which are excreted in the urine. The metabolites
are pharmacologically less active than the parent compound, which
are excreted in the urine.
Adverse Drug Reactions:
 Drowsiness, dizziness, anxiety, depression
 Diarrhea, nausea, vomiting, dry mouth, blurred vision, weight gain,
slow heart
 nightmares
80
Therapeutic Uses:
 It is indicated for the treatment of moderate and severe hypertension,
either alone or as an adjunct, and for the treatment of
renal hypertension, including that secondary to pyelonephritis, renal
amyloidosis, and renal artery stenosis.
Dose:
 At first, 10 or 12.5 milligrams (mg) once a day. Then, your doctor

may increase your dose to 25 to 50 mg once a day.
81
ΒETA -ADRENERGIC RECEPTOR
ANTAGONISTS OR Β-BLOCKERS
82
 These drugs used for the treatment of hypertension, ischemic heart
disease, arrhythmias.
 All the β-blockers are synthetic agents (Compounds) completely
inhibit the action of adrenergic agonists on β-receptors.
 Blockage of β-receptors reduces the heart rate; cardiac output
consequently blood pressure is reduced.
83
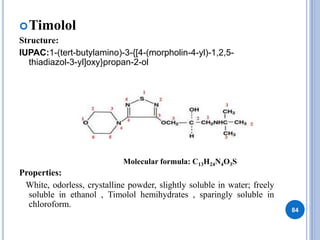
Timolol
Structure:
IUPAC:1-(tert-butylamino)-3-{[4-(morpholin-4-yl)-1,2,5-
thiadiazol-3-yl]oxy}propan-2-ol
Properties:
White, odorless, crystalline powder, slightly soluble in water; freely
soluble in ethanol , Timolol hemihydrates , sparingly soluble in
chloroform.
84
Molecular formula: C13H24N4O3S
Pharmacokinetics:
 Oral, ophthalmic rote of administration metabolized in the liver by
the cytochrome P450 2D6 enzyme, with minor contributions from
CYP2C19. 15-20% of a dose undergoes first-pass
metabolism. Despite its relatively low first pass metabolism, timolol
is 90% metabolized. Four metabolites of timolol have been
identified, with a hydroxy metabolite being the most predominant.
Timolol and its metabolites are mainly found excreted in the urine.
Adverse Drug Reactions:
 Blurred vision, double vision, burning of eyes, eye redness, watery
eye,
 Head ache, drowsiness, nausea, insomnia (sleep problems)
 Weakness, ringing in ears, dry mouth,
 Diarrhea, loss of appetite, stomach upset
 Skin rashes, cough
85
Therapeutic Uses:
Used in the treatment of
 Hypertension
 Glaucoma
 Arrhythmias
Dose:
For the treatment of hypertension.
 Initially, 10 mg PO twice daily, alone or with a diuretic. The usual
dose is 10 to 20 mg PO twice daily. Maximum dose is 60 mg/day,
divided in 2 doses.
For the treatment of Glaucoma
 Instill 1 drop of a 0.25% solution in affected eye(s) twice daily.
For the treatment of migraine prophylaxis.
 Initially, 10 mg PO twice daily. May give maintenance dose of 20
mg PO once daily. Dosage range: 10 to 30 mg/day PO. 86
Reference books
 Text book of Medicinal chemistry volume-1-3rd edition by
V.Alagarasamy.
 Text book of Medicinal chemistry volume-2-3rd edition by
V.Alagarasamy.
 Medicinal chemistry by Rama Rao Nadendla.
 Medicinal Chemistry- 4th edition by Ashutosh Kar
87
THANK YOU
88