Pit and
Fissure
Sealants
Presenter :
Dr. AASHNA
DHINGRA
P.G. Student
First Year
Dept. of Public
Health Dentistry
I N T R O D U C T I O N
Although only 12.5% of all tooth surfaces are
occlusal,
these surfaces develop more than two-thirds
of the total caries experience of children.
Caries potential is directly related to the
shape and depth of the pits and fissures.
Narrow isolated crevices and grooves are the
most important anatomical features leading to
development of occlusal caries.
CONTENTS ….
Introduction
definitions
types of fissures
indications
contraindications
purpose
rationale
criteria for ideal sealants
classification
materials used as sealants
procedure
prr
public health programs
HISTORY1835 – Robertson – caries depth of Pits and fissures
1895 - Wilson - zinc phosphate
1905 - silver nitrate by Miller
1923- HYATT : “PROPHYLACTIC ODONTOTOMY” (Ag and Cu Oxyphosphate cements)
1929 - Bodecker - Enameloplasty (enamel fissure eradication)
1939- Gore – use of ploymers- sol. of cellulose
1942 - Kline and Knutson- ammonical silver nitrate
1951 – Miller J – copper amalgam
1955- Buonocore – Acid Etching (concentrated phosphoric acid solution)
Cyanoacrylates were the first materials to be used as sealants, but never marketed.
1972 – NUVA SEAL(L.D Caulk) –UV P&F sealant – BOWEN
1976- first colored sealant- CONCISE WHITE SEALANT – chemical cure (3M dental products.
Pits and fissures are enamel faults,
narrow shafts or cracks at some
length whose blind ends are
directed more or less towards the
DEJ.
PIT :
defined as a small pin point depression located
at the junction of developmental grooves and at
terminals of those grooves.
FISSURE :
defined as deep clefts between adjoining
cusps.
“to describe a material that is introduced into
the occlusal pit and fissure of caries susceptible
teeth, thus forming a micro-mechanically
bonded, protective layer cutting access of
caries producing bacteria from their source of
nutrients”
•(Simonsen)
“Fissure sealants are materials designed to
prevent pit and fissure caries when they are
applied to the occlusal surfaces of teeth in
order to obliterate occlusal fissures and remove
the sheltered environment in which caries may
thrive.”
•(Gordon-1962)
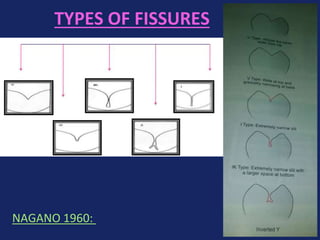
TYPES OF FISSURES
NAGANO 1960:
INDICATIONS :
Ekstrand and Christiansen, 2005
active fissure caries has been
diagnosed.
a high risk had been established.
fissures are deep and the patient or
parent either cannot, or will not remove
plaque effectively.
INDICATIONS :
• presence of deep occlusal pits and fissure on newly
erupted teeth.
• presence of lingual pits or palatal pits in relation to
upper lateral incisors and molars.
• presence of incipient lesion in pit and fissure.
• children and young people with medical, physical, or
intellectual impairment with high caries risk.
• children and young adults with signs of high caries
activity coming from non-fluoridated areas.
CONTRA-INDICATIONS :
• shallow pits and fissures.
• open occlusal carious lesions with extension into
dentin.
• presence of large occlusal restoration.
• presence of proximal caries extending on to occlusal
surface.
• partially erupted tooth where isolation is problem.
• un-cooperative children.
PURPOSE :
• To provide physical barrier to seal off the pit or
fissure.
• To prevent the bacteria and their nutrients from
collecting within the pits or fissures to create the
acid environment necessary for initiation of
dental caries.
RATIONALE :
Very high proportion of dental decay occurs in pits and
fissures.
Recent data shows that relative proportion of pit and fissure
lesions has increased to 84% of total new caries experience.
Pits and fissures remain at risk of caries for long periods of
time, not just within the first few years of eruption.
Fluoride has limited effect in preventing pit and fissure
caries.
Fissure sealants are effective at preventing pit and fissure
caries and are best used as a part of overall preventive
program.
(British society of pediatric dentistry 2000)
1. A viscosity allowing penetration into deep and narrow
fissures.
2. Adequate working time.
3. Rapid cure
4. Good and prolonged adhesion/bonding to enamel.
5. Low sorption and solubility.
6. Resistance to wear.
7. Be compatible with oral tissues.
8. Cariostatic action
CRITERIA FOR THE IDEAL
SEALANT
-Brauer
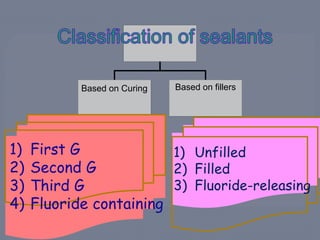
Based on Curing Based on fillers
1) First G
2) Second G
3) Third G
4) Fluoride containing
1) Unfilled
2) Filled
3) Fluoride-releasing
FIRST GENERATION
Polymerised with UV Light
350nm
SECOND GENERATION
FOURTH GENERATION
THIRD GENERATION
Self cured or Chemically cured
Mostly unfilled.
Visible light cured
430-490nm
Filled/unfilled
Addition of fluoride for added benefit
B. Filled
- Need for occlusal adjustments
- More resistant to wear
- may need occlusal adjustments
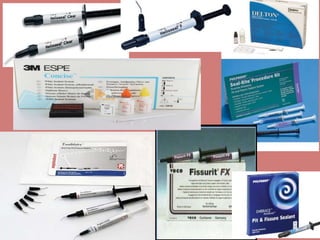
e.g.. Prisma shield, Helioseal,
Delton plus.
A. Unfilled [ free of fillers
]
-Flow is better
- more retention
- abrade easily
- e.g. . Concise White, Delton
MATERIALS
USED AS
SEALANTS
CYANOACRYLATES
Discovered in late 1950’s.
Surgical adhesives and tooth sealants.
moisture - polymerize rapidly : hard and
brittle.
Mechanical durability : unsatisfactory
Initially methyl cyanoacrylate used. : toxic
potential.
Replaced by Butyl and Isobutyl ester.
POLY URETHANES
Eg: EPOXYLITES
Contain 10% sodium mono
fluorophosphate with liquid polyurethane
and utilize citric acid as etchant.
Not regularly used due to poor
mechanical properties and oral durability
and toxicity.
DIMETHACRYLATES
Methyl Methacrylate (MMA) : highly
volatile and lacks penetration.
Enamite, a new sealant utilizes MMA-
PMMA system initiated by butyl boron.
Binds better and is less affected by
immersion in water.
BISGMA : viscous amber liquid of low
volatility diluted with MMA. (3:1)
GLASS IONOMER
Mc Lean and Wilson
Hydrophilic
Good adhesion
Biocompatibility
Fluoride release
Used for fissure orifice exceeding
100µm
3-4yrs : Primary molar sealant application.
6-7yrs : First permanent molar .
11-13yrs : Second permanent molars and the
premolar.
Simonsen 1983.
Group 1 – Caries free patients judged at no risk to
decay.
Group 2 – Patients judged to be at moderate risk
to decay.
Group 3 – Patients with rampant caries at a high
risk to decay.
WHO…??
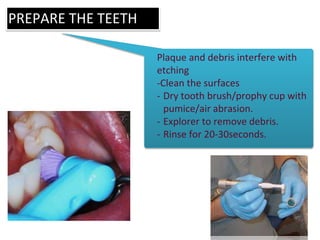
PREPARE THE TEETH
Plaque and debris interfere with
etching
-Clean the surfaces
- Dry tooth brush/prophy cup with
pumice/air abrasion.
- Explorer to remove debris.
- Rinse for 20-30seconds.
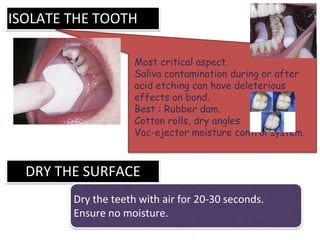
ISOLATE THE TOOTH
Most critical aspect.
Saliva contamination during or after
acid etching can have deleterious
effects on bond.
Best : Rubber dam.
Cotton rolls, dry angles
Vac-ejector moisture control system.
DRY THE SURFACE
Dry the teeth with air for 20-30 seconds.
Ensure no moisture.
ETCH THE SURFACES
37% Ortho-Phosphoric acid
Liquid/gel form.
30-60seconds
On all susceptible pits and fissures
Extend up the cuspal lines, well
beyond (at least 2mm) the
anticipated margin of sealant.
RINSE AND DRY THE
TEETH
Rinse surfaces for 60 seconds.
Surface should appear “Chalky-
White”
Dry teeth with air for 20-30
seconds.
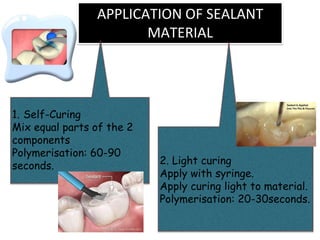
APPLICATION OF SEALANT
MATERIAL
1. Self-Curing
Mix equal parts of the 2
components
Polymerisation: 60-90
seconds. 2. Light curing
Apply with syringe.
Apply curing light to material.
Polymerisation: 20-30seconds.
EVALUATION
THE SEALANT
- for complete
coverage
- for absence of
voids or bubbles
- small voids can be
repaired.
OCCLUSAL
EVALUATION
- Articulating
paper.
- Adjustments :
filled resins.
Re- EVALUATION
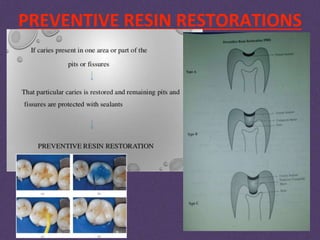
PREVENTIVE RESIN RESTORATIONS
• a natural extension of the use of occlusal sealants.
• integrates the preventive approach of sealant
therapy for caries susceptible pit and fissure with
therapeutic restoration of incipient caries with
composite resin.
• “extension for prevention”
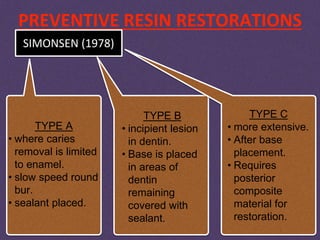
PREVENTIVE RESIN RESTORATIONS
SIMONSEN (1978)
TYPE A
• where caries
removal is limited
to enamel.
• slow speed round
bur.
• sealant placed.
TYPE B
• incipient lesion
in dentin.
• Base is placed
in areas of
dentin
remaining
covered with
sealant.
TYPE C
• more extensive.
• After base
placement.
• Requires
posterior
composite
material for
restoration.
PUBLIC HEALTH SEALANT PROGRAMS
School - based
American Association of Community Dental
Programs has developed a manual “Seal
America : The Prevention Invention”
1990: US Public Health Service published a
national health objective for the year 2000,
stating that 50% children should have
sealants on 1 or more permanent teeth.
Define the community
 School system
 Municipality
 Neighborhood
 State
 Homebound
 Institutions
Assess community need
 High pit and fissure caries level and low
proximal caries level.
 Low sealant prevalence
 Poor access to dental care
 Low income
Weigh support constraints for sealant program
development
 human resources
 fiscal resources
 Community values
on oral health
SUPPORTS CONSTRAINTS
Adequate Lack
Select approaches for increasing sealant prevalence
 Direct service
 Sealant promotion
 Policy development (Medicaid rules, state
practice acts)
Define specific population
 school children
 specific populations :
 head start
 residential care
 military
 managed care organization
 people with disabilities
 geography
Identify individuals to be evaluated for sealants
 All people
 Low SES
 Lack of dental care
Identify teeth/tooth surfaces
 Risk assessment of individual
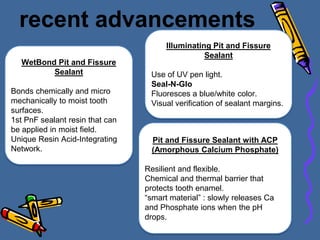
recent advancements
WetBond Pit and Fissure
Sealant
Bonds chemically and micro
mechanically to moist tooth
surfaces.
1st PnF sealant resin that can
be applied in moist field.
Unique Resin Acid-Integrating
Network.
Pit and Fissure Sealant with ACP
(Amorphous Calcium Phosphate)
Resilient and flexible.
Chemical and thermal barrier that
protects tooth enamel.
“smart material” : slowly releases Ca
and Phosphate ions when the pH
drops.
Illuminating Pit and Fissure
Sealant
Use of UV pen light.
Seal-N-Glo
Fluoresces a blue/white color.
Visual verification of sealant margins.
• Compared sealed and
unsealed teeth in the same mouth.
• Teeth which were
initially sound had caries rate 13% at 5 years when unsealed and 8
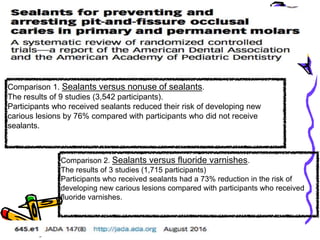
Comparison 1. Sealants versus nonuse of sealants.
The results of 9 studies (3,542 participants).
Participants who received sealants reduced their risk of developing new
carious lesions by 76% compared with participants who did not receive
sealants.
Comparison 2. Sealants versus fluoride varnishes.
The results of 3 studies (1,715 participants)
Participants who received sealants had a 73% reduction in the risk of
developing new carious lesions compared with participants who received
fluoride varnishes.
CONCLUSION …
REFERENCES…
Pit and fissure sealants