




























Dept. of Public Health Dentistry
PCDS & RC
LEARNING OBJECTIVES
• Definitions
• Classification of foods and nutrients
• Balanced diet
• Know about various nutrients and their RDA
• Other Aspects of nutrition.
Nutrition :
The Science Of Food And Nutrients, Their Action And
Interaction For Health And Disease, And The Ways By
Which The Organs Ingest, Digest And Excrete.
DEFINITION…
Diet :
The Sun Total Of Food Taken By An Individual.
Nutrients :
The Substances That Enable Cells And Tissues To Carry
Out Vital Functions.
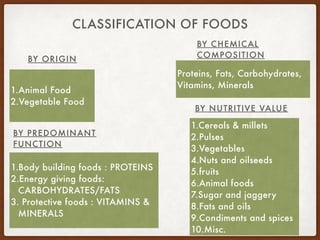
BY ORIGIN
CLASSIFICATION OF FOODS
BY CHEMICAL
COMPOSITION
BY PREDOMINANT
FUNCTION
BY NUTRITIVE VALUE
1.Animal Food
2.Vegetable Food
Proteins, Fats, Carbohydrates,
Vitamins, Minerals
1.Body building foods : PROTEINS
2.Energy giving foods:
CARBOHYDRATES/FATS
3. Protective foods : VITAMINS &
MINERALS
1.Cereals & millets
2.Pulses
3.Vegetables
4.Nuts and oilseeds
5.fruits
6.Animal foods
7.Sugar and jaggery
8.Fats and oils
9.Condiments and spices
10.Misc.
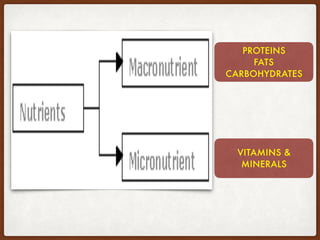
PROTEINS
FATS
CARBOHYDRATES
VITAMINS &
MINERALS
ONE WHICH CONTAINS DIFFERENT T YPES OF FOODS IN SUCH
QUANTITIES AND PROPORTIONS THAT THE ENERGY, AMINO ACIDS,
VITAMINS, MINERALS IS ADEQUATELY MET FOR MAINTAINING
HEALTH, VITALIT Y AND GENERAL WELL BEING.
IT ALSO MAKES PROVISION FOR EXTRA NUTRIENTS REQUIRED
DURING DIFFICULT PERIODS.
BALANCED DIET
THERE IS NO SINGLE FOOD THAT CONTAINS ALL THE NUTRIENTS.
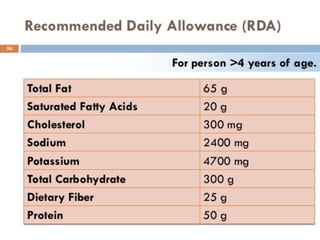
The Recommended Dietary Allowances (RDA) is a guideline for
the nutrient intake setup by the Food and Nutrition Board.
- RDA is the recommendation for the average daily amounts of
nutrients which should be consumed over a period of time.
“The FOOD GUIDE PYRAMID” : a nutritional education guide
emphasizes foods from the five major food groups shown in lower 3
sections of pyramid.
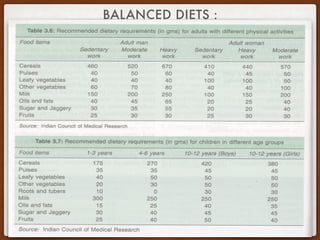
BALANCED DIETS :
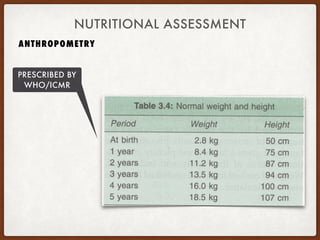
REFERENCE BODY WEIGHTS
NUTRITIONAL ASSESSMENT
ANTHROPOMETRY
PRESCRIBED BY
WHO/ICMR
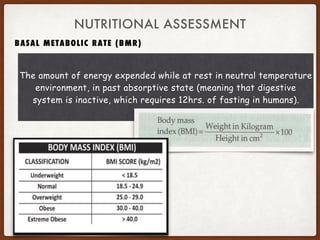
BASAL METABOLIC RATE (BMR)
NUTRITIONAL ASSESSMENT
The amount of energy expended while at rest in neutral temperature
environment, in past absorptive state (meaning that digestive
system is inactive, which requires 12hrs. of fasting in humans).
PROTEINS
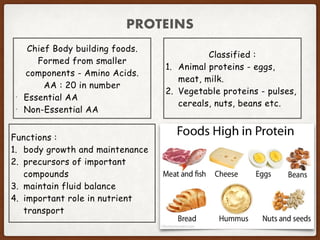
Chief Body building foods.
Formed from smaller
components - Amino Acids.
AA : 20 in number
• Essential AA
• Non-Essential AA
Classified :
1. Animal proteins - eggs,
meat, milk.
2. Vegetable proteins - pulses,
cereals, nuts, beans etc.
Functions :
1. body growth and maintenance
2. precursors of important
compounds
3. maintain fluid balance
4. important role in nutrient
transport
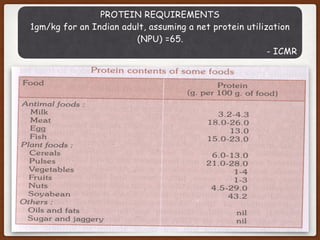
PROTEIN REQUIREMENTS
1gm/kg for an Indian adult, assuming a net protein utilization
(NPU) =65.
- ICMR
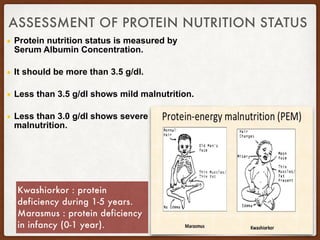
ASSESSMENT OF PROTEIN NUTRITION STATUS
▪ Protein nutrition status is measured by
Serum Albumin Concentration.
▪ It should be more than 3.5 g/dl.
▪ Less than 3.5 g/dl shows mild malnutrition.
▪ Less than 3.0 g/dl shows severe
malnutrition.
Kwashiorkor : protein
deficiency during 1-5 years.
Marasmus : protein deficiency
in infancy (0-1 year).
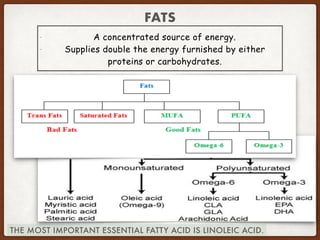
FATS
- A concentrated source of energy.
- Supplies double the energy furnished by either
proteins or carbohydrates.
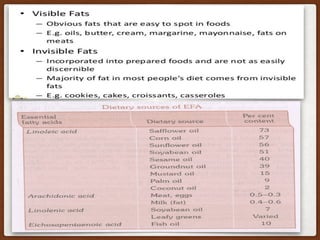
THE MOST IMPORTANT ESSENTIAL FATTY ACID IS LINOLEIC ACID.
A total of 40-60gm of fat can be consumed daily, so that it
contributes to 15-20% of the calories in diet.
RDA for reference man and woman : 20gm/day.
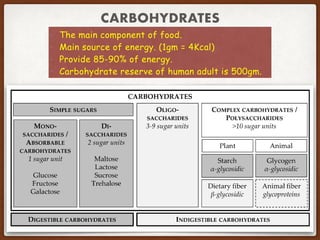
CARBOHYDRATES
- The main component of food.
- Main source of energy. (1gm = 4Kcal)
- Provide 85-90% of energy.
- Carbohydrate reserve of human adult is 500gm.
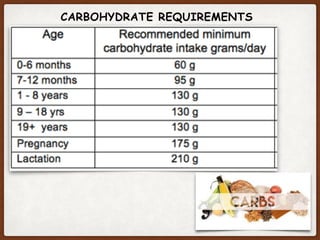
CARBOHYDRATE REQUIREMENTS
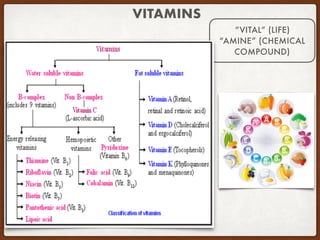
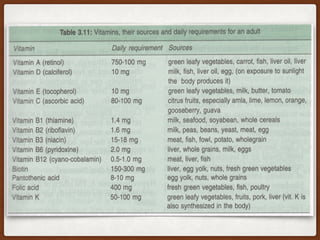
VITAMINS
“VITAL” (LIFE)
“AMINE” (CHEMICAL
COMPOUND)
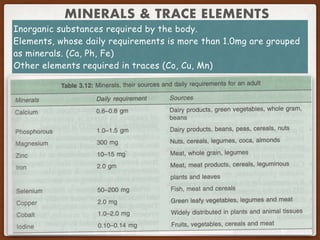
MINERALS & TRACE ELEMENTS
Inorganic substances required by the body.
Elements, whose daily requirements is more than 1.0mg are grouped
as minerals. (Ca, Ph, Fe)
Other elements required in traces (Co, Cu, Mn)
WATER
• Important constituent of diet- comprising both intra and
extracellular component of the body.
• Constitutes 2/3rd of human body.
• A normal man of approx. 65kg contains 40 liters of water.
The total fluid intake
requirement is:
1200ml for 1 year olds.
1500ml for 5 year olds.
>3000ml per day for adults.
Water depletion: dehydration,
mental confusion, vertigo, skin
becomes doughy, RBF reduced.
OTHER ASPECTS OF NUTRITION
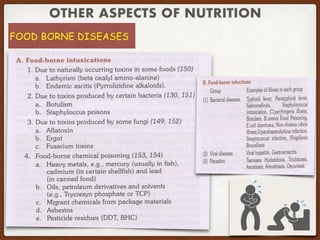
FOOD BORNE DISEASES
FOOD FORTIFICATION
The process whereby nutrients are added to foods to improve
the quality of food.
Eg : Common salt (NaCl) is fortified with Iodine.
Vanaspati ghee is deficient in Vit. A &D (as compared to animal
fat.), so it is fortified with Vit. A & D.
FOOD ADULTERATION
The process of mixing, substituting, concealing, putting up of
decomposed foods for sale, misbranding or giving false labels.
Eg:
Mixing water with milk.
Non-permitted colors used by sweet makers
Green dye used in green peas packing.
Dept. of Public Health Dentistry
PCDS & RC
Part II
LEARNING OBJECTIVES
• Carbohydrates and related diseases
• Fats and related diseases
• Proteins and related diseases
• Vitamins and related diseases
• Trace elements and related diseases
CARBOHYDRATES
SYSTEMIC DISEASES

• Obesity

• Diabetes

• Cardiovascular diseases

• Glycogen storage disease

• Fructosuria, Galactosemia

• Pentosuria
ORAL DISEASES

• Increased incidence of
caries and periodontal
diseases

• Refined carbohydrates :
decalcification of
enamel and dentin.
If ingested in excess, will be deposited in adipose tissue.

ATHEROSCLEROSIS : cholesterol in arterial walls - CHD
(LDL, VLDL: harmful, HDL: protective.)

OBESITY leading to DM, Arterial HTN, etc.

PHRENODERMA : rough n dry skin- “toad skin”. (Kerala,
Karnataka, Gujarat)

CANCER : increased risk of colon and breast cancer.

Fat free diet produces essential fatty acid deficiency.
FATS
WHO/FAO expert group: total fat 15-30% energy is
consistent with good health.
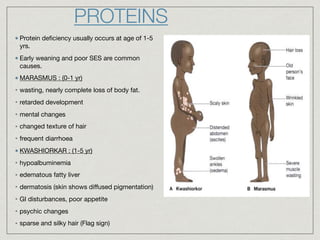
Protein deficiency usually occurs at age of 1-5
yrs.

Early weaning and poor SES are common
causes.

MARASMUS : (0-1 yr)

• wasting, nearly complete loss of body fat.

• retarded development

• mental changes

• changed texture of hair

• frequent diarrhoea

KWASHIORKAR : (1-5 yr)

• hypoalbuminemia

• edematous fatty liver

• dermatosis (skin shows diffused pigmentation)

• GI disturbances, poor appetite

• psychic changes

• sparse and silky hair (Flag sign)
PROTEINS
Protein deficiency in adults usually seen in
hospitalized patients :

Chronic alcoholics and other drugs addicts as they
have irregular food habits.

Patients suffering from GI disorders as they may not be
able to eat, digest and absorb protein.

Surgical patients with sever injuries, burns have
increased nitrogen loss and are unable to feed normally.

Chronic renal disease: patients lose large amount of
protein through urine.

Hepatic disease: patients are unable to synthesize
proteins from amino acids.
SYSTEMIC DISEASES :
Eyes- Xerosis (dryness), Keratomalacia (softness of cornea), Corneal Opacities,
Night blindness.
Skin- dry and rough with hyperkeratinization, atrophy of sweat glands.
Respiratory Tract- keratinization of bronchopulmonary epithelium - increased
susceptibility to infection.
GIT - unhealthy GI mucosa - recurrent diarrhea
Urinary Tract- increased tendency to urinary stone formation.
Reproductive system- sterility due to faulty spermatogenesis.
Growth Retardation
Immune deficiency
VITAMINS
VITAMIN A (Beta Carotene)
HYPOVITAMINOSIS A
HYPERVITAMINOSIS A
ACUTE: headache, drowsiness, irritability, rise in intracranial tension,
vomiting, liver enlargement, shedding of skin.
CHRONIC: weight loss, nausea, vomiting, dryness of mucosa of lips, bone
and joint pain, hepatomegaly.
ORAL DISEASES
Oral Mucosa : hyperkeratotic or follicular keratotic changes
in oral epithelium.
Gingival Epithelium : hyperplastic and hyperkeratotic.
Enamel Organ : atrophy, degeneration of odontoblasts - poor
calcification- enamel hypoplasia.
Atrophy of salivary glands- reduced salivary flow.
Cementum : irregular cemental resorption, ankylosis of
teeth.
Eruption Rate : retarded
Alveolar bone: atrophy in severe cases
HYPOVITAMINOSIS A
HYPERVITAMINOSIS A
ORAL DISEASES
Mesenchymal tissues are highly sensitive. Rate of resorption
of alveolar bone is reduced, as a result the bone becomes
abnormally thin.
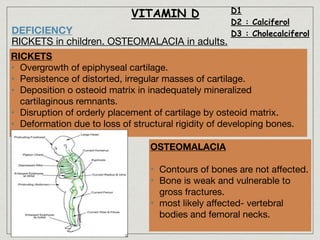
VITAMIN D D1
D2 : Calciferol
D3 : CholecalciferolDEFICIENCY
RICKETS in children. OSTEOMALACIA in adults.
RICKETS
• Overgrowth of epiphyseal cartilage.

• Persistence of distorted, irregular masses of cartilage.

• Deposition o osteoid matrix in inadequately mineralized
cartilaginous remnants.

• Disruption of orderly placement of cartilage by osteoid matrix.

• Deformation due to loss of structural rigidity of developing bones.
OSTEOMALACIA
• Contours of bones are not affected.

• Bone is weak and vulnerable to
gross fractures.

• most likely affected- vertebral
bodies and femoral necks.
Oral Manifestations :
Eruption of teeth is retarded.

Enamel hypoplasia.

Osteoporosis of alveolar bone

• Reduction in width of PDL space.

• Defective calcification of cementum

• Distortion of growth pattern of alveolar bone.
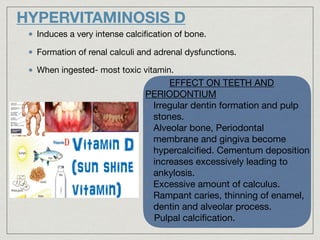
HYPERVITAMINOSIS D
Induces a very intense calcification of bone.

Formation of renal calculi and adrenal dysfunctions.

When ingested- most toxic vitamin.
EFFECT ON TEETH AND
PERIODONTIUM

• Irregular dentin formation and pulp
stones.

• Alveolar bone, Periodontal
membrane and gingiva become
hypercalcified. Cementum deposition
increases excessively leading to
ankylosis.

• Excessive amount of calculus.

• Rampant caries, thinning of enamel,
dentin and alveolar process.

•Pulpal calcification.
DEFICIENCY
Nervous System : Anatomic changes in nervous system.
Clinical manifestations depend upon severity and extent of
lesions. Most consistent- Depressed tendon reflexes,
Ataxia, Dysarthria, Loss of pain sensation.

Blood : Hemolytic and hypoplastic anemia.

Mesenchymal Tissues : Degenerative lesions in skeletal
muscles and heart.
VITAMIN E (Alpha Tocopherol)
HYPERVITAMINOSIS E
Least toxic vitamin.

Hypervitaminosis has yet not been
described.
DEFICIENCY
Development of a bleeding diathesis characterized
by hematomas, hematuria, malena and ecchymoses.

In neonates, most serious manifestation is
intracranial hemorrhage. Bleeding may occur at any
site, including skin, umbilicus, viscera.
VITAMIN K K1 (Phytodione)
K2 (Menadione)
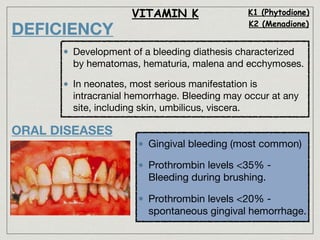
ORAL DISEASES
Gingival bleeding (most common)

Prothrombin levels <35% -
Bleeding during brushing.

Prothrombin levels <20% -
spontaneous gingival hemorrhage.
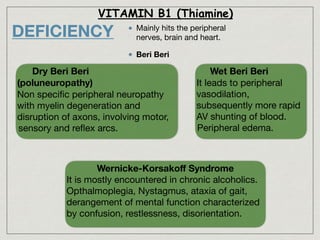
Mainly hits the peripheral
nerves, brain and heart.

Beri Beri
VITAMIN B1 (Thiamine)
DEFICIENCY
Dry Beri Beri
(poluneuropathy)
Non specific peripheral neuropathy
with myelin degeneration and
disruption of axons, involving motor,
sensory and reflex arcs.
Wet Beri Beri

It leads to peripheral
vasodilation,
subsequently more rapid
AV shunting of blood.
Peripheral edema. 

Wernicke-Korsakoff Syndrome

It is mostly encountered in chronic alcoholics.

Opthalmoplegia, Nystagmus, ataxia of gait,
derangement of mental function characterized
by confusion, restlessness, disorientation.
No specific lesions.

Hypersensitivity of oral mucosa seen.

Oral and facial neuralgias and pain, herpes simplex,
aphthous stomatitis can be treated by thiamine.

Edematous swelling of gingiva and lingual papillae
and taste impairment may be seen.
Oral Diseases
HYPERVITAMINOSIS
Thiamine is non toxic when taken by mouth.

Parenteral administration causes anaphylactic
shock in H/S individuals.

Contact dermatitis in patients allergic to thiamine.
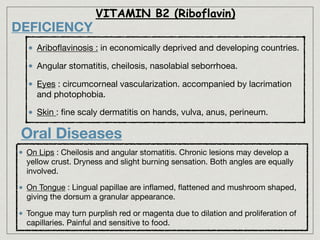
DEFICIENCY
Ariboflavinosis : in economically deprived and developing countries.

Angular stomatitis, cheilosis, nasolabial seborrhoea.

Eyes : circumcorneal vascularization. accompanied by lacrimation
and photophobia.

Skin : fine scaly dermatitis on hands, vulva, anus, perineum.
VITAMIN B2 (Riboflavin)
On Lips : Cheilosis and angular stomatitis. Chronic lesions may develop a
yellow crust. Dryness and slight burning sensation. Both angles are equally
involved.

On Tongue : Lingual papillae are inflamed, flattened and mushroom shaped,
giving the dorsum a granular appearance.

Tongue may turn purplish red or magenta due to dilation and proliferation of
capillaries. Painful and sensitive to food.
Oral Diseases
DEFICIENCY
Dermatitis : usually bilaterally symmetrical, found on exposed areas of
body.

Diarrhoea : Caused by atrophy of columnar epithelium of GI tract.

Dementia : Due to degeneration of brain accompanied by degeneration of
corresponding tracts of spinal cord.
VITAMIN B3 (Niacin/Nicotinic Acid)
Now fourth D : Death also added as disease is fatal if not treated.
PELLAGRA 

(three D’s)
HYPERVITAMINOSIS
Due to its action as a vasodilator.

Reddening and flushing of skin, increased skin temperature,
dizziness, headache, nausea, vomiting, abdominal pain.
Oral Diseases
• 

• Oral Mucosa : entire oral mucosa becomes red and painful.

• Tongue : desquamation of epithelium, leaving a scarlet, smooth,
dry, beefy tongue. Swelling of tongue with indentations on the
margins. Extremely painful and sensitive to food and drinks.

• Gingiva : Tenderness, pain, redness, ulcerations begin at
interdental papillae and spread rapidly. Salivation becomes
excessive, diminished taste sensation. Superimposed ANUG is
common.

• Dental Caries : Incidence of caries is reduced in niacin deficiency.
May be because Nicotinic acid is an essential growth factor for
oral microflora.
VITAMIN B4 (Adenine)
Synthesized by human body.

Does not have much nutritional value.
VITAMIN B5 (Pantothenic Acid)
Deficiency is rare;

Burning feet syndrome
No oral manifestations.

Curative value in treatment of Glossitis
and Cheilitis
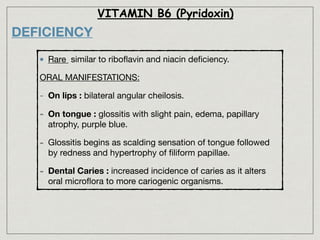
VITAMIN B6 (Pyridoxin)
DEFICIENCY
Rare similar to riboflavin and niacin deficiency.

ORAL MANIFESTATIONS:

- On lips : bilateral angular cheilosis.

- On tongue : glossitis with slight pain, edema, papillary
atrophy, purple blue. 

- Glossitis begins as scalding sensation of tongue followed
by redness and hypertrophy of filiform papillae.

- Dental Caries : increased incidence of caries as it alters
oral microflora to more cariogenic organisms.
VITAMIN B9 (Folic Acid)/Vitamin M
DEFICIENCY
SYSTEMIC MANIFESTATIONS:

Macrocytic Anemia associated with megaloblastic erythropoiesis.

Glossitis, stomatitis, diarrhoea.

Steatorrhoea- foul smelling, copious, greasy appearing, light, liquid-
semiliquid stools.
ORAL MANIFESTATIONS:

- Tongue : glossitis, seen as swelling and redness along tip and margins. 

- Minute, whitish aphthous ulcers with fiery red borders may emerge.

- Filiform papillae are first to disappear, the fungiform papillae remaining
as prominent spots.

- Lips : stomatitis, cheilitis, cheilosis with ulcerative lesions.
VITAMIN B12 (Cyanocobalamin)
DEFICIENCY
SYSTEMIC MANIFESTATONS
- Pernicious Anemia
Weakness, glossitis, numbness and tingling of extremities. It may
lead to severe psychosis.

- Macrocytic anemia and homocysteinuria

ORAL MANIFESTATONS-
- On tongue : recurrent attacks of sore tongue. Tongue becomes
fiery red and painful.

- On Lips : Chelosis, chelitis, painful mucous membranes affecting
buccal mucosa, pharynx, and gingiva.
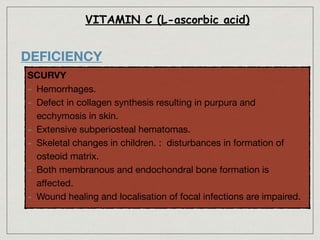
VITAMIN C (L-ascorbic acid)
DEFICIENCY
SCURVY

- Hemorrhages.

- Defect in collagen synthesis resulting in purpura and
ecchymosis in skin.

- Extensive subperiosteal hematomas.

- Skeletal changes in children. : disturbances in formation of
osteoid matrix.

- Both membranous and endochondral bone formation is
affected.

- Wound healing and localisation of focal infections are impaired.
ORAL MANIFESTATION
GINGIVAL and PERIODONTAL TISSUES : interdental
and marginal gingiva is bright red with swollen, smooth,
shiny surfaces. Typical foul breath.

Severe forms - hemorrhages and swelling in
periodontal membranes followed by loss of bone and
loosening of teeth.
CALCIUM
DEFICIENCY
SYSTEMIC MANIFESTATIONS
- Rickets
- Osteomalacia
- Osteoporosis : increased porosity of bone. Seen in elderly
patients.

- Acidosis : this causes an increased excretion of calcium in urine,
leading to rarefaction of skeleton.

- Steatorrhoea : excretion of calcium in faeces.
- Hypocalcemia : may occur if too much parathyroid tissue is
removed, causing diminished mobilization of calcium from bone.
ORAL MANIFESTATIONS
- Effect on alveolar bone : marrow spaces become
hemorrhagic and get filled with fibro-osteoid tissue. As a
result of alveolar bone resorption, teeth become loose.
Destruction of PDL.

- Effect on teeth : when serum calcium falls as low as
6-8mg/100ml, it results in enamel hypoplasia in developing
teeth.

- Dental Caries : positive correlation between hypo plastic
enamel and dental caries incidence.
MAGNESIUM
DEFICIENCY
SYSTEMIC MANIFESTATIONS
Alopecia, tropic skin lesions, hematoma.

Mg interferes with protein synthesis.

Depression, hyperirritability, cardiac arrythmias, muscular
weakness and convulsions.
ORAL MANIFESTATIONS
On Enamel Organ : 

predentin becomes wider, causing dentin-predentin junction to be in
different levels, leading to ‘Predentinstep’- characteristic of Mg
deficiency.

Dentin in labial portion is seriously affected. Incisal area becomes
atrophied.

On Gingival tissues : gingival hypertrophy with chronic destructive
periodontitis - loosening of teeth.
IRON
DEFICIENCY
SYSTEMIC MANIFESTATIONS

Hypochromic microcytic anemia.

Chronic fatigue, slightly depressed blood hemoglobin.

ORAL MANIFESTATIONS
Fissures in labial commissures, superficial glossitis.

Pappillae of tongue are atrophied - smooth, shiny and red
appearance. 

Affected oral tissue becomes susceptible to oral cancer.

Tongue: ‘patchy irregular denudation of papillae’.
SELENIUM
DEFICIENCY
SYSTEMIC MANIFESTATIONS
Liver necrosis, degenerative changes in parenchymal
organs, muscular dystrophy, degeneration of heart muscles,
endocardial calcification and pancreatic atrophy.

Effect on DENTAL TISSUES
Low selenium conc. - Significant antibacterial effect on S.
mutans, so it decreases cariogenicity of plaque.

Combination of Se and Fluoride - effective as preventive
agent against caries.
MANGANESE
DEFICIENCY
Marked hypocholestrolemia, transient dermatitis,
change in color, slow growth of hair and weight loss.
IODINE
Deficiency - enlargement of thyroid gland causing
hypothyroidism, goiter, myxedema.

Iodine toxicity - thyrotoxicosis
COPPER
DEFICIENCY
SYSTEMIC MANIFESTATIONS
Microcytic hypochromic anemia.
Menke’s Kinkyhair Syndrome (in infants)
• severe mental deficiency

• steel hair

• long metaphyseal abnormalities

• micrognathism

• neonatal ataxia

• hypothermia

ORAL MANIFESTATIONS

Copper salts decrease plaque formation in humans, thus affecting
pathogenesis of caries.
Dr. Aashna Dhingra
MDS first year