Normal fetal growth
May be divided into 3 phases:
The initial phase - first 16 wks - Hyperplasia
Second phase - upto 32 wks – Hyperplasia & Hypertrophy
Third phase - > 32 wks – Hypertrophy
Corresponding fetal growth rates during these phases are:
5 g/d at 15 wks , 15 g/d at 24 wks , 30 g/d at 34 wks.
Symphysiofundal height (SFH) measured from upper border of
symphysis pubis to uterine fundus increases by approx. 1cm/wk
between 14 to 36wks.
Abdominal girth increases on average of 1inch/wk after 30wks(30
inches at 30wks in average built women)
3.
Definition
FGR isa pathological condition in which a fetus has not
achieved his genetic growth potential regardless of fetal
size.
FGR & Small for Gestational Age (SGA) are not
synonymous.
A fetus does not need to be small to be growth
restricted.
4.
SGA isdefined as an EFW or AC < 10th
centile
Severe SGA as EFW or AC < 3rd
centile
FGR is defined as SGA with abnormal Doppler indices
such as Umbilical artery PI >95th
centile (or) mean Uterine
artery PI >95th
centile (or) CPR <5th
centile for gestational
age >32 wks.
Classification of FGR:
5.
Delphi concensus criteria:
•Gestational age <32 wks
• AC/EFW <3rd
centile or the AEDF in Umbilical
artery
• AC/EFW <10th
centile combined with Uterine
artery PI >95th
centile and/or Umbilical art PI >95th
centile
Early
FGR
• Gestational age >32 wks
• AC/EFW <3rd
centile (or)
• Atleast 2 of the following-
.AC/EFW <10th
centile,
.AC/EFW crossing centiles >2 quartiles on
growth centiles(noncustomised centiles),
.CPR <5th
centile or Umbilical artery PI >95th
centile.
Late
FGR
6.
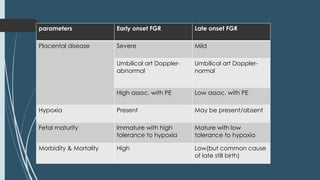
parameters Early onsetFGR Late onset FGR
Placental disease Severe Mild
Umbilical art Doppler-
abnormal
Umbilical art Doppler-
normal
High assoc. with PE Low assoc. with PE
Hypoxia Present May be present/absent
Fetal maturity Immature with high
tolerance to hypoxia
Mature with low
tolerance to hypoxia
Morbidity & Mortality High Low(but common cause
of late still birth)
7.
Risk factors
Maternal:
Previous history of FGR
Previous still births
Previous PE
Extremes of reproductive age
Low socioeconomic status
Low pre pregnancy weight
Poor gestational weight gain
Poor nutrition
Short inter pregnancy interval
Smoker,substance abuse
Drugs & teratogens
Medical conditions like-chr HTN,PE,gestational
Diabetes,SLE,Anti Phospholipid
sundrome,asthma,cyanotic cong heart
ds,vascular & renal ds,chrons ds
Anemia,beta thalassemia
Mullerian anomalies
Maternal infections
Fetal:
Genetic abnormalities
Multifetal gestation,
Congenital malformations
Drugs & teratogens
Infections-
viral(rubella,CMV,herpes,varicella,herpes
zoster,HIV),parasitic(toxoplasmosis,syphilis,malar
ia)
Placental:
Placental & cord abnormalities
Placental insufficiency
Maternal medical conditions
Multifetal gestation
infections
8.
Causes of smallness
4 reasons:
1.error in pregnancy dating
2.SGA:constitutionally small
3.SGA:fetal disease/anamoly/infection(non placental
mediated smallness)
4.SGA:Placental insufficiency
9.
Error in pregnancydating:
If pregnancy is dated inappropriately a fetus can be
misclassified as SGA.
Pregnancy should be dated acc to crown rump length until
13+6 wks gestation,or acc to head circumference from 14+0
wks.
Symmetry-
means that all fetal segments(head,abdomen,long bones) are
small and that centiles of their measurements are
comparable.
Asymmetry-
Related to more accentuated reduction of the
abdomen,compared to other fetal segments.
10.
Constitutionally smallfetuses:
These fetuses are small because they are genetically programmed to be so.
A)they are small from 2nd
trimester
B)symmetrically small
C)have low 1st
trimester risk for aneuploidy,low/normal placental hormones(PAPP-A,hcg)
D)maintain their growth velocity across gestation
E)have Normal fetoplacental Doppler patterns.
Structural or chromosomal abnormality:
Another group of small fetuses
Trisomy 18 MC(chromosomal abnormality)- usually assoc with multiple structural abnormalities
visible on scan.
One example of structural abnormality-Gastroschisis(abd wall defect),abdominal
measurement is smaller.
A)small from early second trimester
B)symmetrical/asymmetrical
C)have high 1st
trimester risk for aneuploidy and low placental hormones
D)Maintain or reduce their growth velocity
E)have normal fetoplacental Doppler patterns.
11.
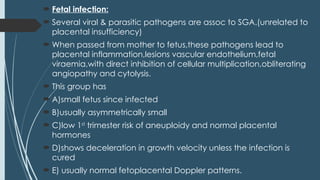
Fetal infection:
Several viral & parasitic pathogens are assoc to SGA.(unrelated to
placental insufficiency)
When passed from mother to fetus,these pathogens lead to
placental inflammation,lesions vascular endothelium,fetal
viraemia,with direct inhibition of cellular multiplication,obliterating
angiopathy and cytolysis.
This group has
A)small fetus since infected
B)usually asymmetrically small
C)low 1st
trimester risk of aneuploidy and normal placental
hormones
D)shows deceleration in growth velocity unless the infection is
cured
E) usually normal fetoplacental Doppler patterns.
12.
placental insufficiency:
Interactions between maternal & fetal circulations in the placenta are
fundamental for adequate exchange of nutrients and oxygen,by continuous
physiological process called ‘waves of trophoblast migration’.
Inadequate placentation is consequent to the absence of muscle
destruction and elastic portion of spiral arteries in trophoblast migration.
It leads to territory with high resistance to blood flow and decreased nutrition
of intervillous space.
This is assoc with greater frequency of PE and SGA.
A)may start from 2nd
trimester
B)asymmetrically small
C)has low 1st
trimester risk for aneuploidy ,but low placental
hormones(particularly PAPP-A)
D)progressive deceleration in growth velocity
E)likely to show abnormal fetoplacental Doppler patterns.
13.
Diagnosis
The firststep in the diagnosis of FGR is to identify women who
are at high risk of developing FGR based on history & co
morbid conditions.
Women with one or more risk factors should have a uterine art
doppler assessment at 20-24 wks.
If ut.a doppler is abnormal with a PI >95th
centile and/or
diastolic notching, these women should be monitored with
serial ultrasound from 26-28 wks of gestation.
Determination of gestational age is of utmost importance for
the diagnosis of FGR.
15.
Clinical examination:
womenare routinely weighed at every antenatal visit.
.Poor weight gain during pregnancy may be assoc with FGR.
.Pre pregnancy weight or booking weight is an important
independent indicator besides total weight gain in pregnancy.
The first line screening tool to assess fetal growth is abdominal
palpation & assessment of fundal height.
.Fundal height or symphysiofundal height is measured by tape
from upper border of pubic symphysis to uterine fundus.
.It usually corresponds in centimeters to gestational age
between 20-36 wks.
.FGR can be suspected if difference between expected &
observed values in fundal height is 3cm or more.
16.
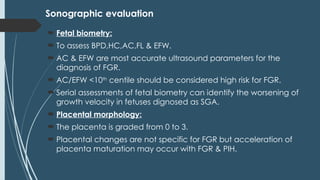
Sonographic evaluation
Fetalbiometry:
To assess BPD,HC,AC,FL & EFW.
AC & EFW are most accurate ultrasound parameters for the
diagnosis of FGR.
AC/EFW <10th
centile should be considered high risk for FGR.
Serial assessments of fetal biometry can identify the worsening of
growth velocity in fetuses dignosed as SGA.
Placental morphology:
The placenta is graded from 0 to 3.
Placental changes are not specific for FGR but acceleration of
placenta maturation may occur with FGR & PIH.
17.
Amniotic fluidvolume:
Amniotic fluid volume reflects how the fetus has been coping
during the previous 2-3wks.
FGR usually assoc with oligohydramnios,which indicates chronic
fetal hypoxia.
Measured by Single deep pocket(SDP) & Amniotic fluid index(AFI).
SDP-normal values 2-8cm,<2cm – oligo.
AFI-normal values 8-25cm,<5cm – oligo.
(after 20 wks gestation)
Interpretation of amniotic fluid volume is based on single deep
vertical pocket over AFI.
18.
Doppler paramaters
Fetal maternaldoppler assessment is gold standard to assess
placental development & function.
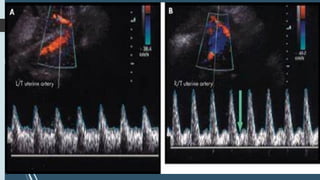
Uterine art doppler:
UtA doppler reflects trophoblastic invasion that is completed
at 23-24 wks gestation & placental development.
Measured at 11-14 wks and repeated in 2nd
trimester.
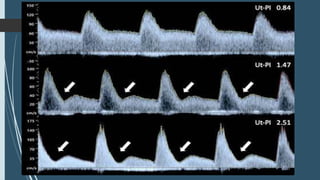
Presence of U/L or B/L Uterine artery notching, indicates risk of
PE,placental failure & FGR.
UtA PI >95th
centile,assoc with AC/EFW <10th
centile used to
diagnose early onset FGR.
Normal UtA doppler may rule out FGR in high risk women.
21.
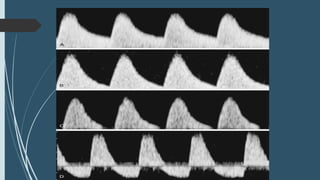
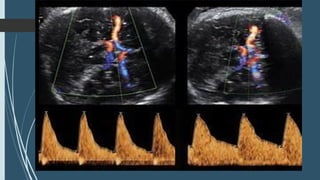
Umbilical arterydoppler:
UA doppler reflects placental function and degree of
placental insufficiency.
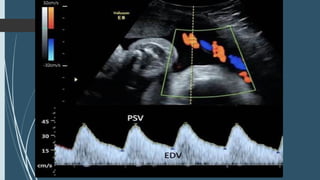
High UA PI (>95th
centile)
with Positive EDF->50% placental insufficiency,
with Absent EDF ->70% placental insufficiency,
with Reverse EDF ->90% placental insufficiency.
UA doppler has an important role in differentiating early & late
onset FGR.
27.
Middle cerebralartery doppler:
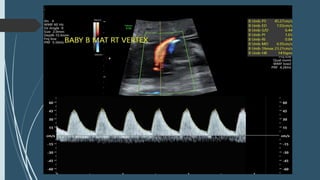
Reflects fetal response to placental insufficiency.
Cerebral vasodilatation,also known as ‘Brain sparing effect’,is a response of fetus to
chronic hypoxemia.(inc in diastolic flow & dec in pulsatality)
Results in reduced MCA PI & reduced CPR (MCA/UA PI ratio) – are early signs of
fetal hypoxia in SGA fetuses.
Brain sparing effect may develop in 2 scenarios-
A)in early onset FGR,where UA was already abnormal bz of worsening of placenta
function,
B)in late onset FGR,UA is typically normal bz fetal metabolic needs are greater than
placental capacity(small placenta)
Development of brain sparing effect is considered for timing of delivery in late onset
FGR where UA is normal.
CPR is a marker of failure to reach growth potential at term and could help in
identifying the at risk fetuses.
Normal CPR- >1,almost constant in last 10wks of pregnancy.
Pathological CPR -<1,FGR,neonatal acidosis,low birth weight.
29.
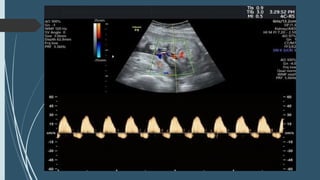
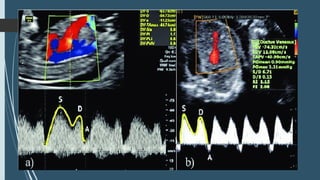
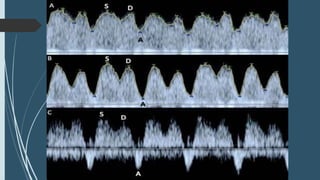
Ductus venosusdoppler:
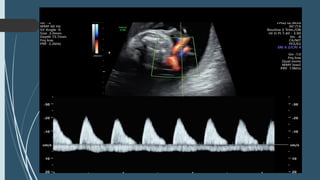
Reflects atrial pressure volume changes during cardiac cycle.
Normally,flow in DV is forward.moving towards heart.
Increased PI and absent or reverse a-wave in DV reflects onset
of overt cardiac compromise.
DV PI >95th
centile-high risk of fetal hypoxia.
Absent or reverse a-wave – fetal survival of longer than 1wk is
unlikely.
Decision to deliver fetus is considered after giving steroids for
lung maturity and magnesium sulphate for neuroprotection.
32.
Tests formaternal & fetal infections:
MC pathogens to be reported are CMV,toxoplasma,syphilis,&
malaria.
Tuberculosis also assoc with fetal growth.
Malaria is known to be a significant cause of preterm birth and LBW
worldwide.
Serological screening for CMV,toxoplasma sld be offered.
Test for malaria ,syphilis must be considered in high risk populations.
If screening results are positive ,the only way to assess fetal infection
is C reactive protiene of amniotic fluid.
Different USG findings can be suggestive of fetal infections,but not
diagnostic.(hydrops,ascites,placental enlargement,echogenic
bowel,cataract,shortening of long bones,bone
deformity,hepatosplenomegaly,ventriculomegaly etc.)
33.
Invasive antenataldiagnosis considered for
chromosomal abnormalities.
Karyotype should be offered in severe SGA.
34.
Management
Mainly includesmonitoring fetal wellbeing and the decision of
when and how to deliver the fetus to prevent neurological
injury and stillbirth.
35.
Pharmacological:
Antiplateletagents during pregnancy are assoc with
consistent reductions in relative risk in PE,birth before 34
wks,SGA and other adverse outcomes.
Aspirin when started before 16 wks – showed reduced
incidence in PE & SGA.
When started after 20 wks – no reduction observed.
Smoking cessation by 15 wks shown recuced incidence of
LBW.
36.
Steroids,
Singlecourse of antenatal glucocorticoids to accelerate fetal
lung maturity,to reduce incidence of respiratory distress
syndrome,intraventricular hemorrhage and death in FGR.
All patients with FGR who are planned for delivery between
24-34 wks gestation should receive steroids.
ACOG recommends extended steroid coverage between
34+0 to 36+6 wks of gestation.
RCOG recommends till 35+6 wks gestation.
37.
Magnesium sulphate,
A portion of growth restricted fetuses will be delivered preterm
and are at high risk for cerebral palsy.
Maternal magnesium sulphate administration – shown to have
neuroprotection & to reduce incidence of cerebral palsy in
preterm infants.
Patients who are planned to deliver before 32 wks gestation
should receive magnesium sulphate for neuroprotection.
RCOG recommends between 24+0 to 29+6 wks gestation.
38.
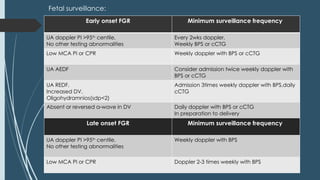
Fetal surveillance:
Early onsetFGR Minimum surveillance frequency
UA doppler PI >95th
centile,
No other testing abnormalities
Every 2wks doppler,
Weekly BPS or cCTG
Low MCA PI or CPR Weekly doppler with BPS or cCTG
UA AEDF Consider admission twice weekly doppler with
BPS or cCTG
UA REDF,
Increased DV,
Oligohydramnios(sdp<2)
Admission 3times weekly doppler with BPS,daily
cCTG
Absent or reversed a-wave in DV Daily doppler with BPS or cCTG
In preparation to delivery
Late onset FGR Minimum surveillance frequency
UA doppler PI >95th
centile,
No other testing abnormalities
Weekly doppler with BPS
Low MCA PI or CPR Doppler 2-3 times weekly with BPS
39.
Timing ofdelivery:
Timing of delivery remains the critical issue.
Delivery timing balances Risks of prolonging the pregnancy (i.e
stillbirth)with the risks due to prematurity.
GA is critical in decision making.
As a thumb rule neonatal risk decreases with increasing GA.
Other critical issues in decision making is the interpretation of
surveillance tests used to predict perinatal outcomes are
sequence of doppler changes,BPP,cCTG
40.
Mode ofdelivery:
Mode of delivery depends primarily on the gestational age
and any evidence of acidaemia.
Vaginal delivery can be allowed as long as there is no
obstetric indication for caesarean and FHR pattern is normal.
Fetuses with major anomalies incompatible with life should be
delivered vaginally.
In all case of FGR with features of acidosis– elective caesarean
section should be performed without trail of labour.
41.
For nearterm fetus,
Delivery of a suspected growth restricted fetus with normal UA
doppler , normal AFI and reassuring fetal testing can likely be
deferred until 37-38 wks gestation.
If oligohydramnios present , delivery between 36+0 and 37+6
wks is recommended.
With normal FHR pattern vaginal delivery is planned.
Notably some of the fetuses cannot tolerate labor.
42.
Fetus remotefrom term,
If growth restriction is identified before 34 wks,with normal
AFI,normal fetal surveillance findings – Observation is
recommended.
As long as interval fetal growth and fetal surveillance test
results are normal,pregnancy is allowed to continue.
Fetal growth Reassessment is typically made no sooner than 3
wks later.
44.
Fetal & Neonatalproblems associated with FGR
Fetal hypoxia and acidosis (repetitive late deccelerations,poor
BPP,reversal of EDF in UA,abnormal venous doppler,blood gas
analysis showing acidic pH)
Stillbirth
Oligohydramnios (common finding)
Neonatal complications (signs of soft tissue wasting,thin skin,little s/c
fat,abdomen is scaphoid,protruberant ribs,reduced muscle
mass,umbilical cord is thin & limp,frequently meconium stained,birth
wt < 10th
centile,thrombocytopenia,elevated nucleated rbc count)
Respiratory distress syndrome
Meconium aspiration syndrome
45.
Persistant fetalcirculation (frequent sequel to hypoxia &
acidosis,pulm hypertension develops,blood flow ductus arteriosis
persists even after birth,rt to lt shunting with no structural heart
defect)
Intraventricular haemorrhage
Newborn encephalopathy (cerebral edema,intracranial bleed or
infarct,cerebral palsy)
Hypoglycemia
Hypocalcemia
Hyperviscosity syndrome (high hematocrit,polycythemia,lead to
sluggish blood flow,thrombosis,congestive heart failure,pulmonary
edema)