FETAL GROWTH
RETARDATION
In Modern Practice –Made Simple
DR. SHARDA JAIN DR JYOTI AGARWAL
SHARING KNOWLEDGE & SKILL IS OUR
BIGGEST MOTTO
Elephants come in different sizes!
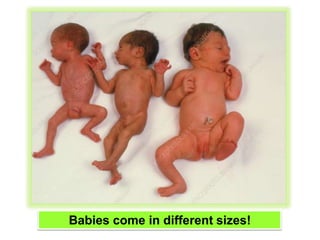
Babies come in different sizes!
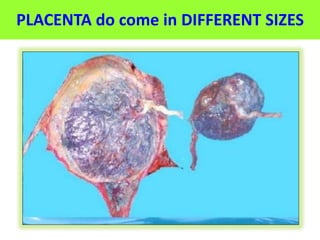
PLACENTA do come in DIFFERENT SIZES
FETAL GROWTH RETARDATION
• Is defined as FAILURE OF A FETUS TO REACH
TO ITS FULL GENETIC GROWTH POTENTIAL
IN-UTERO,PUTTING IT AT RISK OF
PERINATAL MORTALITY & MORBIDITY.
I.U.G.R...X / S.G.A. / L.B.W. (<2.5 kg )
• WHO
• ACOG
S.G.A.< 10 th percentile for gestational age
SGA <3rd centile
THE STEPS ..
3-10 % SINGLETON
12 -40 % TWINS
True FGR
INCIDENCE
MORTALITY 6-8
TIMES MORE
& majority we
loose in ist 24 hrs
only bcz
Hypoxia /academia
MAJOR CONCERN IN FGR
• Cause of concern is not the size ,but the
possibility of life threatening fetal compromise
Hypoxia /Acedemia which we fail to detect.
• Timely identification of fetal compromise is
difficult but crucial for proper management & a
favourable neonatal outcome as it is 2nd leading
cause of Perinatal mortality after prematurity.
No treatment ,diagnosis difficult
FGR Babies pose Big Challenge !
• 50% of still births
• 75% of unexplained fetal
deaths
• 8-10 times Increased Perinatal
morbidity and mortality
Bcz of considerable advances , to detect fetal
compromise in FGR fetus still remains COFUSING!
WHY GYNAECOLOGISTS
ARE CONCERNED ?
ABNORMAL LONG TERM
• NEURODEVELOPMENTAL OUTCOME.
• LONGTERM CARDIOVASCULAR DYSFUNCTION
• METABOLIC SYNDROME
WHY WE ARE UNABLE TO PICK UP THE
BABY AT RISK ?
FUNCTIONAL CLASSIFICATION
of SMALL FETUS
• Contitutional Small FETUS ( normal ) 70%
• ABNORMAL SMALL FETUS – symmetrical
(10%)
• FROWTH RESTRICTED FETUS-Asymmertrical
(20%)
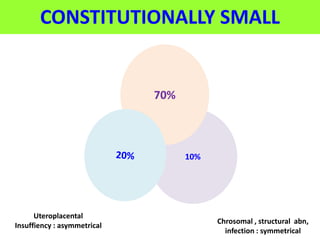
10%
70%
CONSTITUTIONALLY SMALL
Uteroplacental
Insuffiency : asymmetrical
Chrosomal , structural abn,
infection : symmetrical
NORMAL SMALL FETUS
• No Structural abnormality.
Normal umbilical Doppler.
Normal AFI.
• Less than 10th percentile
• Good prognosis.
• No increased risk.
• No special care Needed.
70% INDIA -2.6 KG
USA 3.6 KG
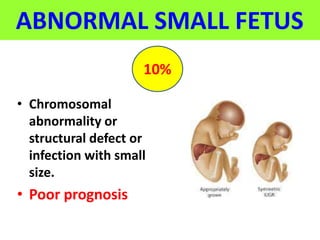
ABNORMAL SMALL FETUS
• Chromosomal
abnormality or
structural defect or
infection with small
size.
• Poor prognosis
10%
GROWTH RESTRICTED FETUS
• Small due to placental dysfunction.
• Variable prognosis. ( late -80% sail through)
(early 20% -bad prognosis)
• Appropriate and timely treatment can
improve outcome.
20%
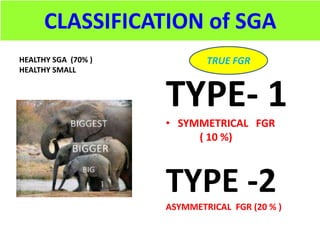
CLASSIFICATION of SGA
HEALTHY SGA (70% )
HEALTHY SMALL
TYPE- 1
• SYMMETRICAL FGR
( 10 %)
TYPE -2
ASYMMETRICAL FGR (20 % )
TRUE FGR
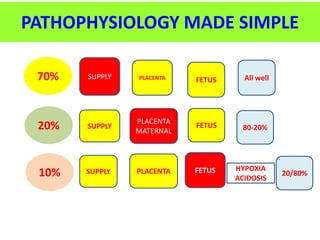
PATHOPHYSIOLOGY MADE SIMPLE
SUPPLY
PLACENTA
MATERNAL
FETUS
SUPPLY PLACENTA FETUS HYPOXIA
ACIDOSIS
SUPPLY PLACENTA FETUS All well70%
20% 80-20%
10% 20/80%
TRUE FGR
SYMMETRICAL FGR
• Less common, 20% cases.
• Both head & abdomen are
small
• HC/AC RATIO IS NORMAL
• FL: AC ratio is normal
• Etiology : Chromosomal,
fetal infection ?chemical
exposure
• POOR PROGNOSIS
ASYMMETRICAL FGR
• More common & 80% cases
of FGR
• Abdomen is smaller than head
• HC/AC ratio increases
• FL: AC ratio increases
• Placental insufficiency
(e.g pre-eclampsia)
• FAIR to GOOD
PROGNOSIS
In SEVERE symmetrical FGR
karyotyping , malformation
& infection screen (Very Bad Prognosis)
Symmetrical
FGR Asymmetrical
FGR
10
–
12
%
Poor prognosis
Fair prognosis
22
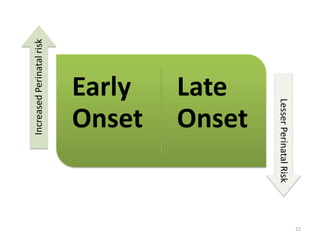
Early
Onset
Late
Onset
IncreasedPerinatalrisk
LesserPerinatalRisk
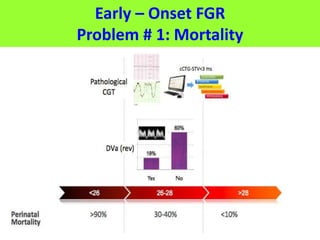
Early – Onset FGR
Problem # 1: Mortality
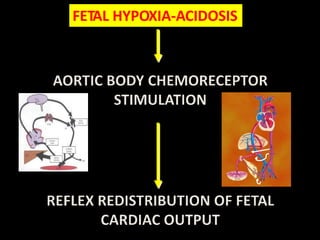
FETAL HYPOXIA-ACIDOSIS
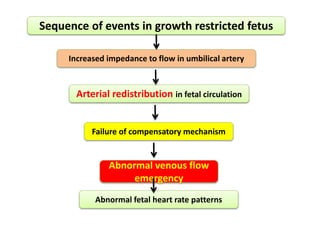
Sequence of events in growth restricted fetus
Increased impedance to flow in umbilical artery
Arterial redistribution in fetal circulation
Failure of compensatory mechanism
Abnormal venous flow
emergency
Abnormal fetal heart rate patterns
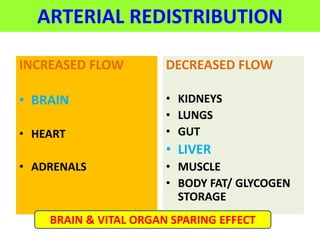
ARTERIAL REDISTRIBUTION
INCREASED FLOW
• BRAIN
• HEART
• ADRENALS
DECREASED FLOW
• KIDNEYS
• LUNGS
• GUT
• LIVER
• MUSCLE
• BODY FAT/ GLYCOGEN
STORAGE
BRAIN & VITAL ORGAN SPARING EFFECT
FIRST 16 WKS:HYPERPLASIA
16-32 WKS:HYPERPLASIA + HYPERTROPHY
> 32 WKS :MOSTLY HYPERTROPHY
PHASES OF FETAL GROWTH
EARLY insult : affect CELLS ,LATER one affects SIZE
BRAIN WEIGHT
NORMAL
3 TIMES
MORE
THAN LIVER
ASYMMETRICAL FGR
5 TO 6 TIMES
MORE
THAN LIVER
IDENTIFYING ETIOLOGY IS
NECESSARY ?
FETAL
• CHROMOSOMAL
• MALFORMATIONS
• INFECTION
• MULTIPLE GESTATIONS
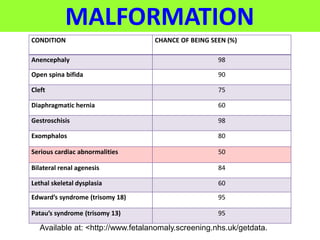
MALFORMATION
CONDITION CHANCE OF BEING SEEN (%)
Anencephaly 98
Open spina bifida 90
Cleft 75
Diaphragmatic hernia 60
Gestroschisis 98
Exomphalos 80
Serious cardiac abnormalities 50
Bilateral renal agenesis 84
Lethal skeletal dysplasia 60
Edward’s syndrome (trisomy 18) 95
Patau’s syndrome (trisomy 13) 95
Available at: <http://www.fetalanomaly.screening.nhs.uk/getdata.
FACTORS AFFECTING FETAL FROWTH
Fetus
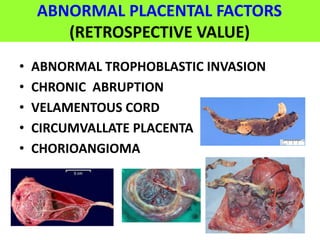
ABNORMAL PLACENTAL FACTORS
(RETROSPECTIVE VALUE)
• ABNORMAL TROPHOBLASTIC INVASION
• CHRONIC ABRUPTION
• VELAMENTOUS CORD
• CIRCUMVALLATE PLACENTA
• CHORIOANGIOMA
FGR & MATERNAL FACTORS
• PREGNANCY COMPLICATIONS
PET/ APH
RENAL
APLA SYNDROME
• ENVIRONMENT / DRUGS
• INFECTIONS
PIH /HDP
COMPLICATIONS
MOTHER
• NIL
• LIFE-THREATENING IN
Severe PET / Eclampsia
• 2 FOLD > Of FGR in next
pregnancy
BABY-6 to 8 fold
Increase in Intra partum &
Postpartum Deaths
ANTEPARTUM –
CHRONIC HYPOXIA /DEATH
INTRAPARTUM
HYPOXIA & ACIDOSIS
POSTPARTUM
MORBIDITY RATE IS > 50 %
DIAGNOSIS OF FGR
Accurate dating /Risk factors
Accurate measuring: Clinical
examination/Close Monitoring
Imaging : Biometry and Doppler
SCREENING SCORE ???
PREDICTIONS
CLINICAL EXAMINATION
• 4 OR MORE DISCREPANCY
• SYMPHYSEO-FUNDAL HEIGHT 18 to 30 wks
if 2-3 cm less - FGR suspected.
• ACOG –SPECIFICITY- 96 % ,SENSITIVETY –
70 to 85 %
• Maternal wt –stationary or decrease
• ABDOMINAL GIRTH –Stationary or decrease
ULTRASOUND
• Estimated FETAL WT < 10 TH OR 3 rd CENTILE
ON GROWTH CHARTS
• NO INCREASE IN HEAD OR ABDOMEN
SIZE ON TWO SCANS 2 WKS APART.
UNTIL DELIVERY
CLOSE SURVEILLANCE
+ DOPPLER
B.P.P
DFMC +NST + AFI
Timeline for fetal hypoxemia
Doppler ultrasound can predict fetal distress
sooner than BPP &CTG
DOPPLER IS EARLIEST& ABNORMAL CTG IS LATE
PANDORA BOX
DR JYOTI AGARWAL
Ultrasound helps to….
• Assign fetal age
• Assess fetal size
• Estimate fetal weight
• Exclude Anomalies
• Amniotic fluid
assessment
• Placental ultrasound
• Color Doppler
• Biophysical profile
Ultrasound has revolutionized the
practice of obstetrics
• It has high negative
predictive value to
r/o FGR
• Cochrane database
(2000) reveals that
there is 40 %
improvement in
perinatal mortality by
judicious use of
doppler
Dating is important i trimester
Compare USG GA with LMP GA
Assign LMP
EDD
< 1wk
> 1wk
Re assign
EDD
VARIBILITY +/- 5-7 days
GOOD TO DATE AT
N.T. SCAN
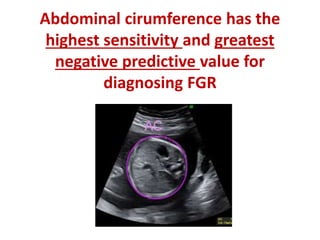
Abdominal cirumference has the
highest sensitivity and greatest
negative predictive value for
diagnosing FGR
Growth – dates uncorrected
Routine Foetal Biometry
Based on customised Growth Curve “VISUAL EFFECT”
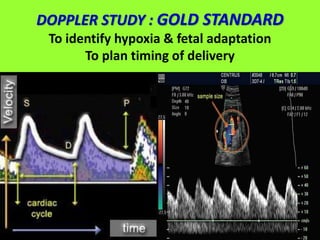
DOPPLER STUDY : GOLD STANDARD
To identify hypoxia & fetal adaptation
To plan timing of delivery
Highest accuracy is required in
assessment of the
Degree of Fetal Deterioration
Degree of fetal Hypoxia
- Fetal arterial doppler
Degree of fetal Acidemia
–Fetal Venous doppler
Each additional day gained in utero can
significantly increase neonatal survival
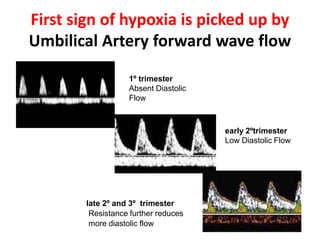
First sign of hypoxia is picked up by
Umbilical Artery forward wave flow
1º trimester
Absent Diastolic
Flow
early 2ºtrimester
Low Diastolic Flow
late 2º and 3º trimester
Resistance further reduces
more diastolic flow
DECREASED EDF ABSENT EDF REVERSED EDF
Abnormal Umb. A doppler appears when at least
60 % of the placental vascular bed is obliterated
PositiveDiastolic Flow 10 - 12% Hypoxic
00% Acidemic
Absent/ Reverse Diastolic
Flow
80% Hypoxic
40 – 45 % Acidemic
UMBILICAL ARTERY DOPPLER SHOULD BE THE
PRIMARY SURVEILLANCE TOOL
• If umbilical artery flow is normal repeat every 15
days
• If abnormal repeat it twice weekly if end diastolic
velocity is present
• Should be done daily with absent or reversed end
diastolic velocity
• In low risk , no conclusive evidence that routine
umbilical artery doppler benefits either mother or baby
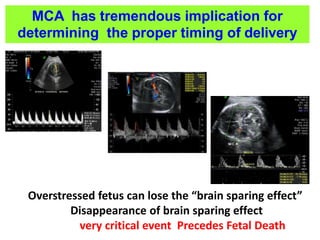
Overstressed fetus can lose the “brain sparing effect”
Disappearance of brain sparing effect
very critical event Precedes Fetal Death
MCA has tremendous implication for
determining the proper timing of delivery
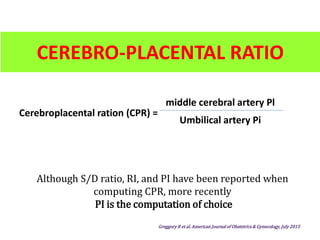
CEREBRO-PLACENTAL RATIO
Although S/D ratio, RI, and PI have been reported when
computing CPR, more recently
PI is the computation of choice
Greggory R et al. American Journal of Obstetrics & Gynecology, July 2015

Cerebroplacental ration (CPR) =
middle cerebral artery Pl
Umbilical artery Pi
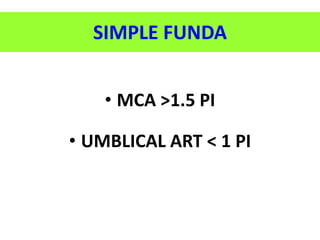
SIMPLE FUNDA
• MCA >1.5 PI
• UMBLICAL ART < 1 PI
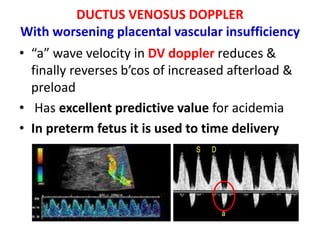
DUCTUS VENOSUS DOPPLER
With worsening placental vascular insufficiency
• “a” wave velocity in DV doppler reduces &
finally reverses b’cos of increased afterload &
preload
• Has excellent predictive value for acidemia
• In preterm fetus it is used to time delivery
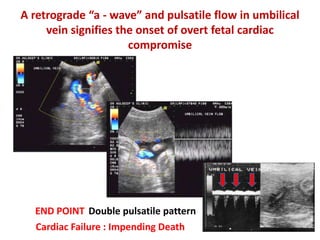
A retrograde “a - wave” and pulsatile flow in umbilical
vein signifies the onset of overt fetal cardiac
compromise
Double pulsatile patternEND POINT
Cardiac Failure : Impending Death
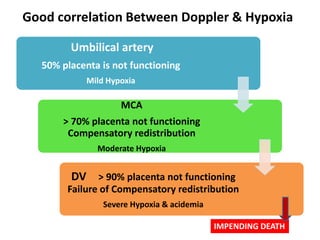
Good correlation Between Doppler & Hypoxia
Umbilical artery
50% placenta is not functioning
Mild Hypoxia
MCA
> 70% placenta not functioning
Compensatory redistribution
Moderate Hypoxia
DV > 90% placenta not functioning
Failure of Compensatory redistribution
Severe Hypoxia & acidemia
IMPENDING DEATH
What does
DOPPLER tell In
FGR ?
UMBLICAL ART DOPPLER , MCA
DOPPLER,DUVTUS VENOSUS DOPPLER
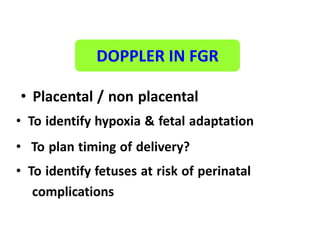
1To identify etiology of IUGR
• Placental / non placental
• To identify hypoxia & fetal adaptation
• To plan timing of delivery?

• To identify fetuses at risk of perinatal
complications
DOPPLER IN FGR
Management
Medical therapy
Antepartum surveillance
Timing of delivery
Stage based approach
IS THERE ANY
ANTENATAL
TREATMENT ??
Antenatal Treatment
*Amino acids ?
*Oxygen?
*Rest ?
*Monitoring
*Steroids
*Mag sulf ( < 32 wks )
3 WAYS TO GIVE( 4 GM + 24 hrs )
Drugs
• Aspirine ?
• Progesterone (Inj/tablet) ?
• Heparin ?
• Sildinafil ?
• L- arginine ?
• Micronutrients
GIVING STEROID & DELIVERY WITHIN 48 HOURS.
DELAYING DOES NOT IMPROVE OUTCOME |(GRIT TRIAL LEVEL I EVIDANCE)
STEROID TREATMENT
REPEAT OR NOT, DEXA √ OR BETAMETHASONE
LETS REVISE
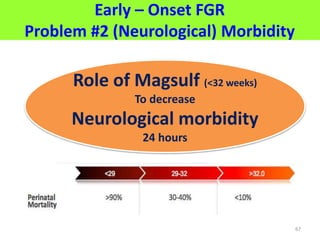
Early – Onset FGR
Problem #2 (Neurological) Morbidity
67
Role of Magsulf (<32 weeks)
To decrease
Neurological morbidity
24 hours
IN FGR : AIM OF DELIVERY
A live fetus
That Grows & survives !
Riskof intrauterine compromisehas tobe
weighed against the potential risksfrom
iatrogenic prematuredelivery
Best Time Is When Fetal Redistribution
Mechanism Starts Failing
Intervene Timely
When to deliver ?
There is a better outcome with timely
intervention & delivery for fetus who shows
sign significant compromise
Time to Deliver
Factors to decide time to deliver
• Degree of Prematurity
• NICU facility
• Degree of Hypoxia, acidemia,
hepatic metabolic derangement (mother)
Challenge to weigh the risks and benefits of
interventions
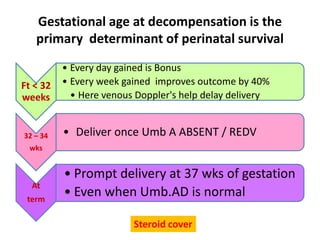
Gestational age at decompensation is the
primary determinant of perinatal survival
Ft < 32
weeks
• Every day gained is Bonus
• Every week gained improves outcome by 40%
• Here venous Doppler's help delay delivery
32 – 34
wks
• Deliver once Umb A ABSENT / REDV
At
term
• Prompt delivery at 37 wks of gestation
• Even when Umb.AD is normal
Steroid cover
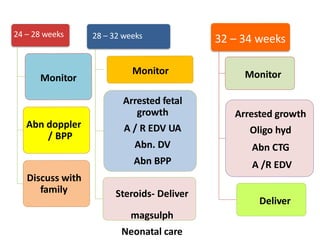
24 – 28 weeks
Monitor
Abn doppler
/ BPP
Discuss with
family
28 – 32 weeks
Monitor
Arrested fetal
growth
A / R EDV UA
Abn. DV
Abn BPP
Steroids- Deliver
magsulph
Neonatal care
32 – 34 weeks
Monitor
Deliver
Arrested growth
Oligo hyd
Abn CTG
A /R EDV
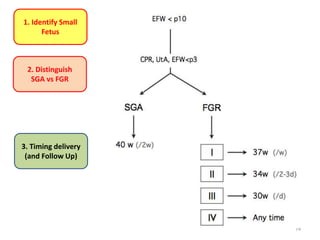
74
1. Identify Small
Fetus
2. Distinguish
SGA vs FGR
3. Timing delivery
(and Follow Up)
How to Deliver ?
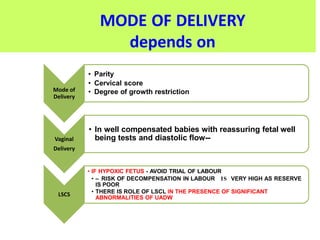
MODE OF DELIVERY
depends on
Mode of
Delivery
• Parity
• Cervical score
• Degree of growth restriction
Vaginal
Delivery
• In well compensated babies with reassuring fetal well
being tests and diastolic flow--
LSCS
• IF HYPOXIC FETUS - AVOID TRIAL OF LABOUR
• – RISK OF DECOMPENSATION IN LABOUR IS VERY HIGH AS RESERVE
IS POOR
• THERE IS ROLE OF LSCL IN THE PRESENCE OF SIGNIFICANT
ABNORMALITIES OF UADW
BABIES OUTCOME
is 5-20 times greater than for AGA, mainly
due to
• intrauterine death,
• perinatal asphyxia,
• Congenital anomalies.
Perinatal mortality for FGR infants
Is 5-10 times higher than for AGA infants, especially for infants with
↓ head circumference at birth.
Intellectual and motor function (excluding those with congenital
infections, chromosomal abnormalities) depends on adverse perinatal
events and on the specific cause of growth restriction.
Early identification and treatment of hypoglycemia and polycythemia
improves outcome. Neurologic abnormalities are usual with genetic and
infectious causes of IUGR.
NEUROLOGIC MORBIDITY
Catch-up growth occurs fast after birth
but these patients usually remain smaller than expected.
FGR: With placental causes of IUGR
Recent studies implicate FGR with adult onset of
• Hypertension,
• Coronary heart disease,
• Hypercholesterolemia,
• Diabetes.
These studies suggest that Fetal growth retardation has long term
affects on endocrine development and homeostasis.
Fetal “Programming”
of cardiovascular disease:
TAKE HOME MESSAGE
• Timing of delivery in FGR:
• Before 32-34 weeks, base delivery on ductus venosus
• After 34 weeks, absent/reversed EDF indication to deliver
• If umbilical artery normal but MCA at or below 5th centile – sign
of cerebral redistribution – offer delivery at 37 weeks
(RCOG, 2013)
• No role of aortic isthmus as yet
FETAL GROWTH  RETARDATION  In Modern Practice –Made Simple