Fetal growth
⚫Three phasesin the prenatal fetal growth
1. Ovular period (germinal period) lasts for 2 weeks
following ovulation or 4 weeks of GA from the
LMP
2. Embryonic period- lasts from the beginning of 3rd
weeks following fertilization until completion of
8th
weeks following fertilization or 5th
to 10th
weeks fro LMP
3. Fetal period- is from the beginning of 9th
week to
birth or 11th
week from the LMP till the end of
pregnancy. Organ maturation & growth occur
during this period.
3.
Phase of fetalgrowth
⚫Up to 16 weeks- cellular hyperplasia
⚫16 to 32 weeks- Cellular hyperplasia & hypertrophy
⚫After 32 weeks to term- Cellular hypertrophy
⚫Most of fetal weight gain (2/3) occurs beyond 24th
week of
pregnancy
⚫First half of the pregnancy: Growth is dependant on
chromosomal and genetic factors
⚫Second half of the pregnancy: Growth is dependant on the
availability of placental growth support.
4.
Rate of humanfetal growth
⚫At first 15 weeks, growth rate is -5 g/day
⚫At 24 weeks, it is 15-20 g/day
⚫At 34 weeks, it is 30-34 g/day, after which growth rate
decreases at 24 g/day
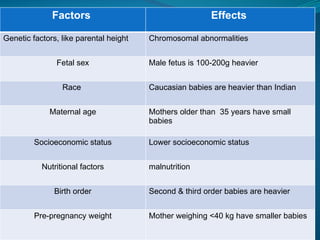
Factors Effects
Genetic factors,like parental height Chromosomal abnormalities
Fetal sex Male fetus is 100-200g heavier
Race Caucasian babies are heavier than Indian
Maternal age Mothers older than 35 years have small
babies
Socioeconomic status Lower socioeconomic status
Nutritional factors malnutrition
Birth order Second & third order babies are heavier
Pre-pregnancy weight Mother weighing <40 kg have smaller babies
❖IUGR/FGR: Intrauterine growthrestriction (IUGR) defined as
pathological inhibition of fetal growth & failure of the fetus to
attain its growth potential.
• Fetus is said to be growth restricted if ultrasound measured fetal
weight deviates below gestational age specific threshold of <10th
centile.
❖ This definition intentionally excludes of fetuses that are small
for gestational age (SGA) but are not pathologically small
• SGA May or may not have pathological restriction in its growth.
Pathophysiology
⚫ There isreduction in the available nutrients and
micronutrients to the fetus either due to their less
availability to the mother (poverty or
malnutrition) or their reduced placental transfer.
⚫ In some cases there is faulty utilization of
nutrients by the fetus.
⚫ The end result is a small fetus with scanty liquor
and reduced glycogen and fat stores.
14.
Continue…
● There seemsto be absence of invasion of trophoblast in
media of spiral arteries with reduced cytotrophoblastic
proliferation and impairment of placental angiogenesis in
placenta of growth-restricted fetuses like in pre-eclampsia.
● In the early stages of hypoxia, the fetus uses adaptive
techniques such as growth reduction, decreased foetal
movements and vascular redistribution to reduce its
oxygen requirements, in an attempt to prevent hypoxic
injury.
● There is stimulation of erythropoiesis with an increase in
foetal hematocrit.
15.
Continue..
⚫ As thefetus becomes increasingly hypoxemic,
there may be a decrease in flow to other organs
and a corresponding increase in foetal blood
flow to the brain, heart and adrenals.
⚫ Failure of compensatory mechanisms cause
abnormal foetal heart rate patterns.
16.
Pathophysiology
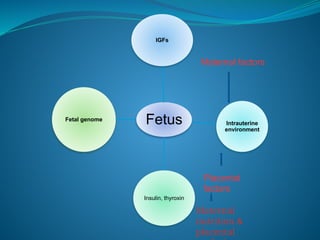
1. Genomic mechanisms–this may d/t differential
expression of maternal/paternal chromosomal
region because of suppressed expression of
either maternal or paternal alleles
2. Uteroplacental and fetoplacental vascular
development: deficient vascular invasion l/t
elevated vascular impedance
3. Deficiency in placental transport mechanism:
may lead to nutrient deprivation for fetus
4. Somatotrophic mechanism: deficiency of main
regulatory factor for fetal growth e.g- IGF-I, II,
IGFBP 1-6
17.
Maternal cause
1. Constitutional
2.Maternal body weight – pre pregnancy & weight gain
during pregnancy
3. Nutritional:
✔ Severe malnutrition
✔ Inflammatory bowel disease
✔ Intestinal bypass surgery
4. Hypoxia:
✔Asthma
✔Cyanotic heart disease
✔High altitude
✔SLE
✔Pulmonary disease
Smoking, substance abuseand SGA.
- The mean birth weight is reduced by 175- 200 g in
infants born to cigarette smokers
- Cotinine decreases uteroplacental blood
flow in a dose-related way by stimulating
sympathetic neurons.
- Carboxyhemoglobin levels are elevated in
mothers who smoke and in their fetuses, and
the avidity of fetal hemoglobin to carbon
monoxide may exacerbate fetal hypoxia.
21.
- Nicotine hasa demonstrated teratogenic
effect in animals.
- Marijuana, cocaine, heroin, amphetamines
and alcohol can all cause IUGR, with the
head circumference affected in many
studies, suggesting a symmetrical form of
growth retardation and an insult during the
cell mitotic phase in early pregnancy.
Classification of IUGR
Basedon clinical & USG examination:
✔ Symmetrical IUGR
✔ Asymmetrical IUGR
Based on gestational age:
✔ Early onset IUGR –Effects before 32 week
✔ Late onset IUGR- Effects after 32 week
Based on clinical examination: Lag of FH from GA
✔ Mild IUGR: FH lags by 2-4 weeks
✔ Moderate: 4-6 weeks
✔ Severe: >6 weeks
25.
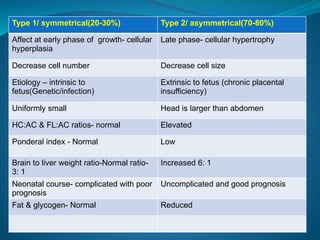
Type 1/ symmetrical(20-30%)Type 2/ asymmetrical(70-80%)
Affect at early phase of growth- cellular
hyperplasia
Late phase- cellular hypertrophy
Decrease cell number Decrease cell size
Etiology – intrinsic to
fetus(Genetic/infection)
Extrinsic to fetus (chronic placental
insufficiency)
Uniformly small Head is larger than abdomen
HC:AC & FL:AC ratios- normal Elevated
Ponderal index - Normal Low
Brain to liver weight ratio-Normal ratio-
3: 1
Increased 6: 1
Neonatal course- complicated with poor
prognosis
Uncomplicated and good prognosis
Fat & glycogen- Normal Reduced
26.
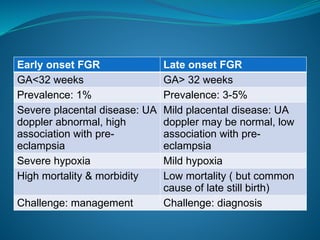
Early onset FGRLate onset FGR
GA<32 weeks GA> 32 weeks
Prevalence: 1% Prevalence: 3-5%
Severe placental disease: UA
doppler abnormal, high
association with pre-
eclampsia
Mild placental disease: UA
doppler may be normal, low
association with pre-
eclampsia
Severe hypoxia Mild hypoxia
High mortality & morbidity Low mortality ( but common
cause of late still birth)
Challenge: management Challenge: diagnosis
27.
Ponderal index
Way ofcharacterizing the relationship of
height to mass for an individual.
⚫PI = 1000 x 3 Mass (kgs)
⚫ Height (cms)
⚫Typical values are 20 to 25.
⚫PI is normal in symmetric IUGR.
⚫PI is low in asymmetric IUGR.
Clinical method
1. Clinicalpalpation of the uterus-
✔ Fundal height
✔ Liquor volume
✔ Fetal mass
2. Symphysis fundal height: A lag of >3 cm suggest growth
restriction
3. Measurement of maternal weight gain & AG- stationary or
falling
30.
Role of USGin FGR
▪ Identification of FGR
▪ Identification of type of FGR-
✔Symmetric
✔Asymmetric
▪ Identification of cause
✔Infections
✔Structural abnormalities
✔Aneuploidy
▪ Antenatal surveillance
✔Amniotic fluid assessment
✔Biophysical profile
Abdominal
circumference
⚫Most sensitive singleindicator of
FGR
⚫Optimal time to screen for FGR is
at 32 weeks
⚫the HC/AC ratio is > 1.0 before 32
weeks, 1.0 at 32-34 weeks and <
1.0 after 34 weeks.
⚫If the AC falls below the expected
curve, then FGR can be diagnosed
⚫When the AC & EFW < 10th
percentile, FGR can be diagnosed
accurately
⚫If FGR confirmed , Scan should
be repeated 2 weeks interval
33.
Estimated fetal
weight
Amniotic fluid
volume
⚫Theformula for estimating EFW
uses combination of BPD, HC, AC
& FL
⚫EFW less than 10th
percentile is
diagnostic for FGR
⚫ Amniotic fluid volume is usually
reduced in late FGR.
⚫ Vertical pocket of amniotic fluid
< 2 cm and amniotic fluid index
(AFI) less than 5 indicates
oligohydramnios and FGR.
34.
Head-to-
abdomen ratio
Femur length
⚫Inearly pregnancy HC is
larger than the AC
⚫At term AC>HC
⚫ But, in growth restricted
fetus with asymmetric FGR
HC>AC
⚫Femur length (FL) is
relatively spared in late FGR.
The normal FL/AC ratio is 22
from 21st weeks till term
and does not need accurate
gestation.
⚫ A ratio > 23.5 diagnosis FGR.
35.
Serial
observation of
biometric
growth pattern
(growth
velocity)
⚫Doneby using USG biometric
parameters.
⚫Growth curves should be based
on a homogenous fetal
population.
⚫Customized growth charts take
into consideration.
✔More accurate than population
based growth chart in diagnosis
of FGR & exclusion of
Constitutionally small fetus.
✔Adjustment for maternal height,
weight, parity, ethnic origin &
fetal sex, giving an individual
chart for every patient.
Aims of surveillance
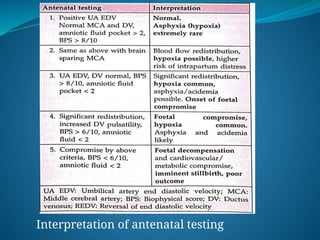
⚫THEPURPOSE OF FETAL MONITORING IS TO
IDENTIFY FETAL ACIDEMIA.
⚫IT HELPS THE OBSTETRICIAN TO PLAN TIMELY
DELIVERY PRIOR TO IRREVERSIBLE END
ORGAN DAMAGE AND INTRAUTERINE FETAL
DEATH.
FREQUENCY OF FETAL
MONITORING:WHAT RCOG
SAYS……
⚫UMBILICAL ARTERY DOPPLER
⮚It should be the primary tool in the
monitoring of IUGR fetuses.
⮚The use of this tool has shown to reduce
perinatal morbidity and mortality.
41.
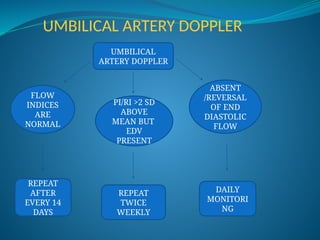
UMBILICAL ARTERY DOPPLER
UMBILICAL
ARTERYDOPPLER
FLOW
INDICES
ARE
NORMAL
PI/RI >2 SD
ABOVE
MEAN BUT
EDV
PRESENT
ABSENT
/REVERSAL
OF END
DIASTOLIC
FLOW
REPEAT
AFTER
EVERY 14
DAYS
DAILY
MONITORI
NG
REPEAT
TWICE
WEEKLY
42.
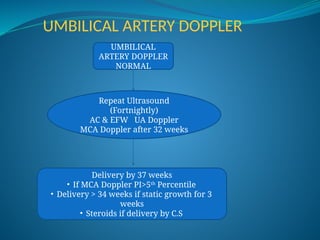
UMBILICAL ARTERY DOPPLER
UMBILICAL
ARTERYDOPPLER
NORMAL
Repeat Ultrasound
(Fortnightly)
AC & EFW UA Doppler
MCA Doppler after 32 weeks
Delivery by 37 weeks
• If MCA Doppler PI>5th
Percentile
• Delivery > 34 weeks if static growth for 3
weeks
• Steroids if delivery by C.S
43.
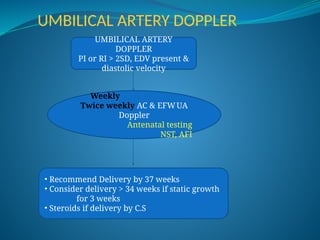
UMBILICAL ARTERY DOPPLER
UMBILICALARTERY
DOPPLER
PI or RI > 2SD, EDV present &
diastolic velocity
Weekly
Twice weekly AC & EFWUA
Doppler
Antenatal testing
NST, AFI
• Recommend Delivery by 37 weeks
• Consider delivery > 34 weeks if static growth
for 3 weeks
• Steroids if delivery by C.S
44.
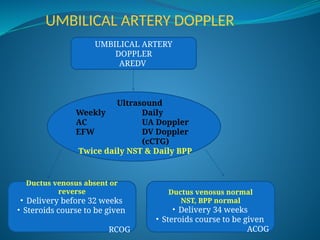
UMBILICAL ARTERY DOPPLER
UMBILICALARTERY
DOPPLER
AREDV
Ultrasound
Weekly Daily
AC UA Doppler
EFW DV Doppler
(cCTG)
Twice daily NST & Daily BPP
Ductus venosus normal
NST, BPP normal
• Delivery 34 weeks
• Steroids course to be given
ACOG
Ductus venosus absent or
reverse
• Delivery before 32 weeks
• Steroids course to be given
RCOG
45.
cardiotocography
⚫It should notbe used as the only form of
fetal surveillance in IUGR fetuses.
⚫Interpretation of CTG should be based on
short term fetal heart rate variation from
computerized analysis.
⚫ Short term variability 3 Higher rate of
≤
metabolic acidaemia and neonatal death
46.
Amniotic fluid volume
⚫Ultrasonographic assessment of amniotic fluid volume
should not be used as the only form of surveillance in IUGR
fetuses.
⚫ Interpretation of amniotic fluid volume should be based on
single deepest vertical pocket.
⚫ Limited information of oligoamnios to independently
predict perinatal mortality.
⚫ AFI<5 risk of CS
risk of low apgar score
But not academia
47.
Biophysical profile(BPP)
⚫It includesfour variables:
1. Fetal breathing movements
2. Fetal gross body movements
3. AFI
4. CTG
⚫Each assigned a score of 2 if normal and 0 if
abnormal.
48.
Biophysical profile(BPP)
⚫Reduced BPPscore is associated with lower
antepartum umbilical venous pH and high perinatal
mortality.
⚫But it is a time consuming test with high false negative
rates.
⚫It should not be used for fetal surveillance in preterm
IUGR fetuses
⚫ BPP as a surveillance tool No reduction in perinatal
mortality, risk of C.S
49.
Middle cerebral arteryDoppler
IN PRETERM IUGR FETUSES :
This test has limited accuracy in predicting fetal
acidaemia and should not be used to time delivery of
fetus.
IN TERM IUGR FETUSES :
In fetuses with normal umbilical artery Doppler , an
abnormal MCA Doppler ( PI < 5TH
PERCENTILE) has
moderate predictive value for fetal acidaemia.
This test can be used to time delivery.
50.
Ductus venosus andumbilical vein
doppler
⚫Patterns reflects atrial pressure-volume changes
in cardiac cycle.
⚫As FGR worsens , velocity reduces in the DV a-
wave owing to increased afterload and preload
as well as increased end diastolic pressure.
⚫A retrograde a-wave in DV doppler and pulsatile
umbilical vein doppler shows significant fetal
cardiac compromise.
51.
Ductus venosus doppler
⚫Hasmoderate predictive value for
acidaemia and adverse outcome.
⚫Should be used for surveillance in the
preterm SGA fetus with abnormal
umbilical artery doppler to time delivery.
54
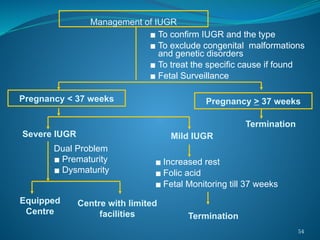
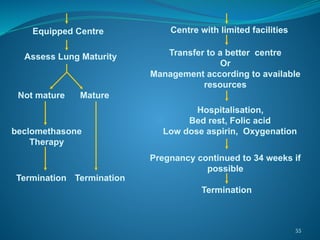
Management of IUGR
▪To confirm IUGR and the type
▪ To exclude congenital malformations
and genetic disorders
▪ To treat the specific cause if found
▪ Fetal Surveillance
Pregnancy < 37 weeks Pregnancy > 37 weeks
Severe IUGR Mild IUGR
Dual Problem
▪ Prematurity
▪ Dysmaturity
▪ Increased rest
▪ Folic acid
▪ Fetal Monitoring till 37 weeks
Termination
Equipped
Centre
Centre with limited
facilities
Termination
55.
55
Assess Lung Maturity
Notmature Mature
beclomethasone
Therapy
Termination Termination
Transfer to a better centre
Or
Management according to available
resources
Pregnancy continued to 34 weeks if
possible
Hospitalisation,
Bed rest, Folic acid
Low dose aspirin, Oxygenation
Termination
Equipped Centre Centre with limited facilities
56.
Prenatal Management
⚫Symmetric IUGR– need to consider
amniocentesis and TORCH analysis, along
with Maternal TORCH antibody titres.
⚫- Also need to look at Maternal Health – e.g.
illness such as chronic renal disease need to
be considered. This includes discouraging
tobacco use, and substance abuse as well as
regular checks through pregnancy
57.
⚫- Ongoing closeobservations, with U/S
(including doppler flows) and CTG’s.
⚫- Early delivery has to be considered based
upon the relative chance of fetal morbidity
and mortality in-utero to the chance of
morbidity and mortality of prematurity. Can
often be a difficult choice.
58.
Postnatal Management ofSGA baby:
⚫These babies handle stress of birth and post-
natal life poorly.
• Greater risk of stillbirth (4x)
• Greater risk of asphyxia (2x)
• Likely to have lower APGAR scores
• Higher incidence of meconium at delivery
• Risk of hypoglycaemia
• Risk of hypocalcaemia and hypomagnesaemia
• Risk of hypothermia
59.
At delivery:
⚫IUGR infantsare more prone to hypoxemia
during labor and delivery because of
uteroplacental insufficiency, and more prone
to cord compression due to lack of amniotic
fluid and a thin cord.
60.
⚫- A neonatalteam capable of managing
asphyxia and meconium aspiration
syndrome should be available at the time of
delivery.
⚫- Special attention should be addressed to
prevention of hypothermia and
hypoglycemia.
61.
Management after birth:
⚫SGAbabies are at risk as noted. Therefore
attention to WARM, PINK, SWEET &
INFECTION needed.
-Need to attend to basics of care – in
particular:
⚫ 1. Respiratory care – esp. with
meconium.
⚫ 2. Hypoglycemia due to low sugar
reserves and higher energy consumption –
esp. with cold stress.
62.
⚫ 3. Hypothermiadue to lack of
subcutaneous
fat and relatively high S.A to body weight
ratio.
⚫ 4. Beware infection – at risk as immune
system of babies is immature – being
SGA worsens this.
63.
⚫ 5. Polycythaemia– due to in-utero hypoxia.
Can cause venous thrombo-emboli and
can also worsen cerebral ischaemia and
perpetuate hypoglycaemia.
⚫ 6. Haemorrhage – can develop due to lack
of
liver coag factor production, and also may
have low platelets if TORCH.
⚫ 7. Management of asphyxia.
64.
Investigations of SGAbaby:
⚫Initially, babies need to be examined in a
warm environment.
⚫True blood glucose should be assessed at ½
to 1 hour of age, and pre-feeds for at least the
next 2 feeds. Feeds should be frequent (2-3
hourly initially).
65.
⚫ If babyjittery, then glucose and calcium
and magnesium must be checked.
>>Full blood count - 3 reasons
⚫ - polycythaemia
⚫ - platelet count
⚫ - white cells
66.
Nutrition:
- Important toestablish nutrition as early as
possible but be wary as hypoxia and
polycythaemia may have resulted in
diminished gut blood flow – risk of NEC.
- If delay in establishing enteral feeds, must
use TPN.
- Weight gain monitoring needed to ensure
sufficiency of caloric intake.
67.
- It iscommon that caloric intake in IUGR
⚫ infants will exceed the usual intake of 100-
⚫ 120 Kcal/kg/day, and daily weight gain will
⚫ exceed 25 g/day.
- Neurologic prognosis may relate directly to
⚫ restoring good nutrition. Poor subsequent
⚫ head growth bodes poorly for intellectual
⚫ development.
68.
Outcome for SGAbabies:
Increased mortality and morbidity as noted.
Long term outlook:
⚫ Neurological.
⚫ - IUGR infants have an increased risk of
long-term neurologic and behavioral
handicaps.
⚫ - Infants with ultrasonographic evidence of
delayed head growth before the
third trimester also have delayed neurologic
and intellectual development.
69.
⚫ - Ifcongenital anomalies and clinically
detected prenatal infections are excluded,
studies show normal IQ/DQ in most SGA
infants.
⚫ - Preterm IUGR infants have similar outcomes at
18-24 months of age, compared to AGA preterm
infants.
⚫ - Severe malnutrition in utero can decrease the
number of brain cells. Normally in the first 2
years of life there occurs a "spurt in brain
growth" during which the predominant change is
⚫ - increase in myelination.
70.
⚫ - Overall,IUGR infants have an increased
incidence of lower intelligence, learning
and behavioral disorders and neurologic
handicaps.
⚫- The long-term neurologic outcome in SGA
infants is related to the type of SGA,
severity and concomitant asphyxial insult.
⚫- Future handicap is dependent also on the
existence of perinatal complications such as
asphyxia, meconium aspiration syndrome,
hypothermia, hypoglycemia and
⚫ - polycythemia.
71.
Growth.
⚫ - AsymmetricIUGR infants have better growth
potential than symmetric IUGR infants who
typically have suffered a genetic, infectious
or teratogenic insult early in life.
⚫ - Asymmetric SGA infants capable of
achieving normal weight and proportions
within 6-12 months of birth.
⚫ - Symmetric SGA infants born often remain
shorter, lighter and have a smaller head
circumference throughout life.
72.
Other.
⚫ - Delayederuption of teeth and enamel
hypoplasia.
⚫ - Increased incidence of postnatal infections
possibly due to delayed humoral and
cellular immunity found .
⚫ - Risk of SIDS considerably greater (30%
of
SIDS cases occur in SGA infants) – reasons
behind SGA may account for this however
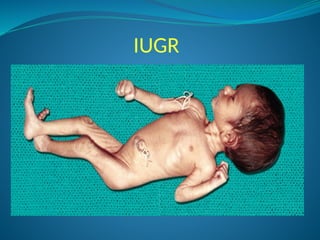
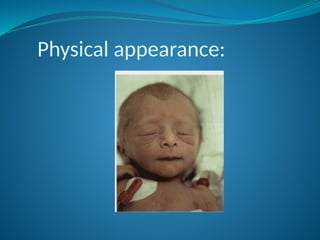
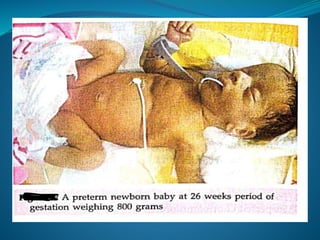
Physical appearance:
• Headsare disproportionately large for their
trunks and extremities
• Facial appearance has been likened to that of a
“wizened old man”.
• Long nails.
• Scaphoid abdomen
76.
• Signs ofrecent wasting
- soft tissue wasting
- diminished skin fold thickness
- decrease breast tissue
- reduced thigh circumference
• Signs of long term growth failure
- Widened skull sutures, large fontanelles
- shortened crown – heel length
- delayed development of epiphyses
• Comparison to premature infants,IUGR has brain and
heart larger in proportion to the body weight, in
contrast the liver, spleen, adrenals and thymus are
smaller.
77.
Complications of FGR
EarlyLate
⚫Metabolic complications
✔Hypothermia
✔Hypoglycemia
✔Hypocalcemia
✔Polycythemia
✔Hyperviscosity syndrome
• Complications d/t asphyxia
✔HIE
✔Persistent fetal circulation
✔Meconium aspiration syndrome
✔NEC, pulmonary
haemorrhage,electrolyte imbalance,
metabolic acidosis
⚫Slow growth at birth
⚫Increased chances of
retarded neurological,
intellectual , cognitive &
behavioural development
⚫Increased risk of
cardiovascular, T2DM&
hyperlipidemia in
adulthood( Barker’s
hypothesis)