USG & DOPPLER IN DIAGNOSIS &
MANAGEMENT OF IUGR
Dr. Shivshankar Lasune (MS Obstetrics and Gynaecology)
SGA(small for gestational age)
• Def: a fetus that has not attained or achieved a
particular biometric parameter threshold for
given gestational age.
• Most universally accepted parameter is EFW
10th centile.
• Other parameters AC, HC, BPD -5th centile.
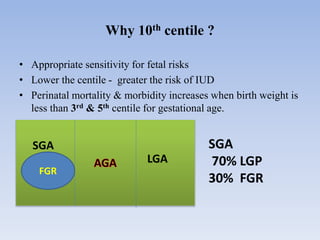
• Appropriate sensitivity for fetal risks
• Lower the centile - greater the risk of IUD
• Perinatal mortality & morbidity increases when birth weight is
less than 3rd & 5th centile for gestational age.
Why 10th centile ?
FGR
SGA
LGA
SGA
70% LGP
30% FGR
MATERNAL RISK FACTORS
• PIH
• Hypertension
• Diabetic vasculopathy
• APLA
• Renal disease
• Heart disease
• Asthma
• Hbpathy
• PKU
• Severe malnutrion
• Smoking
• Substance abuse
FETAL FACTORS
• Multiple gestation
• Infection
• Malformation
• Syndromes
PLACENTAL FACTORS
• Confined placental mosaicism
• Placenta previa
• Abruption
• Infarction
• Circumvallate placenta
• Morbid adherence
• Velamentous insertion
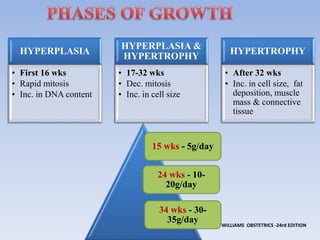
HYPERPLASIA
• First 16 wks
• Rapid mitosis
• Inc. in DNA content
HYPERPLASIA &
HYPERTROPHY
• 17-32 wks
• Dec. mitosis
• Inc. in cell size
HYPERTROPHY
• After 32 wks
• Inc. in cell size, fat
deposition, muscle
mass & connective
tissue
WILLIAMS OBSTETRICS -24rd EDITION
34 wks - 30-
35g/day
24 wks - 10-
20g/day
15 wks - 5g/day
GENETIC POTENTIAL
• Derived from both parents
• Mediated through factors like insulin like growth factor
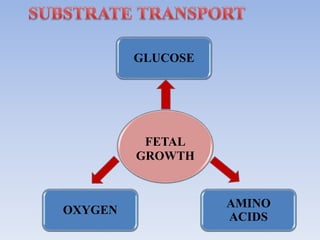
 SUBSTRATE SUPPLY
• Derived from placenta
• Depend upon Uterine & Placental vascularity
GLUCOSE
AMINO
ACIDS
OXYGEN
FETAL
GROWTH
Small for gestational age
Low growth profile
• Constitutionally small
• Serial monitoring
• Curve to nomograms or parallel
• Anatomy normal
• BPP/AF normal
• Doppler normal
• No treatment
• Smallness is not equal to sickness
Fetal growth restriction (fetal
cause)
• Syndrome/anomoly / aneuploidy
• Serial monitoring
• Curve drops off
• Anatomy normal/abnormal
• AF normal/ abnormal
• Doppler normal/ abnormal
• Karyotype, inf., markers of aneuploidy.
Small for GA
• Fetal growth restriction – classical placental cause
• Failure to attain genetic potential
• Serial monitoring
• Curves drops off (cuts across percentile)
• Body disproportion
• Anatomy normal
• BPP Normal / Abnormal
• Amniotic fluid Normal/ Abnormal
• Doppler Normal // Abnormal
• Surveillance for fetal growth and well being
• Optimisation of the time of delivery
• Decreases perinatal morbidity and mortality
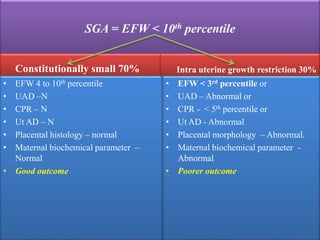
SGA = EFW < 10th percentile
Constitutionally small 70%
• EFW 4 to 10th percentile
• UAD –N
• CPR – N
• Ut AD – N
• Placental histology – normal
• Maternal biochemical parameter –
Normal
• Good outcome
Intra uterine growth restriction 30%
• EFW < 3rd percentile or
• UAD – Abnormal or
• CPR - < 5th percentile or
• Ut AD - Abnormal
• Placental morphology – Abnormal.
• Maternal biochemical parameter -
Abnormal
• Poorer outcome
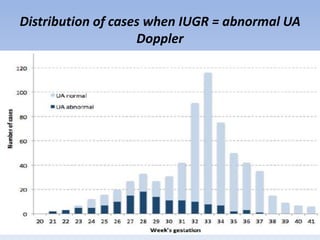
Distribution of cases when IUGR = abnormal UA
Doppler
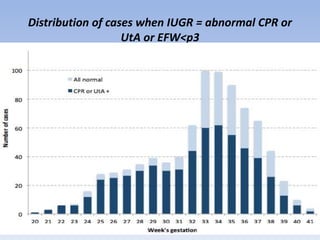
Distribution of cases when IUGR = abnormal CPR or
UtA or EFW<p3
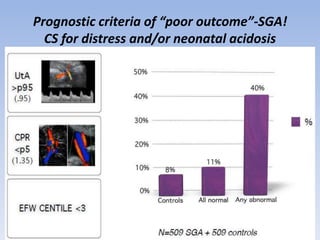
Prognostic criteria of “poor outcome”-SGA!
CS for distress and/or neonatal acidosis
FGR classification
• Early vs Late
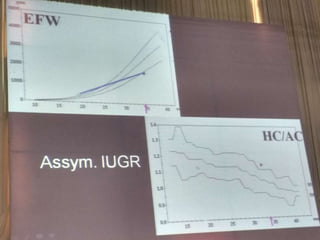
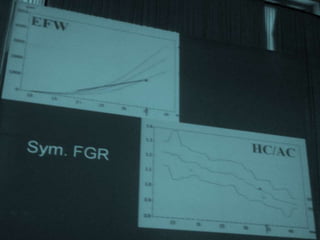
• Symmetric vs Asymmetric
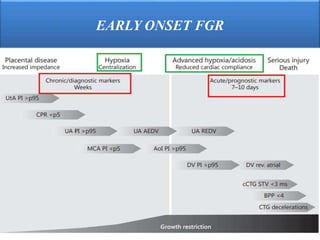
• Early onset FGR – Diagnosed before 34 weeks of GA
• Cellular hyperplasia is stunted
• Proportionally small fetus (EFW < 10th pct)
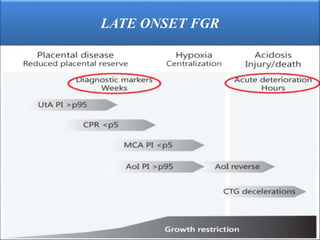
• Late onset FGR – Diagnosed after 34 weeks
• Cellular hypertrophy stunted
• Disproportionally small fetus (EFW< 10th pct)
• HC/AC and FL/AC ratios (assymetric)
• Substrate inadequacy
• Associated with maternal disease
Importance of early vs late
Cause – Severity – Counselling - Management
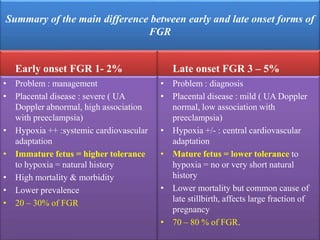
Summary of the main difference between early and late onset forms of
FGR
Early onset FGR 1- 2%
• Problem : management
• Placental disease : severe ( UA
Doppler abnormal, high association
with preeclampsia)
• Hypoxia ++ :systemic cardiovascular
adaptation
• Immature fetus = higher tolerance
to hypoxia = natural history
• High mortality & morbidity
• Lower prevalence
• 20 – 30% of FGR
Late onset FGR 3 – 5%
• Problem : diagnosis
• Placental disease : mild ( UA Doppler
normal, low association with
preeclampsia)
• Hypoxia +/- : central cardiovascular
adaptation
• Mature fetus = lower tolerance to
hypoxia = no or very short natural
history
• Lower mortality but common cause of
late stillbirth, affects large fraction of
pregnancy
• 70 – 80 % of FGR.
EARLY ONSET FGR
LATE ONSET FGR
Nomogram concept
• Portrays relation between two variables
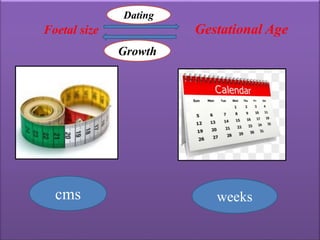
• In the context of fetal growth (Fetal size – cms or kg vs Time – weeks )
• Biological diversity / variability
• Continuous foetal growth
• Graph or chart forms
• Gives mean & confidence limits of a parameter for a given gestational age
• Standard deviation / percentile
Biological variability of foetal size
Ethical
Altitude
Social -
Economical
Racial
Birth order
• The variability of range in size for a given gestation increases with
advancing gestational age.
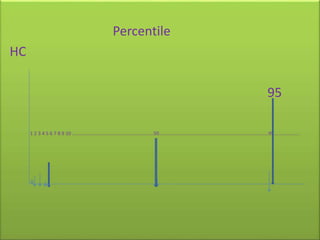
Percentile
HC
95
1 2 3 4 5 6 7 8 9 10 .............................................................50..................................................................................95...................
Percentiles
• Arrange 100 items in order of magnitude
• The 50th item has 49 items below & 50 above – 50th percentile
• The 95th item has 94 items below & 5 above – 95th percentile
• The 5th item has 4 items below & 95 above – 5th percentile
• +2SD = 97.72nd percentile -2SD = 2.28th percentile
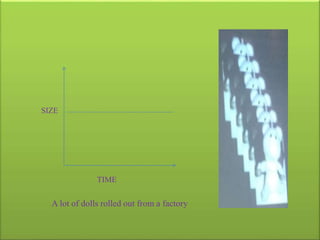
SIZE
TIME
A lot of dolls rolled out from a factory
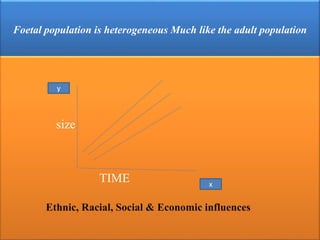
Foetal population is heterogeneous Much like the adult population
size
TIME
Ethnic, Racial, Social & Economic influences
y
x
TIME SIZE
SIZE TIME
Difference between the two graphs
x x
y y
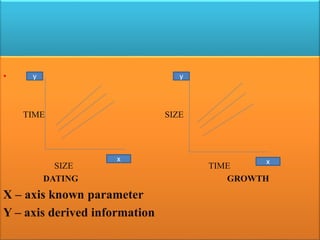
• Y Y
TIME SIZE
SIZE TIME
DATING GROWTH
X – axis known parameter
Y – axis derived information
x x
y y
Foetal size Gestational Age
cms weeks
Dating
Growth
US determination of GA – Dating scan
Good in the 1st trimister & 1st half of 2nd trimister.
First trimister - CRL up to 13wks + 6 days
Second trimister – BPD, HC, AC and FL
Dating is poor in the 3rd trimister
Reassignment is done if there is more than one week difference from
menstrual age. If not the Menstrual age is validated.
Once reassigned the GA is not changed during the rest of the gestation.
RELIABILITY OF US DATING
• +/- 8% of actual gestational age
• 10weeks +/- 6 days
• 24 weeks +/- 14 days
• 34 weeks +/- 20 days
Essence Of Diagnosis Of Fetal Growth
• Growth Normal / Abnormal
• Date – Determination of Gestational age
• Plot – Determination of growth
• Date – only once (earliest)
• Plot – more than once (growth)
• No diagnosis of fetal growth or disorders without plotting growth
curve.
Case study
• LMP – 14- 3- 16 ; Dating scan – 11- 5- 16 ; MA = 9 weeks.
• CRL = 2.7 cms = 9 weeks
• Hence US GA correlates with MA
• 2nd Scan 2- 8- 16
• GA = 8-9 weeks + interval = 9 wks + 11 wks = 20 wks.
• The biometry is then done and the results are :
• Parameter cms
• BPD 4.8
• HC 17.3
• AC 15.2
• FL 3.0
CASE STUDY
• The dating scan could be from another centre in your town / city / country
• 2nd scan – 2 – 8- 16
• GA = 8-9 weeks + interval = 9 wks + 11 wks = 20 wks.
• The biometry is then done and the results are :
• Parameter cms
• BPD 4.8
• HC 17.3
• AC 15.2
• FL 3.0
Case study
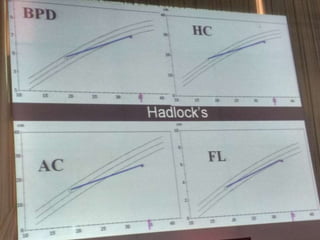
• Hence 2nd scan parameters fall within the confidence limits for 20weeks and
therefore the interval growth is normal.
• 3rd scan 12 – 11 – 2016
• GA = 9wks + interval = 9 wks + 26 weeks = 35 weeks
• The biometry is
• Parameters cms
• BPD 7.6
• HC 29.3
• AC 25.5
• FL 6.0
DOPPLER
Doppler effect:
• Change in the apparent frequency due to relative motion
between the source & the observer.
(Doppler probe & RBCs)
• When the sound wave strikes a moving target, the frequency
of sound waves reflected back is proportionate to the
velocity & direction of moving object.
• Used to determine the volume & rate of blood flow
through vessels.
Types:
1) CONTINUOUS WAVE DOPPLER:
Two crystals are used, one transmits & other receives wave
Used in M-mode echocardiography
1) PULSE WAVE DOPPLER:
Only one crystal that
Transmits-wait-Receives-wait-Transmits
Allows precise targeting & visualization of the vessel of interest
Have software that displays blood flow-
Towards transducer as RED
Away from transducer as BLUE
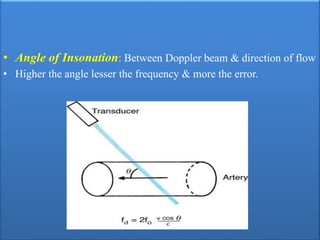
• Angle of Insonation: Between Doppler beam & direction of flow
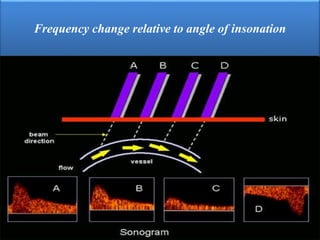
• Higher the angle lesser the frequency & more the error.
Frequency change relative to angle of insonation
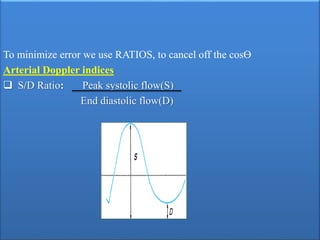
To minimize error we use RATIOS, to cancel off the cosϴ
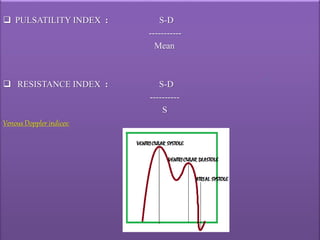
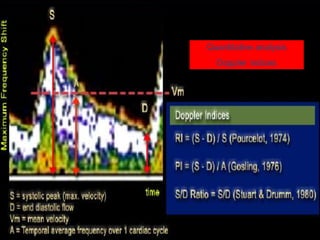
Arterial Doppler indices
 S/D Ratio: Peak systolic flow(S)
End diastolic flow(D)
 PULSATILITY INDEX : S-D
-----------
Mean
 RESISTANCE INDEX : S-D
----------
S
Venous Doppler indices:
Quantitative analysis
Doppler indices
• MATERNAL SIDE
Uterine artery
• PLACENTAL SIDE
Umbilical artery
• FETAL SIDE
Arterial: MCA, Aortic Isthmus
Venous: Ductus venosus, Hepatic vein, Umbilical vein
Fetal echocardiography
Doppler vessels to be studied
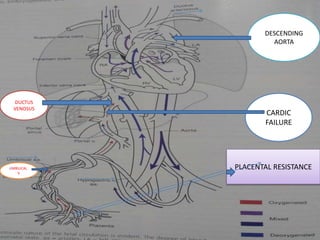
PLACENTAL RESISTANCE
CARDIC
FAILURE
UMBILICAL.
V
DUCTUS
VENOSUS
DESCENDING
AORTA
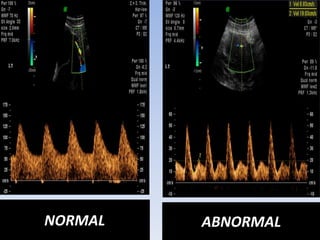
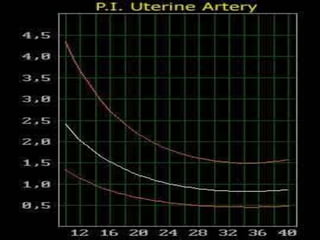
Uterine artery Doppler
• Its main use is in screening.
• Early diastolic notch in the uterine artery
@ 12-14 wks. suggest delayed trophoblastic invasion .
• Persistence of B/L notch beyond 24 wks confirms & indicates an
increased risk of Pre-eclampsia, Placental abruption & Early onset
IUGR.
• Increase impedence of flow in Uterine artery @ 16-20 wks was
predictive of superimposed pre-eclampsia developing in women with
chronic hypertension.
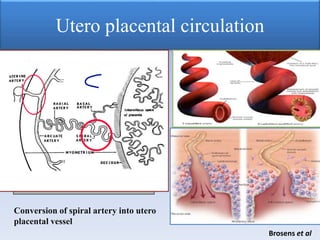
Utero placental circulation
Conversion of spiral artery into utero
placental vessel
Brosens et al
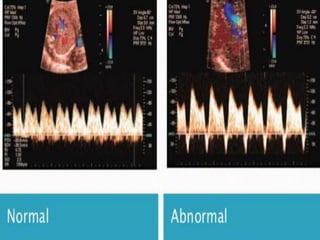
NORMAL ABNORMAL
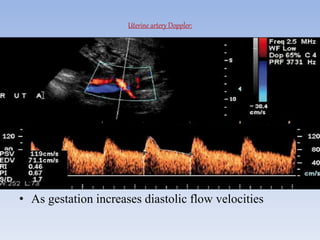
Uterine artery Doppler:
• As gestation increases diastolic flow velocities
•High diastolic flow velocities
• UMBILICAL ARTERY
• UA Doppler is the only measure that provides both diagnostic and
prognostic information for the management of FGR.
• On the one hand, increased UA Doppler PI has a great clinical value
for the identification of FGR, alone or combined in the CPR ratio.
• On the other hand, the progression of UA Doppler patterns to absent
or reverse end-diastolic flow correlates with the risks of injury or
death.
• When Umbilical artery Doppler are incorporated into management
algorithm of growth restricted fetus, perinatal death is reduced as
much as 29%.
• Umbilical artery Doppler becomes abnormal when at least 30% of
the fetal villous structure is abnormal.
• In extreme cases of growth restriction, end-diastolic flow may become
absent or even reversed (AREDF).
• AREDF occurs when 60-70% of the fetal villous structure is
abnormal.
• About ½ of the cases of AREDF are associated with aneuploidy or a
major anomaly
• Absent or reversed end-diastolic velocities, the end of the spectrum of
the abnormalities of the UA Doppler, have been reported to be present
on average 1 week before the acute deterioration.
• There is an association between reversed end-diastolic flow in the UA
and adverse perinatal outcome (with a sensitivity and specificity of
about 60%), which seems to be independent of prematurity.
• After 30 weeks the risk of stillbirth of a fetus with isolated
reversed end-diastolic velocities in the UA Doppler overcomes the
risks of premaurity.
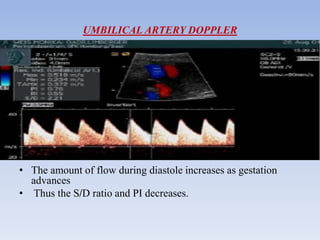
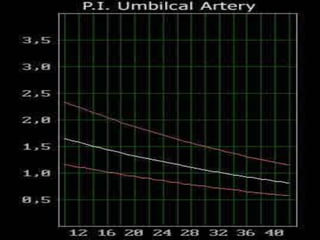
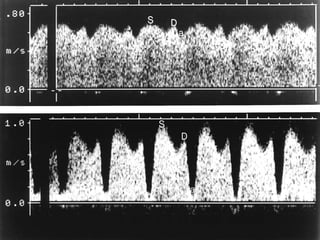
UMBILICAL ARTERY DOPPLER
• The amount of flow during diastole increases as gestation
advances
• Thus the S/D ratio and PI decreases.

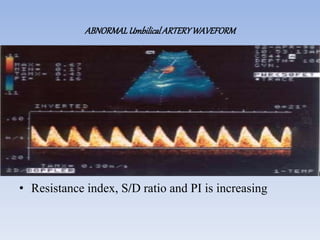
ABNORMALUmbilicalARTERYWAVEFORM
• Resistance index, S/D ratio and PI is increasing
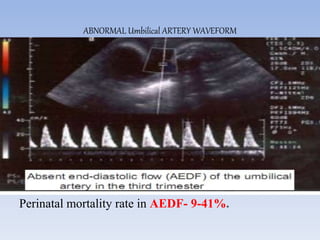
ABNORMAL Umbilical ARTERY WAVEFORM
Perinatal mortality rate in AEDF- 9-41%.
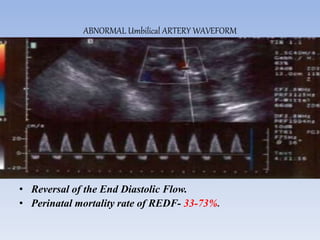
ABNORMAL Umbilical ARTERY WAVEFORM
• Reversal of the End Diastolic Flow.
• Perinatal mortality rate of REDF- 33-73%.
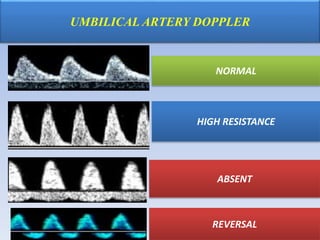
UMBILICAL ARTERY DOPPLER
Umbilical arteries
NORMAL
HIGH RESISTANCE
ABSENT
REVERSAL
MIDDLE CEREBRAL ARTERY DOPPLER
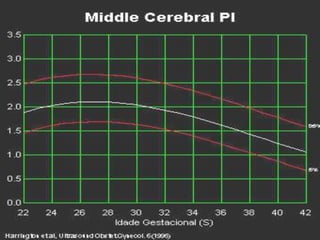
• Middle cerebral artery pulsatility index < 5th percentile is considered early stage
change of IUGR.
• The nadir of MCA PI is reached 14 days or more before fetal compromise.
• Normalisation of MCA PI
 The reversal of adaptation in growth restricted fetus is considered a poor
prognostic sign.
 Due to cerebral edema.
• MCA informs about the existence of brain vasodilatation, a surrogate marker of
hypoxia.
• Abnormal MCA PI had a six fold risk of emergency caesarean section for
fetal distress when compared with SGA fetuses with normal MCA PI.
• Abnormal MCA PI is associated with poor perinatal outcome and @ 2 years
neurological outcome.
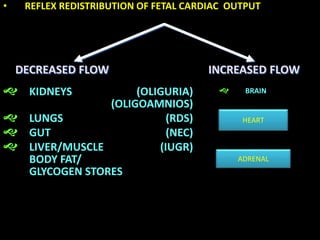
• REFLEX REDISTRIBUTION OF FETAL CARDIAC OUTPUT
 KIDNEYS (OLIGURIA)
(OLIGOAMNIOS)
 LUNGS (RDS)
 GUT (NEC)
 LIVER/MUSCLE (IUGR)
BODY FAT/
GLYCOGEN STORES
INCREASED FLOWDECREASED FLOW
 BRAIN
HEART
ADRENAL
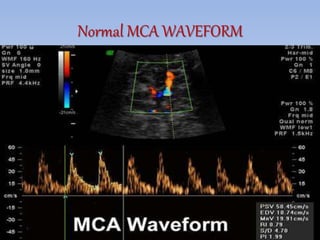
Normal MCA WAVEFORM
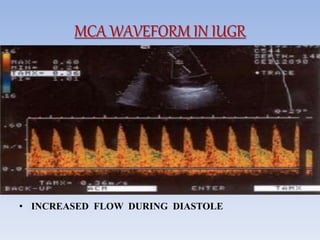
MCA WAVEFORM IN IUGR
• INCREASED FLOW DURING DIASTOLE
CEREBRO-PLACENTAL RATIO(CPR):
MCA Pulsatility Index
Umbilical A. Pulsatility Index
• The CPR is essentially a diagnostic index.
• It is more sensitive index for detecting poor perinatal outcome than
UA or MCA Doppler alone, the CPR is already decreased when its
individual components suffer mild changes but are still within normal
ranges.

• Abnormal CPR predicts neurobehavioral problems at 18 months of
age.
AORTIC ISTHMUS DOPPLER
 This vessel reflects the balance between the impedance of the brain
and systemic vascular systems.

 Strong association with both adverse perinatal and neurological
outcome.

 AoI precedes Ductus Venosus abnormalities by 1 week.
DUCTUS VENOSUS
• It is strongest single Doppler parameter to predict the short-term
risk of fetal death in early-onset FGR.
• DV flow waveforms become abnormal only in advanced stages of
fetal compromise.
• There is a good correlation of abnormal DV waveform with late- stage
acidemia at cordocentesis.
• Absent or reversed velocities during atrial contraction are
associated with perinatal mortality independently of the
gestational age at delivery, with a risk ranging from 40 to 100% in
early-onset FGR.
• In about 50% of cases, abnormal DV precedes the loss of short-term
variability (STV) in computerized cardiotocography (cCTG), and in
about 90% of cases it is abnormal 48–72 h before the biophysical
profile (BPP).
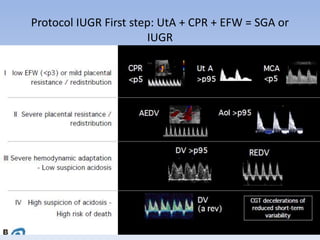
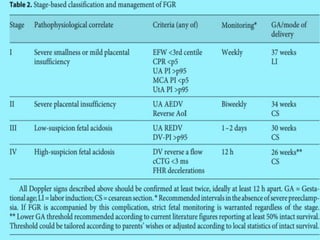
Protocol IUGR First step: UtA + CPR + EFW = SGA or
IUGR
STEROID PROPHYLAXIS
• RCOG
• Single course of antenatal corticosteroids to women between 24+0 to
34+6 weeks of gestation who are at risk of preterm delivery.
• Antenatal corticosteroids can be considered for women between 23+0
to 23+6 weeks gestation who are at risk of preterm delivery, decision
should made at senior level.
• IUGR Single course of antenatal corticosteroid should receive
between 24+0 to 35+6 weeks of gestation who are at risk of preterm
delivery.
• Antenatal corticosteroids should be given to all women for whom
elective LSCS planned before 39 weeks.
continue
• Single rescue course may be considered where initial course was
given at less than 26+0 weeks.
• In multifetal gestation single course of antenatal corticosteroids
should be given between 24+0 to 34+6 weeks gestation at risk of
preterm delivery.
• Regularly scheduled repeat courses or serial courses of antenatal
corticosteroids are not recommended.
ACOG
• Single course of antenatal corticosteroids should given to women
between 24+0 to 33+6 weeks of gestation at risk of preterm delivery.
(PPROM, MULTIPLE GESTATION, FGR)
• Also consider for 23 0/7 weeks if risk of preterm delivery within 7
days, based on family decision regarding resuscitation.
• Single course of corticosteroid should given between 34 0/7 to 36
6/7weeks at risk of preterm delivery within 7 days, who have not
received a previous course of corticosteroid.
• Single rescue course of antenatal corticosteroid should be considered
in women less than 34 0/7 weeks of gestation at risk of preterm
delivery within 7 days & prior course given more than 14days.
continue
• Rescue course should be provided as early as 7 days from the prior
dose, if clinically indicated.
• Regularly scheduled repeat courses or serial courses of antenatal
corticosteroids are not recommended.
• DOSAGE
• Inj. Betamethasone 12mg i.m 2 doses 24 hrs apart.
• Inj. Dexamethasone 6mg i.m 4 doses 12 hrs apart.
• Betamethasone most preferred to Dexamethasone
• Most effective 24 hrs after and up to 7 days after administration
second dose of antenatal corticosteroids.
ADVERSE EFFECT OF MULTIPLE DOSES OF STEROIDS
• Fetal growth restriction
• Reduced birth weight
• Reduced HC
• Delayed myelination of CNS
• Altered blood pressure soon after birth
• Increased insulin response to glucose challenge in early childhood.
• Behavioural disorders at 3 years of age.
• Placental infarction
• Adrenal gland insufficiency
• Perinatal morbidity & mortality of IUGR infants is 3-20 times greater
than normal infants.(IanDonalds)
• Risk is increased 3 times at 26 weeks compared with only a 1.13-fold
increased risk at 40 weeks.(Williams 24rd edition)
Antenatal Period:
• Oligohydraminos
• Fetal Distress
• IUD
During labour:
• Meconium aspiration
• Fetal distress
• Acidosis
• Still birth
Neonatal period:
• Hypoxic Ischemic Encephalopathy
• Persistent Fetal circulation
• Difficulty in temperature regulation
• Hypoglycemia
• Polycythemia
• Necrotising Enterocolitis
Childhood:
• Infectious Diseases
• Cerebral Palsy(4-6 times higher)
• Subtle impairment in cognitive improvement
• Educational underachievement
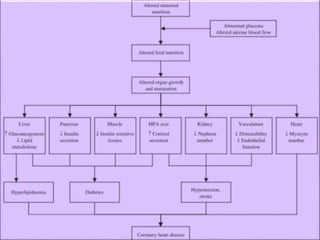
Long term:
Increase risk of 
• Coronary Heart Disease
• Hypertension
• Type II Diabetes Mellitus
• Dyslipidaemia
• Stroke
BARKERS HYPOTHESIS
David J P Barker
British epidemiologist
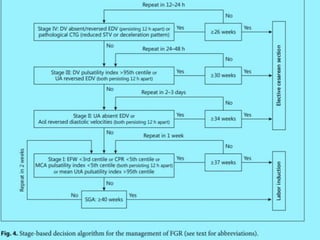
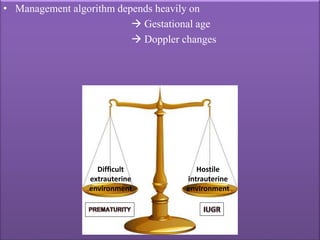
• Management algorithm depends heavily on
 Gestational age
 Doppler changes
Difficult
extrauterine
environment
Hostile
intrauterine
environment
THANK
YOU