





























DRUGS MODIFYING
BLOOD COAGULATION
Dr. Pravin Prasad
M.B.B.S., MD Clinical Pharmacology
Assistant Professor, Maharajgunj
MedicalCampus
6 February, 2020 (23 Magh, 2076),Thursday
A case scenario
 A 35 years male patient with impacted tooth
 Started tooth extraction
 Bleeding seenâ€Ļ..
īļ What would you do?
 By your experience, the bleeding was more
than expected
īļ What could be the reason?
Another case scenario
By the end of the class, BDS II
Year students will be able to:
☞ List drugs used to achieve coagulation and anti-
coagulation
☞ Describe the pharmacology of heparin and
warfarin
☞ Explain the pharmacological basis of protamine
and vitamin K
By the end of the class, BDS II
Year students will be able to:
☞ Describe the pharmacology of anti-platelet
drugs (aspirin, dipyridamole)
☞ Describe the pharmacology of thrombolytic
agents (streptokinase, urokinase)
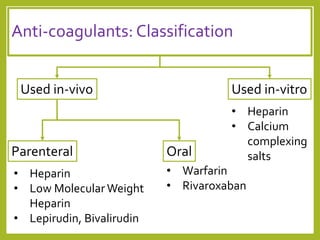
Anti-coagulants: Classification
Used in-vivo Used in-vitro
Parenteral Oral
â€ĸ Heparin
â€ĸ Low Molecular Weight
Heparin
â€ĸ Lepirudin, Bivalirudin
â€ĸ Warfarin
â€ĸ Rivaroxaban
â€ĸ Heparin
â€ĸ Calcium
complexing
salts
Heparin
 Non-uniform mixture of straight chain
mucopolysaccharides
 Effective both in vivo and in vitro
 Heparin binds with and activatesAnti-thrombin
III (AT III)
 Increases interaction betweenAT III and
clotting factors (IIa, Xa, IXa, XIa, XIIa and XIIIa)
 Intrinsic and common pathway affected (aPTT
prolonged)
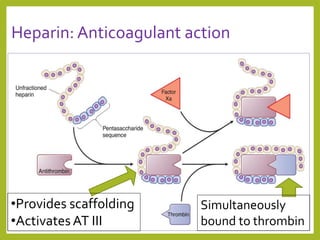
Heparin: Anticoagulant action
â€ĸProvides scaffolding
â€ĸActivatesAT III
Simultaneously
bound to thrombin
Heparin: Other actions
 Antiplatelet action
īļ Seen at higher dose
īą Prolonged bleeding time
 Lipaemia clearing
īļ Seen at lower concentration
īļ Releases Lipoprotein lipase from vessel wall
īļ Hydrolyses triglycerides of chylomicron and very
low density lipoprotein to free fatty acids
īļ Passes into tissue  turbid post-prandial
lipaemic plasma becomes clear
 Absorption:
īļ Oral: not absorbed (large, highly
ionised)
īļ Intravenous: instant action (bolus,
continuous infusion)
īļ Subcutaneous: inconsistent (every 8-12 hrs)
 Distribution:
īļ Does not cross blood brain barrier, placenta
 Metabolised in liver (heparinise)
 Excreted in urine
Heparin: Pharmacokinetics
Heparin: Adverse effects
 Bleeding due to overdose
īļ Proper monitoring required (aPTT)
 Thrombocytopenia
īļ Discontinue heparin
 Osteoporosis on long term use
 Hypersensitivity reactions (rare)
Heparin: Contraindications
 Bleeding disorders
 History of heparin induced thrombocytopenia
 Severe hypertension, threatened abortion,
piles, g.i. ulcers
 Subacute bacterial endocarditis, large
malignancies, tuberculosis
Heparin: Contraindications
 Ocular and neurosurgery, lumbar puncture
 Chronic alcoholics, cirrhosis
 Renal failure
 Caution:
īļ Co-administered antiplatelet drugs
īą Aspirin, Clopidrogrel
Coumarin derivatives
 Warfarin, Nicomalone
īļ Active in vivo only
īļ Acts indirectly by:
īą Interfering with synthesis of vitamin K
dependent clotting factors
īą Lowers plasma level of clotting factors in
dose dependent manner
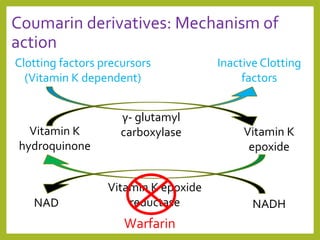
Coumarin derivatives: Mechanism of
action
Clotting factors precursors
(Vitamin K dependent)
Inactive Clotting
factors
Vitamin K
hydroquinone
Vitamin K
epoxide
Vitamin K epoxide
reductase NADHNAD
Îŗ- glutamyl
carboxylase
Warfarin
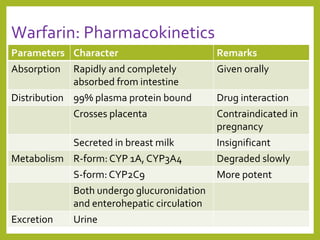
Warfarin: Pharmacokinetics
Parameters Character Remarks
Absorption Rapidly and completely
absorbed from intestine
Given orally
Distribution 99% plasma protein bound Drug interaction
Crosses placenta Contraindicated in
pregnancy
Secreted in breast milk Insignificant
Metabolism R-form: CYP 1A, CYP3A4 Degraded slowly
S-form:CYP2C9 More potent
Both undergo glucuronidation
and enterohepatic circulation
Excretion Urine
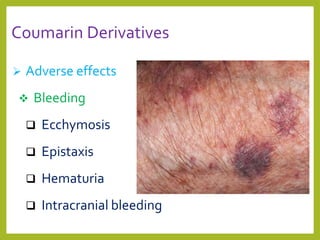
Coumarin Derivatives
 Adverse effects
īļ Bleeding
īą Ecchymosis
īą Epistaxis
īą Hematuria
īą Intracranial bleeding
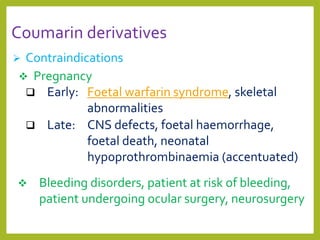
Coumarin derivatives
 Contraindications
īļ Pregnancy
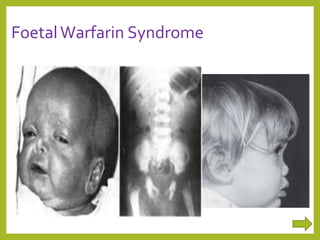
īą Early: Foetal warfarin syndrome, skeletal
abnormalities
īą Late: CNS defects, foetal haemorrhage,
foetal death, neonatal
hypoprothrombinaemia (accentuated)
īļ Bleeding disorders, patient at risk of bleeding,
patient undergoing ocular surgery, neurosurgery
FoetalWarfarin Syndrome
Warfarin: Interactions
 Increased effect
īļ Prolonged
antibiotic therapy,
malnutrition,
malabsorption
īļ Liver disease,
chronic alcoholism
īļ Hyperthyroidism
 Decreased effect
īļ Pregnancy
īļ Nephrotic Syndrome
īļ Genetic warfarin
resistance
Anticoagulants: Indications
 Deep vein thrombosis, pulmonary embolism
 Myocardial infarction
īļ Prevent mural thrombi at the site of infarction
and venous thrombi in leg veins
 Unstable angina
īļ Along with aspirin
 Rheumatic heart disease, atrial fibrillation
īļ Prevent thromboembolism
īļ Prior attempting rhythm conversion
Anticoagulants: Indications
 Embolic stroke (cerebrovascular disease)
 Vascular surgery, prosthetic heart valves, retinal
vessel thrombosis, extracorporeal circulation,
haemodialysis
īļ Prevent thromboembolism
 Defribrination syndrome
īļ Heparin (paradoxical effect)
Protamine
 Strongly basic, low molecular weight protein
 Administered intravenously
īļ 1 mg for 100 U of heparin
 More commonly used when heparin action needs
to be terminated rapidly, e.g. after cardiac or
vascular surgery
 Has weak anticoagulant in the absence of heparin
 Adverse effects: Hypersensitivity reaction, flushing
and breathing difficulties on rapid i.v. injection
Coagulants: Classification
 Coagulants
īļ Fresh whole blood/ plasma
īļ Vitamin K: K1 , K3
īļ Miscellaneous: Fibrinogen, Antihaemophilic factor
 Local Haemostatics
īļ Styptics: fibrin, thrombin, vasoconstrictors,
astringents
īļ Sclerosing agents
 Anti-fibrinolytics
īļ Epsilon amino-caproic acid (EACA),Tranexamic acid
Vitamin K
 K1:
īļ Phytonadione, Phylloquinone
īļ Plant source, Fat soluble
 K3:
īļ Synthetic
īļ Fat soluble: Menadione, acetomenaphthone
īļ Water soluble: Menadione sod. bisulphite,
menadione sod. diphosphate
Vitamin K
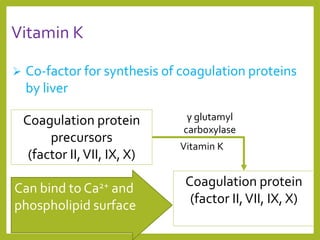
 Co-factor for synthesis of coagulation proteins
by liver
Coagulation protein
precursors
(factor II,VII, IX, X)
Coagulation protein
(factor II,VII, IX, X)
Îŗ glutamyl
carboxylase
Vitamin K
Can bind to Ca2+ and
phospholipid surface
Vitamin K
 Absorption
īļ Fat soluble: lymphatics of intestine, bile salts
required
īļ Water soluble: portal blood
 Distribution:Temporarily stored in liver
 Metabolism: Liver (side chain cleavage and
glucuronidation)
 Excretion: bile and urine
Vitamin K: Uses
 Newborn baby
īļ Prevent/treat haemorrhagic disease of the
newborn
 Overdose of oral anticoagulants
īļ Phytonandione
 Prolonged high dose salicylate therapy
Vitamin K: Uses
 Dietary deficiency
 Prolonged antimicrobial therapy
 Obstructive jaundice
 Malabsorption syndromes
īļ Sprue, Regional ileitis, Steatorrhoea
 Liver disease
Vitamin K: Adverse effects
 Oral, intra-muscular injection:
īļ Safe
 Intra-venous injection:
īļ severe anaphylactoid reaction by emulsified
preparation
 Menadione,Water soluble K3:
īļ Haemolysis in dose-dependent manner
īļ Kernicterus in newborn
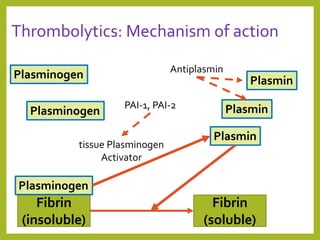
Fibrinolytics (Thrombolytics)
 These are drugs used to lyse thrombi/clot to
recanalize occluded blood vessels (mainly
coronary artery)
 Work by activating the natural fibrinolytic
system
 Includes:
īļ Streptokinase, Urokinase
īļ Alteplase,Tenecteplase, Reteplase
Thrombolytics: Mechanism of action
Plasmin
tissue Plasminogen
Activator
Fibrin
(insoluble)
Fibrin
(soluble)
Plasminogen
Plasminogen
Plasminogen
Plasmin
Plasmin
Antiplasmin
PAI-1, PAI-2
Streptokinase
 Obtained from β haemolytic Streptococci group
C
 Combines with circulating plasminogen
molecules
īļ Gets activated
īļ Breaks plasminogen to plasmin (in a limited
manner)
 Non-fibrin specific
Streptokinase
 Drawbacks:
īļ Less effective than newer agents
īļ Increased risk of bleeding
īļ Inactivated by antibodies to past streptococcal
infection
īļ Is antigenic
īļ Cannot be used second time
īļ Fever, hypotension, arrhythmia
Urokinase
 Commercially prepared from cultured human
kidney cells.
 Activates plasminogen directly and has a
plasma tÂŊ of
10–15 min
 It is nonantigenic
 Side effects: Fever
 Indicated in patients in whom streptokinase has
been given for an earlier episode
Thrombolytics: Uses
 Acute myocardial infarction
 Deep vein thrombosis
 Pulmonary embolism
 Stroke
 Peripheral arterial occlusion
Thrombolytics: Contraindications
1. H/o Intracranial haemorrhage
2. H/o Ischaemic stroke in past 3 months
3. H/o Head injury in past 3 months
4. Intracranial tumour/vascular abnormality/
aneurysms
5. Active bleeding/bleeding disorders
6. Peptic ulcer, esophageal varices
7. Any wound or recent fracture or tooth extraction
8. H/o major surgery within 3 weeks
9. Uncontrolled hypertension
10. Pregnancy
Anti-platelet drugs (anti-thrombotic
drugs)
 These are drugs which interfere with platelet
function and are useful in the prophylaxis of
thromboembolic disorders.
 More useful in arterial thrombosis
 Includes:
īļ Aspirin, Dipyridamole
īļ Ticlopidine,Clopidogrel, Prasugrel
īļ Abicximab, Eptifibatide,Tirofiban
Aspirin
 Acetylsalicylic acid gets converted to salicylic
acid
 Antiplatelet action:
īļ Small doses irreversibly inhibitsTXA2 synthesis
by platelets.
īą Interferes with platelet aggregation
īą Lasts for 5-7 days
Aspirin: Pharmacokinetics
 Absorption:
īļ Stomach and small intestines
īļ Microfining the drug particles and inclusion of an
alkali (solubility is more at higher pH) enhances
absorption
īļ Rapidly deacetylated in the gut wall, liver, plasma
and other tissues to release salicylic acid which is
the major circulating and active form.
Aspirin: Pharmacokinetics
 Distribution
īļ Slowly enters brain but freely crosses placenta
 Metabolism
īļ Conjugated with glycine (major pathway) and
glucuronic acid
 Excretion
īļ Glomerular filtration as well as tubular secretion
Aspirin: Uses
 As antiplatelet aggregatory
īļ 75-150 mg in post-MI patient
īļ 100-150 mg in new onset angina
Dipyridamole
 Initially introduced as vasodilator
 Phosphodiesterase inhibitor:
īļ Increases platelet cAMP
īļ Potentiated PGI2  antiaggregatory effect
 Also been used to enhance the antiplatelet
action of aspirin
Conclusion
 Heparin effects intrinsic and common pathway of
clot formation
īļ Inactivates both Xa and Iia
 Warfarin is active only in vivo
 Always check in patients for possible warfarin
(drug) interaction
 Protamine sulfate reverses the action of heparin
 Vitamin K reverses the action of warfarin
Conclusion
 Streptokinase and urokinase acts by activating
plasminogen
 Aspirin acts by inhibitingCOX-1 (decreasing
formation of thromboxaneA2 in platelets)
 Dipyridamole shows antiplatelet effect by
inhibiting breakdown of cAMP
īļ Is a phosphodiesterase enzyme inhibitor
Any questions??
 Thank you!