THERAPEUTIC DRUG
MONITORING
DIGOXIN
Blessy Rachel Thomas
Vth Pharm D
INTRODUCTION
• Digoxin is the primary cardiac glycoside.
• It is used in the
-treatment of CHF because of its
inotropic effects on the myocardium.
- treatment of atrial fibrillation because
of its chronotropic effects.
-treatment of atrial flutter because of its
positive inotropic effects
-treatment paroxysmal atrial tachycardia
because of its positive inotropic effects
PHARMACOLOGICAL ACTIVTY
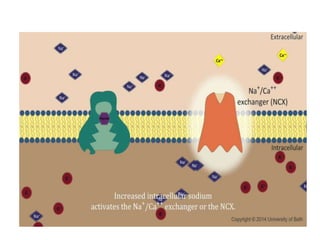
• The positive inotropic effects is caused by the
binding to Na+ K+ ATPase activated adenosine
phosphate → inhibition of Na pump →
decreased transport of Na+ out of myocardial
cells ( increased intracellular conc ) → calcium
entry and decrease calcium elimination →
enhanced myocardial contractility.
THERAPEUTIC RANGE
• 0.8-2 ng/ml
CLINICAL PHARMACOKINETICS/
PHARMACODYNAMICSCONSIDERATIONS
• Pharmacodynamic considerations for tachyarrhythmias and
systolic heart failure as follows:
 Tachyarrhthmias
• Narrow therapeutic range.
• Used to control the ventricular response rate, particular in
CHF.
• Ventricular rate control usually achieved over 24 hours.
• A loading dose given in divided doses because of a long
distribution half-life.
• Possible to use higher doses to control rate in the acute
setting.
 Systolic heart failure
• Decreases frequency of hospitalization for
exacerbation of heart failure.
• No improvement in cardiovascular mortality.
• Serum concentration achieved in mortality trial
at the lower end of therapeutic range.
• Necessary to maintain serum conc in the mid to
low therapeutic range ( < 1.5 ng/ml ).
• Edema and cardiac output changes with severity
of heart failure may alter pharmacoknetic
parameters.
PHARMACOKINETIC CONSIDERATION:
ABSORPTION
• Completely absorbed from the gut.
• In some patients, absorption may be decreased
due to digoxin inactivation by gut bacteria
(Eubacterium lenium).
• Also by some drugs like antacids, cholestyramine,
tetracycline, neomycin and kaolin.
• For patients with normal absorption:
Digoxin tablets: 50-90%
Digoxin elixir: 80%
Digoxin liquid filled capsules: 100%
DISTRIBUTION
• Digoxin distributes into lean body tissue but not
appreciably into adipose or fatty tissues.
• For this reason ideal body weight should be used to
dose digoxin.
• 20-30% bound to albumin.
• Vd : 6- 7 l/kg
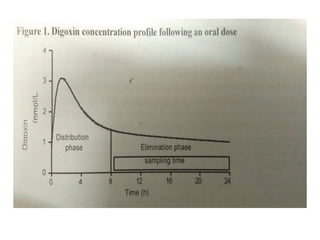
• Distributive phase is 6 to 8 hour.
• Two clinical implications:
-loading doses of digoxin need to be
administered in divided doses 6 hour apart.
-serum digoxin levels should be determined at
least 8 hr after administration.
METABOLISM
• Takes place in stomach and intestine.
• Involves :
Deglycosylation
Reduction of the lactone ring
Oxidation
Epimerization
Conjugation to polar metabolites
CONTINUE...
• In Stomach,
Gastric acid
removes digitoxose sugars of digoxin
formation of deglycosylated congeners
• In intestine,
Intestinal flora
results in metabolism of digoxin
to its reduced form, dihydrodigoxin
Continue…..
Digoxin overdose
decreased sodium pump activity
Hyperkalemia
ELIMINATION
• Excreted largely unchanged in the urine.
• Small proportion is cleared by nonrenal routes,
biliary excretion and intestinal clearence.
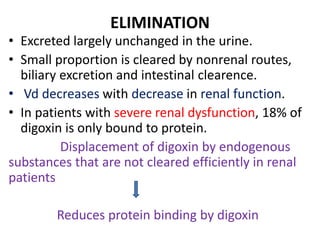
• Vd decreases with decrease in renal function.
• In patients with severe renal dysfunction, 18% of
digoxin is only bound to protein.
Displacement of digoxin by endogenous
substances that are not cleared efficiently in renal
patients
Reduces protein binding by digoxin
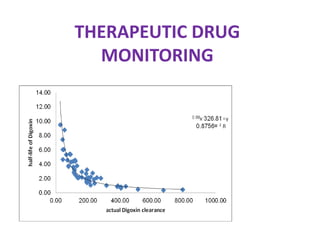
• Systemic clearance (Clt):
Clt = (1.01 × Clr ) + Clm
Clr = renal clearence
= 0.927 × Cr Cl ( ml/min/1.73 m2 )
Clm = metabolic clearence
= 36 ml /min ÷ 1.73 m2 (in resolved or
no history of heart disease)
= 20 ml /min ÷ 1.73 m2 ( with severe
heart disease)
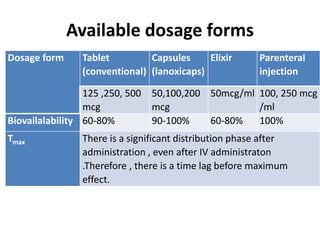
Available dosage forms
Dosage form Tablet
(conventional)
Capsules
(lanoxicaps)
Elixir Parenteral
injection
125 ,250, 500
mcg
50,100,200
mcg
50mcg/ml 100, 250 mcg
/ml
Biovailalability 60-80% 90-100% 60-80% 100%
Tmax There is a significant distribution phase after
administration , even after IV administraton
.Therefore , there is a time lag before maximum
effect.
THERAPEUTIC DRUG
MONITORING
INDICATIONS
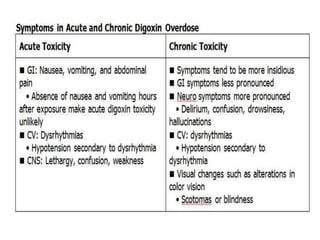
• Confirmation of toxicity
• Assessing the effect of factors altering
pharmacokinetics
• Therapeutic failure
• Medication compliance
Confirmation of toxicity
• Need to measure digoxin conc for
Confirmation of toxicity due to the low
therapeutic index.
• Therapeutic range: 1.0-2.5 nmol/l
• Risk of toxicity : Over 2.6 nmol/l
Assessing the effect of factors altering
pharmacokinetics
• No. of factors influence the pharmacokinetics.
• Renal function is the major contributor.
• Cockroft gault equation will result in an appropriate
dose.
• P-glycoprotein is involved in the transport of digoxin into
the body and out of the body in the renal tubules.
• Mutation within this gene →alter bioavailability and
renal clearence.
• drug interaction → affect serum conc of digoxin by
competitive inhibition of P-glycoprotein.
Therapeutic failure
• TDM is useful to detect patients with
-low digoxin conc
-who may benefit from increased dose
-who develop toxicity symptoms from an
increased dose
• Results from the “PROVED” and “RADIANCE” trials,
suggest that digoxin concentrations between 0.6 &
1.2 nmol/l may be efficacious and less pro-
arrythmic ,than conc with heart failure.
APPROPRIATE SAMPLING TIME
• Digoxin is well absorbed, with peak serum
conc occurring within one hour.
• Because of large Vd , digoxin concentrates in
the tissues, with the active site within
myocardial and other cells.
• Redistribution from serum to tissue takes at
least 8 hours.
Samples taken within 8 hours
falsely shows elevated conc
results in inappropriate dose reduction
thus, measure digoxin conc after 8 hours
(when conc have steady state)
shows linear
• Digoxin elimination is predominantly renal in nature
(fraction excreted: 0.6-0.9)
• Depends on glomerular filtration and p-glycoprotein
mediated active tubular secretion.
• A long t1/2 of atleast 30 hour results in steady state
conc taking at least 5 days to be achieved (in normal
renal function patient).
• In the elderly and patients with renal impairment,
elimination is diminished and t1/2 prolonged.
• In this case , steady state may take several weeks to
achieve.
DOSE ADJUSTMENT
• When the conc is above the therapeutic
range, the dose should be reduced even in the
absence of obvious toxicity →patient is at risk
of arrhythmias.
• Also, toxicity can occur with conc within the
therapeutic range → result from several
known factors that change tissue sensitivity to
digoxin and alter the therapeutic index.
Increased sensitivity Decreased sensitivityy
Hypokalemia
Hypercalcaemia
Hypothyroidism
Hypoxia/acidosis
Hyperkalemia
Hypocalcaemia
Hyperthyroidism
Neonates
DOSING
• Jeliffe method is a simple method for
calculating loading and maintenance dose.
• Produce dosing regimens that will provide a
serum digoxin level of approx 2.0 ng/ml.
• it is important to adjust the dose empirically if
significant drug-disease or drug-drug
interactions are present.
 LOADING DOSE ( TOTAL BODY STORES)
LD ( TBS) = (10 mcg/kg)×IBW(kg)
F
• Half of this loading dose is administered
intravenously or orally.
• The remaining dose is divided equally and
administered at 6-h interval (1/2 dose , ¼ dose, ¼
al 6 h intervals).
• This is necessary to account for the slow
distribution , half life of the drug.
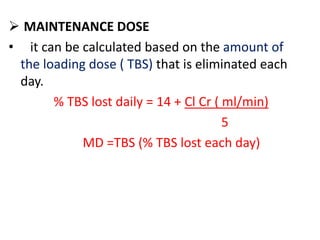
 MAINTENANCE DOSE
• it can be calculated based on the amount of
the loading dose ( TBS) that is eliminated each
day.
% TBS lost daily = 14 + Cl Cr ( ml/min)
5
MD =TBS (% TBS lost each day)
• Example:
JL is a 68 year old male who is admitted to the
hospital for atrial fibrillation. During his
hospitalization he is converted to normal sinus
rhythm b quinidine. His past medical history includes
CHF . His thyroid function is normal. His weight is 84
kg (IBW = 73 kg) and his estimated creatinine
clearance is 68 ml/min. what would be an
appropriate oral loading and maintenance dose?
• LD = 10 × 73 =TBS = 1043 mcg(1.4 mg)
0.7
Administer 0.5 mg orally, then 0.25 mg in 6 h, then
0.25 mg in 6 h.
MD= TBS (%TBS LOST EACH DAY)
% TBS LOST EACH DAY =14 + 68 ml/min = 27.6%
5
MD = 1.04 mg (27.6%) = 0.29 mg
Because JL is also on quinidine the MD would be
decreased by 50%.
MD = 0.15 or 0.125 mg/day
ANALYTICAL METHODS
• Enzyme Immunoassay ( EIA)
• Cloned Enzyme Donor Immunoassay (CEDIA)
• Enzyme Multiplied Immunoassay (EMIT)
• Fluorescence Polarisation Immunoassay (FPIA)
Enzyme Immunoassay ( EIA)
• In this method, the label on the tracer is an
enzyme.
• The catalytic properties of enzymes allows the
detection and quantitation of small quantities of
the drug.
Cloned Enzyme Donor Immunoassay
(CEDIA)
• The method uses an antibody to detect the
drug to be measured.
• A label is used to measure the binding reaction.
• It uses genetically engineered fragment of the
enzyme β-galactosidase as the label.
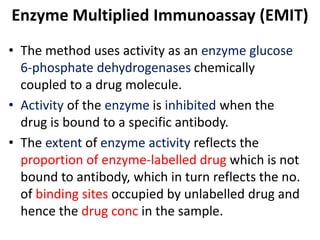
Enzyme Multiplied Immunoassay (EMIT)
• The method uses activity as an enzyme glucose
6-phosphate dehydrogenases chemically
coupled to a drug molecule.
• Activity of the enzyme is inhibited when the
drug is bound to a specific antibody.
• The extent of enzyme activity reflects the
proportion of enzyme-labelled drug which is not
bound to antibody, which in turn reflects the no.
of binding sites occupied by unlabelled drug and
hence the drug conc in the sample.
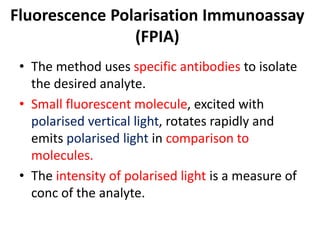
Fluorescence Polarisation Immunoassay
(FPIA)
• The method uses specific antibodies to isolate
the desired analyte.
• Small fluorescent molecule, excited with
polarised vertical light, rotates rapidly and
emits polarised light in comparison to
molecules.
• The intensity of polarised light is a measure of
conc of the analyte.
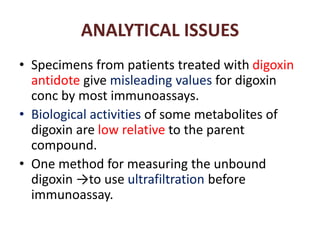
ANALYTICAL ISSUES
• Specimens from patients treated with digoxin
antidote give misleading values for digoxin
conc by most immunoassays.
• Biological activities of some metabolites of
digoxin are low relative to the parent
compound.
• One method for measuring the unbound
digoxin →to use ultrafiltration before
immunoassay.
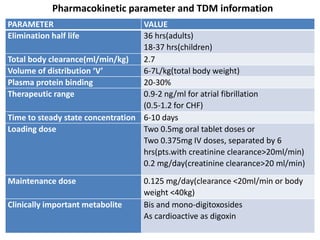
Pharmacokinetic parameter and TDM information
PARAMETER VALUE
Elimination half life 36 hrs(adults)
18-37 hrs(children)
Total body clearance(ml/min/kg) 2.7
Volume of distribution ‘V’ 6-7L/kg(total body weight)
Plasma protein binding 20-30%
Therapeutic range 0.9-2 ng/ml for atrial fibrillation
(0.5-1.2 for CHF)
Time to steady state concentration 6-10 days
Loading dose Two 0.5mg oral tablet doses or
Two 0.375mg IV doses, separated by 6
hrs(pts.with creatinine clearance>20ml/min)
0.2 mg/day(creatinine clearance>20 ml/min)
Maintenance dose 0.125 mg/day(clearance <20ml/min or body
weight <40kg)
Clinically important metabolite Bis and mono-digitoxosides
As cardioactive as digoxin