Monika Singh
Assistant Professor
PSIT, Kanpur
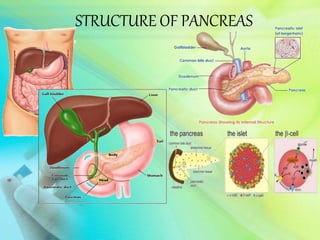
STRUCTURE OF PANCREAS
Pancreas – elongated tapered organ – lies behind stomach – connects with duodenum –
small tube – pancreatic duct – narrow end – called tail – extends to left side of body
towards spleen
Types of pancreas
 Exocrine: Secrete – digestive enzymes – secreted into ducts network – joining
main pancreatic duct – runs same length of pancreas
 Endocrine: Consists – islets of Langerhans – secretes hormones into bloodstream
Types of pancreatic cells
Alpha cells: Glucagon (15–20% of total islet cells)
Beta cells: Insulin and amylin (65–80%)
Delta cells: Somatostatin (3–10%)
PP cells (gamma cells): Pancreatic polypeptide (3–5%), Vasoactive Intestinal
Peptide (VIP)
Epsilon cells: Ghrelin (<1%)
PANCREAS
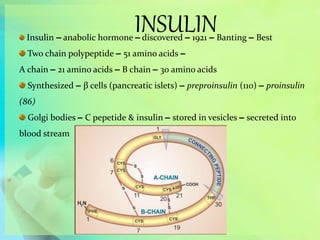
INSULINInsulin – anabolic hormone – discovered – 1921 – Banting – Best
Two chain polypeptide – 51 amino acids –
A chain – 21 amino acids – B chain – 30 amino acids
Synthesized – β cells (pancreatic islets) – preproinsulin (110) – proinsulin
(86)
Golgi bodies – C pepetide & insulin – stored in vesicles – secreted into
blood stream
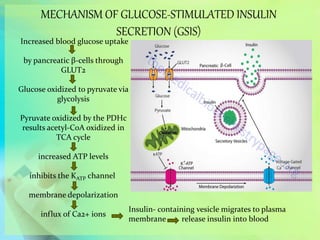
MECHANISM OF GLUCOSE-STIMULATED INSULIN
SECRETION (GSIS)
Increased blood glucose uptake
by pancreatic β-cells through
GLUT2
Glucose oxidized to pyruvate via
glycolysis
Pyruvate oxidized by the PDHc
results acetyl-CoA oxidized in
TCA cycle
increased ATP levels
inhibits the KATP channel
membrane depolarization
influx of Ca2+ ions
Insulin- containing vesicle migrates to plasma
membrane release insulin into blood
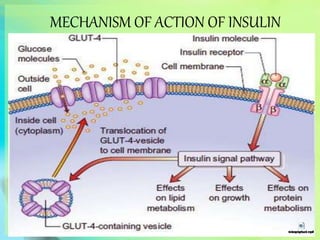
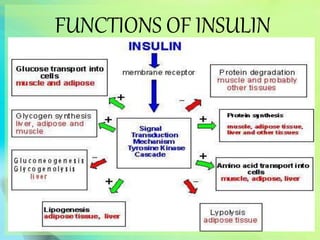
MECHANISM OF ACTION OF INSULIN
FUNCTIONS OF INSULIN
DIABETES
Diabetes – metabolic disorder – causing excessive – thirst & large amounts –
urine production
Diabetes :
Diabetes mellitus – metabolic disorder – characterized by chronic
hyperglycemia – disturbances – carbohydrate – fat – protein metabolism –
defects in insulin secretion – insulin action – or both
Diabetes insipidus (DI) – characterized – excessive thirst & severely
dilute urine excretion (large amounts) – humans – neurological form – central
DI (CDI) – arginine vasopressin (AVP) /anti-diuretic hormone (ADH)
deficiency – second type – nephrogenic diabetes insipidus(NDI) – kidney or
nephron dysfunction – caused – ADH insensitivity – kidneys or nephrons
Diabetes mellitus
Diabetes insipidus
Diabetes mellitus Classification
Type-I diabetes/ IDDM (Insulin Dependent Diabetes Mellitus)
Immune mediated
Idiopathic
Type-II diabetes / NIDDM (Non-Insulin Dependent Diabetes Mellitus)
Gestational diabetes mellitus
Other specific types
Genetic defects of β-cell function
Genetic defects in insulin action
Diseases of the exocrine pancreas
TYPE-I DIABETES MELLITUS / IDDMType 1 Diabetes mellitus (T1D) – known – formerly – insulin-dependent diabetes –
juvenile diabetes – diabetes mellitus form – results from autoimmune destruction –
beta cells (pancreas) – producing insulin
Characterized by hyperglycemic patients – absolute deficiency of the insulin
hormone
Lifelong insulin injections – require – survival
Usually develops – children and adolescents (although can occur later in life)
Patients are at increased risk of developing microvascular and macrovascular
complications.
Etiology: β cell destruction – pancreatic islets – Type 1A: Autoimmune antibodies –
destroy β cells – detectable in blood – Type 1B: Idiopathic cause—no β cell antibody
found
Circulating insulin levels – low or very low – all type 1 cases – patients – more prone
to ketoacidosis or coma – less common – low degree – genetic predisposition
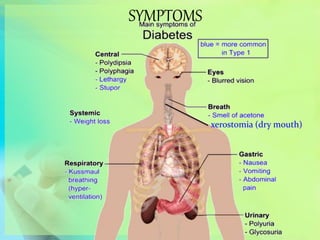
SYMPTOMS
xerostomia (dry mouth)
TYPE-II DIABETES MELLITUS / NIDDM
Formerly named – non-insulin-dependent diabetes mellitus (NIDDM) – over 90%
cases – type-II DM
Characterized by hyperglycemia – defect – pancreatic insulin secretion – insulin
resistance
Patients – higher risk – microvascular & macrovascular complications
No loss or moderate reduction – β cell mass – insulin in circulation – low – normal or
even high – no anti-β-cell antibody demonstrable – has high degree of genetic
predisposition – generally has a late onset (past middle age)
Etiology
β cell gluco-receptor abnormality
Down regulation – insulin receptor
Excess hyperglycaemic hormone/ obesity
TREATMENT REGIMENDIABETES MELLITUS TYPE I / IDDM
TYPE II / NIDDM
Insulin injection
Oral Hypoglycemic drugs
Enhanced insulin secretion
Sulfonylureas (KATP channel blockers)
First generation: Tolbutamide
Second generation: glibenclamide, glyburide,
Glipizide
Third generation: Glimeperide
Meglitinide/phenylalanine analogue
Repaglinide, nateglinide
Glucagon-like peptide-1 (GLP-1) receptor agonists
Exenatide, liraglutide
Dipeptidyl peptidase-4 (DPP-4) inhibitors
Sitagliptin, vildagliptin
Overcome insulin resistance
Biguanide (AMPK activator): Metformin
Thiazolidinediones (PPARƔ activator): Pioglitazone
α- glucosidase inhibitors: Miglitol, acarbose
Amylin analogue: pramlintide
Dopamin receptor-D2 receptor agonist: Bromocriptin
Sodium-glucose cotransport-2 (SGLT-2): Dapagliflozin
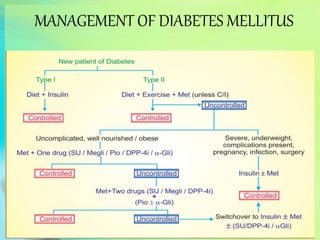
MANAGEMENT OF DIABETES MELLITUS
SULFONYLUREAS (KATP CHANNEL
BLOCKERS)
Sulfonylureas – organic compounds – medicinal & agricultural use –
antidiabetic drugs – type-II diabetes mellitus management
First generation
Tolbutamide
Second generation
Glipizide
Gliclazide
Glibenclamide
Third generation
Glimepiride
Fourth generation (light-dependent)
JB253
JB558
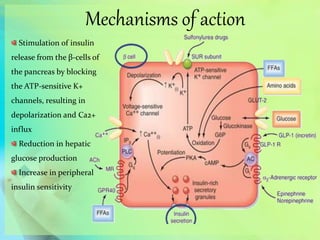
Stimulation of insulin
release from the β-cells of
the pancreas by blocking
the ATP-sensitive K+
channels, resulting in
depolarization and Ca2+
influx
Reduction in hepatic
glucose production
Increase in peripheral
insulin sensitivity
Mechanisms of action
CLINICAL USES
Diabetes Mellitus Type 2 (Higher
Glucose Levels Than Recommended
Hba1c Level >6.5%)
Neonatal diabetes (rare)
ADVANTAGES
Long acting – duration of action ~ 24
hrs
Lower incidence of hypoglycaemia.
Complete gastrointestinal absorption
Generally well tolerated
SIDE EFFECTS
Hypoglycemia
Trembling or shaking
Nervousness or anxiety
Sweating, fatigue &tiredness
Lightheadedness or dizziness
Headache
Fast heart rate or palpitations
Weight gain
Hyper-insulinemia
Non specific side effects
Headache
Nausea
Dizziness
Weakness
Hypersensitivity
Anaphylaxis
Angioedema
Stevens-Johnsons syndrome
BIGUANIDE
Class of drugs – function as oral antihyperglycemic drugs – for diabetes
mellitus – or prediabetes treatment
Metformin
First-line medication for the treatment of type 2 diabetes
Only currently available biguanide – classed as insulin sensitizer
Decreases insulin resistance
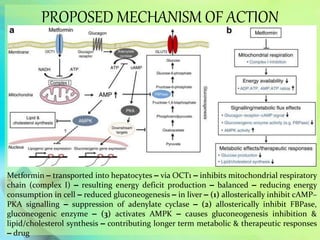
PROPOSED MECHANISM OF ACTION
Metformin – transported into hepatocytes – via OCT1 – inhibits mitochondrial respiratory
chain (complex I) – resulting energy deficit production – balanced – reducing energy
consumption in cell – reduced gluconeogenesis – in liver – (1) allosterically inhibit cAMP–
PKA signalling – suppression of adenylate cyclase – (2) allosterically inhibit FBPase,
gluconeogenic enzyme – (3) activates AMPK – causes gluconeogenesis inhibition &
lipid/cholesterol synthesis – contributing longer term metabolic & therapeutic responses
– drug
METFORMIN ACTIONS
CLINICAL USES
Type 2 diabetes mellitus
Polycystic ovary syndrome/ Infertility
Gestational diabetes
Prediabetes
ADVANTAGES
Nonhypoglycaemia
Weight loss promoting
Modestly reduce hyperlipidemia
Prevent diabetic macrovacsular & microvascular complications
No acceleration of β- cell exhaution/ failure in type-II diabetes
Can be combined – oral/ injectable antidiabetics
SIDE EFFECTS
Abdominal pain
Anorexia
Bloating
Nausea
Metallic taste
Diarrhoea (mild)
Tiredness
Lactic acidosis
Vitamin B12 deficiency (long term use)
CONTRAINDICATIONS
Renal disease
Hepatic disease
Acute myocardial infarction
Severe infection
Diabetic ketoacidosis
Congestive heart failure history
Alcohol abuse history
THIAZOLIDINEDIONE
PIOGLITAZONE: Proposed
Mechanism of Action
Stimulates the nuclear
receptor peroxisome proliferator-
activated receptor gamma (PPAR-
γ) and to a lesser extent PPAR-α
↑ insulin sensitivity in muscle
and adipose tissue
Inhibit hepatic gluconeogenesis
CLINICAL USES
Diabetes mellitus type 2 (T2DM)
Non-alcoholic steatohepatitis (fatty liver)- experimental
ADVANTAGES
Well tolerated
Nonhypoglycaemia
SIDE EFFECTS
Edema
Weight gain
Headache
Myalgia
Anaemia (mild)
Cardiovascular
Fractures
CONTRAINDICATED
Liver diseases
Congestive Heart Failure
Pregnancy