Complications of Total Hip
Replacement
Dr Humayun Israr
Resident Orthopaedic Surgery
DHQ Teaching Hospital, Sahiwal
Complications Related to Anaesthesia
Spinal:
 Time & Failure
 Haematoma which can lead to cord compression
 Spinal Headache ( PDPH)
 Chemical Meningitis
 Loss of bladder function post operatively
 Spinal Nerve Injury (less than 0.1%)
 CoRd Damage due to incorrect placement
General:
 PONV
 Malignant hyperthermia due to inhalational gases and suxamethonium
 Drowsiness
 death
Intra-operative
Nerve Injury:
 Primary (.5 %) sciatic nerve is most commonly damaged in posterior Approach andlateral approach is associated with damage to the lateral femoral
cutaneous nerve or superior gluteal nerve.
 The patient should wear a knee immobilizer or hinged knee brace with drop locks for walking to prevent knee buckling when the quadriceps remains
weak.
 Abductor weakness with trendelenberg gait may result from gluteal nerve injury.
 Patients with persistent sciatic nerve injury should have the foot supported to prevent fixed equinus deformity.
 Late exploration of sciatic nerve may be considered if recovery is not present by 6 weeks. Or if a mass of cement or transacetabular screw is compressing
the nerve.
 Revision (3.5 %)
 DDH (2.3%)
 Obturator nerve injury can occur from extruded cement, mechanical injury from retractors or screws placed in anteroinferior quadrant . Persistent groin
pain is only symptom.
Intra Operative
Fat Embolism:
 Associated with pressurization of Cement in femoral canal specially in elderly patients.
 Hypoxia and hypotension
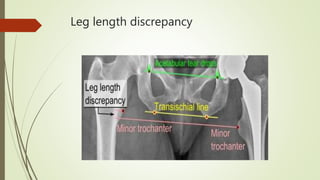
Leg length discrepancy
 Upto 1 cm is tolerated.
 Limb length is mostly increased than decreased.
Leg length discrepancy
Leg length Discrepancy
 Lengthening may be result from inadequate resection of bone from the femoral neck, use of a prosthesis with a long neck or inferior displacement of
center of rotation of acetabulum.
 Patients with unacceptable leg lengths must be carefully evaluated for cause if surgical treatment is to be successful.
 Leg length discrepancy can be minimized by both careful preoperative planning and intra operative measurement.
Intra Operative
Vascular Injuries:
 Major vascular injuries following THR are rare (0.04 % in primary THR and 0.2 % in revision THR)
 There is a 15 % chance of amputation if vessel injury occurs.
 Measures taken to protect femoral nerve can also protect femoral vessels.
 The retractor shouldbe blunt tipped and not allowed to slip anteromedial to the iliopsoas.
 Removal of soft tissues and osteophytes from inferior surface of acetabulum can cause bleeding from obturator vessels.
Post operative
Dislocation:
 Incidence 3% , reduced significantly with posterior capsular repair and repair of short external rotator or abductor tendon to greater trochanter with non
absorbable sutures.
 Risk increased with revision, female sex, advanced age, previous hip fracture.
 Reduced with appropriate head neck size and head neck ratio
 Alignment
Acetabulum: anteversion 10-20, abduction 35 to 45
Femoral: Anteversion 5-15
Femoral component anteversion is checked intraoperatively by comparing the axis of prosthetic femoral neck with the shaft of the tibia when the knee is flexed
to 90 degree. If anteversion is more than 15 then anterior dislocation is more likely and if it is less than 5 then posterior dislocation is more likely.
Post Operative
Infection:
 Incidence 1%, mortality 2.5%
Tsukyama Classification:
 Early < 4 weeks
 Chronic > 4 weeks
 Acute haematogenous infection: onset more than 1 month after surgery, acute onset of symptoms in previously well
patients , distant source of infection.
 Positive intra Operative cultures: positive cultures obtained at the time of revision for supposedly aseptic conditions.
Post Operative
Management:
 Antibiotic therapy
 Debridement and irrigation of hip with component retention
 Debridement and irrigation of hip with component removal
 One stage or two stage re implantation of total hip arthroplasty
 Arthrodesis
 Amputation
Post Operative
DVT:
 It can be a complication of any surgery but risk is significantly increased in orthopaedics specially hip and knee surgery.
 A deep clot is formed in veins and it can even embolize to lungs to cause fatal pulmonary embolism.
 Warfarin and lmwh , factor x A inhibitors and aspirin can be given as prophylaxis. Ideal agent is not clearly established.
 Early mobilization can be preventive
 Anaesthesia technique also plays a role . Risk is greater with general anaesthesia 27% than regional anaesthesia 13%.
 Enography is the most sensitive and specific test for detection.
Haematoma Formation:
 Risk factors include anti platelet therapy, anti inflammatory medication, blood dyscrasias,coagulopathies.
 Common sources of bleeding are branches of obturator vessels , the first perforating branch of profunda femoris, branches of femoral vessels near
anterior capsule, branches of superior and inferior glute0al vessels.
Post-operative
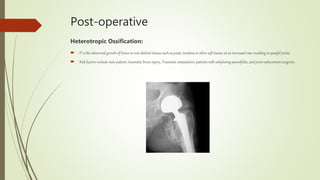
Heterotropic Ossification:
 IT is the abnormal growth of bones in non skeletal tissues such as joints, tendons or other soft tissues at an increased rate resulting in painful joints.
 Risk factors include male patient, traumatic brain injury, Traumatic amputation, patients with ankylosing spondylitis, and joint replacement surgeries.
Post Operative
 Anterior or anterolateral approach is also associated with increased risk.
 Calcification may be seen by 3rd or 4th post operative week.
 Nsaids have shown to reduce the risk of bone formation.
 Surgery to remove heterotropic bone is rarely indicated because excision is difficult and pain is not much of a problem.
Aseptic loosening of hip:
 It is the failure of formation of a bond between bone and implant in the absence of infection.
 In all cases suspected of loosening of one or both components the possibility of infection must be considered.
Post Operative
 At each post operative visit the radiographs shouldbe carefully evaluated for changes in components, the cement if present, the bone and the interfaces
between them.
Causes of loosening of cemented femoral component
 The following are technical problems that contribute to stem loosening
1. Failure to remove soft cancellous bone from medial surface of the femoral neck
2. Failure to provide a cement mantle of adequate thickness around the entire stem
3. Removal of all trabecular bone from the canal, leaving a smooth surface with no capacity for cement intrusion
4. In adequate quantity of cement
5. Failure to pressurize the cement
6. Failure to position the component in a neutral or centralized position in the femoral canal.
Post Operative
Cement less femoral Loosening
Fixation is Classified as
 Bony ingrowth: no subsidence minimal radiopaque line formation
 Stable: No subsidence but radiopaque line formation
 Unstable : Progresive subsidence with radio-opaque lines surrounding it
Cemented acetabular components
Technical problems encountered include;
 INADEQUate support of the cup by the surrounding bone and cement
 Failure to remove all the cartilage , loose bone fragments, fibrous tissue
 Failure to pressurize the cement
 Failure to spread the cement all around the outer surface of cup
 Movement of the cup or mantle while the cement is hardening
 Movement of relatively undersized cup while it is held in large cement mantle.
Post operative
Cementless Acetabular components:
 Engh , griffin and Marx classified these components as stable, probably unstable when progressive radiolucencies are present and unstable when
measurable migration is present.
Fractures:
 Femoral and acetabular fractures can occur.
 Femoral fractures often require treatment and acetabular fractures often go un noticed and can be managed conservatively.
 Risk factors for peri prosthetic fractures include female patients, advanced age, osteoarthritis , osteoporosis or bony deformity.
Post Operative
Post Operative
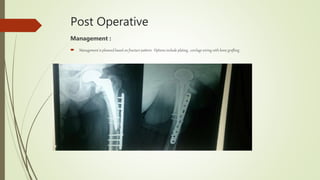
Management :
 Management is planned based on fracture pattern. Options include plating , cerclage wiring with bone grafting .
Post Operative
Osteolysis:
 It can occur in loose and even well fixed cemented and non cemented prosthesis.
 It is recognized that particles of metal, cement and polyethylene can produce osteolysis, either alone or in concert.
 the mechanism of osteolysis can be seen from three perspectives
1. The generation of wear particles
2. Their migration to periprosthetic surface
3. The response to the particulate debris
 The pattern of osteolysis depends upon the implant design.
 Femoral component with limited or non circumferential porous coating are subject to early development of distal cortical lesions because debris may gain
access to distal parts of implant bone ingrowth through channels.
 Acetabular components with thin polyethylene, incongruity, with poor fixation are more likely to early pelvic osteolysis.
Post Operative:
 When femoral or acetabular osteolysis is detected radiographs shouldbe maintained at 3 to 6 monthly intervals.
 Loose implants and large lytic lesions are clear indications for surgery.
 If fixation of implant has been compromised by osteolysis, complete revision surgery becomes unavoidable.
 If implant remains stable despite bone loss, then bone grafting with retention of implant is recommended.
Complications of total hip replacement final