EVALUATION OF REGULATORY
AND SCIENTIFIC REQUIREMENT
OF
BIOEQUIVALENCE STUDY
Md. Mizanur Rahman Miajee
Assistant Manager, Regulatory Affairs
The ACME Laboratories Ltd.
1
BASIC CONTENTS OF THE PRESENTATION
 What is a generic drug? What is quality? Myths about generic drugs, generic
review process
 What is BE/BA
 Requirements for submission of BA/BE data
 Biowaiver criteria (How to get Biowaiver)
 Approaches of BE study
 How to select CRO
 Types of BE study (Fasting/Fed, Pilot/Pivotal)
 Review of pilot study results for designing pivotal protocol
 Fasting & fed BE study
 Relevant definition & abbreviation
 How to choose reference product (name and strength)
 Pre-audit requirement and major component of CRO QMS inspection
 Basic criteria of test product Flow chart of a complete BE study with tentative
timeline 2
BASIC CONTENTS OF THE PRESENTATION
 Study design (parallel & crossover)
 Study design for highly variable drug
 Basic inclusion & exclusion criteria
 General consideration (screening, housing, dosing, sample collection)
 Sample size estimation
 Selection of investigators
 Washout period calculation
 Study monitoring/inspection
 Dropout, protocol deviation and ADR management
 Plasma sample management
 Bioanalytical and other deficiencies
 Acceptance criteria
 Reporting of results
 Pharmacokinetic information in the submission
 Statistical information in the submission
 Archiving of study report 3
WHAT IS A GENERIC DRUG?
A copy of a brand-name drug, which must have the:
 Same quality
 Same safety
 Same strength
WHAT IS QUALITY?
 For a Drug Product, Typically the Patient Cannot “See” Quality! The Patient Expects
Quality!!
Patients and caregivers assume that their drugs:
 Are safe, efficacious, and have the correct identity
 Deliver the same performance as described in the label
 Perform consistently over their shelf life
 Are made in a manner that ensures quality
 Will be available when needed
4

MYTHS ABOUT GENERIC DRUGS
 Generics…are not as safe
 Generics…are not as potent
 Generics…take longer to act in the body
 Generics…are made in sub-standard manufacturing facilities
5
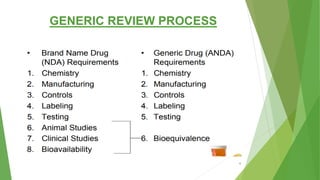
GENERIC REVIEW PROCESS
6
THREE EXPECTATION/ RIGHT OF
CONSUMER
1. Safety : Can be ensured by BE study (Pre marketing)
and Pharmacovigilance (Post Marketing)
1. Efficacy: Therapeutic Equivalence (BE)
2. Quality: Ensured by CMC data submitted to Drug Authority
(Authority’s approval upon evaluation) & Testing
7
BIOEQUIVALENCE
The rate and extent of absorption (Bioavailability) of the drug do
not show a significant difference from the rate and extent of
absorption of the listed drug when administered at the same
molar dose of the therapeutic ingredient under similar
experimental conditions in either a single dose or multiple doses.
8
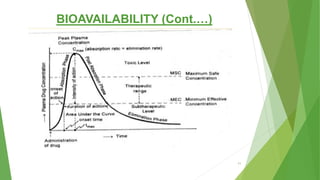
BIOAVAILABILITY
The extent and the rate to which a drug substance or its therapeutic
moiety is delivered from a pharmaceutical form into the general circulation
 Rate: Cmax and Tmax
 Extent: AUC
 Cmax: Cmax is the maximum observed concentration, Cmax tends to
have higher variability, Need adequate sampling time-points
 AUCt: measure of the total exposure of drug to the body up to the
last sampling time
 AUCinf: theoretical measure of the total exposure of drug to the
body from administration till all the drug is eliminated
 Tmax: Time of Cmax 9
BIOAVAILABILITY (Cont.…)
 Absolute bioavailability
Amount of the drug available to the body or system. This is
measured as a ratio between the AUC after intravenous
administration and AUC oral administration. It should be a figure
less than 1 since it is assumed that 100% of the drug is available to
the body after iv administration. (e.g: 0.96, 0.98 )
 Relative bioavailability
Relative bioavailability measures the bioavailability (estimated as
the AUC) of a formulation (A) of a certain drug when compared with
another formulation (B) of the same drug, usually an established
standard.
10
BIOAVAILABILITY (Cont.…)
11
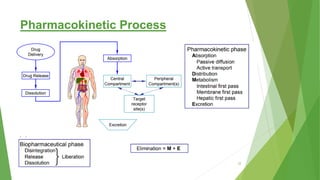
Pharmacokinetic Process
12
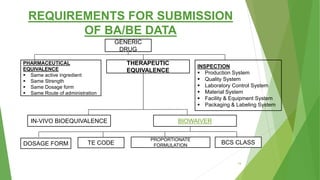
REQUIREMENTS FOR SUBMISSION
OF BA/BE DATA
GENERIC
DRUG
PHARMACEUTICAL
EQUIVALENCE
 Same active ingredient
 Same Strength
 Same Dosage form
 Same Route of administration
THERAPEUTIC
EQUIVALENCE
INSPECTION
 Production System
 Quality System
 Laboratory Control System
 Material System
 Facility & Equipment System
 Packaging & Labeling System
IN-VIVO BIOEQUIVALENCE BIOWAIVER
DOSAGE FORM TE CODE
PROPORTIONATE
FORMULATION BCS CLASS
13
APPROACHES OF BE STUDY
PHARMACOKINETIC
Use of pharmacokinetic endpoints in an accessible biological matrix, such as blood,
plasma, and/or serum, to indicate release of the drug substance from the drug
product into the systemic circulation. BE frequently relies on pharmacokinetic
endpoints such as C max (peak plasma concentration) and AUC (area under the
plasma concentration time curve) that are reflective of rate and extent of absorption,
respectively. If serial measurements of the drug or its metabolites in plasma, serum,
or blood cannot be accomplished, measurement of urinary excretion can be used to
demonstrate BE.
BIOEQUIVALENCE
PHARMACOKINETICS PHARMACODYNAMICS CLINICAL IN-VITRO
STUDY
14
PHARMACODYNAMIC
Studies in healthy volunteers or patients using pharmacodynamics measurements may be
used for establishing equivalence between two pharmaceutical products. These studies may
become necessary if quantitative analysis of the drug and/or metabolite(s) in plasma or urine
cannot be made with sufficient accuracy and sensitivity. Furthermore, pharmacodynamic
studies in humans are required if measurements of drug concentrations cannot be used as
surrogate endpoints for the demonstration of efficacy and safety of the particular
pharmaceutical product e.g., for topical products without intended absorption of the drug into
the systemic circulation.
 COMPARATIVE CLINICAL TRIALS
Lack of meaningful pharmacodynamic parameters which can be measured and a comparative
clinical trial has to be performed in order to demonstrate equivalence between two
formulations.
 IN-VITRO STUDIES
BCS Based Bio waiver/ Other approach
15
HOW TO SELECT CRO
1. QMS Audit by Technical Person (QA/RA)
2. Pervious study conduct history of desired/selected molecule
3. Bioanalytical Method Validation Availability
4. Regulatory Inspection History and Achievement
5. Qualified Personnel availability
6. Hospital Facility near or inside the CRO
7. Equipment/software Facility
16
TYPES OF BE STUDY
 CONSIDERING STUDY POPULATION
Pilot Study
Pivotal Study
 CONSIDERING FOOD INTAKE
Fasting Study
Fed Study
There are Four Stages of BE study:
 Clinical Phase
 Bio analytical Phase
 Pharmacokinetic Phase
 Statistical Phase
* Only clinical phase is different for different type of study, other
phase remain same.
17
REVIEW OF PILOT STUDY RESULTS FOR
DESIGNING PIVOTAL PROTOCOL
A pilot study in a small number of subjects can be carried out before proceeding with
a full bioequivalence study. The study can be used to:
 Validate analytical methodology
 Assess variability
 Optimize sample collection time intervals
 Provide other information. (LOQ Level, ADR)
18
FASTING & FED BE STUDY
 Co-administration of food with oral drug products can influence BE. Therefore, fed
BE studies can determine whether test and RLD products are bioequivalent when
co-administered with meals.
 When a fasting in vivo BE study is recommended for an orally administered,
immediate release product, it is recommend that applicants conduct a fed study,
except when the dosage and administration section of the RLD labeling states that
the product should be taken only on an empty stomach (e.g., the labeling states
that the product should be administered 1 hour before or 2 hours after a meal).
 For orally administered, immediate release products labeled to be taken only with
food, fasting and fed studies are recommended, except when serious adverse
events are anticipated with fasting administration. In these latter cases, we
recommend that applicants conduct only a fed study; a fasting study is not
recommended.
19
DEFINITION
 Bioavailability: Bioavailability can be defined as the rate and extent to which the API or
active moiety is absorbed from a pharmaceutical dosage form and becomes available in the
systemic circulation.
 Bioequivalence: Two pharmaceutical products are bioequivalent if they are pharmaceutically
equivalent or pharmaceutical alternatives, and their bioavailabilities, in terms of rate (Cmax
and tmax) and extent of absorption (area under the curve (AUC)), after administration of the
same molar dose under the same conditions, are similar to such a degree that their effects
can be expected to be essentially the same.
 Interchangeable pharmaceutical product: An interchangeable pharmaceutical product is
one which is therapeutically equivalent to a comparator product and can be interchanged with
the comparator in clinical practice.
 Pharmaceutical Alternatives: Products are pharmaceutical alternative(s) if they contain the
same active pharmaceutical moiety or moieties but differ in dosage form (e.g. tablets versus
capsules), strength, and/or chemical form (e.g. different salts or different esters).
 Pharmaceutical equivalence: Products are pharmaceutical equivalents if they contain the
same molar amount of the same APIs in the same dosage form, if they meet comparable
standards and if they are intended to be administered by the same route. 20
LIST OF ABBREVIATION
 ANOVA: Analysis of Variance
 AUC: Area under the plasma concentration-time curve
 AUC0→t : Area under the plasma concentration-time curve from zero (0) hours to time (t)
 AUC0→∞: Area under the plasma concentration-time curve from zero (0) hours to infinity (∞)
 IP: Investigational Product
 US-FDA: United States Food and Drug Administration
 GCP: Good Clinical Practice
 GLP: Good Laboratory Practice
 Cmax: Maximum drug concentration
 IRB: Institutional Review Board
 Log: Logarithmic
 Tmax: Time of maximum concentration
 T1/2: Terminal elimination half life
 λz :Terminal elimination rate constant
21
LIST OF ABBREVIATION
 TE: Therapeutic Equivalence
 BE: Bio Equivalence
 NDA: New Drug Application
 ANDA: Abbreviated New Drug Application
 CMC: Chemistry, Manufacturing and Control
 QMS: Quality Management System
 MAA: Marketing Authorization Application
 RLD: Reference Listed Drug
 CRO: Contract Research Organization
 ADR: Adverse Drug Reaction
 ICD: Informed Consent Document
 LOQ: Limit of Quantitation
 DBE: Division of Bioequivalence
 OGD: Office of Generic Drug 22
HOW TO CHOOSE REFERENCE
PRODUCT (NAME AND STRENGTH)
To be selected based on the requirement of respective regulatory authority
 e.g: For US-FDA… there are two different Reference Product to established Generic Product
1. RLD: Reference product and strength To Develop Generic Product of respective strength
2. RS: Strength of RLD to perform BE Study
Basic criteria
 Reference product should be purchased with Data logger
 Purchase Invoice should be collected during purchase of RLD
 Should be purchased from latest batch available in market
For EU MAA reference product should be selected from following link: http://mri.cts-mrp.eu/Human/
23
PRE-AUDIT REQUIREMENT AND MAJOR
COMPONENT OF CRO QMS INSPECTION
BE CRO should be audited by Sponsor/nominated representative of sponsor
before finalization the CRO. Inspection should be conducted based on ICH E6
(Good Clinical Practice) and experience.
24
BASIC CRITERIA OF TEST PRODUCT
 Should be from a production lot
 Should be clearly identified by its lot number, manufacture,
and expiration dates
 The potencies of test and reference products should not vary
by more than ± 5%
 Produced under production conditions
 Should pass all QC test
 With good Uniformity results
25
FLOW CHART OF WHOLE STUDY
Formulation Development
CRO Selection based on paper/ Inspection
Protocol Design and review by sponsor
Protocol Approval
Import Permission for IP
IP to Study Site
Clinical and Bioanalytical Analysis
Pharmacokinetic Study
Statistical Analysis
Final Report Preparation and review by CRO
Final Report review by Sponsor (On site or paper)
Final Report submitted to Sponsor
Flow Chart along with tentative timeline are as follows:
26
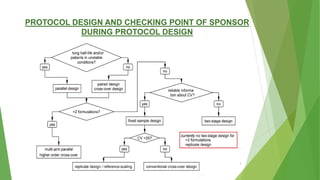
PROTOCOL DESIGN AND CHECKING POINT OF SPONSOR
DURING PROTOCOL DESIGN
 Study Design: Should be as per recommended by respective drug regulatory
authority.
Example: BE recommendation of Metformin Tablet by US FDA
Generally there are two types of Study design:
1. Parallel
2. Crossover
27
PROTOCOL DESIGN AND CHECKING POINT OF SPONSOR
DURING PROTOCOL DESIGN
28
HIERARCHY OF STUDY DESIGNS
29
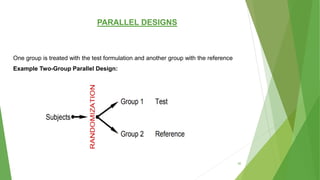
PARALLEL DESIGNS
One group is treated with the test formulation and another group with the reference
Example Two-Group Parallel Design:
30
PARALLEL DESIGNS
Advantages
 Faster than cross-over
 Straight forward statistical analysis
 Drugs with long half life
 Potentially toxic drugs or effect and/or AEs unacceptable in healthy subjects – Studies in
patients, where the condition of the disease irreversibly changes
Disadvantages
 Lower statistical power than crossover design
31
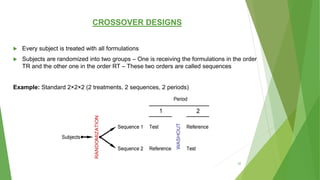
CROSSOVER DESIGNS
 Every subject is treated with all formulations
 Subjects are randomized into two groups – One is receiving the formulations in the order
TR and the other one in the order RT – These two orders are called sequences
Example: Standard 2×2×2 (2 treatments, 2 sequences, 2 periods)
32
CROSSOVER DESIGNS
Advantages
 Globally applied standard protocol for bioequivalence
 Healthy subjects and patients with a stable disease
 Straight forward statistical analysis
Disadvantages
 Not suitable for drugs with long half life
 Not optimal for studies in patients with instable diseases
 Not optimal for Highly variable drug
33
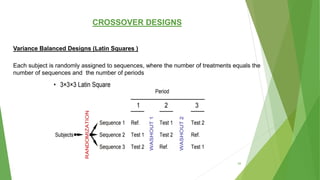
CROSSOVER DESIGNS
Variance Balanced Designs (Latin Squares )
Each subject is randomly assigned to sequences, where the number of treatments equals the
number of sequences and the number of periods
34
CROSSOVER DESIGNS
Advantages
 Allows to choose between two candidate test formulations in a pilot study or comparison of
one test formulation with two reference formulations (e.g., the FDA’s RLD and a European
originator)
 Number of subjects in the study is a multiplicative of three
 Design for establishment of dose proportionality
Disadvantages
 Statistical analysis more complex (especially in the case of dropouts and a small sample
size)
 Not available in all software
35
CROSSOVER DESIGNS
Variance balanced designs (Williams’ design)
3×6×3
4×4×4
36
CROSSOVER DESIGNS
Advantages
 Allows to choose between two candidate test formulations in a pilot study or comparison of
one test formulation with two reference formulations (e.g., the FDA’s RLD and a European
originator)
 Design for establishment of dose proportionality – Mentioned in Brazil’s (ANVISA), the
EMA’s, and the WHO’s GLs
Disadvantages
 Mores sequences for an odd number of treatment needed than in a Latin Squares design
(but equal for even number)
 – Statistical analysis more complex (especially in the case of dropouts and a small sample
size)
 Not available in all software
37
STUDY DESIGN FOR HIGHLY VARIABLE DRUG
 For an oral immediate release product with a long elimination half-life drug (>24 hrs),
applicants can conduct a single-dose, crossover study, provided an adequate washout
period is used. If the crossover study is problematic, applicants should use a BE study with
a parallel design. For either a crossover or parallel study, sample collection time should be
adequate to ensure completion of gastrointestinal transit of the drug product and absorption
of the drug substance. (Which usually occurs within approximately 2 to 3 days). Applicant
can use Cmax and a suitably truncated AUC to characterize peak and total drug exposure,
respectively. For drugs that demonstrate low intra subject variability in distribution and
clearance,applicant can use an AUC truncated at 72 hours (AUC0-72 hr) in place of AUC0-t
or AUC0-inf. For drugs demonstrating high intra subject variability in distribution and
clearance, AUC truncation should not be used.
38
BASIC INCLUSION CRITERIA
 Healthy volunteers
 Should be 18 years of age or older.
 Weight should be within the normal range with a body mass index (BMI) between 18 and 30
kg/m2.
 Should have no history of alcohol or drug-abuse problems and should preferably be
non-smokers.
 If a drug product is intended for use in both sexes, should include similar proportions of
males and females in the study
 If the drug product is predominantly intended for use in the elderly, should include as many
subjects as possible at or above age 60
The criteria may change based on the nature of drug
39
BASIC EXCLUSION CRITERIA
 Contraindication or hypersensitivity (e.g., anaphylaxis) to study drug or related group of drugs or
any of its excipients.
 History or presence of significant asthma, urticaria, or other allergic-type reactions after taking
aspirin or other NSAIDs.
 Participation in a drug research study within 90 days prior to dosing of this study.
 Blood loss or whole blood donation within 90 days prior to drug administration.
 Consumption of high caffeine (more than 5 cups of coffee or tea/day).
 History of dehydration from diarrhea, vomiting or any other reason within a period of 72.00 hours
prior to dosing of each study period.
 Difficulty in swallowing solids like tablets or capsules.
 Difficulty with donating blood.
The criteria may change based on the nature of drug
40
GENERAL CONSIDERATION
Sample collection
General recommendation is collecting 12 to 18 samples, including a predose sample, per
subject, per dose. This sampling should continue for at least three or more terminal
elimination half-lives of the drug. The exact timing for sample collection depends on the
nature of the drug and the rate of input from the administered dosage form. The sample
collection can be spaced in such a way that the maximum concentration of drug in the
blood (Cmax) and terminal elimination rate constant (Kel) can be estimated accurately. At
least three to four samples should be obtained during the terminal log-linear phase to
obtain an accurate estimate of λz from linear regression.
First Point Cmax: Collection of blood samples at an early time point, between 5 and 15
minutes after dosing, followed by additional sample collections (e.g., two to five) in the first
hour after dosing is usually sufficient to assess peak drug concentrations. Failure to include
early (5-15 minute) sampling times leading to first time-point Cmax values may result in
FDA not considering the data for affected subjects from the analysis.
41
GENERAL CONSIDERATION
 Screening: 21-00 (days)
 Dose administration: Fasting restriction 10.00 hours pre-dose and 4 hours post-dose.
(Fasting study)
 Housing: Not less than 10 hours pre-dose till 24 hours post-dose in each period.
 Dosing fluid: 240 ± 02 mL
 Temperature: Ambient
 Posture restriction: The subject will be in sitting/standing posture for 2 hours after
dosing, not sleeping
 The lot numbers of both test and RLD products and the expiration date for the RLD
product should be stated. The assayed drug content of the test product batch not differ
from the RLD product by more than ± 5 percent. The applicant should include a
statement of the composition of the test product and, if possible, a side by-side
comparison of the compositions of test and RLD products.
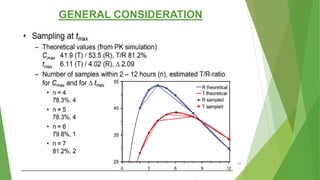
42
GENERAL CONSIDERATION
43
GENERAL CONSIDERATION
44
GENERAL CONSIDERATION
SAMPLE SIZE CONSIDERATIONS
Minimum sample size generally 12. The number of subjects in a clinical trial should always
be large enough to provide a reliable answer to the questions addressed. It is not possible
to calculate the required sample size directly. Power is calculated instead; the smallest
sample size which fulfills the minimum target power is used.
 The sample size and power vary like below,
Α- Patient Risk: BA of the test compared to reference in a particular patient is risky either
below 80% or above 125%.
If we keep the risk of particular patients at α 0.05 (5%), the risk of the entire population of
patients (125%) is 2×α (10%) – expressed as: 90% CI = 1 – 2×α = 0.90.
Β- Sponsor Risk: To get no approval of an equivalent formulation
Set in study planning to ≤0.2 (20%), where power = 1 – β = ≥80%
If power is set to 80 %, one out of five studies will fail just by chance!
45
GENERAL CONSIDERATION
SAMPLE SIZE CONSIDERATIONS
 Generally power is set to at least 80% (β, error type II: producers’s risk to get no
approval for a bioequivalent formulation; power = 1 – β).
 If you plan for power of less than 70%, probably you will face problems with the ethics
committee (ICH E9).
 If you plan for power of more than 90% (especially with low variability drugs), problems
with regulators are possible (‘forced bioequivalence’).
46
GENERAL CONSIDERATION
SAMPLE SIZE CONSIDERATIONS
47
GENERAL CONSIDERATION
SAMPLE SIZE CONSIDERATIONS
48
GENERAL CONSIDERATION
SAMPLE SIZE CONSIDERATIONS
49
GENERAL CONSIDERATION
Fed Treatments: Subjects start the recommended meal 30 minutes before administration
of the drug product following an overnight fast of at least 10 hours. Study subjects should
eat this meal in 30 minutes or less and the drug product should be administered 30 minutes
after start of the meal. The drug product should be administered with 8 fluid ounces (240
mL) of water.
Subjects should receive standardized meals scheduled at the same time in each period of
the study.
 Be allowed water as desired, except for 1 hour before and after drug administration
 Be provided standardized meals no less than 4 hours after drug administration
 Abstain from alcohol for 24 hours before each study period and until after the last
sample from each period has been collected.
50
GENERAL CONSIDERATION
 Fed studies test meal composition: Meals should be fixed that provide
the greatest effects on gastrointestinal (GI) physiology and systemic drug
availability. High-fat (approximately 50 percent of total caloric content of the
meal), high-calorie (approximately 800 to 1000 calories) test meal. This test
meal should derive approximately 150, 250, and 500-600 calories from
protein, carbohydrate, and fat, respectively. The caloric breakdown of the
test meal should be provided in the study report.
 Data deletion because of vomiting: Subjects who experience
emesis during the course of a BE study for immediate release
products be deleted from statistical analysis if vomiting occurs at or
before 2 times median Tmax. For modified release products, we
recommend deleting data from the analysis if a subject vomits during
a period of time less than or equal to the dosing interval stated in the
labeling of the product. 51
SAMPLE SIZE ESMITATION
Limit: 13 to 15
Value of 10 subjects:
12, 12, 12, 14, 11, 14, 15, 14, 17, 16
Total: 137
Average: 13.7
Lowest: 11
Highest:17
Value of 06 subjects:
12, 12, 12, 14, 11, 14
Total: 75
Average: 12.5
Lowest: 11
Highest:14
52
INVESTIGATOR
Selection of investigators
The investigator(s) should have the appropriate expertise, qualifications and competence to
undertake the proposed study. Prior to the trial, the investigator(s) and the sponsor should draw
up an agreement on the protocol, monitoring, auditing, standard operating procedures (SOPs)
and the allocation of trial related responsibilities. The identity and duties of the individuals
responsible for the study and safety of the subjects participating in the study must be specified.
The logistics and premises of the trial site should comply with requirements for the safe and
efficient conduct of the trial.
53
WASHOUT
Wash-out interval
Should normally be more than five times the median terminal half-life of the API. The minimum
washout period should be at least seven days unless a shorter period is justified by a short half-
life. The adequacy of the wash-out period can be estimated from the pre-dose concentrations of
the API in the second study period and should be less than 5% of the observed Cmax.
54
STUDY MONITORING/INSPECTION
Study monitoring/Inspection should be performed in 06 Phases:
1. Pre Audit QMS- To Qualify CRO
2. During Volunteer screening
3. 1st Period Dosing
4. 2nd Period Dosing
5. Bioanalytical study phase
6. Before Final Report submission
55
DROPOUT, PROTOCOL DEVIATION AND
ADR MANAGEMENT
 Dropout: Sponsors should enter a sufficient number of subjects in the study to
allow for dropouts. Because replacement of subjects could complicate the
statistical model and analysis, dropouts generally should not be replaced.
 Protocol Deviation: All protocol deviation should be mentioned in Report
 ADR: ADR should be managed and follow up by CRO up to physical fitness of
the volunteer
56
MOIETIES TO BE MEASURED
The moieties to be measured in biological fluid collected in bioequivalence
studies are either the active drug ingredient or its active moiety in the
administered dosage form (parent drug) and, when appropriate, its active
metabolites. Measurement of a metabolite may be preferred when the parent
drug levels are too low to allow reliable analytical measurement in blood, or
serum for an adequate length of time. The metabolite data obtained from
these studies should be subjects to a full statistical evaluation including a
confidence interval approach for bioequivalence demonstration.
57
PLASMA SAMPLE MANAGEMENT
 Anticoagulant: K2EDTA (commonly used)
 Centrifugation details: At 3500 ± 50 RPM for 10 minutes at 2°C-
8°C (commonly used)
 Sample storage (commonly used) at -25°C ± 5°C for maximum
period of 4 hours (Short time) -70°C ±10°C or -75°C ±10°C (Long
term)
Plasma sample storage condition and Time should be validated during
Bio Analytical Method Validation (Long Term Stability of sample)
58
BIOANALYTICAL
 Why Validation?
To identify the answer of below question:
 Does the method measure the intended analyte (s)?
 What is the range of measurements that provide reliable data?
 What is the variability in these measurements?
 How does sample collection, handling and storage affect the reliability of
the data?
59
BIOANALYTICAL
 Deficiencies in Bioanlytical Phase
60
BIOANALYTICAL
 Deficiencies in Bioanlytical Phase
61
BIOANALYTICAL
 Deficiencies in Bioanlytical Phase
62
OTHER DEFICIENCIES
 Dissolution specification: The in vitro dissolution testing specifications were not
proposed or not as recommended by DBE.
 Dissolution method: The dissolution method used in the application is not optimal
or not consistent as that suggested by DBE.
 Failure to submit individual dissolution data for each of the 12 units of test and
reference products.
 Incomplete dissolution testing (for example, lacking dissolution data in multimedia
for extended release products and alcohol dose dumping data for certain
products).
 High variability in dissolution data.
 Bio-summary tables: Summary tables for BE studies (available to the industry on
OGD’s website) are not submitted or incomplete.
63
OTHER DEFICIENCIES
 Unjustified exclusion of subjects: Subjects are excluded from statistical
analysis without proper justification.
 Dropping subjects who are assumed outliers from statistical analysis
without adequate justification.
 Improper submission or missing of electronic data files which are required
for statistical analysis.
 Inadequate information on the failed bioequivalence study.
64
ACCEPTANCE CRITERIA
Regarding Cmax & AUC, the 90% confidence interval should generally be within the acceptance
range 80.00% to 125.00% (when log transformed data are used). For scaled BE study following limit
can be used:
65
REPORTING OF RESULTS
The report of a bioequivalence study should give the complete documentation of its
protocol, conduct and evaluation complying with GCP and GLP rules. The relevant
International Conference on Harmonisation of Technical Requirements for
Registration of Pharmaceuticals for Human Use (ICH) guideline (E3) can be used in
the preparation of the study report. The responsible investigator(s) should sign the
respective sections of the report. Names and affiliations of the responsible
investigator(s), site of the study and period of its execution should be stated.
Some zone has its respective format of reporting.
66
REPORTING OF RESULTS
The names and batch numbers of the pharmaceutical products used in the study as
well as the composition (s) of the tests product(s) should be given. Results of in vitro
dissolution tests conducted in media with pH of 1.2, 4.5 and 6.8 and the QC media, if
different, should be provided. In addition, the applicant should submit a signed
statement confirming that the test product is identical to the pharmaceutical product
that is submitted for registration.
67
PHARMACOKINETIC INFORMATION IN THE
SUBMISSION
68
STATISTICAL INFORMATION IN THE
SUBMISSION
69
Not recommend to round off CI values; therefore, to pass a CI limit of 80 to 125 percent,
the value would be at least 80.00 percent and not more than 125.00 percent.
HANDLING & RETENTION OF IP
Single Container: If a single container of the test article and reference
standard are provided to the testing facility, the testing facility should remove a
sufficient quantity of the test article and reference standard from their
respective containers to conduct the study; the remainder in each container
should be retained as reserve samples in the original containers.
Multiple Containers: If multiple containers of the test article and reference
standard are provided to the testing facility, the testing facility should randomly
select enough containers of the test article and reference standard to conduct
the study; the remaining containers of the test article and reference standard
should be retained as the reserve sample in the original containers. Generally,
multiple open bottles are discouraged.
Unit Dose: If the test article and reference standard are provided to the testing
facility in unit dose packaging, the testing facility should randomly select a
sufficient quantity of unit doses of the test article and reference standard to
conduct the study; the remaining unit doses of the test article and of the
reference standard should be retained as the reserve samples in the original
unit dose packaging. 70
HANDLING & RETENTION OF IP
Blinded Study: If the study is to be blinded and the test article and reference
standard are provided to the testing facility in unit dose packaging with each
unit dose labeled with a randomization code, the study sponsor and/or drug
manufacturer should provide the testing facility with a labeled set of the test
article and reference standard sufficient to conduct the study and with
additional, identically labeled sets sufficient to retain the “five times quantity”
The testing facility should randomly select a labeled set to conduct the study;
the remaining labeled sets would be retained in their unit dose packaging as
the reserve samples.
QUANTITY OF RESERVE SAMPLES
The quantity of reserve samples should be sufficient to permit the Agency to
perform five times all of the release tests required in the application or
supplemental application
71
ARCHIVING OF STUDY REPORT
All clinical, pharmacokinetic, biostatical data and Bioanalytical data of the study,
together with a copy of this protocol and signed ICDs will be retained at Study
center archives for a maximum period of 05 years (or) as per mutual
understanding between the sponsor and CRO.
72
REFERENCES
 Bioequivalence studies with pharmacokinetic endpoints for drugs submitted
under an abbreviated new drug application- US- FDA draft guidance
 Handling and retention of bioavailability and bioequivalence testing
samples- US- FDA guidance
 Guidelines on drug bioequivalence requirements in the GCC countries - ICH
 Guideline for good clinical practice – ICH- E6 (R2)
 Structure & content of clinical study reports – ICH –E3
 Guideline on the investigation of bioequivalence (EMEA)
 Multisource (generic) pharmaceutical products: guidelines on registration
requirements to establish interchangeability (WHO Annex 7)
 Guidelines for bioavailability & bioequivalence studies- CDSCO, India
 ASEAN guideline for the conduct of bioequivalence studies
 Other journals and relevant website 73
74