Approach To The Critically
Ill Patient
Ahmed Mohamed Abdelazeem
Critical Care Medicine Department
Benha University
2019
PRIMARY SURVEY
1. Airway and cervical spine control
2. Breathing and ventilation
3. Circulation with hemorrhage control
4. Disability
5. Exposure/Environmental control
Airway and Cervical
Spine Control
Assessment
1. Airway Patency
• Have the patient speak
If the patient talks to you normally, the airway is clear. If there is no response to speech,
perform a more detailed assessment of the airway
• Look, listen and feel
Look for secretions, blood, vomit, foreign bodies, facial, mandibular, or tracheolaryngeal
fractures
Listen for upper airway noises
Gurgling ” caused by fluids (secretions, blood or vomit) in the oropharynx”
Snoring “partial airway obstruction at the pharyngeal level”
Stridor ”high-pitched inspiratory sound, may be associated with partial airway obstruction
at the level of the larynx (inspiratory stridor) or the trachea (expiratory stridor)”
Hoarseness “caused by partial laryngeal obstruction associated with oedema”
Absent breath sounds indicates either complete airway obstruction or absence of
breathing
Feel air flow
2. Airway Protection
• Testing the gag reflex or the ability to swallow
3. Assume Injury To The Cervical Spine In Any Patient With The
Following Findings:
• Multi-system or major trauma
• Altered level of consciousness
• Blunt injury above the clavicles
• Concerning mechanism of injury
• Neck pain, ecchymosis or deformity
• Neurologic deficits
“A normal neurologic exam does not exclude cervical spine injury”
Interventions
1. General Guidelines
• Protection of the cervical spine
All trauma victims should be placed in a protective cervical spine collar
• Prevention of aspiration
Suctioning of the lower pharynx and oropharynx
A vomiting patient should be rolled to the left lateral decubitus position and the entire
spine properly protected so that the airway can be cleared.
2. Simple Maneuvers
• Head tilt/chin lift: contraindicated if neck injury is suspected
• Jaw thrust: the preferred method for patients with possible cervical spine injury
3. Airway Adjuncts
• Oropharyngeal airway (unconscious patient)
• Nasopharyngeal airway (semiconscious patient)
“Do not use a nasopharyngeal airway if you suspect a skull base fracture”
• Laryngeal mask airway
4. Tracheal Intubation
Breathing and
Ventilation
Assessment
1. Physical Examination
• Inspection: Observe the chest wall for symmetric rise as well as for
paradoxical movement suggestive of flail chest
• Palpation: position of the trachea in the suprasternal notch,
Subcutaneous Emphysema, for crepitus and rib tenderness
• Auscultation: provides clues to possible causes of respiratory arrest or
distress, including pneumothorax, congestive heart failure (CHF),
pulmonary edema, or pleural effusions
2. Monitoring
• pulse oximeter, end-tidal CO2 monitor
3. Diagnostics
• arterial blood gas, portable chest radiograph (+ pelvic and cervical spine
views in multiply injured).
Interventions
1. Administration Of Supplemental Oxygen
• Nasal cannula: delivers oxygen at concentrations of 25%–45% at a flow rate of 1–6
L/min
• Simple face mask: delivers oxygen at concentrations of 40%–60% at a flow rate of 6–
10 L/min
• Venturi mask: delivers oxygen at concentrations of 65%–75% at a flow rate of 12–15
L/min
• Non rebreather mask: delivers oxygen at concentrations of 24%–60% at a flow rate
of 2–15 L/min
• Bag-mask: delivers oxygen at concentrations of 90%–97% at a flow rate of 12–15
L/min, while the previous methods require spontaneous respirations the BVM is used
for apneic patients
• Mechanical positive-pressure ventilation
2. Treatment Of The Cause
• Needle thoracostomy
• Chest tube thoracostomy
• Thoracocentesis
• Furosemide
Circulation with
Hemorrhage Control
Assessment
1. Physical Examination
• Pulse
palpable carotid, femoral, radial, dorsalis pedis pulse = SBP > 60, 70, 80, 90 mm hg
• Neck veins
• Level of consciousness
• Skin temperature and color
• Capillary refill time
• Heart sounds
• Blood pressure
• Urine output
2. Monitoring
• Continuous electrocardiographic monitoring and noninvasive blood pressure
monitoring
3. Diagnostics
• ECG, POCUS
Interventions
1. Establishing Intravenous Access
2. Take Initial Blood Samples For Blood Grouping, Full Blood Count, Coagulation
Studies, Electrolytes, Kidney Functions, Liver Functions
3. Fluid Resuscitation, Blood Products, Vasopressors, Inotropes
4. Treatment Of The Cause
• needle decompression followed by tube thoracostomy for tension pneumothorax
• needle pericardiocentesis for cardiac tamponade
• thrombolytics for pulmonary embolism
• Cardioversion
• pacing
Disability
Assessment
1. Level Of Consciousness:
• AVPU/GCS
2. Pupillary Examination:
• Size, equality, reactivity to light
• In structural causes of coma the light reflex is usually absent, in metabolic
causes it is usually present
• A difference in pupil diameters >1 mm suggests A structural cause
3. Movement Of Extremities And Lateralization
4. Check The Blood Glucose
Interventions
1. Anticonvulsants For Seizures
2. Dextrose For Hypoglycemia
3. Antidote For Drug Overdose
Exposure/
Environmental
Control
Assessment
• Fully Undress The Patient To Examine The Patient’s
Skin Surface
Interventions
1. Remove All Wet Or Contaminated Clothing
2. Keep The Patient Warm By
• Applying warm blankets
• Ventilating with warm humidified air
• Administering warmed IV fluids
SECONDARY SURVEY
1. Subjective
2. Objective
3. Assessment and plans
Subjective
1. Chief Complaints
• Demographics
• Name
• Age
• Gender
• Admission date
• Source of referral
• Relevant comorbidities
• Complaining of
2. History Of Present Illness
• Presenting scenario (A brief summary of significant data only
“subjective, objective, assessment, plan” in a chronological order, first
during Pre hospital course then during ED/floor hospital course and
finally during ICU course)
• Relevant Systems Review, Past History, Personal and Social
History, Family History, Allergies, Medications
3. Systems Review
• Neurological
• Cardiovascular
• Respiratory
• Gastrointestinal
• Genitourinary
• Infectious Diseases
• Hematological
• Endocrinal
• Musculoskeletal
4. Past History
• Medical
• Surgical
• Ob/Gyn
5. Personal And Social History
• Occupation
• Marital status
• Living conditions
• Habits “Tobacco, Alcohol, Illicit drugs”
6. Family History
7. Allergies
8. Medications
• Indication
• Dose
• Duration
• Side effects
Objective
1. Physical Exam
• General
• Vitals (Height, Weight, Temperature, Heart Rate, Blood Pressure, Central Venous
Pressure, Respiratory Rate, Oxygen Saturation, 24 hr Urine Output, Net Fluid
Balance)
• HEENT “Head, Eyes, Ears, Nose and sinuses, Throat”
• Neck
• Cardiovascular
• Respiratory
• Abdominal
• Neurological
• Extremeties
• Skin
2. Laboratory Data
• ABG, CBC, Coagulation studies, electrolytes “Na, K, Ca, Mg, Ph”, Kidney
functions, Liver functions, Thyroid function, Adrenal function, CRP, PCT,
Cultures, Antibiotic levels, Troponins, Ck-Mb, others
3. Imaging Data
• X Ray, CT, MRI, US, ECG, ECHO, others
Assessment and
Plans
1. Summary Statement with Synthesized Problem List
• Demographics (Name, Age, Gender, Admission date, Source of referral),
Relevant comorbidities, Presented complaining of, Found to have “main
problems in descending order of importance”
2. System – Based/Problem - Based Assessment and
Plans (Diagnostic, Therapeutic)
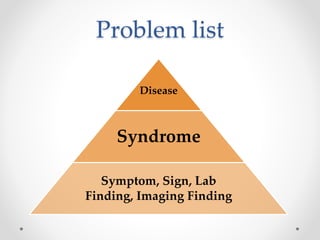
Problem list
Disease
Syndrome
Symptom, Sign, Lab
Finding, Imaging Finding
Daily Presentation
1. Summary Statement with Synthesized Problem List
2. Major events during the last 24 h
3. System - Based Assessment and Plans (Diagnostic, Therapeutic):
• Neurological (SOAP)
• Cardiovascular (SOAP)
• Respiratory (SOAP)
• Renal (24 hr Urine Output, Dialysis, Urea, Creatinine), Fluids (Net Fluid Balance,
Cumulative Fluid Balance), Electrolytes (Na, K, Ca, Mg, Ph)
• Gastrointestinal (SOAP), Nutrition (Albumin, Tolerance)
• Genitourinary (SOAP)
• Infectious diseases (Temperature, TLC, CRP, PCT, Cultures, Antibiotic levels)
• Hematological (CBC, PT, PTT, Fibrinogen, FDPs, D-dimer, Peripheral blood smear,
Blood products transfusion)
• Endocrinal (Glycemic control, Thyroid function, Adrenal function)
• FAST HUGS SLR: Feeding, Analgesia, Sedation, Thromboembolic prophylaxis, Head
of bed elevation, Ulcer prevention, Glycemic control, Skin breakdown ”Wounds,
Bedsores”, Stool, Lines/catheters/drains, Readiness to wean
• Physical Therapy
• Discharge Planning
Summary
• Primary Survey
 Airway and cervical spine control
 Breathing and ventilation
 Circulation with hemorrhage control
 Disability
 Exposure/Environmental control
• Secondary Survey
 Subjective
 Objective
 Assessment and plans
THANKS