Hyperlipidemia (Hyperlipoproteinaemia)
• Lipids and cholesterol are
transported through the
bloodstream as macromolecular
complexes of lipid and protein
known as lipoproteins.
Hyperlipidemia (Hyperlipoproteinaemia)
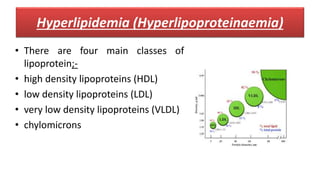
• There are four main classes of
lipoprotein;-
• high density lipoproteins (HDL)
• low density lipoproteins (LDL)
• very low density lipoproteins (VLDL)
• chylomicrons
• A family history of hyperlipidemia.
• A diet high in total fat, saturated fat,
or cholesterol.
• Obesity
Causes of hyperlipidemia
• Certain conditions including
• Diabetes.
• Renal disease.
• Hypothyroidism.
• Liver disease.
• Cushing's syndrome (↑ blood cortisol).
Causes of hyperlipidemia
• Certain drugs such as
• Hormones or birth control pill
• Corticosteroids
• Isotretinoin (antiacne agent)
• β blockers
• Thiazides diuretics
•
Untreated hyperlipidemia can cause (↑ risk of )
Atherosclerosis (hardening of the
arteries)
Heart attack
Stroke (sudden unconsciousness due to
cerebrovascular thrombosis, embolism
or hemorrhage with varying degrees of
hemiplegia).
Risk factors include
• Advancing age
• Adult men (any age)
• Adult women (postmenopause)
• Lack of exercise
• Stress
• Smoking
• excessive alcohol intake
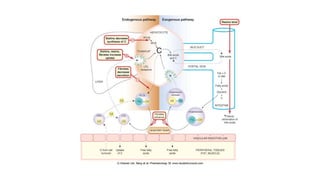
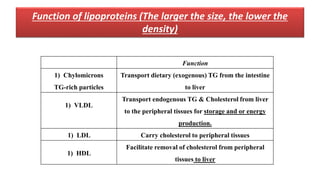
Function of lipoproteins (The larger the size, the lower the
density)
Function
1) Chylomicrons
TG-rich particles
Transport dietary (exogenous) TG from the intestine
to liver
1) VLDL
Transport endogenous TG & Cholesterol from liver
to the peripheral tissues for storage and or energy
production.
1) LDL Carry cholesterol to peripheral tissues
1) HDL
Facilitate removal of cholesterol from peripheral
tissues to liver
Lipoproten lipase (LPL)
• Cause Degradation (lipolysis) of TGs present in VLDL and
chylomicrons fatty acids and glycerol (to be stored or utilized
in energy production)
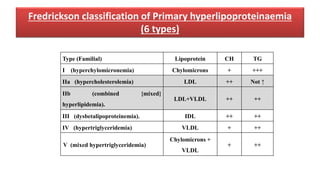
Fredrickson classification of Primary hyperlipoproteinaemia
(6 types)
Type (Familial) Lipoprotein CH TG
I (hyperchylomicronemia) Chylomicrons + +++
IIa (hypercholesterolemia) LDL ++ Not ↑
IIb (combined {mixed}
hyperlipidemia).
LDL+VLDL ++ ++
III (dysbetalipoproteinemia). IDL ++ ++
IV (hypertriglyceridemia) VLDL + ++
V (mixed hypertriglyceridemia)
Chylomicrons +
VLDL
+ ++
Management of Hyperlipidemia
• Diet and lifestyle changes can help treat
hyperlipidemia
• Diet Changes
• Restriction of caloric intake (35% as fat,
50% as carbohydrate and 15% as protein)
• Restriction of cholesterol to < 300
mg/day (equivalent to 11/2 eggs)
• Replace animal fats with polyunsaturated
fatty acids & Increase in dietary fibers
• ↑ dietary fibers (fruits & vegetables)
Management of Hyperlipidemia
• Lifestyle Changes
– Weight reduction (for overweight and
obese persons).
– Exercise.
– Cessation of smoking.
– Reduction or elimination of alcohol
intake.
• A combination of diet, lifestyle
changes and medication may be
required in some cases
Drug Therapy
• 1- Fibric acid derivatives (Fibrates or
peroxisome proliferator-activated
receptor-α (PPAR α)activators agonist)
• Clofibrate ,
• Fenofibrate ,
• Bezafibrate ,
• Etofibrate ,
• Ciprofibrate,
• Gemfibrozil
Mechanism of action
• Activate the nuclear peroxisome proliferator-activated
receptor-α (PPAR α) which is found mainly in hepatocytes and
adipocytes and functions to regulate lipoprotein metabolism.
• ↓ TG level through
1-↑ fatty acid oxidation mediated through PPAR α - stimulation
2-↑ peripheral LPL (lipoprotein lipase) synthesis
3-↓ Hepatic TG synthesis
Mechanism of action
• ↓ LDL levels by enhancing
its hepatic clearance.
– Bezafibrate and fenofibrate
are more effective than
gemfibrozil and clofibrate in
lowering LDL level.
Indications of Fibrate therapy
• Indicated in clinical disorders associated with ↑ circulating
TGs such as
• Type IIb (↑ VLDL+LDL) mixed hyperlipidemia.
• type III (↑IDL)
• Types IV (↑ VLDL) hypertriglyceridemia.
• Type V (↑ VLDL+CM) mixed hypertriglyceridemia.
Indications of Fibrate therapy
• Fibrate therapy is a suitable choice for
the treatment of dyslipidemia in
diabetic patients who often
demonstrate hypertriglyceridemia and
low levels of HDL
Fibrate Pharmacokinetics
• All fibrates are absorbed rapidly
and efficiently (> 90%) when
given with a meal but less
efficiently when taken on an
empty stomach
Adverse effects of Fibrates
• GIT disturbances (5-10% of patients)
• Cholelithiasis (gallstone formation) due to
↑ biliary cholesterol excretion.
•
• Myopathy  fibrates can cause myositis
especially in patients with renal
insufficiency (Muscle weakness and
tiredness should be evaluated)
Adverse effects of Fibrates
• Infrequent adverse effects( ADRs) include
 arrhythmias,
hypokalemia,
 ↑ aminotransferase,
↑ alkaline phosphatase,
skin rashes,
urticaria,
headache,
hair loss,
 impotence,
 myalgia,
fatigue
 anaemia.
Drug Interactions
• Fibrates X oral anticoagulants 
(↑ anticoagulant Activity).
• (Displacement reaction so ↓ anticoagulant
dose)
• Fibrates X oral sulphonylureas
(↑ sulphonyluria action
Contraindications
Pregnancy and lactation.
Severe hepatic and renal dysfunction.
Pre-existing gallbladder disease.
2) HMG-CoA Reductase Inhibitors (Statins)
• High-potency statins  Rosuvastatin and atorvastatin.
• Intermediate potency statins  simvastatin and pravastatin.
• Low-potency statins  lovastatin and fluvastatin.
Most effective and best-tolerated agents for treating elevated LDL-C.
hydroxymethylglutarate coenzyme
Mechanism of action
• (1) Inhibition ofHydroxy Methyl Glutarate –CoA( HMG-CoA)
reductase enzyme (↓ CH synthesis)
• statins competitively inhibit the enzyme HMG-CoA reductase (the rate-
limiting step in cholesterol synthesis) leading to
» Inhibition of hepatic cholesterol synthesis
» depletion of intracellular free cholesterol
•
Mechanism of action
• (2) Increase in LDL receptor (↑LDL catabolism)
• Depletion of intracellular cholesterol  hepatic cell ↑ number of
surface LDL receptors that can bind and remove LDL-C from blood
• Statins also can enhancing the removal of LDL-C precursors (VLDL &
IDL) from the circulation ↓ LDL-C levels
• (3) Reduction of plasma TGs
• By ↓ hepatic VLDL production and secretion.
• (4) Elevation of HDL-C
Indications of Statins
» Treatment of familial types IIa and IIb
» dyslipidemic diabetic patients (↓ LDL and
TGs and ↑ HDL)
» Treatment of elevated LDL plasma levels
either as monotherapy or with bile acid
binding resins or niacin
» Statins are less effective in patients with
homozygous familial hypercholesterolaemia
who lack LDL receptors
Pharmacokinetics
• Absorbed after oral administration.
• Metabolism in liver
• Bound to plasma protein
• Statins are excreted mainly through the bile and feces (>70%)
with some urinary excretion.
Adeverse effects
• Transient elevation of serum transaminases
• Myopathy (muscle weakness) and
rhabdomyolysis (disintegration of muscle
tissue)
Contraindications
• Pregnancy and lactation.
• Children and teenagers.
• Homozygous familial hypercholesterolemia
3) Bile acid-binding Resins
• Cholestyramine,
• Colestipol,
• Colesevelam
Mechanism of action
• These are highly positively charged anion-
exchange resins that bind negatively charged
bile acids and bile salts in the small intestine
 non-absorbable resin/bile acid complex
 excreted in stool  preventing bile acids
from returning back to the liver by the
enterohepatic circulation
•
Mechanism of action
• ↓ Hepatic bile acid  as a compensatory
mechanism hepatocytes ↑ conversion of
cholesterol to bile acids (essential
components of bile)
• The resultant ↓ intracellular cholesterol 
↑ hepatic uptake of cholesterol-rich LDL 
upregulation of hepatocyte surface LDL
receptors ↓ plasma LDL-C
Mechanism of action
• Produce a modest rise in HDL-C in some patients
Indications
• Primary chylomicronemia.
• Familial hypertriglyceridemia
• Relief of excess bile acid-induced pruritus in patients with biliary obstruction.
Adverse effects
• GIT effects  constipation, bloating (flatulence)
& nausea .
• High-dose cholestyramine and colestipol impairs the
absorption of fat-soluble vitamins (ADEK).
Drug Interactions
• Cholestyramine and colestipol interfere
with the intestinal absorption of many
drugs including tetracycline, digoxin,
warfarin , pravastatin, fluvastatin,
aspirin, phenobarbital and thiazide
diuretics
4) Niacin (Nicotinic acid,Vitamin B3)
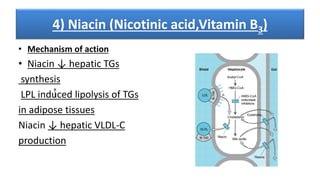
• Mechanism of action
• Niacin ↓ hepatic TGs
synthesis
LPL induced lipolysis of TGs
in adipose tissues
Niacin ↓ hepatic VLDL-C
production
Therapeutic Uses
– Familial hyperlipidemias (↓ cholesterol & TGs).
– Severe hypercholsterolemias (+ statins).
– Familial dysbetalipoproteinemia (Type III) (↑lDL  ↑TGs + TC)
Adverse Effects
• Flushing (due to cutaneous PG-mediated vasodilatation)
• Dyspepsia, nausea & abdominal pain.
• Uric acid retention
Contraindications
• Pregnancy
• History of gout (gout may occur in 20% of patients).
5) Cholesterol Absorption Inhibitors
(Ezetimibe)
Mechanism of Action
• Ezetimibe selectively inhibits intestinal absorption of dietary
and biliary cholesterol ↓ ch in chylomicrons (CM) ↓
cholesterol delivery to the liver ↓ hepatic cholesterol stores
 ↑ hepatic LDL receptors  ↑ cholesterol clearance from
blood.
•
Therapeutic Uses
• Treatment of hypercholesterolemia often in combination with
a statin
• As monotherapy in statin-intolerant patients
Adverse Effects
• Myopathy (with or without statins).
• Allergic reactions (rarely).
• Hepatotoxicity
Contraindications
• Pregnancy & lactation.
• Moderate and severe hepatic insufficiency
6) Probucol
• Probucol is a hypolipidemic drug ↓ plasma LDL-C and HDL-C.
• It has minimal cholesterol lowering effects,
• May act by ↓ the oxidation of LDL (Oxidized LDL is taken up by
macrophages to produce foam cells and atherosclerotic plaques)
• Probucol is not commonly used because it ↓ HDL-C to a greater
degree than LDL-C and has been associated with ventricular
arrhythmias
•
6) Probucol
• The use of probucol
• ↓ the risk of atherosclerosis might be due to
– Mainly to its anti-oxidant property
– An effect of lipid lowering action
D-Thyroxine
– ↑ LDL uptake (clearance) by ↑ LDL receptors synthesis.
– It can be used in
• Young patients with type IIa familial hypercholesterolemia,
who do not have coronary artery disease
• In whom dietary treatment and other drugs have not been
successful.
•
Neomycin
• It binds bile acids in the intestine ↑ hepatic conversion of
cholesterol into bile acids.
Plant sterols (Phytosterols)
• These agents block intestinal cholesterol uptake by
competition for its absorption sites, without themselves being
absorbed.
Fish Oils
– Fish oil contains ϖ3 fatty acids
• ↓ VLDL-C synthesis and improved clearance of remnant
particles.
• ↓ Production of arachidonic acid metabolites, ↓ platelet
aggregation.
‫والنشر‬ ‫للطباعة‬ ‫النصر‬