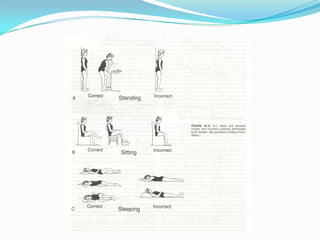
Body Mechanics
 The efficient, coordinated, and safe use of the body to
  produce motion and maintain balance during activity.


Major purpose: facilitate safe and efficient use
of appropriate groups of muscles.
3 Basic Elements
 Body alignment (posture): geometric arrangement of
  body parts in relation to each other.
 Balance (stability): state of equipoise (equilibrium) in
  which opposing forces counteract each other.
 Coordinated body movement: integrated functioning
  of the musculoskeletal and nervous system as well as
  joint mobility.

Important Concepts
 The center of gravity of an object is the center of its
  mass. In humans, it is at the center of the pelvis about
  midway between the umbilicus and the symphysis
  pubis.
 The line of gravity is the vertical line passing through
  the center of gravity.
 The base of support is the foundation that provides the
  object/person’s stability.
Principles of Body Mechanics
 a. Spread your feet       b. Place your feet
                           appropriately in the
 apart to provide a wide
                           direction in which the
 base of support           movement occurs.


 c. Keep objects to be     d. Push, pull, roll, or slide
 moved close to the body   objects rather than lifting
                           them, whenever possible.
Principles of Body Mechanics
e. When pushing or pulling           f. Avoid twisting the spine
an object, use the body’s            by pushing or pulling
weight to counteract the             objects directly away from
weight of the object.                or toward the body and
                                     squarely facing the
                                     direction of movement.


          g. When lifting objects,
          distribute the weight
          between large muscles of
          the legs and arms.
Other Strategies
to Prevent Back Injuries
1.   Wear low-heeled shoes that provide good foot
     support
2.   When standing for long periods, occasionally flex
     one hip and knee and rest your foot on an object if
     possible
3.   Sit with knees slightly higher than hips
4.   Exercise regularly, including exercises to strengthen
     the pelvic, abdominal, and lumbar muscles
5.   Sleep on a firm mattress
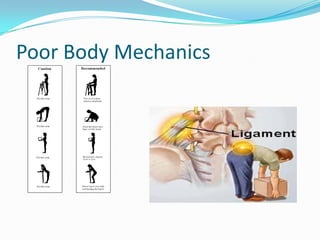
Poor Body Mechanics
Complications Related to
Poor Body Mechanics
  1. Muscle fatigue
                            2. Joint strain


        3. Lower back injuries- most
        common injury among
        nurses

           4. Repetitive motion injuries
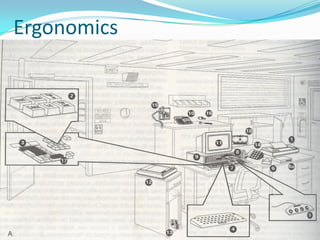
Ergonomics
Ergonomics
Ergonomics
Complications
of Immobility
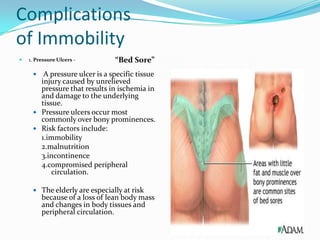
   1. Pressure Ulcers -       “Bed Sore”
       A pressure ulcer is a specific tissue
       injury caused by unrelieved
       pressure that results in ischemia in
       and damage to the underlying
       tissue.
      Pressure ulcers occur most
       commonly over bony prominences.
      Risk factors include:
       1.immobility
       2.malnutrition
       3.incontinence
       4.compromised peripheral
           circulation.

      The elderly are especially at risk
         because of a loss of lean body mass
         and changes in body tissues and
         peripheral circulation.
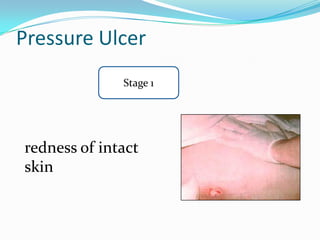
Pressure Ulcer
              Stage 1


redness of intact
skin
Pressure Ulcers
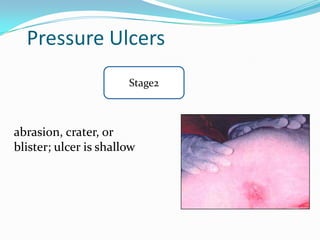
                       Stage2


abrasion, crater, or
blister; ulcer is shallow
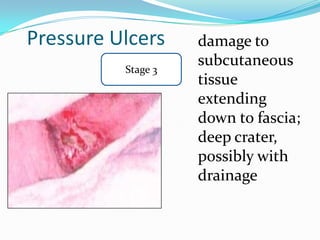
Pressure Ulcers     damage to
          Stage 3
                    subcutaneous
                    tissue
                    extending
                    down to fascia;
                    deep crater,
                    possibly with
                    drainage
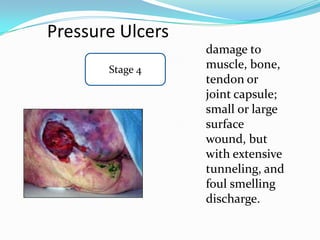
Pressure Ulcers
                  damage to
       Stage 4    muscle, bone,
                  tendon or
                  joint capsule;
                  small or large
                  surface
                  wound, but
                  with extensive
                  tunneling, and
                  foul smelling
                  discharge.
Nursing Measures to prevent
Pressure Sores:
 Frequent turning of immobile clients every 2 hours
 Instruct patients to do weight shifts (pressure relief) at
  least every 15-20 minutes when sitting in your
  wheelchair.
   If your injury is at levels C4 and higher you can use a
    power tilt wheelchair for regular pressure relief.
   With an injury at levels C5 or C6 you can usually lean
    forward or side-to-side for regular pressure relief.
   If your levelof injury is C7 and below you can usually
    perform a wheelchair push-up for regular pressure relief.
Nursing Measures to prevent
Pressure Sores:
 Provide for good nutrition with diet high in protein,
  carbohydrates, fluids, vitamin C and zinc
 Use alternating-pressure air mattress, flotation pads,
  elbow and heel pads, sheepskin pads
 Do not use “donuts” or rubber rings
 Protect from infection
Nursing Measures to prevent
Pressure Sores:
 Wash skin gently, pat dry to prevent skin abrasion
 Use clean, dry, wrinkle-free bed linens and pads
 Promote circulation by gently massaging skin with
  lotion that does not contain alcohol
 Remove dead tissue and debris for stages 2-4
   Dead tissue in the pressure sore can delay healing and
    lead to infection. Removing dead tissue is often painful.
    The client may be given pain-relieving medicine 30 to 60
    minutes before these procedures.
Nursing Measures to prevent
Pressure Sores:
 Procedure
    Rinsing (to wash away loose debris).
    Wet-to-dry dressings.
    Enzyme medications to dissolve dead tissue only.
    Special dressings
 Complications of pressure sores include localized (i.e.
 osteomyelitis, cellulitis) and even systemic infection
 (i.e. sepsis)
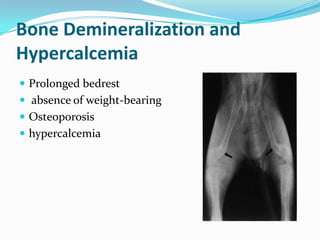
Bone Demineralization and
Hypercalcemia
 Prolonged bedrest
 absence of weight-bearing
 Osteoporosis
 hypercalcemia
Bone Demineralization and
Hypercalcemia
 Nursing Measures:
    Prevent injury related to dec. bone strength
    Encourage weight-bearing on long bones, if possible
    Correct Body alignment, firm mattress
    Encourage self – care, ROM, avoid fatigue
    Assume wt. bearing positions (Tilt Table)
    Decrease calcium intake, provide balanced diet
    Diet: high CHON, Vit.C, Dec. Ca
    May be given estrogen, as necessary, and medications like
     biphosphonates (i.e. alendronate, residronate) to retard
     demineralization
    Encourage fluids, acid ash diet
Negative Nitrogen Balance
 Negative nitrogen balance is aggravated by anorexia. It
  represents depletion of protein stores that are essential
  for building muscle tissue and for wound healing.
 Nursing Measure: Give high protein diet in small,
  frequent feedings
Orthostatic Hypotension
 Orthostatic hypotension is decrease in BP > 20/10 mmHg
  and it happens when there is decreased ability of the
  autonomic nervous system to equalize the blood supply
  when position is changed from recumbent to upright.
  Another contributing factor is the pooling of blood in the
  lower extremities due to the decrease in muscle action that
  causes pressure on the veins and assisting in venous return.

 May lead to faintness, weakness, or dizziness in an attempt
  to stand. The patient is at high risk for injury due to falls.
Orthostatic Hypotension
 Nursing Measures:
   Increase activity gradually
   Encourage ROM and leg exercises
   Teach patient to rise from bed slowly and dangle legs
    before getting up
   Elastic stockings
   Tilt table
   Sitting & lying BP
Increased Cardiac Workload
 When the body is recumbent, the
 total blood volume that would be in
 the legs due to gravity is redistributed
 to other parts of the body, increasing
 the circulating volume and workload
 of the heart.

 With prolonged immobility the
 sympathetic nervous system takes
 over resulting to tachycardia
Increased Cardiac Workload
 Valsalva maneuver further increases cardiac workload
 Nursing Measures: Goal is to prevent injury and
 further ischemic damage to cardiac tissue by
 decreasing workload of heart:
   Semi-recumbent position when in bed, pillows between
      legs when side-lying
     Passive & Active ROM exercises
     Turn every 2 hour, dangle legs
     Avoid Valsalva maneuver: use overhead trapeze when
      moving in be
     Encourage slow, deep breathing when moving in bed
Contractures
 Contractures are joint abnormalities
  due to abnormal shortening of muscle
  tissue, rendering the muscle highly
  resistant to stretching.
 Due to lack of active or passive ROM
  and improper positioning of joints
 On assessment: fixed, shortened
  extremities with pain on manipulation
 Leads to difficulties in performing ADL

Contractures
 Nursing Measures:
    Promote frequent change in position
    Use pillows, trochanter rolls, and
     foot board to promote proper body
     alignment
    Avoid knee gatch
    Perform therapeutic ROM exercises
     as appropriate
    Promote proper body alignment
    Position: Functional, correct
     alignment
Thrombus Formation
  This is development of clot in a
  vein due to venous stasis,
  increased coagulability of blood
  and damage to the endothelial
  wall of the vessel
               DVT present as groin or calf
               tenderness, pain, warm and
               edematous extremities. It poses the
               danger of throwing off an emboli
               leading to pulmonary infarction
Thrombus Formation
 Nursing Measures:
    Prevent by leg exercises: flexion and extension of toes
     for 5 minutes every hour
    Ambulate patients as appropriate
    Avoid using knee gatch on bed or pillows to support
     knee flexion
    Use anti-thromboembolic stockings
    Check for Homan sign
Stasis of Respiratory Secretions
 Due to inability of cilia to move normal secretion out
  of bronchial tree due to ineffective coughing, lack of
  thoracic expansion or effects of medications
 This leads to hypostatic pneumonia (frequent
  nosocomial infection)
Stasis of Respiratory Secretions
 Nursing Measures:
    Teach patient the importance of turning,
     deep breathing, coughing
    Teach patient how to use incentive
     spirometry
        Hold the spirometer upright
        Teach patient to exhale first and seal the lips
         tightly around the mouthpiece
        Take in a slow, deep breath to elevate the balls or
         cylinder. Hold the breath initially for 2 seconds
         and then increasing to 6 seconds.
        Repeat the procedure four or five times hourly.
         Practice increases inspiratory volume, maintains
         alveolar ventilation and prevents atelectasis.
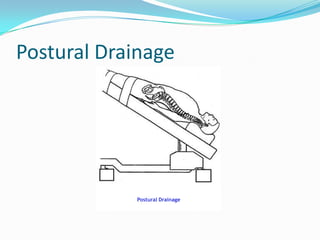
Postural Drainage
 Administer postural drainage
    This is drainage by gravity of secretions from various lung segments
    Scheduled 2-3 times daily before meals and at bedtime
    Before the procedure, patient may be given a bronchodilator
     medication or nebulization therapy to loosen the secretions
    Sequence: positioning, percussion, vibration, and removal of secretions
     by coughing or suction. Positions are assumed for 10-15 minutes
     depending on patient’s tolerance
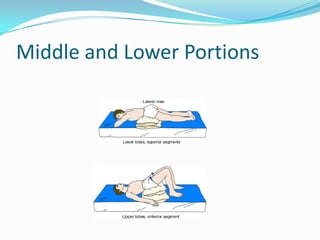
    Position for draining middle to lower lung field: head is lower than a
     chest; patient may be placed in Trendelenburg position
    Position for draining upper lung field: sitting position at about 45
     degrees
    Postural drainage should not be performed on pregnant women; on
     those with rib or chest injuries; on those with dizziness, fainting, head
     or neck injuries; on those with pulmonary embolism or abdominal
     surgery
Postural Drainage


          Postural Drainage
               Postural Drainage
Middle and Lower Portions
Postural Drainage
    •Upper portions of lungs
        •Sitting position at about a 45 angle


                    Sitting position at about 45 degrees
Postural Drainage
  When you are in the proper postural drainage position,
  change your position while following this sequence:


    1. Turn side to side


                              2. Lay on stomach


  Remain in each position approximately five to   3. Lay on back
  ten minutes. Use suction or assisted cough
  before changing position.
Postural Drainage
  Nursing Management
  Should not be performed in:

           Pregnant women           Patients with rib or chest injuries


            Patients with dizziness, fainting, head or neck injuries


           Patients with pulmonary embolism or abdominal surgery

     Increase oral fluid intake to liquefy secretions
     Reinforce coughing and deep breathing exercises
Constipation
 Constipation is due to stasis of fecal
  material in the rectum and sympathetic
  nervous system activity
 May present as ribbon-like diarrhea and
  fecal smearing
 Nursing Measures:
   Promote ambulation early
   encourage high fiber, high fluid diet
   Ensure privacy with the use of bedpan or
    commode
   Administer stool softeners as necessary
Urinary Stasis
          Immobility leads to inability to
           completely empty the bladder
          Leads to urinary tract infection and
           renal calculi formation
          Nursing Measures:
            Have patient void in normal position,
             if possible
            Low calcium diet, increase fluid intake
             and increase acid ash residue
Sensory Input                           Depression
  Changes                            • Encourage self care that starts
• This may lead to confusion and     with simple gross activities then
disorientation                       advancing to complex, fine motor
                                     movements
• Orient patient frequently and      • Support patient with positive
place clock/ calendar within sight   feedback for his efforts and
                                     accomplishments
                                     • Schedule OT and allow visitors as
                                     appropriate
ASSISTIVE DEVICES
 Crutches
    Height of crutch – measure two to three fingers or 2.5 -5
     cm below the axilla
    Patient should support weight on the handpiece and not
     at the axilla: to prevent brachial plexus palsy
    Tripod stance: proper standing position with crutches;
     crutches are placed about 15 cm (6 inches) infront of the
     feet and out laterally, about 15 cm, creating a wide base
    Elbows should be flexed at 20 -30 degrees angle for
     correct placement of hand grips
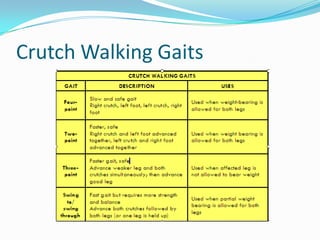
Crutch Walking Gaits
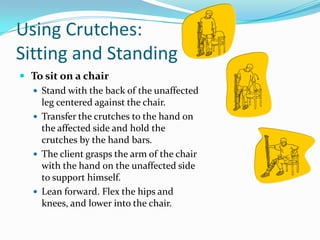
Using Crutches:
Sitting and Standing
 To sit on a chair
   Stand with the back of the unaffected
    leg centered against the chair.
   Transfer the crutches to the hand on
    the affected side and hold the
    crutches by the hand bars.
   The client grasps the arm of the chair
    with the hand on the unaffected side
    to support himself.
   Lean forward. Flex the hips and
    knees, and lower into the chair.
 stand up from a chair
    Hold the hand grips of both
     crutches in one hand.
    Push off from the chair with
     the other hand.
    Stand and check your balance.
Crutch walking Gaits

      Note:        To go up stairs, advance good
                   leg first followed by crutches
                          and affected leg.


          To go down stairs, advance
          crutches with affected leg
          first, followed by good leg.


       “Up with the good, down with the bad”
       “Up                              bad”
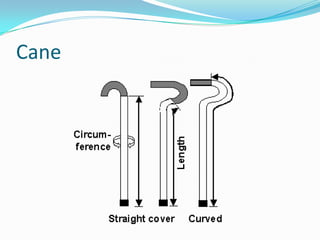
Cane
Cane
 Types: straight cane and quad cane
 Tips should have concentric rings as shock absorber and to
  provide optimal stability
 Flex elbow 20-30 degrees angle and hold handle
 Tip of cane should be 15 cm lateral to the base of the fifth
  toe
 Procedure:
      Hold cane on the good side
      Advance cane and affected leg
      Lean on cane when moving good leg
      When going up the stairs, follow “up with the good, down
       with the bad”
Walker
 Lift and move walker forward 8-10 inches
 With partial or non-weight bearing, put weight on
  wrists and arms and step forward with affected leg,
  supporting self on arms, and follow with good leg
 Nurse should stand behind patient, hold onto gait belt
  at waist as needed for balance
Mobility and Immobility