GAIT DEVIATIONS IN
TRANSTIBIAL PROSTHESIS
USERS
DR. JOE ANTONY
PHYSICAL MEDICINE AND
REHABILITATION
KGMU
CONTENTS
DR.
JOE
ANTONY
2
• BASICS OF GAIT
• Ranchos los amigos gait
terminology
• Kinematics
• Kinetics and muscle action
• DEVIATIONS IN
• Initial contact
• loading response
• Mid stance
• Terminal stance
• Preswing
• Swing phase
RANCHOS LOS AMIGOS
GAIT TERMINOLOGY
Stance
Phase
Starting
point
End point
Initial
contact
Foot comes in contact with
ground
Loading
response
Initial
contact
C/l foot
leaves
ground
Mid stance C/l foot
leaves
ground
I/l heel leave
the ground
Terminal
stance
I/l heel leave
the ground
C/l initial
contact
3
DR.
JOE
ANTONY
RANCHOS LOS AMIGOS GAIT
TERMINOLOGY
Swing
Phase
Starting
point
End point
Initial
swing
Foot
leaving the
ground
I/l foot in
alignment
with C/l
Ankle
Mid swing I/l foot in
alignment
with C/l
Ankle
I/l tibia
become
vertical
Terminal I/l tibia Initial
4
DR.
JOE
ANTONY
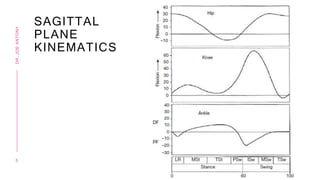
SAGITTAL
PLANE
KINEMATICS
5
DR.
JOE
ANTONY
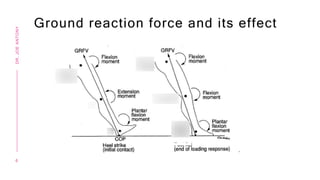
Ground reaction force and its effect
6
DR.
JOE
ANTONY
KINETICS AND MUSCLE ACTION
7
DR.
JOE
ANTONY
Initial contact and loading response Mid stance progression
8
DR.
JOE
ANTONY
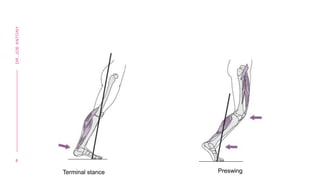
Terminal stance Preswing
INITIAL
CONTACT
• Initial contact with the heel
• Normal toe out angle is kept at 5-10
degree, heel-to-toe progression
through lateral border
• Knee maintained in 5-10 flexion
• Stride length equal to that of the
9
DR.
JOE
ANTONY
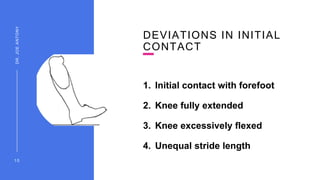
DEVIATIONS IN INITIAL
CONTACT
1. Initial contact with forefoot
2. Knee fully extended
3. Knee excessively flexed
4. Unequal stride length
1 0
DR.
JOE
ANTONY
INITIAL CONTACT WITH FOREFOOT
Causes Solution
Excessive plantar
flexion of
prosthetic feet
Realignment of feet
Restricted ROM of
extension ( knee
flexion contracture)
Exercises to
improve ROM,
adjust the socket to
accommodate the
contracture
1 1
DR.
JOE
ANTONY
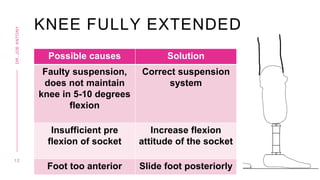
KNEE FULLY EXTENDED
Possible causes Solution
Faulty suspension,
does not maintain
knee in 5-10 degrees
flexion
Correct suspension
system
Insufficient pre
flexion of socket
Increase flexion
attitude of the socket
Foot too anterior Slide foot posteriorly
1 2
DR.
JOE
ANTONY
KNEE EXCESSIVELY FLEXED
(GREATER THAN 10DEGREES)
Possible causes Solution
Faulty suspension
(maintain knee in greater
than 10 degree flexion)
Correct suspension
system
Flexion contracture Evaluate ROM then decide
• Accommodate if less
than 20 degree
• Stretch the hamstrings
• Surgical correction of
deformity
1 3
DR.
JOE
ANTONY
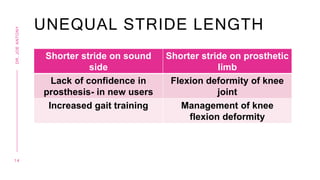
UNEQUAL STRIDE LENGTH
Shorter stride on sound
side
Shorter stride on prosthetic
limb
Lack of confidence in
prosthesis- in new users
Flexion deformity of knee
joint
Increased gait training Management of knee
flexion deformity
1 4
DR.
JOE
ANTONY
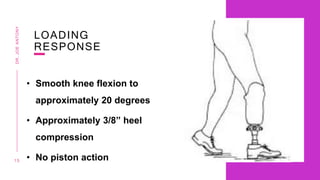
LOADING
RESPONSE
• Smooth knee flexion to
approximately 20 degrees
• Approximately 3/8” heel
compression
• No piston action
1 5
DR.
JOE
ANTONY
DEVIATIONS IN
LOADING
RESPONSE
• Abrupt knee flexion
• Knee remains extended
• Piston action
1 6
DR.
JOE
ANTONY
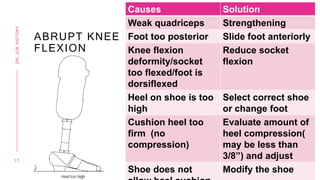
ABRUPT KNEE
FLEXION
Causes Solution
Weak quadriceps Strengthening
Foot too posterior Slide foot anteriorly
Knee flexion
deformity/socket
too flexed/foot is
dorsiflexed
Reduce socket
flexion
Heel on shoe is too
high
Select correct shoe
or change foot
Cushion heel too
firm (no
compression)
Evaluate amount of
heel compression(
may be less than
3/8”) and adjust
Shoe does not Modify the shoe
1 7
DR.
JOE
ANTONY
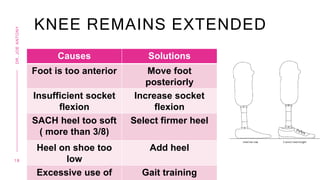
KNEE REMAINS EXTENDED
Causes Solutions
Foot is too anterior Move foot
posteriorly
Insufficient socket
flexion
Increase socket
flexion
SACH heel too soft
( more than 3/8)
Select firmer heel
Heel on shoe too
low
Add heel
Excessive use of Gait training
1 8
DR.
JOE
ANTONY
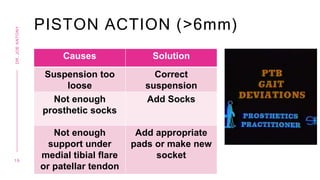
PISTON ACTION (>6mm)
Causes Solution
Suspension too
loose
Correct
suspension
Not enough
prosthetic socks
Add Socks
Not enough
support under
medial tibial flare
or patellar tendon
Add appropriate
pads or make new
socket
1 9
DR.
JOE
ANTONY
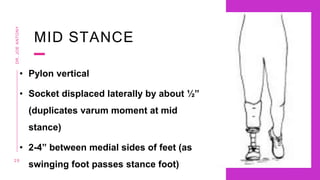
MID STANCE
• Pylon vertical
• Socket displaced laterally by about ½”
(duplicates varum moment at mid
stance)
• 2-4” between medial sides of feet (as
swinging foot passes stance foot)
2 0
DR.
JOE
ANTONY
DEVIATIONS IN
MID STANCE
1. Pylon leans medially
2. Pylon leans laterally
3. ½” varus moment not apparent
4. Varus moment excessive
5. Less than two inches between feet at mid
stance
6. Greater than four inches between feet at mid
2 1
DR.
JOE
ANTONY
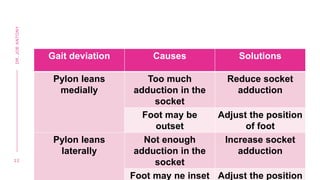
Gait deviation Causes Solutions
Pylon leans
medially
Too much
adduction in the
socket
Reduce socket
adduction
Foot may be
outset
Adjust the position
of foot
Pylon leans
laterally
Not enough
adduction in the
socket
Increase socket
adduction
Foot may ne inset Adjust the position
2 2
DR.
JOE
ANTONY
Deviations Causes Solutions
½” varus
moment not
apparent (for
some
patients who
cannot
control varus
force, this is
desirable)
Foot
relatively
outset
Inset foot
Varus
moment
excessive (
more than ½”
Foot too inset Reduce foot
inset
Socket ML Reduce
2 3
DR.
JOE
ANTONY
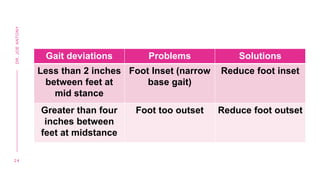
Gait deviations Problems Solutions
Less than 2 inches
between feet at
mid stance
Foot Inset (narrow
base gait)
Reduce foot inset
Greater than four
inches between
feet at midstance
Foot too outset Reduce foot outset
2 4
DR.
JOE
ANTONY
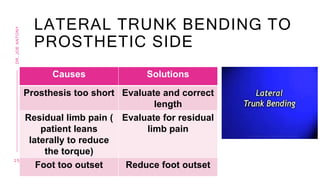
LATERAL TRUNK BENDING TO
PROSTHETIC SIDE
Causes Solutions
Prosthesis too short Evaluate and correct
length
Residual limb pain (
patient leans
laterally to reduce
the torque)
Evaluate for residual
limb pain
Foot too outset Reduce foot outset
2 5
DR.
JOE
ANTONY
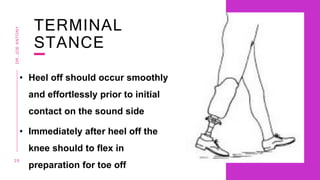
TERMINAL
STANCE
• Heel off should occur smoothly
and effortlessly prior to initial
contact on the sound side
• Immediately after heel off the
knee should to flex in
preparation for toe off
2 6
DR.
JOE
ANTONY
DEVIATIONS IN
TERMINAL
STANCE
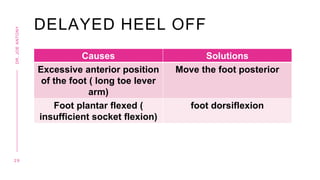
1. Heel-off occurs early
2. Heel-off is delayed
2 7
DR.
JOE
ANTONY
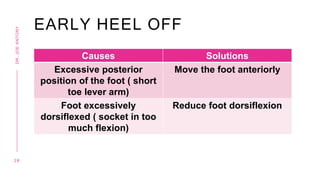
EARLY HEEL OFF
Causes Solutions
Excessive posterior
position of the foot ( short
toe lever arm)
Move the foot anteriorly
Foot excessively
dorsiflexed ( socket in too
much flexion)
Reduce foot dorsiflexion
2 8
DR.
JOE
ANTONY
DELAYED HEEL OFF
2 9
DR.
JOE
ANTONY
Causes Solutions
Excessive anterior position
of the foot ( long toe lever
arm)
Move the foot posterior
Foot plantar flexed (
insufficient socket flexion)
foot dorsiflexion
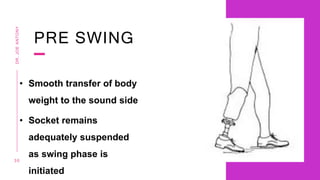
PRE SWING
• Smooth transfer of body
weight to the sound side
• Socket remains
adequately suspended
as swing phase is
initiated
3 0
DR.
JOE
ANTONY
DEVIATIONS IN
PRE SWING
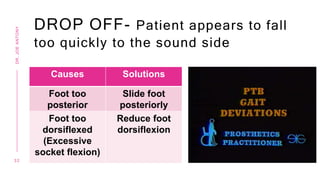
1. Drop off
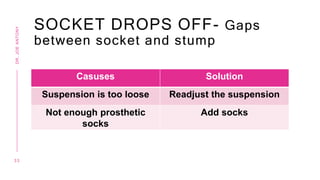
2. Socket drops away from
the residual limb
3 1
DR.
JOE
ANTONY
DROP OFF- Patient appears to fall
too quickly to the sound side
Causes Solutions
Foot too
posterior
Slide foot
posteriorly
Foot too
dorsiflexed
(Excessive
socket flexion)
Reduce foot
dorsiflexion
3 2
DR.
JOE
ANTONY
SOCKET DROPS OFF- Gaps
between socket and stump
Casuses Solution
Suspension is too loose Readjust the suspension
Not enough prosthetic
socks
Add socks
3 3
DR.
JOE
ANTONY
SWING
PHASE
• During initial swing the heel of the foot should accelerate
smoothly with no tendency to “whip” medially or laterally
• During mid swing the foot should swing through without
touching the floor. The patient should not have to exert
extra effort to assure clearance
3 4
DR.
JOE
ANTONY
DEVIATIONS IN
SWING PHASE
1. Foot whips medially or laterally
during initial swing
2. Prosthetic foot touches the
floor during mid swing
3 5
DR.
JOE
ANTONY
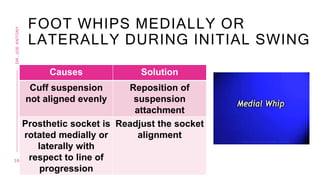
FOOT WHIPS MEDIALLY OR
LATERALLY DURING INITIAL SWING
Causes Solution
Cuff suspension
not aligned evenly
Reposition of
suspension
attachment
Prosthetic socket is
rotated medially or
laterally with
respect to line of
progression
Readjust the socket
alignment
3 6
DR.
JOE
ANTONY
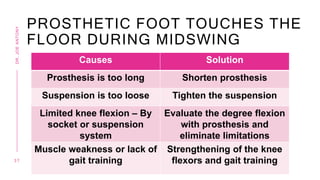
PROSTHETIC FOOT TOUCHES THE
FLOOR DURING MIDSWING
Causes Solution
Prosthesis is too long Shorten prosthesis
Suspension is too loose Tighten the suspension
Limited knee flexion – By
socket or suspension
system
Evaluate the degree flexion
with prosthesis and
eliminate limitations
Muscle weakness or lack of
gait training
Strengthening of the knee
flexors and gait training
3 7
DR.
JOE
ANTONY
3 8
DR.
JOE
ANTONY
References
• Braddoms textbook of PMR 21st edition
• Orthotics and Prosthotics in rehabilitation, Kevin K chui, 4 th
edition
• Atlas of orthosis and assistive devices , 4th edition, AAOS
THANK YOU