Prevention of osteoporosis in
     early menopause
            Dr. Santiago Palacios
              Antonio Acuña, 9
                28009 Madrid
           Phone: +34 91 578 05 17
   E-mail: ipalacios@institutopalacios.com
Diapositivas/Slides


www.institutopalacios.com
• CONCEPT
• EFFECT OF ESTROGEN DEFICIENCY ON
  BONE LOSS
• BONE LOSS AFTER NATURAL
  MENOPAUSE
• EFFECT OF EARLY MENOPAUSE ON BMD
• EARLY MENOPAUSE AND FRACTURES
• PREVENTION
• CONCLUSIONS
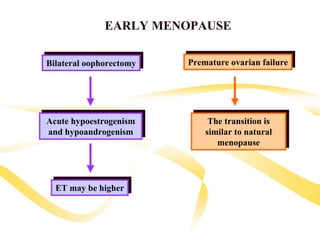
EARLY MENOPAUSE

Bilateral oophorectomy
Bilateral oophorectomy   Premature ovarian failure
                         Premature ovarian failure


Acute hypoestrogenism
Acute hypoestrogenism          The transition is
                              The transition is
 and hypoandrogenism
and hypoandrogenism           similar to natural
                             similar to natural
                                 menopause
                                menopause


  ET may be higher
  ET may be higher
BILATERAL OOPHORECTOMY


Ovarian, endometrial or fallopian tube
cancers
Severe endometriosis
Bilateral tubo-ovarian abscess
Familial breast-ovarian cancer syndrome
Severe premenstrual syndrome
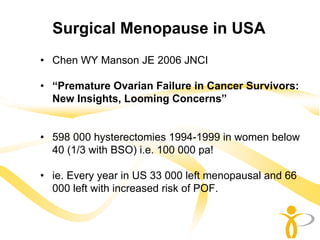
Surgical Menopause in USA
• Chen WY Manson JE 2006 JNCI

• “Premature Ovarian Failure in Cancer Survivors:
  New Insights, Looming Concerns”


• 598 000 hysterectomies 1994-1999 in women below
  40 (1/3 with BSO) i.e. 100 000 pa!

• ie. Every year in US 33 000 left menopausal and 66
  000 left with increased risk of POF.
PREMATURE OVARIAN FAILURE


 Is the development of amenorrhea with
Is the development of amenorrhea with
 concomitant sex hormone deficiency and
concomitant sex hormone deficiency and
 elevated serum gonadotropin levels before
elevated serum gonadotropin levels before
 age of 40 years?
age of 40 years?
Clinical Definitions
• Abnormal Menses: a history of at least 3
  consecutive months of oligomenorrhea or
  abnormal uterine bleeding.
• Evidence of Reduced Fecundity: the development
  of fewer than 5 follicles (>15 mm) after
  appropriate gonadotropin stimulation (300 IU/day)
  or no pregnancy after one year of unprotected
  intercourse.
• Elevated FSH: above the normal limit (95% CI)
  for the early follicular phase (days 2 to 5) as
  defined by the assay employed.
PREMATURE OVARIAN FAILURE
STUDY OF WOMEN ACROSS THE NATION (SWAN)

                             CAUCASIAN                   1.0%

                    AFRICAN – AMERICAN                   1.4%

                                 LATIN                   1.4%

                               CHINESE                   0.5%

                              JAPANESE                   0.1%


~ 70.000 women in Spain who have experienced premature ovarian failure

 Coulam CB et al. Obstet Gynecol. 1986 Apr;67(4):604-6
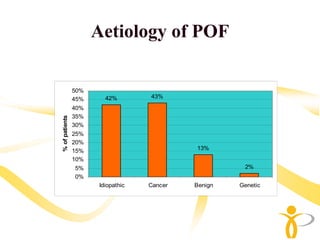
Aetiology of POF

                50%
                45%     42%        43%

                40%
                35%
% of patients


                30%
                25%
                20%
                15%                         13%
                10%
                5%                                    2%
                0%
                      Idiopathic   Cancer   Benign   Genetic
• CONCEPT
• EFFECT OF ESTROGEN DEFICIENCY ON
  BONE LOSS
• BONE LOSS AFTER NATURAL
  MENOPAUSE
• EFFECT OF EARLY MENOPAUSE ON BMD
• EARLY MENOPAUSE AND FRACTURES
• PREVENTION
• CONCLUSIONS
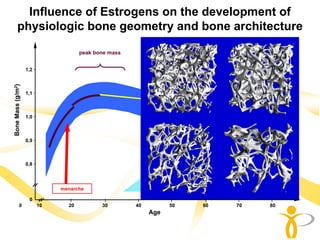
Influence of Estrogens on the development of
       physiologic bone geometry and bone architecture
                                                             menopause
                                       peak bone mass
                                                                   „norma
                   1,2 -                                             l“
Bone Mass (g/m2)


                   1,1 -


                   1,0 -


                   0,9 -                                                                     mean
                                                                                              SD

                   0,8 -

                                                                             fracture
                                                                            threshold
                                menarche

                     0     I       I           I        I           I            I      I     I
            0              10     20          30        40         50           60      70   80
                                                             Age
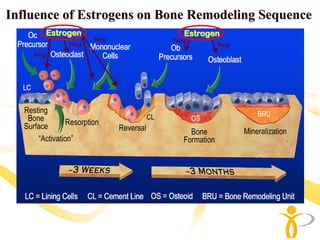
Influence of Estrogens on Bone Remodeling Sequence
      Estrogen               Estrogen
                 Neg       Neg
           Neg   .                  Neg
                           .
           .                        .
    Neg
    .
• CONCEPT
• EFFECT OF ESTROGEN DEFICIENCY ON
  BONE LOSS
• BONE LOSS AFTER NATURAL
  MENOPAUSE
• EFFECT OF EARLY MENOPAUSE ON BMD
• EARLY MENOPAUSE AND FRACTURES
• PREVENTION
• CONCLUSIONS
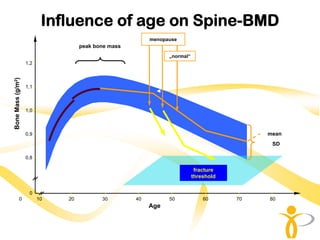
Influence of age on Spine-BMD
                                                             menopause
                                       peak bone mass
                                                                   „normal“
                   1,2 -
Bone Mass (g/m2)


                   1,1 -


                   1,0 -


                   0,9 -                                                                       mean
                                                                                                SD

                   0,8 -

                                                                               fracture
                                                                              threshold


                     0     I      I            I        I           I              I      I     I
            0              10     20          30        40         50             60      70   80
                                                             Age
Age-adjusted RR for Spine and Hip-Fracture
                in Relation to endogenous Serum E2-Levels
                1,00
                                                Hip-Fracture      Spine-Fracture
                       1.0   1.0

                0,75                   Independent of BMD
Relative Risk


                0,50                                              0.5          0.5
                                        0.4     0.4
                                                            0.3                      0.3
                0,25


                0,00
                       <5                 5-6                     7-9                  >9
                                   Endogenous Serum Estradiol Level [pg/ml]


                                              Cummings et al. (1998); NEJM Vol 339 No 11, 733-740
• CONCEPT
• EFFECT OF ESTROGEN DEFICIENCY ON
  BONE LOSS
• BONE LOSS AFTER NATURAL
  MENOPAUSE
• EFFECT OF EARLY MENOPAUSE ON BMD
• EARLY MENOPAUSE AND FRACTURES
• PREVENTION
• CONCLUSIONS
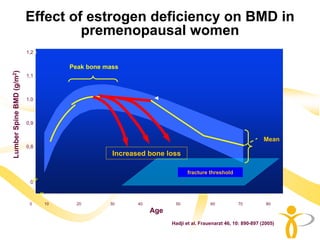
Effect of estrogen deficiency on BMD in
                                   premenopausal women
                          1,2-


                                      Peak bone mass
Lumber Spine BMD (g/m2)


                          1,1-


                          1,0-


                          0,9-


                                                                                                        SD Mean
                          0,8-
                                                  Increased bone loss

                                                                           fracture threshold
                           0


                           0     10     20       30      40          50              60          70           80
                                                              Age
                                                                    Hadji et al. Frauenarzt 46, 10: 890-897 (2005)
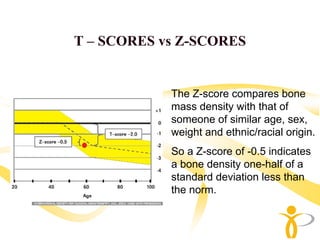
T – SCORES vs Z-SCORES


            The Z-score compares bone
            mass density with that of
            someone of similar age, sex,
            weight and ethnic/racial origin.
            So a Z-score of -0.5 indicates
            a bone density one-half of a
            standard deviation less than
            the norm.
PREMATURE OVARIAN FAILURE
  Peak bone mass reaches
  its maximum between ages
  20 to 29 years
  Up to 60% of adult total
  bone mineral is acquired
  during adolescence
  There are no normative tables
  for women <25 years

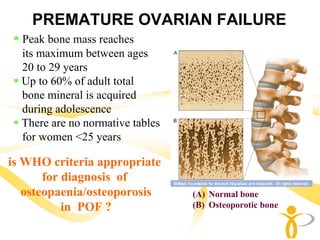
is WHO criteria appropriate
       for diagnosis of
   osteopaenia/osteoporosis       (A) Normal bone
           in POF ?               (B) Osteoporotic bone
Current T scores are invalid diagnostic markers of bone density in young
POF patients
POF patients require their own group specific baseline BMD values
The rising incidence of premature ovarian failure in an increasingly younger
age group warrants re-evaluation of our diagnostic criteria to facilitate
management of reduced bone mass in this vulnerable patient group.

ALTERNATIVES:
    Quantitative computed tomography (QCT)
 - evaluate bone in 3 dimensions, ‘gold standard’, primarily for research
    Quantitative ultrasound
  - no radiation exposure, inexpensive, lack adequate normative databases
    Magnetic resonance imaging
 - radiation-free, evaluate bone geometry AND quality, lack normative databases
• CONCEPT
• EFFECT OF ESTROGEN DEFICIENCY ON
  BONE LOSS
• BONE LOSS AFTER NATURAL
  MENOPAUSE
• EFFECT OF EARLY MENOPAUSE ON BMD
• EARLY MENOPAUSE AND FRACTURES
• PREVENTION
• CONCLUSIONS
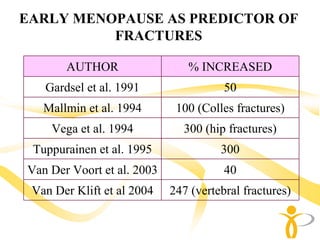
EARLY MENOPAUSE AS PREDICTOR OF
          FRACTURES

       AUTHOR                  % INCREASED
   Gardsel et al. 1991                 50
   Mallmin et al. 1994       100 (Colles fractures)
    Vega et al. 1994          300 (hip fractures)
 Tuppurainen et al. 1995              300
Van Der Voort et al. 2003              40
 Van Der Klift et al 2004   247 (vertebral fractures)
OOPHORECTOMY AS PREDICTOR OF
               FRACTURE


 (1) Women younger than
                                                    Fracture %
       age 45 years
         Oophorectomy                                        39

  Histerectomy (non oop.)                                    24

      Natural menopause                                      21
  (2) Oophorectomy after                      Equal than natural
        menopause                                menopause

(1)   Johansson C et al. Maturitas 1993;17:39-50
(2)   Antoniucci DM et al. J Bone Miner Res 2005;20:741-47
• CONCEPT
• EFFECT OF ESTROGEN DEFICIENCY ON
  BONE LOSS
• BONE LOSS AFTER NATURAL
  MENOPAUSE
• EFFECT OF EARLY MENOPAUSE ON BMD
• EARLY MENOPAUSE AND FRACTURES
• PREVENTION
• CONCLUSIONS
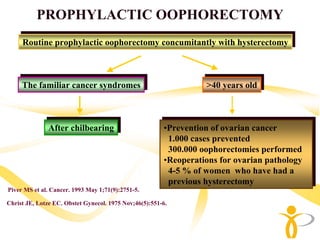
PROPHYLACTIC OOPHORECTOMY
     Routine prophylactic oophorectomy concumitantly with hysterectomy
     Routine prophylactic oophorectomy concumitantly with hysterectomy


     The familiar cancer syndromes
     The familiar cancer syndromes                                 >40 years old
                                                                  >40 years old


               After chilbearing
               After chilbearing                         •Prevention of ovarian cancer
                                                        •Prevention of ovarian cancer
                                                           1.000 cases prevented
                                                          1.000 cases prevented
                                                           300.000 oophorectomies performed
                                                          300.000 oophorectomies performed
                                                         •Reoperations for ovarian pathology
                                                        •Reoperations for ovarian pathology
                                                          4-5 % of women who have had aa
                                                           4-5 % of women who have had
                                                           previous hysterectomy
                                                          previous hysterectomy
Piver MS et al. Cancer. 1993 May 1;71(9):2751-5.

Christ JE, Lotze EC. Obstet Gynecol. 1975 Nov;46(5):551-6.
Principles of Hormone Replacement in early
                menopause
 Estrogen replacement is first line treatment


 1)Pre pubertal : To induce development of secondary
 sexual characteristics

 2)To relieve the immediate sequelae of menopause i.e.
 symptom relief and quality of life

 3)To prevent the long term sequelae of the menopause

 4)To create an environment conducive to the successful
 replacement of donated embryos
Early menopause
              Therapeutic Options
• Route / Type HRT

• Choice of oestrogen route of administration must be made
  on individual basis

• No controlled studies regarding the ideal hormone
  replacement strategy for women with premature
  ovarian failure

  In principle, non oral E2 / progesterone preparations
  can be better monitored but what is ideal E2 level?
HRT preparations in Early
              menopause

• Progestogenic opposition if uterus present
   – Even after radiotherapy

• Aim for minimum effective oral dose or local
  opposition with Mirena / Crinone / Cyclogest

• ?Aim for natural progesterone replacement
Timing of HRT Usage
• Management
  – Liaise with gynae oncologists / medical oncologists /
    haematologists re time to start

   – Immediately if curative procedure (after hist diagn)

   – Delay (1 year disease free interval) if oestrogen
     sensitive tumour e.g. endometrial carcinoma

   – Treat at least until average age of menopause

   – HRT “holidays” to test ovarian function
Hormonal Replacement Therapy
• Hormonal therapy would seem warranted for women – to
  eliminate symptoms and prevent bone loss; data from the WHI
  do not apply.
• Abundant data indicate that E/P in any form does not prevent
  ovulation and pregnancy – for unclear reasons. Thus, barrier
  contraception may be warranted.
• Young women without ovarian function may require more
  estrogen than older women to alleviate symptoms of estrogen
  deficiency.
• There are virtually no data regarding the safety and efficacy of
  E/P in women with POF.
Premature Ovarian Failure
                         Therapeutic Options


  • Combined oral contraceptive pill


       – “Use of ethinylestradiol has been driven by
         practicalities rather than science”

                  » Conway et al (1996)

                                                 33 West London
17th Nov 2005                                  Menopause & PMS
                                                          Centre
Premature Ovarian Failure
                                      Therapeutic Options


• Combined Pill v HRT
    – 0.625mg v 30mcg EE in 17 adult women with Turner’s
      Syndrome

    – 6 month cross over study :Hormones, Lipids, Bone
      Turnover etc

    – FSH most suppressed by EE, BUT HRT was superior at
      minimising hyperinsulinaemia & bone turnover

 Guttman et al Clin Endocrinol 2001                West London Menopause & PMS Centre
Questions for Gynecologists, ACOG 2003-5: Would
 you give a woman with idiopathic POF hormone
                 therapy (HT)?

                 • Yes – 94%
                  • No – 6%
Questions for Gynecologists, ACOG 2003-5: What
form of HT would you administer to women with
                     POF?

•   Combination oral contraceptives   60%
•   Continuous combined HT             16%
•   Sequential HT                      22%
•   No therapy                           1%
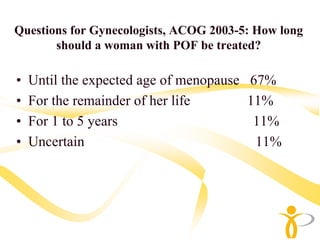
Questions for Gynecologists, ACOG 2003-5: How long
       should a woman with POF be treated?

•   Until the expected age of menopause 67%
•   For the remainder of her life       11%
•   For 1 to 5 years                     11%
•   Uncertain                            11%
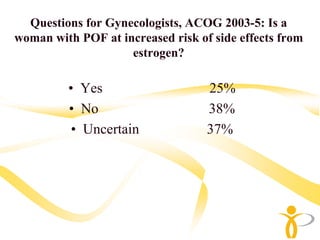
Questions for Gynecologists, ACOG 2003-5: Is a
woman with POF at increased risk of side effects from
                    estrogen?

         • Yes                     25%
         • No                      38%
          • Uncertain              37%
Additional Treatment in POF

• Addition of exogenous androgen?
• Recommendations to prevent osteoporosis are
  warranted:
  – Calcium 1200-1500 mg/day
  – Daily weight bearing exercise
  – Daily vitamin D
Fertility Options in women at risk of POF
• Surgery
   – Ovarian transposition

   – Ovarian Tissue Cryopreservation
        • Transplantation – e.g. (Donnez 2004, Chaim Sheba Medical
          Centre Israel 2005, Oktay 2006)

• IVF
   – Own Embryo Cryopreservation
   – Own Oocyte Cryopreservation (1st pregnancy 2001)
• CONCEPT
• EFFECT OF ESTROGEN DEFICIENCY ON
  BONE LOSS
• BONE LOSS AFTER NATURAL
  MENOPAUSE
• EFFECT OF EARLY MENOPAUSE ON BMD
• EARLY MENOPAUSE AND FRACTURES
• PREVENTION
• CONCLUSIONS
FUTURE RESEARCH IN WOMEN UNDERGOING
            PREMATURE MENOPAUSE


     1.     Is premature menopause a deficiency disease
            requiring physiologic replacement?
     2.     Should be treated with exogenous E with or without
            progestin?
     3.     What form of HT is most appropiate?
     4.     For how long should HT be administrated?
     5.     How safe is HT in women with premature versus
            natural menopause?

Hendrix SL. Am J Med. 2005 Dec 19;118(12 Suppl 2):131-5.
Future Objectives:

• Need to merge data over the long term to look at
  quality of life / fertility outcomes / osteoporosis / CV
  disease


• POF patients should therefore remain under long term
  follow up