






























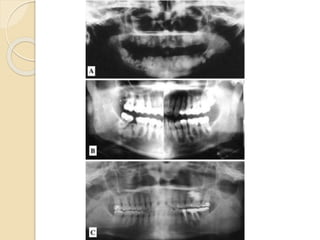

















FIBRO-OSSEOUS LESIONS 
“The term fibro-osseous lesion (FOL) is a 
generic designation of a group of jaw 
disorders” characterized by the 
replacement of bone by a benign 
connective tissue matrix. 
This matrix displays varying degrees of 
mineralization in the form of woven bone 
or of cementum-like round acellular 
intensely basophilic structures.
Classification 
Charles Waldron Classification Of The Fibro-Osseous Lesions Of 
The Jaws (1985) 
1. Fibrous Dysplasia 
a. Monostotic 
b. Polyostotic 
2. Fibro-Osseous (Cemental) Lesions Presumably Arising In The 
Periodontal Ligament 
a. Periapical Cemental Dysplasia 
b. Localized Fibro-Osseous-Cemental Lesions (Probably Reactive In 
Nature) 
c. Florid Cement-Osseous Dysplasia (Gigantiform Cementoma) 
d. Ossifying & Cemenifying Fibroma 
3. Fibro-Osseous Neoplasms Of Uncertain Or Detectable Relationship 
To Those Arising In The Periodontal Ligament (Category II) 
a. Cemetoblastoma, Osteoblastoma & Osteoid Osteoma 
b. Juvenile Active Ossifying Fibroma & Other So Called Aggressive, Active 
Ossifying /Cementifying Fibromas.
Eversole Classification, 2008
 By definition, all benign fibro-osseous 
lesions possess an osseous and fibrous 
tissue component.
 The ossifications in BFOL can be quite 
heterogeneous even within a specific 
disease entity. 
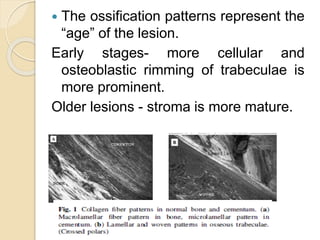
 Newly formed bone - woven pattern of 
collagen fiber orientation. 
 Mature bone - lamellar pattern. 
 Many have both irregular trabeculae 
as well as spheroidal cementicle 
calcifications, so called “ Cemento-ossifying” 
lesions.
 The ossification patterns represent the 
“age” of the lesion. 
Early stages- more cellular and 
osteoblastic rimming of trabeculae is 
more prominent. 
Older lesions - stroma is more mature.
FIBROUS DYSPLASIA 
 Lichtenstein,1938 
 It is a disease of bone maturation and 
remodeling in which the normal medullary 
bone and cortices are replaced by a 
disorganized fibrous woven bone. 
 The resultant fibro-osseous bone is more 
elastic and structurally weaker than the 
original bone. 
 Caused by postzygotic mutation in the 
GNAS1 gene. 
 Mutations of the GSa gene 
 No hereditary influence.
Investigation of the GSa gene in 
the diagnosis of fibrous 
dysplasia 
 Done by direct sequencing of the Gsa 
gene. 
 High prevalence of GSa gene 
mutations in fibrous dysplasia. 
Int. J. Oral Maxillofac. Surg. 2004; 33: 498–501 
Oral Surg Oral Med Oral Pathol Oral Radiol Endod 2011;111:618- 
626
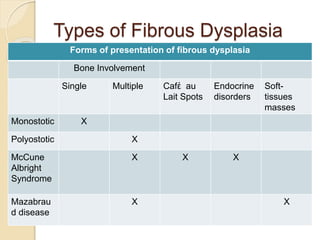
Types of Fibrous Dysplasia 
Forms of presentation of fibrous dysplasia 
Bone Involvement 
Single Multiple Cafἐ au 
Lait Spots 
Endocrine 
disorders 
Soft-tissues 
masses 
Monostotic X 
Polyostotic X 
McCune 
Albright 
Syndrome 
X X X 
Mazabrau 
d disease 
X X
 If the mutation occurs during early 
embryologic life 
Multiple bone lesions, Cutaneous 
pigmentation and endocrine 
disturbances
 If the mutation occurs during later 
stages 
Multiple bone lesions 
 If the mutation occurs during postnatal 
life 
Affects single bone
Monostotic Fibrous Dysplasia 
 Limited to a single bone. 
 Accounts for 80% to 85% of all cases 
 M:F = 1:1 
 Painless swelling. 
 Growth is generally slow but occasionally 
rapid. 
 Maxilla > Mandible. 
 60% of cases causes displacement of 
mandibular canal. 
 Often detected during the first two 
decades of life. 
Fibro-osseous Iesions of the jaws. J Oral MaxilIofac Surg 43:249, 1985
 Mandibular lesions are truly 
monostotic. 
 Maxillary lesions often involve 
adjacent bones(e.g., zygoma, 
sphenoid, occipital) 
Craniofacial Fibrous Dysplasia.
Polyostotic Fibrous dysplasia; 
Jaffe-Lichtenstein Syndrome; 
McCune – Albright Syndrome 
 Involvement of two or more bones. 
 When seen with cafἐ au lait 
pigmentation  Jaffe- Lichtenstein 
syndrome. 
 Polyostotic fibrous dysplasia + cafἐ au 
lait pigmentation + multiple 
endocrinopathies  McCune Albright 
Syndrome.
 Causes facial asymmetry. 
 Pathologic fractures with pain and 
deformity. 
 Leg length discrepency is common 
due to involvement of upper portion of 
the femur ( Hockey Stick deformity).
Radiographic Features 
 Depends upon the stage of the 
disease. 
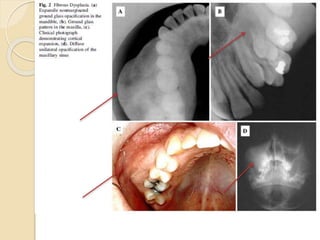
 Early onset lesions are radiolucent 
and later progressively calcify, 
culminating in a “Ground Glass” or 
Mottled Mixed radiolucent/ radiopaque 
pattern. 
 Critical feature to diagnosis- FD fails 
to manifest any discreate margins; 
rather, the lesional bone subtly blends 
into the surrounding normal appearing
Histopathology 
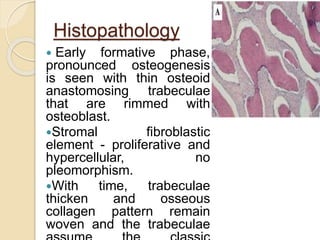
 Early formative phase, 
pronounced osteogenesis 
is seen with thin osteoid 
anastomosing trabeculae 
that are rimmed with 
osteoblast. 
Stromal fibroblastic 
element - proliferative and 
hypercellular, no 
pleomorphism. 
With time, trabeculae 
thicken and osseous 
collagen pattern remain 
woven and the trabeculae 
assume the classic
 Long-standing polyostotic FD is 
sarcomatous , which can occur in 
absence of radiation therapy. 
 Most frequent site - craniofacial 
skeleton. 
 Differentiating features on radiograph 
between sarcoma and FD are: 
◦ Permeative ill-defined borders, 
◦ Destroyed cortical outline and/or spiculated 
periosteal new bone formation 
◦ Periodontal ligament space widening.
Malignant Transformation of 
FD: 
 Occur in <1% of the cases. 
Osteosarcoma is the most common 
histologic type, followed by 
fibrosarcoma, chondrosarcoma, and 
malignant fibrohistiocytoma. 
Most common in the maxilla and 
mandible 
 Calvarium – rare involvement. 
Spontaneous Conversion of Fibrous Dysplasia 
Into Osteosarcoma(J Craniofac Surg 2011;22: 959 -961)
Treatment and Prognosis 
 Timing of intervention is based on the 
symptoms manifesting as a result of the 
disease. 
 Recommended treatment options can be 
divided into 4 categories: 
1. Observation 
2. Medical therapy 
3. Surgical remodelling 
4. Radical excision and reconstruction
1. Observation: 
 Monitoring is through serial radiographs, 
CT scans, and clinical examinations. In 
lesions that present in childhood, 
monitoring until skeletal maturity may 
allow for ultimately less radical treatment 
and less overall morbidity. 
 Special attention to cranial nerve 
function during monitoring of these 
lesions should be exercised 
 Decreased nerve function may be an 
indication for surgical therapy.
2. Medical treatment 
Currently, no medical therapy exists for the 
permanent cure of fibrous dysplasia. 
1. Biphosphonates. 
2. Systemic steroids
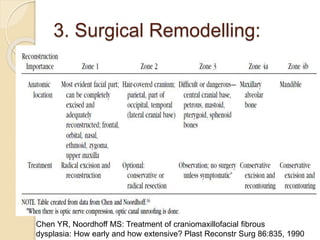
3. Surgical Remodelling: 
Chen YR, Noordhoff MS: Treatment of craniomaxillofacial fibrous 
dysplasia: How early and how extensive? Plast Reconstr Surg 86:835, 1990
4. Surgical Treatment 
Indications: 
 
Functional concern 
 
Facial recontouring 
 
Compression of the optic canal, recommended 
decompression 
Other indications for surgical therapy: 
 
Cosmetic Deformity 
 
Pain 
 
Pathologic Fracture 
 
Hearing Loss 
 
Sinus Or Nasal Obstruction 
 
Epistaxis 
 
Malocclusion and Impeded mastication.
Osteitis Deformans( Paget 
Disease) 
 Rapid turnover remodeling of bone 
throughout the skeleton. 
 Disease of the elderly. 
 Although two Paget-like bone 
dysplasias that arise during childhood.
Etiology 
 Defective function of the 
osteoprotegerin/TNFRSF11A or 
B/RANKL/RANK pathway, a molecular 
regulator of osteoclastogenesis.
Classic Paget Disease of Bone 
( CPDB) 
 Late adult onset. 
 Characterized by rapid turnover of bone 
remodeling and osseous expansion with 
progressive skeleton deformities. 
 Tubular bones show bowing and spinal 
curvature with vertebral collapse. 
 Elevated serum alkaline phosphatase, 
 Normal calcium and phosphorus levels. 
 Cranial nerve neuropathies can develop 
as a consequence of foramina 
narrowing. 
 Deafness
Radiographic Features 
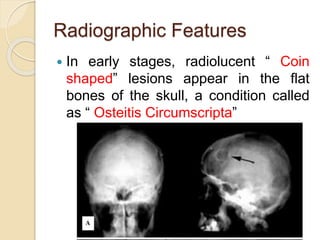
 In early stages, radiolucent “ Coin 
shaped” lesions appear in the flat 
bones of the skull, a condition called 
as “ Osteitis Circumscripta”
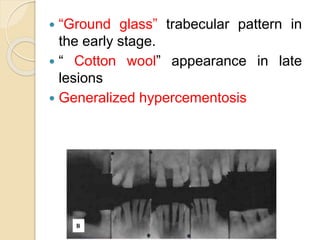
 “Ground glass” trabecular pattern in 
the early stage. 
 “ Cotton wool” appearance in late 
lesions 
 Generalized hypercementosis
Histological Features 
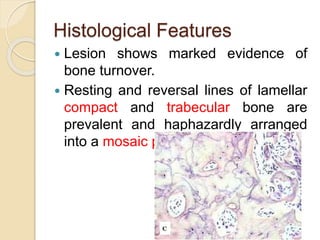
 Lesion shows marked evidence of 
bone turnover. 
 Resting and reversal lines of lamellar 
compact and trabecular bone are 
prevalent and haphazardly arranged 
into a mosaic pattern.
Neoplastic Transformation 
 Two neoplastic processes may occur 
1. Giant cell tumors 
2. Sarcomas( Osteogenic sarcoma, 
fibrosarcoma, chondrosarcoma and 
undifferentiated sarcoma)
Treatment 
 Biphosphonates 
 Histological appearance also appear 
more normal after drug therapy.
Juvenile Paget Disease 
(Idiopathic Hyperphosphatasia) 
 Inherited as an autosomal recessive 
trait 
 Deformities in the long bones, 
kyphosis, acetabular protrusion and 
pathophysiologically by rapid turnover. 
 Long bone widening with pathologic 
fracture and thickening of skull. 
 Elevated serum alkaline phosphatase 
 Osteopenia and skeletal deformity 
with bowed limbs
Familial Expansile Osteolysis( 
FEO) 
 Autosomal dominant trait 
 Manifest in the second decade 
 Osteoclastic resorption with cancellous 
bone expansion and elevated serum 
alkaline phosphatase. 
 Early tooth loss by external resorption 
 Deafness 
 Histologically - focal collection of 
multinucleated giant cells and viral-like 
inclusions.
Expansile Skeletal 
Hyperphosphatasia(ESH) 
 Autosomal dominant trait 
 Accelerated bone turnover with 
hyperostotic expansion of the long bones 
 Pain in phalanges 
 Premature tooth exfoliation and deafness 
 Episodic hypercalcemia 
 Absence of large osteolytic lesions with 
cortical thinning. 
 Elevated alkaline phosphatase. 
 No viral like inclusions.
Segmental Odontomaxillary 
Dysplasia 
 Lesion confined to a single segment of 
the maxilla, usually in premolar and 
molar. 
 Clinical Features: 
◦ Teeth fail to erupt 
◦ Dental anomalies like- malformed, mis 
shapened and/ or teeth of anomalous 
size. 
 Expansion of alveolar bone
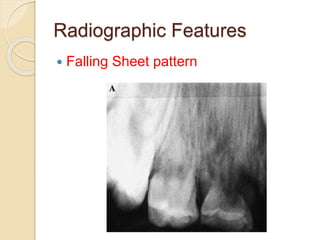
Radiographic Features 
 Falling Sheet pattern
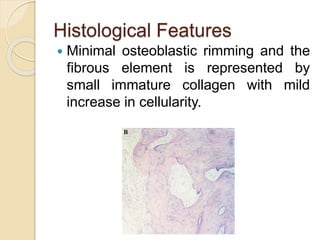
Histological Features 
 Minimal osteoblastic rimming and the 
fibrous element is represented by 
small immature collagen with mild 
increase in cellularity.
Cemento-Osseus Dysplasia 
 These conditions are defined by 
specific clinical and pathological 
features and have been classified as 
Cemento-Osseus Dysplasia 
 Periapical Cemental Dysplasia 
 Focal Cemento-Osseus Dysplasia 
 Florid Osseous Dysplasia
 Precise etiology is unknown. 
 Disorders of metabolism of cells 
normally involved in production of 
bone and cementum matrices. 
 The aberrant activity of the tissues 
may be the result of an unusual 
response to undefined local factors.
Periapical Cemental Dysplasia 
 Seen at the apices of the teeth with vital , non-inflamed 
pulps. 
 Predominantly involves mandibular incisors. 
 Usually detected incidentally on routine 
radiographic examination. 
Radiographic Examination 
 Consist of multiple round to ovoid , radiolucent 
lesions at the apex of the vital teeth. 
 May mimic periapical pathology of pulpal origin. 
 Individual lesions are seldom more than 1.0 cm in 
diameter and most are less than 0.5 cm in size. 
 The radiolucences maybe discrete with well 
defined borders or they maybe large enough to 
appear confluent as they overlap and merge.
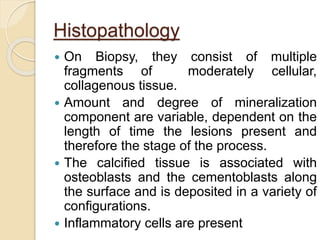
Histopathology 
 On Biopsy, they consist of multiple 
fragments of moderately cellular, 
collagenous tissue. 
 Amount and degree of mineralization 
component are variable, dependent on the 
length of time the lesions present and 
therefore the stage of the process. 
 The calcified tissue is associated with 
osteoblasts and the cementoblasts along 
the surface and is deposited in a variety of 
configurations. 
 Inflammatory cells are present
Focal Cemento-Osseus 
Dysplasia 
Clinical Features : 
 Female predominance. 
 4th -5th decades of life. 
 Solitary lesions , in posterior mandible.
Radiographic Features 
 Diagnosed in routine radiographs, 
characteristically, asymptomatic. 
 Most lesions appear as radiolucent – radio-opaque 
areas. 
 In edentulous areas development of 
idiopathic bone cavities, result in bony 
expansion of affected area.
Histopathology 
 Consistency of tissue 
removed for biopsies is 
important . 
 Difficult to curette form 
the sockets, is removed 
as multiple fragments of 
gritty tissues 
 Distinction between 
ossifying fibroma, which 
typically can be 
removed as large 
fragmented that can be 
separated cavity form 
bone. 
“Ginger root” Pattern
Treatment 
 Lesions exhibit only limited potential 
for progressive growth, more lesion 
require no additional treatment 
following biopsy. 
 Periodic observation
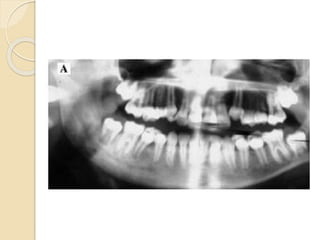
Florid Cemento-Osseous 
Dysplasia 
 Middle-aged females 
 Painless non-expansile lesion often 
involving two or more jaw quadrants. 
 Radiographically - multiple confluent 
lobular radiopaque masses in tooth-bearing 
areas 
 Tendency toward bilateral, 
symmetrical involvement 
 Asymptomatic and detected incidentally
 Jaw expansion - large lesions. 
 Dull pain or drainage are always 
associated with exposure of the 
sclerotic calcified masses to the oral 
cavity as the result of progressive 
alveolar atrophy under a denture or 
after extraction of teeth in the involved 
area.
Treatment 
 Often difficult, not very satisfactory. 
 In the asymptomatic patient 
observation 
 Antibiotics 
 Sequestration of the cementum-like 
masses will occur slowly and followed 
by healing. 
 Saucerization or surgical excision
Inflammatory/ Reactive 
Processes 
 This include: 
◦ Focal Sclerosing Osteomyelitis( 
Condensing Osteitis) 
◦ Diffuse Sclerosing Osteomyelitis 
◦ Proliferative Periostitis
Focal Sclerosing Osteomyelitis 
( Condensing Osteitis) 
 Mildest and most self-limiting form 
 Posterior mandible at apices of molar 
teeth 
 Bacterial origin 
 Pathogenic bacteria are of low 
virulence
Clinical Features 
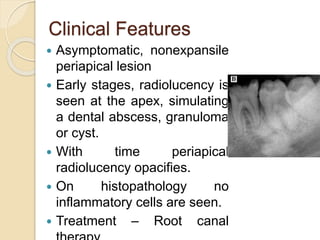
 Asymptomatic, nonexpansile 
periapical lesion 
 Early stages, radiolucency is 
seen at the apex, simulating 
a dental abscess, granuloma 
or cyst. 
 With time periapical 
radiolucency opacifies. 
 On histopathology no 
inflammatory cells are seen. 
 Treatment – Root canal 
therapy
Differential Diagnosis 
 Focal osteosclerosis 
 Focal cemento osseous dysplasia
Diffuse Sclerosing 
Osteomyelitis 
 Unilateral diffuse ground glass 
opacification without defined boundaries 
of the mandibular body. 
 Cortical expansion 
 H/O dull episodic pain that last for weeks 
to subside and later become 
symptomatic again. 
 Caused by gram negative anaerobic 
bacteria of low virulence. 
 Definitive anaerobic culture 
 Source of infection - Odontogenic
 Microscopically, bone exhibits a fibro 
osseous pattern with intervening foci 
of dense sclerotic bone. 
 Osseous elements are trabecular 
 Cementifying areas - absent.
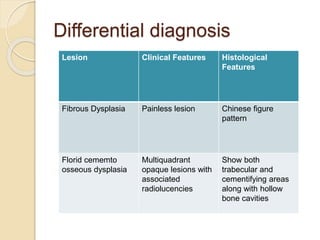
Differential diagnosis 
Lesion Clinical Features Histological 
Features 
Fibrous Dysplasia Painless lesion Chinese figure 
pattern 
Florid cememto 
osseous dysplasia 
Multiquadrant 
opaque lesions with 
associated 
radiolucencies 
Show both 
trabecular and 
cementifying areas 
along with hollow 
bone cavities
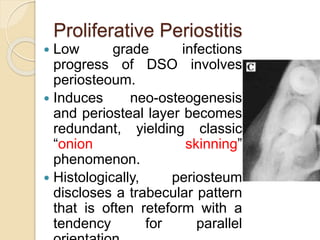
Proliferative Periostitis 
 Low grade infections 
progress of DSO involves 
periosteoum. 
 Induces neo-osteogenesis 
and periosteal layer becomes 
redundant, yielding classic 
“onion skinning” 
phenomenon. 
 Histologically, periosteum 
discloses a trabecular pattern 
that is often reteform with a 
tendency for parallel 
orientation
Treatment 
 Removing odontogenic infection 
source by extraction or RCT. 
 Long term antibiotic therapy.
Hyperparathyroidism 
 The “brown tumor” of 
hyperparathyroidism, a giant cell 
lesion, may be encountered anywhere 
in the skeleton in both primary and 
secondary HPT. 
 Reported among patients with renal 
osteodystrophy.
Clinical Features 
 Marked facial deformity 
 Thickening of dipole and massive 
maxillomandibular enlargement with 
protrusion of anterior teeth and wide 
diastemas. 
 Also known as – Sagliker Syndrome 
and the Uglifying Human Face 
Syndrome. 
 Histologically, trabecular pattern is 
seen
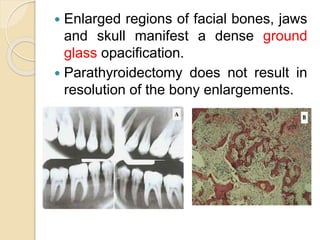
 Enlarged regions of facial bones, jaws 
and skull manifest a dense ground 
glass opacification. 
 Parathyroidectomy does not result in 
resolution of the bony enlargements.
Ossifying Fibromas 
 Neoplasms with a fibro-osseous 
histology represented by the ossifying 
fibroma group of lesions. 
 Neoplasms in the true sense 
exhibiting progressive proliferative 
capabilities with bony expansion and 
well defined margins radiologically.
Types 
 Ossifying/ Cementifying Fibroma 
 Juvenile Ossifying Fibroma 
 Trabecular Juvenile Ossifying Fibroma 
 Psammomatoid Juvenile Ossifying 
Fibroma 
 Gigantiform Cementoma
Ossifying/Cementifying 
Fibroma 
 Most common form of OF occurs in 
maxilla and mandible. 
 Mutation in HRPT2 gene that encodes 
parafibromin protein. 
 Painless with expansion of both cortices. 
 Larger lesions may expand the inferior 
aspect of mandible. 
 Teeth are displaced superiorly ( 
mandibular lesion) and inferiorly( 
maxillary lesion) and expand into the 
antrum.
Radiographic Features 
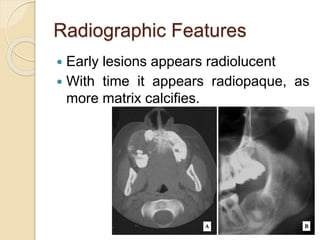
 Early lesions appears radiolucent 
 With time it appears radiopaque, as 
more matrix calcifies.
Histological Features 
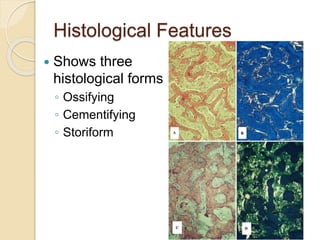
 Shows three 
histological forms 
◦ Ossifying 
◦ Cementifying 
◦ Storiform
Juvenile Ossifying Fibroma 
 Also known as Juvenile Active 
Ossifying Fibroma and Juvenile 
Aggressive Ossifying Fibroma. 
 2 clinicopathologic entities 
1. Trabecular Juvenile Ossifying Fibroma 
( TrJOF) 
2. Psammomatoid Juvenile Ossifying 
Fibroma (PsJOF)
Trabecular Juvenile Ossifying 
Fibroma(TrJOF) 
 Also known as trabecular desmo-osteoblastoma. 
 Majority of patients are children and 
adolescents. 
 Only 20% are over 15 years of age. 
 M:F = 1:1 
 Maxilla and mandible are dominant 
sites. 
 Maxilla is slightly more affected.
Clinical Features 
 Progressive and sometimes rapid 
expansion of bone 
 In maxilla, obstruction of nasal 
passages and epistaxis may be 
present.
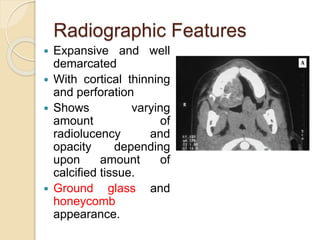
Radiographic Features 
 Expansive and well 
demarcated 
 With cortical thinning 
and perforation 
 Shows varying 
amount of 
radiolucency and 
opacity depending 
upon amount of 
calcified tissue. 
 Ground glass and 
honeycomb 
appearance.
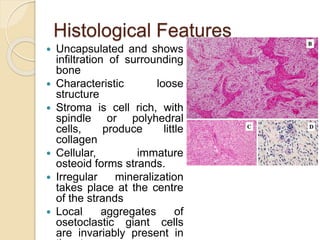
Histological Features 
 Uncapsulated and shows 
infiltration of surrounding 
bone 
 Characteristic loose 
structure 
 Stroma is cell rich, with 
spindle or polyhedral 
cells, produce little 
collagen 
 Cellular, immature 
osteoid forms strands. 
 Irregular mineralization 
takes place at the centre 
of the strands 
 Local aggregates of 
osetoclastic giant cells 
are invariably present in 
the stroma.
 Clinical course is characterized by 
infrequent recurrence following 
conservative excision. 
 Complete cure could be achieved in 
those cases without resorting to 
radical surgical intervention. 
 Malignant transformation not reported
Psammomatoid Juvenile 
Ossifying Fibroma 
 Affects extragnathic craniofacial 
bones, particularly periorbital, frontal 
and ethmoid bones. 
 Gogl,1949, as psammomatoid fibroma 
of the nose and paranasal sinuses. 
 Margo,1985 described as a distinctive 
solitary fibro-osseous lesion that 
affects the orbit and shows distinctive 
histologic features.
 16 to 33 years. 
 Range of 3 months to 72 years. 
 Majority originates in paranasal 
sinuses ( frontal and ethmoid). 
 10 % in calvarium 
 7% in mandible( Makek in 1983)
Clinical Features 
 Bone expansion involves orbital or 
nasal bones and sinuses. 
 Orbital extension- proptosis and visual 
complaints including blindness, nasal 
obstruction, ptosis, papilledema and 
disturbances in ocular mobility.
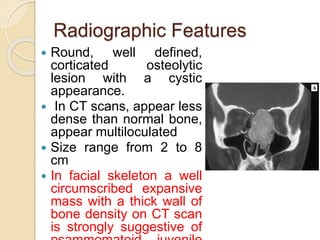
Radiographic Features 
 Round, well defined, 
corticated osteolytic 
lesion with a cystic 
appearance. 
 In CT scans, appear less 
dense than normal bone, 
appear multiloculated 
 Size range from 2 to 8 
cm 
 In facial skeleton a well 
circumscribed expansive 
mass with a thick wall of 
bone density on CT scan 
is strongly suggestive of 
psammomatoid juvenile
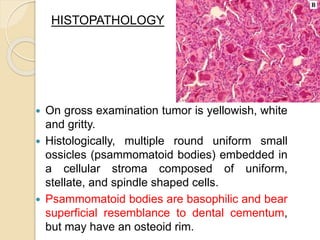
HISTOPATHOLOGY 
 On gross examination tumor is yellowish, white 
and gritty. 
 Histologically, multiple round uniform small 
ossicles (psammomatoid bodies) embedded in 
a cellular stroma composed of uniform, 
stellate, and spindle shaped cells. 
 Psammomatoid bodies are basophilic and bear 
superficial resemblance to dental cementum, 
but may have an osteoid rim.
 Surgical excision is treatment of 
choice. 
 Recurrence rate of >30% reported. 
 No malignant change observed.
Familial Gigantiform 
Cementoma 
 An autosomal dominant variant 
usually involving multiple quadrants 
with variably expansile lesions. 
 Anterior mandible. 
 No racial predilection. 
 Often evolve during childhood and 
can grow rapidly.
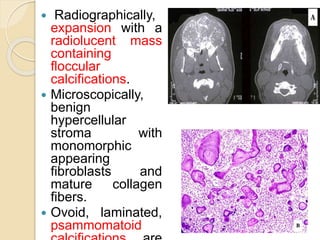
 Radiographically, 
expansion with a 
radiolucent mass 
containing 
floccular 
calcifications. 
 Microscopically, 
benign 
hypercellular 
stroma with 
monomorphic 
appearing 
fibroblasts and 
mature collagen 
fibers. 
 Ovoid, laminated, 
psammomatoid 
calcifications are
 Treatment is resection with immediate 
or staged reconstruction.
Fibro Osseous Lesions