DR. MUSHTAQ AHMED
Associate Professor, Pharmacology
Punjab Institute of Medical Sciences, Jalandhar, INDIA
Diabetes Mellitus
Diabetes mellitus (DM) is a metabolic disorder resulting from a
defect in insulin secretion or insulin action, or both
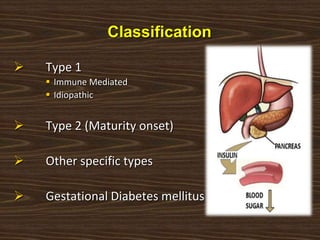
 Classification of DM
 Type 1
• Immune Mediated
• Idiopathic
 Type 2 (Maturity onset)
 Other specific types
 Gestational Diabetes mellitus
Prevalence of DM
 India is the “Diabetes Capital” of the World
 In 2010 - >200 million people worldwide had DM and
300 million will subsequently have the disease by 2025
 India had 32 million diabetic subjects in the year 2000
and this number would increase to 80 million by the year
2030
 There is increased incidence of DM in urban population
than rural
Classification
 Type 1
 Immune Mediated
 Idiopathic
 Type 2 (Maturity onset)
 Other specific types
 Gestational Diabetes mellitus
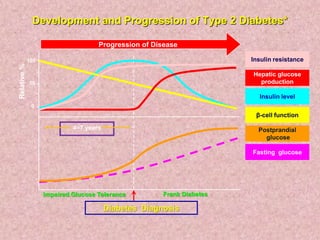
Development and Progression of Type 2 Diabetes*
Progression of Disease
Impaired Glucose Tolerance
Insulin level
Insulin resistance
Hepatic glucose
production
Diabetes Diagnosis
Postprandial
glucose
Fasting glucose
β-cell function
Frank Diabetes
4–7 years
0
50
100
Relative%
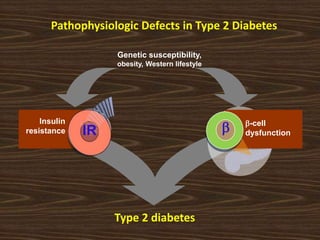
Insulin
resistance
Genetic susceptibility,
obesity, Western lifestyle
Type 2 diabetes
IR
b-cell
dysfunctionb
Pathophysiologic Defects in Type 2 Diabetes
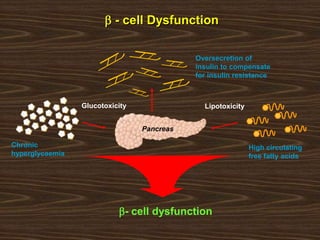
b - cell Dysfunction
Chronic
hyperglycaemia
Oversecretion of
insulin to compensate
for insulin resistance
High circulating
free fatty acids
Glucotoxicity
Pancreas
Lipotoxicity
b- cell dysfunction
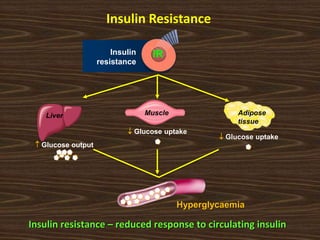
Insulin resistance – reduced response to circulating insulin
Insulin
resistance
 Glucose output
 Glucose uptake
 Glucose uptake
Hyperglycaemia
Liver Muscle Adipose
tissue
IR
Insulin Resistance
Causes of Insulin Resistance
 Defect (structural) in insulin molecule
 Elevated levels of insulin antagonists
(counter-regulatory hormones)
 Target tissue defects (Major cause)
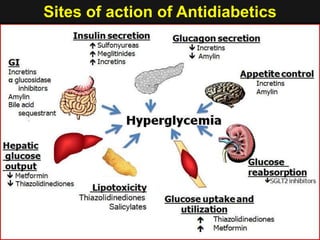
Sites of action of Antidiabetics
What is the role of an ideal oral hypoglycaemic agent?
 Conserve islet cell function - delay the subsequent
use of insulin.
 Improve patient compliance- single daily dosing.
 Reduce the incidence of hypoglycaemic events
Management of Diabetes




Role of Exercise in Type 2 DM
• Exercise - probably the best treatment for
type 2 diabetes
• Lowers blood sugar
• Decrease insulin resistance
• Raise metabolism
• Improve blood flow through capillaries
• Improve stroke volume & blood lipids
• Control & prevent moderate hypertension
• Decrease body mass
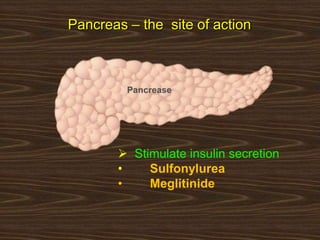
Pancreas – the site of action
 Stimulate insulin secretion
• Sulfonylurea
• Meglitinide
Pancrease
Classification of Oral Antidiabetics
 Oral Hypoglycaemic Agents
1. Sulphonylureas
First Generation: Tolbutamide, Chlorpropamide
Second Generation: Glibenclamide (glyburide), Glipizide,
Gliclazide, Glimepiride
2. Meglitinide Analogues:
Repaglinide, Nateglinide
Oral Hypoglycaemic Agents
Sulphonylureas
 First Generation
Tolbutamide
• O.O.A. is within one hour & lasts for 6-12 Hrs
• It is weaker, short acting, less likely to cause hypoglycemia
Chlorpropamide
• O.O.A. is within one hour & lasts for 24-60 Hrs
• It is more potent, long lasting, risk of prolonged hypoglycemia
• Potentiates ADH action
Sulphonylureas (contd)
 Second Generation
Glibenclamide (glyburide)
• O.O.A. is within 1-4 hours & lasts for 10-24 Hrs
• It is more potent than tolbutamide, risk of severe hypo.
Glipizide
• O.O.A. is within 1-3 hours & lasts for 10-24 Hrs
• Less potent than glibenclamide but more potent than tolbutamide
• Risk of prolonged hypoglycemia
Gliclazide
• O.O.A. & D.O.A, same as glipizide
• More potent than tolbutamide
• Has an antioxdent and antiplatelet action
• Less weight gain
Glimepiride:
• Same as glipizide
Sulphonylureas
 M.O.A
• Stimulates Insulin release from β- cells
• Inhibits SUR-1 receptors present on ATP sensitive K+ channels → depolarization
followed by Ca+ entry → insulin release
• Glucagon levels are suppressed
 Pharmacokinetics
• well absorbed
• PPB is high
• Metabolized in liver or kidney and excreted in urine
 Adverse effects
• Hypoglycemia
• Weight gain
• Cross placental barrier – fetal hypoglycemia (avoid in gestational DM)
 Contra indications
• Ketocanazole, chloramphenicol and anticoagulants- inhibit their metabolism
• Sulfonamides, salicylates etc- protein binding displacement
• Propranolol masks the symptoms of sulfonylureas
Meglitinide Analogues
Repaglinide
• Its O.O.A is within one hour & lasts for 4-5 hrs
• Dose 0.25-4mg before each meal
Nateglinide
• Its O.O.A & D.O.A, same as repaglinide
• Dose 60-120mg before each meal
• Hypoglycemic risk is low
 M.A.O
• Stimulate insulin release, same as sulfonylurea
• Administered before meal to control PP blood glucose
Advantages of Nateglinide/Repaglinide
 Flexibility in mealtime dosing - „Ramzan Drug‟
 No significant increase in bodyweight
 Can be utillised in mild to moderate renal failure
 Nateglinide: approved in hepatic failure
Dosage:
Repaglinide: 0.5mg/1mg/2mg/4mg per dose per meal
Nateglinide: 60mg/120mg per dose per meal
Lower incidence of hypoglycemia
Useful Situations
– Elderly patients in whom hypoglycaemia is a concern
– Patients with kidney failure or mild hepatic impairment
– patients taking low-dose sulphonylureas who encounter
problems with hypoglycaemia
– Patients with irregular meal patterns
Int J Clin Pract. 2003 Jul-Aug;57(6):535-41.
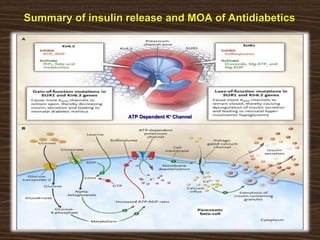
Summary of insulin release and MOA of Antidiabetics
ATP Dependent K+ Channel
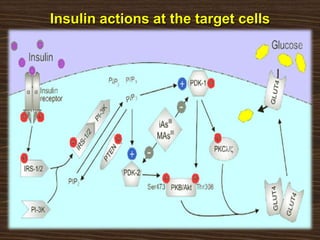
Insulin actions at the target cells
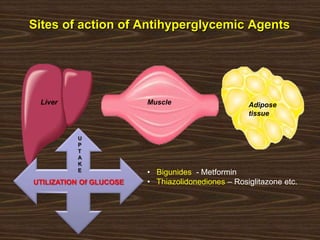
Sites of action of Antihyperglycemic Agents
Liver Muscle Adipose
tissue
• Bigunides - Metformin
• Thiazolidonediones – Rosiglitazone etc.
U
P
T
A
K
E
UTILIZATION Of GLUCOSE
Antihyperglycemic Agents
 Biguanides
 Metformin
 The primary drug of choice for diabetes by ADA guidelines.
• Does not stimulate insulin release
• Not dependent on functional β- cells for its action
• Does not lower blood glucose in normal subjects
• Causes anorexia, no weight gain
• As monotherapy, rarely causes hypoglycemia
Dose:
500mg twice a day after meals
Biguanides Contd
Advantages:
 Perpetuates weight loss
 Can be combined with insulin to reduce
insulin requirements
 Decreases risk of macro & microvascular
disease
Disadvantages:
 Nausea, Vomiting and diarhorrea (5%),
Vitamin B12 Deficiency (0.5%)
Adverse effect:
 Nausea, metallic taste, anorexia,
flatulence & diarrhoea
 Non diabetic use of Metformin:
Hirsutism with PCOD to enhance
fertility in women
 Phenformin
• Its use has been discontinued because of
lacticacidosis
Biguanides Contd
Biguanides Contd
 M.O.A
• Increased uptake and utilization of glucose by muscles →
reduce insulin resistance
• Inhibition of hepatic and renal gluconeogenesis → reduce
hepatic glucose output
• Slowing of glucose absorption from GIT
• Promotion of insulin binding to its receptor
 PK
• No PPB, Plasma t1/2 2-3 hours
• Excreted unchanged by kidneys
Thiazolidinediones (Glitazones)
 New class of drugs – acts as agonist to nuclear
receptor PPAR-Ƴ in adipose tissue, sk. Muscle
and liver.
Pioglitazone
• D.O.A. more than 24hrs
• 10-45 mg OD
Rosiglitazone (withdrawn from the market in Oct. 2010 b/o risk of
Heart failure and MI)
• D.O.A. same as pioglitazone
• Dose 4-8mg OD
Glitazones Contd
 MOA
• Stimulates (nuclear receptor) i.e. Peroxisome Proliferator Activated
Receptor-gamma (PPAR-Ƴ) → promotes transcription of insulin
responsive genes which control glucose & lipid metabolism → ↑
insulin sensitivity & ↓ insulin resistance
• Promotes uptake and utilization of glucose by increasing the GLUT-4
transpotors
• Decrease glucose output by inhibiting gluconeogenesis
 AE
• Weight gain. hepatotoxicity is rare, yet LFT are advisable
 CI
• Hepatic failure, pregnancy, lactating mother, children and heart failure
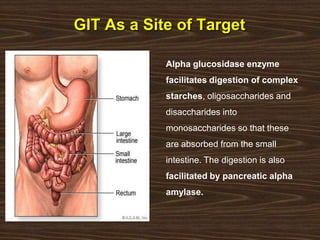
GIT As a Site of Target
Alpha glucosidase enzyme
facilitates digestion of complex
starches, oligosaccharides and
disaccharides into
monosaccharides so that these
are absorbed from the small
intestine. The digestion is also
facilitated by pancreatic alpha
amylase.
α-Glycosidase Inhibitors
Acarbose, Miglitol, Voglibose
 Work on the brush border of the intestine
cause carbohydrate malabsorption
• Reduce post meal hyperglycemia
• Regular use tend to lower HbA1c,
triglycerides and body weight
• Do not directly affect insulin secretion
• No hypoglycemia
• Dose: 50-100mg TDS
α-Glycosidase Inhibitors contd.
 M.O.A
• Reduce PP digestion and absorption of
carbohydrates by inhibiting α – glucosidase
enzyme
 PK
• Absorption of acarbose is minimal, but miglitol
is absorbed well
• A Part of acarbose is excreted unchanged
while a part is metabolized by intestinal
bacterial flora
α-Glycosidase Inhibitors Contd.
 Advantages:
• Selective for postprandial hyperglycaemia
• No hypoglycaemic symptoms
 Disadvantages:
• Abdominal distension and flatus
• Only effective in mild hyperglycaemia
 Dose:
 Acarbose - 25 mg to 50mg TID
 Miglitol - 25mg to 100mg TID
 Voglibose - 0.2 to 0.3 mg TID
What are Incretins?
 I s a group of hormones (GLP & GIP) – released
after meals and augment glucose-dependent
insulin secretion
 GLP-1 (glucagon-like peptide 1) (*More Imp)
• is a prominent insulinotrophic incretin.
• half life- 1-2 min.
• metabolized quickly by DPPIV enzyme.
 GIP: Glucose-dependent insulinotrophic
polypeptide
Small effect in Type 2 diabetes.
Incretin concept
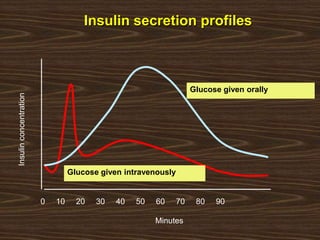
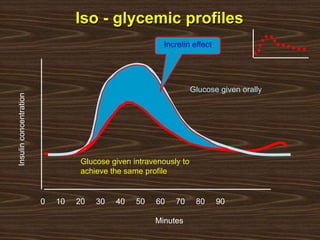
 Insulin secretion dynamics is dependent on the
method of administration of glucose
 Intravenous glucose gives a marked first and
second phase response
 Oral glucose gives less marked first and second
phase insulin response, but a prolonged and
higher insulin concentration
Insulinconcentration
0 10 20 30 40 50 60 70 80 90
Minutes
Glucose given orally
Glucose given intravenously
Insulin secretion profiles
Insulinconcentration
0 10 20 30 40 50 60 70 80 90
Minutes
Glucose given orally
Glucose given intravenously to
achieve the same profile
Incretin effect
Iso - glycemic profiles
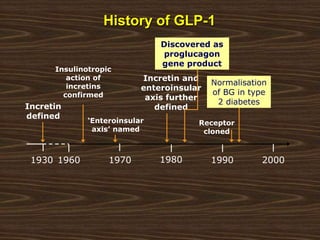
20001960
‘Enteroinsular
axis’ named
Incretin
defined
Discovered as
proglucagon
gene product
Receptor
cloned
1930 19801970 1990
Normalisation
of BG in type
2 diabetes
Insulinotropic
action of
incretins
confirmed
Incretin and
enteroinsular
axis further
defined
History of GLP-1
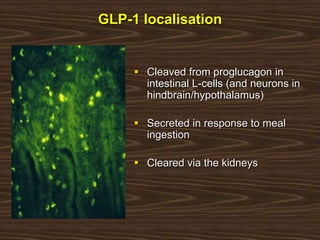
GLP-1 localisation
 Cleaved from proglucagon in
intestinal L-cells (and neurons in
hindbrain/hypothalamus)
 Secreted in response to meal
ingestion
 Cleared via the kidneys
Incretin-Mimetics
 Incretin–mimetics
• Glucagon Like Peptide – 1 (GLP-1) → released after meals from the upper &
lower bowel → augment glucose dependent insulin secretion, during the phase
of nutrition absorption from GIT
• t ½ GLP-1 – 1 to 2 min
• Metabolized quickly by DPP-IV enzyme
Exenatide [incretin (GLP-1) agonist]
• Obtained from salivary gland venom of Gila monster
• Resistant to DPP-IV degradation
• Potent agonist of GLP-1 receptor, Orally inactive
• Given SC (5-10μg) twice daily, 30-60 min before meals
• It reduces only post meal glucose rise
 MOA
• Stimulates insulin secretion from β- cells
• Decreases glucagon release
 AE
• Diarrhea, nausea, anorexia
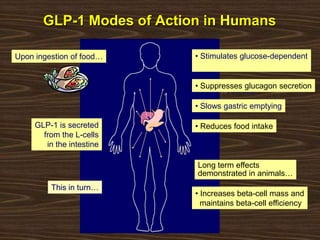
GLP-1 is secreted
from the L-cells
in the intestine
This in turn…
• Stimulates glucose-dependent
insulin secretion
• Suppresses glucagon secretion
• Slows gastric emptying
Long term effects
demonstrated in animals…
• Increases beta-cell mass and
maintains beta-cell efficiency
• Reduces food intake
Upon ingestion of food…
GLP-1 Modes of Action in Humans
His Ala Glu Gly Thr Phe Thr Ser Asp
Lys Ala Ala Gln Gly Glu Leu Tyr Ser
Ile Ala Trp Leu Val Lys Gly Arg Gly
Val
Ser
Glu
Phe
GLP-1
7
37
NH2
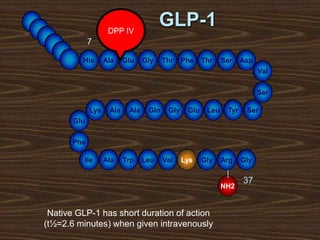
Native GLP-1 has short duration of action
(t½=2.6 minutes) when given intravenously
DPP IV
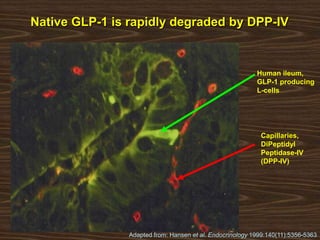
Human ileum,
GLP-1 producing
L-cells
Capillaries,
DiPeptidyl
Peptidase-IV
(DPP-IV)
Adapted from: Hansen et al. Endocrinology 1999:140(11):5356-5363
Native GLP-1 is rapidly degraded by DPP-IV
His Ala Glu Gly Thr Phe Thr Ser Asp
Lys Ala Ala Gln Gly Glu Leu Tyr Ser
Ile Ala Trp Leu Val Lys Gly Arg Gly
Val
Ser
Glu
Phe
DPP-IV (DPP4)
inhibitors7
37
NH2
DPP IV
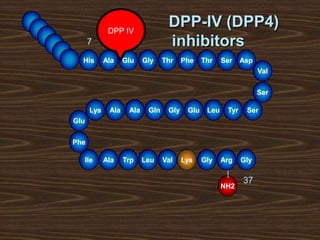
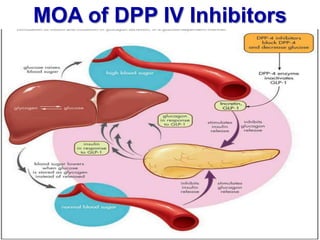
DPP-IV Inhibitors
 DPP-IV Inhibitors
 Sitagliptin, Vildagliptin, Saxagliptin, Septagliptin, Allogliptin
• Orally active
• Selective inhibitors of DPP-IV enzyme that deactivates GLP-1
 MOA
• Increase insulin secretion
• Decrease glucagon release
• Delay gastric emptying
• Suppress appetite
 AE
• Nasopharyngitis because substance P is also a substrate for DPP-IV, whose
levels get elevated, GIT distress and diarrhea
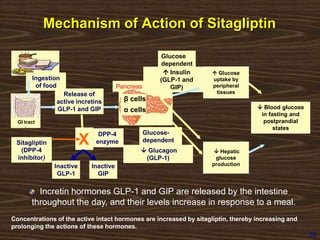
Incretin hormones GLP-1 and GIP are released by the intestine
throughout the day, and their levels increase in response to a meal.
Concentrations of the active intact hormones are increased by sitagliptin, thereby increasing and
prolonging the actions of these hormones.
Release of
active incretins
GLP-1 and GIP  Blood glucose
in fasting and
postprandial
states
Ingestion
of food
 Glucagon
(GLP-1)
 Hepatic
glucose
production
GI tract
DPP-4
enzyme
Inactive
GLP-1
XSitagliptin
(DPP-4
inhibitor)
 Insulin
(GLP-1 and
GIP)
Glucose-
dependent
Glucose
dependent
Pancreas
Inactive
GIP
β cells
α cells
 Glucose
uptake by
peripheral
tissues
30
Mechanism of Action of Sitagliptin
MOA of DPP IV Inhibitors
Amylin - mimetics
 Amylin
• A hormone co-secreted with insulin from β- cells
• Inhibit glucagon secretion
• Delay gastric emptying
• Suppress appetite
Pramlintide
• Stimulates amylin receptor (a G-protein coupled receptor)
• SC before meals
• No hypoglycemia
 AE
• Nausea, diarrhea, headache
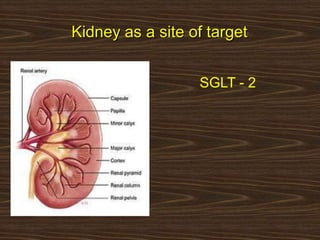
Kidney as a site of target
SGLT - 2
SGLT-2 Inhibitors
 SGLT-2 Inhibitors
• Newer antidiabetic drugs
• Kidney continuously filters glucose through glomerulous which is reabsorbed
back from PT by Na2+ glucose co-transporter -2 (SGLT-2)
• Inhibition of SGLT – 2 decreases glucose re-absorption
Dapaglifozin, Serglifozin, Remoglifozin
 Advantages
• Weight loss
• No hypoglycemia
 Disadvantages
• Because of polyuria there will be more polydipsia
• Increased risk of urinary infection in presence of glycosuria
• Risk of Na2+loss
Oral antidiabetics by Dr. Mushtaq Ahmed, Associate Professor, Pharmacology, PIMS Punjab