Pharmacotherapy of Diabetes Mellitus Dr Naser Ashraf TadviAssociate Professor Kamineni Institute of Medical Sciences Narketpally, Nalgonda
DiabetesDiabetes  is  a group of metabolic  disorders characterized  by chronic hyperglycemiaassociated with disturbances of carbohydrate, fat and protein metabolism due to absolute or relative deficiency in insulin secretion and/or actionDiabetes causes long term damage, dysfunction & failure of various organs
Diagnosis of diabetes Fasting  Plasma  Glucose ≥  126  mg / dlSymptoms of DM and a random blood glucose level of  ≥  200 mg/dlOral glucose tolerance test2 hr after 75 gm glucose load ≥  200  mg / dl
Classification  of  DiabetesProposed  by  ADA -  1997.Type I: Absolute  Insulin Deficiency due to islet cell destruction Either immune mediated or idiopathic Type II: Relative insulin deficiency due to impaired -cell function Marked ↑ peripheral insulin resistanceType III: Other  Specific  typesType IV:Gestational  Diabetes
Other  specific  typesA)  Genetic  defects  of  Beta  cell  functionB) Genetic  defects  in  Insulin  actionC) Diseases  of  the  Exocrine  PancreasD) Secondary  to  EndocrinopathiesE) Drugs  /  Chemical  induced F) InfectionsG) Uncommon  form  of  Immune  Mediated  Diabetes.H) Other  Genetic  Syndromes  associated  with  DiabetesMODY SyndromesLipo atrophic DiabetesFCPDPancreatitisTraumaNeoplasiaCystic FibrosisHemochromatosisAcromegalyCushings SyndromePheochromocytomaHyperthyroidismSteroidsThiazidesDiazoxideBeta BlockersThyroid HormonesCongenital RubellaCMVAnti insulin Receptor AntibodiesDown’s SyndromeTurnersKlinefelters
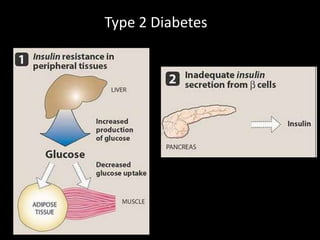
Type 2 Diabetes
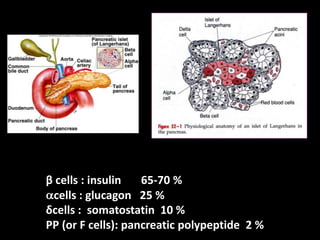
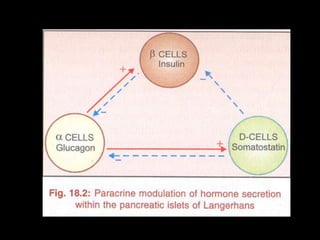
β cells : insulin       65-70 %cells : glucagon   25 %δcells :  somatostatin10 % PP (or F cells): pancreatic polypeptide  2 %
Physiology of Human InsulinBeta cell statisticsOnly  2%  of  the pancreas weight is endocrine. 98 % Exocrine
Total number of Islets….     1 lakh
Number of cell / Islet           1-2 thousand
Beta cells / Islet                   65-70 %
Total Insulin storage            200 units
Daily insulin release             40 -50 units
1 unit Insulin                      8-10 gm. GlucoseInsulin
Discovery of insulin
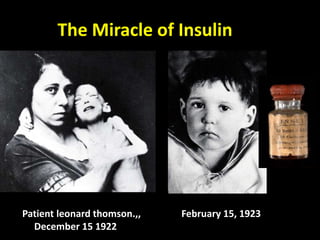
The Miracle of Insulin        Patient leonardthomson.,,                 February 15, 1923December 15 1922
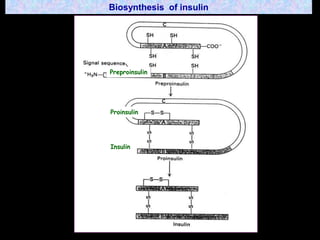
Biosynthesis  of insulin PreproinsulinProinsulinInsulin
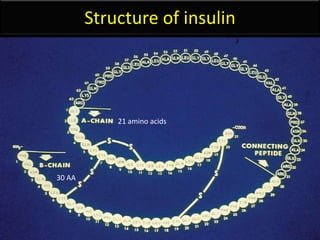
Structure of insulin 21 amino acids 30 AA
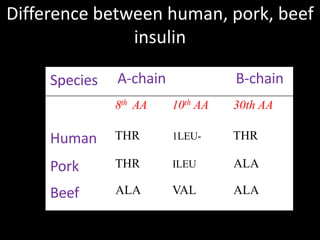
Difference between human, pork, beef insulin
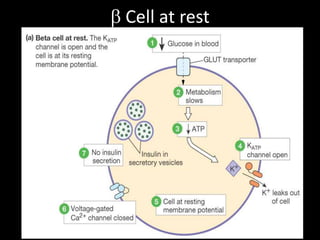
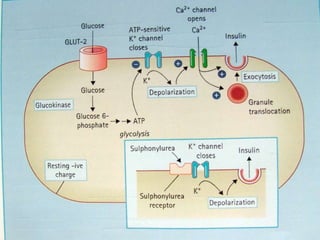
 Cell at rest
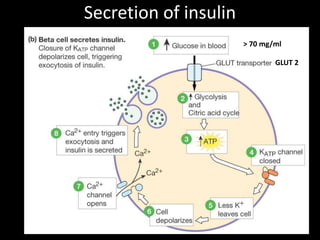
Secretion of insulin > 70 mg/mlGLUT 2
Bioassay of insulin 1 IU reduces the BSL to 45 mg/dl in fasting rabbits 1 mg insulin = 28 IUCan also be measured by radioimmunoassay or enzyme immunoassay
Regulation of insulin secretionDirect stimulation
Plasma glucose or Amino Acids , ketones
 Hormonal regulation
 Gastrointestinal hormones (GIP, CCK) directly   stimulate β cells
 Neural regulation
Parasympathetic stimulates insulin release through IP3/ DAG
Sympathetic NS inhibits insulin release through 2 receptor activation
Actions of insulin Intermediary actions Rapid actions Long termSec / min Few hours > 24 hrs ↑ multiplication
↑ differentiation  of cells
 Imp role in intrauterine & extrauterine growth Through DNAe.g ↑ GLUT synthesis
 Synthesis of enzymes for AA metabolism E.g  Metabolic actions
Actions of insulin Metabolic:  carbohydrate, lipid , protein, electrolyteVascular Anti-inflammatory FibrinolyticGrowth Steroidogenesis
Carbohydrate metabolism Over all action of insulin is to ↓ glucose level in blood ↑ Transport of glucose inside the cell↑ Peripheral  utilization of glucose ↑ Glycogen synthesis↓ Glycogenolysis↓ Neoglucogenesis
Lipid  metabolism↓ Lipolysis↑ Lipogenesis↑ Glycerogenesis↓ Ketogenesis↑ Clearance of VLDL & chylomicrons from blood through enzyme Vascular Endothelial Lipoprotein Lipase
Protein metabolism Protein synthesis ↑ entry of amino acids in cells Electrolyte  metabolism ↑ transport of K+, Ca++, inorganic phosphates Other actions Vascular actions: Vasodilation ? Activation of endothelial NO production Anti-inflammatory actionEspecially in vasculature Decreased fibrinolysisGrowthSteroidogenesis
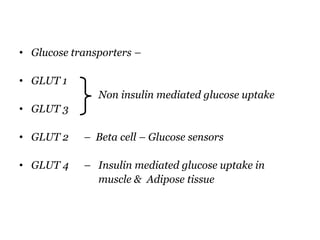
Glucose transporters –
GLUT 1                                Non insulin mediated glucose uptakeGLUT 3
GLUT 2      –  Beta cell – Glucose sensors
GLUT 4      –   Insulin mediated glucose uptake in 	                               muscle &  Adipose tissue
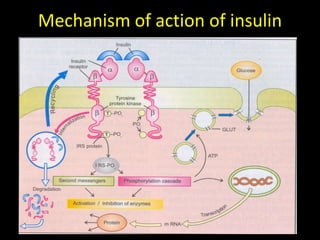
Mechanism of action of insulin
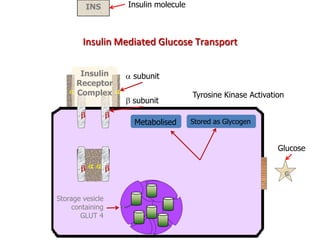
Insulin moleculeINSInsulin Mediated Glucose TransportInsulinReceptorComplexa subunitaaTyrosine Kinase Activationbbb subunitMetabolisedStored as GlycogenGlucosebbINSaaGStorage vesiclecontainingGLUT 4
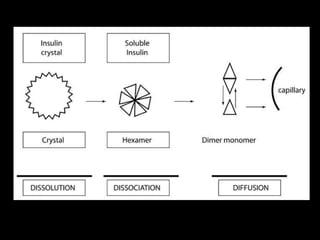
Fate of insulin Distributed only extracellularlyMust be given parenterallyAddition of zinc or protein decreases its absorption & prolongs the DOA Insulin released from pancreas is in monomeric formHalf life of insulin = 5 -9 minutes
Different types of insulin preparations  Conventional preparations of insulin Produced from beef or pork pancreas 1 % of other proteinsPotentially antigenic Highly purified insulin preparations Gel filtration reduces proinsulin (50-200PPM) Human insulinsNewer insulin analogs
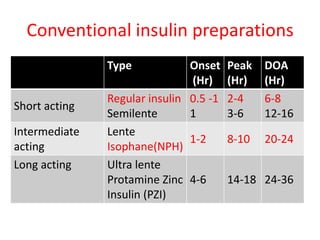
Conventional insulin preparations
Highly purified insulin preparations Single peak insulinsPurified by gel filtration contain 50 to 200 PPM proinsulinActrapid: purified pork regular insulin Monotard: purified pork lenteMixtard: purified pork regular(30%) + isophane(70%)Mono component  insulinsAfter gel filtration purified by ion exchange chromatography  contain 20 PPM proinsulinActrapid MC, Monotard MC

Human insulinsHuman (Actrapid, monotard, insulatard, mixtard)Obtained by recombinant DNA technology AdvantagesMore water soluble as well as hydrophobic More rapid SC absorption , earlier & more defined peak Less allergy Disadvantages Costly Slightly shorter DOA
Indications of human insulinsInsulin resistance Allergy to conventional preparations Injection site lipodystrophyDuring pregnancy Short term use of insulin
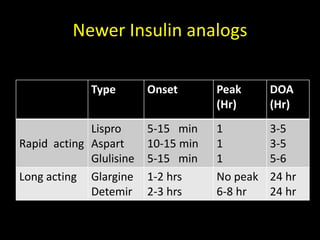
Newer Insulin analogs
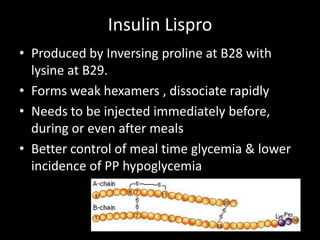
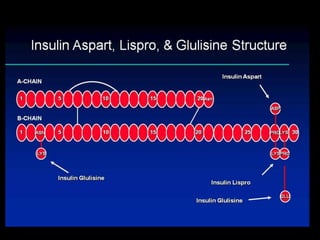
Insulin LisproProduced by Inversing proline at B28 with lysine at B29. Forms weak hexamers , dissociate rapidly Needs to be injected immediately before, during or even after meals Better control of meal time glycemia & lower incidence of PP hypoglycemia
Insulin aspart:Proline at B28 replaced by aspartic acid Change reduces tendency for self aggregation Insulin glulisine lysine replaces aspargine  at B3 & glutamic acid replaces lysine at position B29
Insulin glarginePrepared  by adding 1 glycine at A21 together with 2 arginine residues at end of B chain Improved StabilityMuch better bioavailabilty Smooth peakless effect is obtained Fasting & interdigestive BGL effectively lowered irrespective of time of day Lower hypoglycemic episodesCannot be mixed with other insulins
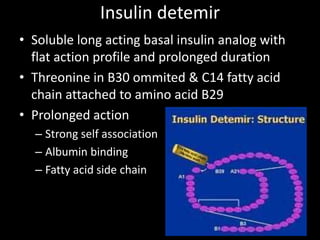
Insulin detemirSoluble long acting basal insulin analog with flat action profile and prolonged duration Threonine in B30 ommited & C14 fatty acid chain attached to amino acid B29 Prolonged actionStrong self association Albumin bindingFatty acid side chain

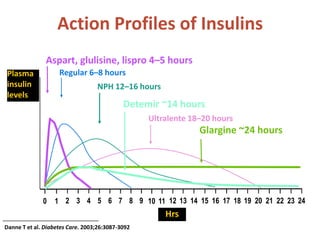
Aspart, glulisine, lispro 4–5 hoursRegular 6–8 hoursNPH 12–16 hoursDetemir ~14 hoursUltralente 18–20 hoursGlargine ~24 hours2534678912131415161718192021222324011011Action Profiles of InsulinsPlasmainsulinlevelsHrs Danne T et al. Diabetes Care. 2003;26:3087-3092
Insulin analogs score over conventional insulinsLess nocturnal hypoglycemia
Less weight gain
Better efficacy (?)
More physiological action profiles
Less premeal lag time (0-15 mts)
Lispro & Glulisine even after meals
Better PP glucose control
Less intra-patient/inter-patient variability
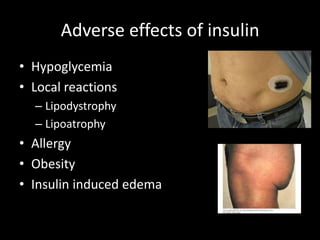
Improved predictability, tolerability, and flexibility Adverse effects of insulin Hypoglycemia Local reactions LipodystrophyLipoatrophyAllergy ObesityInsulin induced edema
Drug interactions of insulin Non selective beta blockers Thiazides,furosemide, corticosteroids, OCP , nifedipine↑ BSLAlcohol Precipitates hypoglycemia Salicylates, lithium, theophylline, may accenuate hypoglycemia
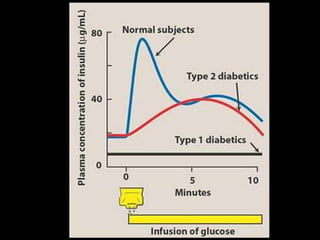
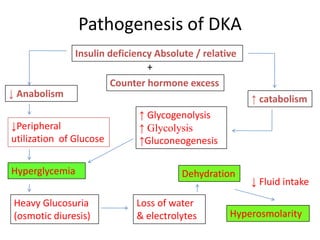
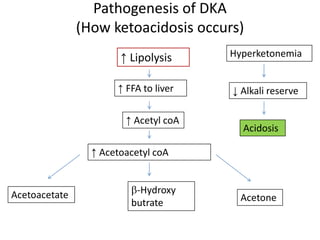
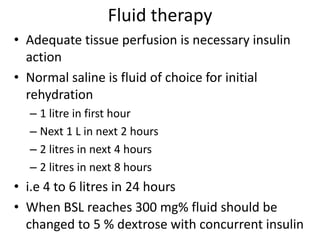
Uses of insulin Diabetes mellitus Must for type I diabetics Can be used in type II diabetics Diabetic ketoacidosisHyperosmolar non ketotic hyperglycemic coma
Indications of insulin in type II DMPrimary or secondary failure of oral hypoglycemicsPregnancyPerioperative period CKDSteroid therapyLADAFasting > 300 mgms HbA1c > 10Unintentional wt loss with or with out ketosisType 2 with DKA ( severe beta cell dysfunction)
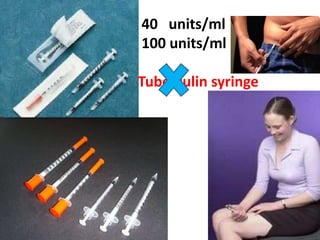
Recommended sites for S/C Insulin injections
Initial Insulin dosage in  T1DM 0.5 U/kg/day with negative to moderate ketones
0.7 U/kg/day with large ketonesClinical case14 yrs old, Chitra
3Ps & weight loss – 10 days duration
RBS 418 mg %
36 kg wt
No marked dehydration
T1DM- No ketoacidosis
Proceed?Insulin dose for this child(0.5 U/kg/day with negative to moderate ketones)
36 kg wt
No ketoacidosis
36 X 0.5 = 18 U/day18 U/day as“Four-shot-per-day”Basal-Bolus therapy
Ideal for better control & flexible lifestyle
50% Basal dose= 9 U at bedtime (NPH,G,D)
50% Bolus dose = 9 U premeals (R,A,L,Glu)3U Prebreakfast              3U Prelunch              3U Predinner
18 U/day as“Five-shot-per-day”Basal-Bolus therapy
Ideal for better control & flexible lifestyle but “too many shots”
50% Basal dose= 9 U divided as 5 U prebreakfast + 4 U at bedtime (G or D)
50% Bolus dose = 9 U premeals (R,A,L,Glu)3U Prebreakfast              3U Prelunch              3U Predinner
18 U/day as “Two-shot-per-day”Split mixed regimen 2/3 prebreakfast (12 U)
1/3 predinner (6 U)
Prebreakfast:8 U NPH + 4 U Regular (A,L,G)
Predinner:3 U NPH + 3 U Regular “8 N/4 R  -  0  -   3N/3R”
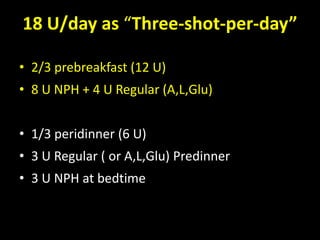
18 U/day as “Three-shot-per-day”2/3 prebreakfast (12 U)
8 U NPH + 4 U Regular (A,L,Glu)
1/3 peridinner (6 U)
3 U Regular ( or A,L,Glu) Predinner
3 U NPH at bedtimeHow to initiate insulin treatment in type 2Start with 0.2 units / kg  (or)
Body weight divided by 5  (or)
Dose = FBS-50    (or)                   10