Dr Kiran Rajagopal DA DNB.
Anaesthesiologist
CONGENITAL HEART DISEASE
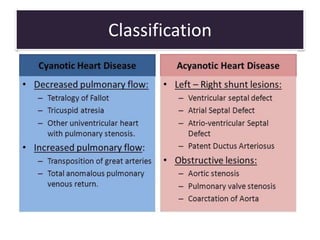
Classification
Simple Shunts
Obstructive
lesions
Complex
shunts
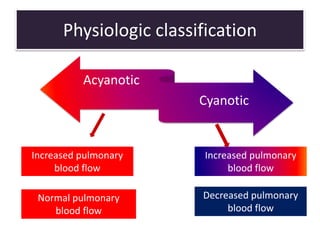
Physiologic classification
Acyanotic
Cyanotic
Increased pulmonary
blood flow
Normal pulmonary
blood flow
Increased pulmonary
blood flow
Decreased pulmonary
blood flow
Classification
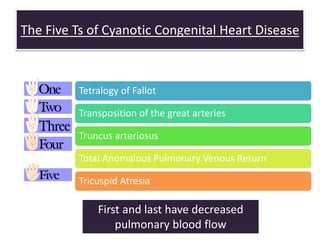
The Five Ts of Cyanotic Congenital Heart Disease
Tetralogy of Fallot
Transposition of the great arteries
Truncus arteriosus
Total Anomalous Pulmonary Venous Return
Tricuspid Atresia
First and last have decreased
pulmonary blood flow
Shunt lesions
Cardiac shunting is the process whereby venous return into one
circulatory system is recirculated through the arterial outflow of the
same circulatory system
Flow of blood from the systemic venous (right) atrium (RA) to the
aorta
Flow of blood from the pulmonary venous (left) atrium (LA) to the
pulmonary artery (PA)
Pathophysiology of congenital heart disease
• Recirculation of blood produces a physiological shunt
• In an anatomical shunt, blood moves from one circulatory
system to the other via a communication at the level of the
cardiac chambers or great vessels
• Physiological shunts can exist in the absence of an anatomical
shunt. Eg TGA
Plumbing principle
• Laws which govern the flow across a shunt
- Ohms law
- Hagen Poiseuille
• Combination & modification of both results in
plumbing principle
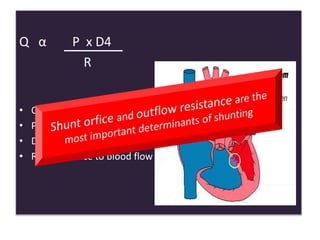
Q α P x D4
R
• Q = Blood flow
• P = Pressure gradient
• D = Diameter
• R = Resistance to blood flow
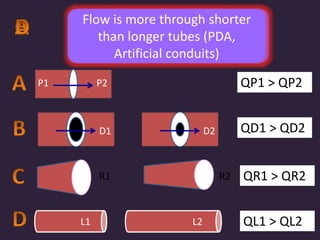
P1 P2 QP1 > QP2
QD1 > QD2D2D1
R1
L1
R2 QR1 > QR2
QL1 > QL2L2
Plumbing
principle
More flow through
VSD than ASD
More flow through a non
restrictive VSD than a restrictive
VSD
Flow depends on the vascular
resistance of the bed distal to
the shunt
Flow is more through shorter
than longer tubes (PDA,
Artificial conduits)
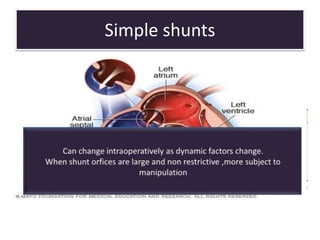
Simple shunts
• No associated obstructive lesions eg ASD
• Outflow resistance = SVR & PVR
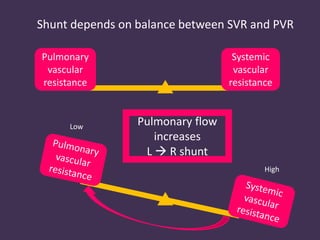
Shunt depends on balance between SVR and PVR
Pulmonary
vascular
resistance
Systemic
vascular
resistance
Low
High
Pulmonary flow
increases
L  R shunt
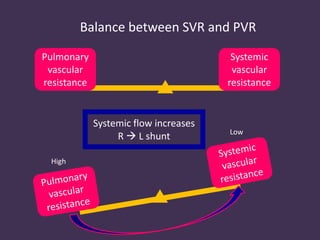
Balance between SVR and PVR
Pulmonary
vascular
resistance
Systemic
vascular
resistance
Low
High
Systemic flow increases
R  L shunt
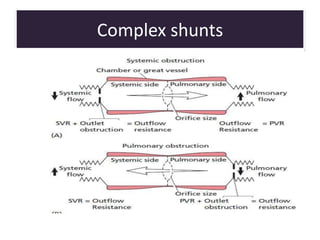
Complex shunts
• Fixed outflow obstruction present @
valvular, subvalvular, supravalvular level
or in major vessals eg TOF
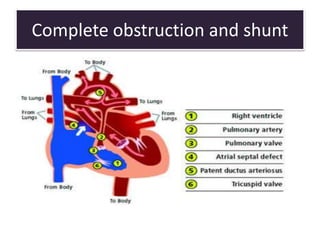
Complete obstruction and shunt
Complete obstruction to flow of blood
Shunting proximal to obstruction occurs
A downstream shunt provides flow to the
obstructed side of circulation.depends on
SVR & PVR
Eg PS with ASD & PDA
Manipulation of PVR & SVR
Ventilatory control
PVR can be controlled independently of SVR
by adjusting ventilation
Anesthetics and PVR
Ketamine & N2O increase PVR in adults
Not in infants with normal or increased PVR
Large doses of opiods attenuate stress response in
pulmonary vasculature to noxious stimuli like intubation
Adequate depth also decrese stress response in pulmonary
vasculature
Manipulation of SVR
Iv vasopressors are shunted R – L directly into the systemic
circulation  Increases SVR and decreases R – L shunt
Proximal aortic pressure can be increased by partially
occluding aorta with a clamp
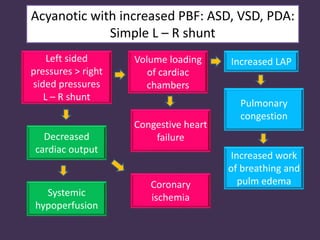
Acyanotic with increased PBF: ASD, VSD, PDA:
Simple L – R shunt
Left sided
pressures > right
sided pressures
L – R shunt
Volume loading
of cardiac
chambers
Increased LAP
Congestive heart
failure
Pulmonary
congestion
Decreased
cardiac output
Systemic
hypoperfusion
Coronary
ischemia
Increased work
of breathing and
pulm edema
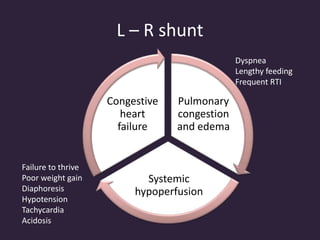
L – R shunt
Pulmonary
congestion
and edema
Systemic
hypoperfusion
Congestive
heart
failure
Failure to thrive
Poor weight gain
Diaphoresis
Hypotension
Tachycardia
Acidosis
Dyspnea
Lengthy feeding
Frequent RTI
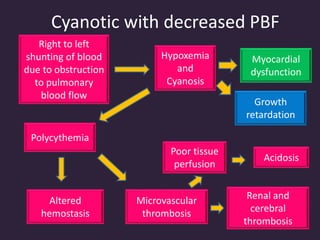
Cyanotic with decreased PBF
Right to left
shunting of blood
due to obstruction
to pulmonary
blood flow
Hypoxemia
and
Cyanosis
Polycythemia
Altered
hemostasis
Microvascular
thrombosis
Growth
retardation
Myocardial
dysfunction
Poor tissue
perfusion
Renal and
cerebral
thrombosis
Acidosis
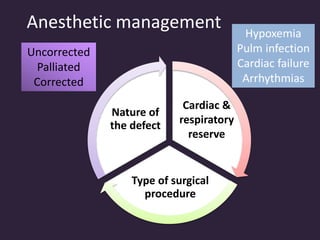
Anesthetic management
Type of surgical
procedure
Nature of
the defect
Cardiac &
respiratory
reserve
Uncorrected
Palliated
Corrected
Hypoxemia
Pulm infection
Cardiac failure
Arrhythmias
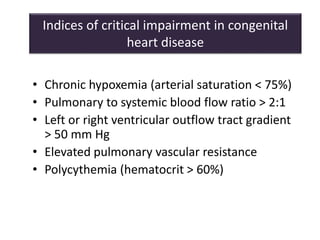
Indices of critical impairment in congenital
heart disease
• Chronic hypoxemia (arterial saturation < 75%)
• Pulmonary to systemic blood flow ratio > 2:1
• Left or right ventricular outflow tract gradient
> 50 mm Hg
• Elevated pulmonary vascular resistance
• Polycythemia (hematocrit > 60%)
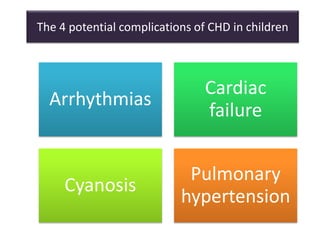
The 4 potential complications of CHD in children
Arrhythmias
Cardiac
failure
Cyanosis
Pulmonary
hypertension
Arrhythmias
Supraventricular Ventricular
• Atrial arrhythmias after
repair of ASDs
• Damage to AV node and
bundle of His after a
ventriculotomy or with RV
to PA conduit
Heart block
 After TOF repair
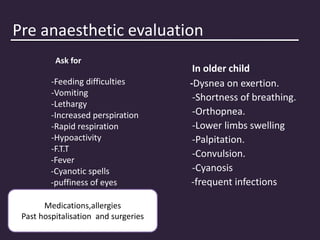
Pre anaesthetic evaluation
Ask for
-Feeding difficulties
-Vomiting
-Lethargy
-Increased perspiration
-Rapid respiration
-Hypoactivity
-F.T.T
-Fever
-Cyanotic spells
-puffiness of eyes
In older child
-Dysnea on exertion.
-Shortness of breathing.
-Orthopnea.
-Lower limbs swelling
-Palpitation.
-Convulsion.
-Cyanosis
-frequent infections
Medications,allergies
Past hospitalisation and surgeries
Physical examination
• Congestive heart failure will inhibit age-
appropriate gains in weight, height and head
circumference
• Cyanosis
• Clubbing
• Tachypnea
CVS
• organic murmurs
CNS
• Convulsions
• Signs of raised
intracranial tension
• An unsettling fever –
cerebral abscess
Respiratory
Increased PBF
• Crepitations
• Wheeze
• Bronchial breathing
signifies consolidated
lungs
Airway examination
• Airway abnormalities common
– Pierre Robin, Treacher Collins, Down’s
• Tracheal stenosis
– Previous prolonged intubation after cardiac
surgery
– Vascular rings
– Compression by enlarged CVS structures as well as
artificial conduits
Establish room air
saturation in all
cyanotics
Laboratory data
• Hb
• Blood routine
• Coagulation profile
• Electrolytes
• Arterial blood gases
• X ray chest
• ECG
• ECHO
• Cardiac cath
Continue cardiac drugs
• Unrepaired cyanotic CHD, including palliative
shunts and conduits
• Completely repaired congenital heart defect with
prosthetic material or device, whether placed by
surgery or by catheter intervention, during the
first 6 months after the procedure
• Repaired CHD with residual defects at the site or
adjacent to the site of a prosthetic patch or
prosthetic device (which inhibit
endothelialization)
Avoid air embolus.Use air trapsInfective endocarditis prophylaxis
•Prosthetic cardiac valve
•Previous IE
•Cardiac transplantation recepients who
develop valvulopathy
NPO Guidelines
• 2hrs for clear liquids
• 4 hours for breast milk
• 6hrs for formula
• 8hrs for solid food
• IV hydration during NPO
• Minimum NPO time
Dehydration
• deleterious effects on
haemodynamics
• Increase blood viscosity
in polycythemic patient
(cyanosis with Hct>60%)
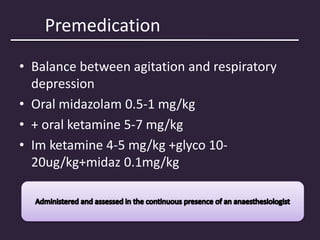
Premedication
• Balance between agitation and respiratory
depression
• Oral midazolam 0.5-1 mg/kg
• + oral ketamine 5-7 mg/kg
• Im ketamine 4-5 mg/kg +glyco 10-
20ug/kg+midaz 0.1mg/kg
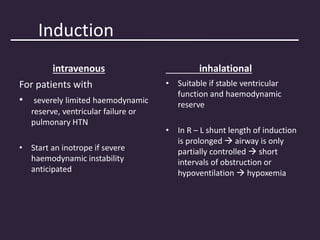
Induction
intravenous
For patients with
• severely limited haemodynamic
reserve, ventricular failure or
pulmonary HTN
• Start an inotrope if severe
haemodynamic instability
anticipated
inhalational
• Suitable if stable ventricular
function and haemodynamic
reserve
• In R – L shunt length of induction
is prolonged  airway is only
partially controlled  short
intervals of obstruction or
hypoventilation  hypoxemia
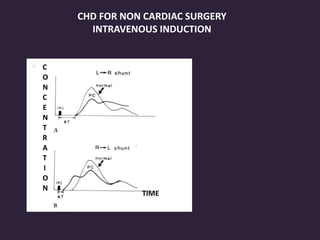
CHD FOR NON CARDIAC SURGERY
INTRAVENOUS INDUCTION
TIME
C
O
N
C
E
N
T
R
A
T
I
O
N
• Fentanyl 15-25 ug/kg + pancuronium 0.2 mg/kg
Good haemodynamic stability
Prompt airway control
Attenuates inc PVR due to intubation
• Vecuronium or cisatracurium may also be used
• Ketamine 1-3 mg/kg is an alternative
• Atropine or glycopyrrolate given
Maintenance
• Fentanyl + inhalational agent ( sevo 1-2%)
• Avoid nitrous
- risk of airbubbles
-Pulmonary HTN
• Use air to reduce FIO2
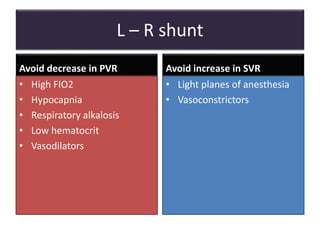
L – R shunt
Avoid decrease in PVR Avoid increase in SVR
• High FIO2
• Hypocapnia
• Respiratory alkalosis
• Low hematocrit
• Vasodilators
• Light planes of anesthesia
• Vasoconstrictors
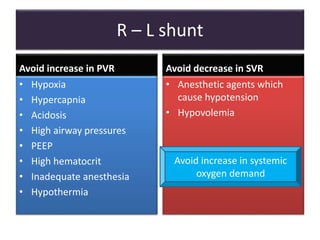
R – L shunt
Avoid increase in PVR Avoid decrease in SVR
• Hypoxia
• Hypercapnia
• Acidosis
• High airway pressures
• PEEP
• High hematocrit
• Inadequate anesthesia
• Hypothermia
• Anesthetic agents which
cause hypotension
• Hypovolemia
Avoid increase in systemic
oxygen demand
Choice of anaesthetic agents
Inhaled agents
Immature cardiovascular system
Decreased reserves
• Halothane ( 1& 1.5 MAC) depresses heart more than
sevo/iso/fentanyl+midazolam
• Sevoflurane – less depression & low risk of
arrythmias
Nitrous oxide
• Controversial
-enlarges air embolus
-increase PVR
• However, increases in pulmonary artery pressure or PVR in
infants given 50% nitrous oxide do not occur, regardless of pre
- existing PVR.
IV agents
• Provides a larger margin of safety
R – L shunts
• Very high transient ,arterial,cardiac,brain
concentrations occur when normal doses are given
as rapid infusion
-pulmonary circulation is bypassed
• Normal doses of lignocaine,barbiturates,beta
blockers may become toxic
Ketamine
• 2 mg/kg IV in premedicated infants and young
children does not increase pulmonary artery
pressure or PVR, even when the baseline PVR is
elevated.
• Ensure that the airway and ventilation are carefully
maintained
hypoventilation or apnea
PVR increases due to change in PaO2 & PaCO2
Opioids
• High - dose opioid anesthesia
excellent cardiovascular stability in children with CHD
No significant changes in pulmonary and systemic
hemodynamics
• Fentanyl (25 – 75 μ g/kg) and sufentanil (5 – 15 μ g/kg)
• Pancuronium - muscle relaxant of choice with high dose
opiods
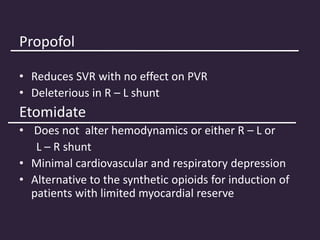
Propofol
• Reduces SVR with no effect on PVR
• Deleterious in R – L shunt
Etomidate
• Does not alter hemodynamics or either R – L or
L – R shunt
• Minimal cardiovascular and respiratory depression
• Alternative to the synthetic opioids for induction of
patients with limited myocardial reserve
Post operative care
• Adequate pain relief
– Pain increases SVR and PVR
– Pain worsens infundibular spasm of TOF
• Avoid respiratory depression
• Use regional analgesia wherever applicable
– Caution in cyanotics (coagulopathy)
– Can decrease SpO2 in R – L shunts
– Hazardous in left sided obstructive lesions
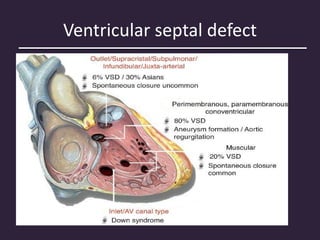
Ventricular septal defect
• An opening in the ventricular septum that permit
communication between RV and LV
• Membranous or perimembranous type
most common (80%)
• Subpulmonary or supracristal type
• Muscular defects
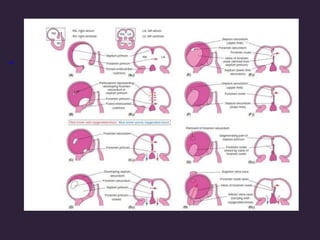
• Ventricular septation 5- 7 weeks
• The primordial interventricular septum arises from a median
muscular ridge between the right and left ventricular masses.
• Increased growth and dilation of the ventricles, combined
with fusion of the medial ventricular wall, result in
enlargement of the muscular ventricular septum
• The membranous portion of the septum is derived from tissue
ingrowth from the right side of the endocardial cushion to the
muscular region of the interventricular septum.
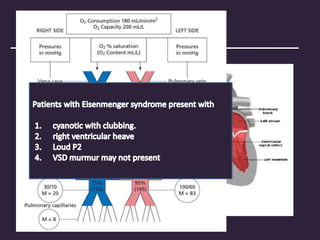
Haemodynamics
CVS
 holosystolic or pansystolic
murmur
 ESM at pulmonary area due to ↑
pulmonary flow
 Diastolic rumble at the apex
 left ventricular heave
 laterally displaced apical impulse
 S1 accentuated
 S2 wide & variable split
varies with respiration
ECG
• LVH
• RVH
• All children are born
with RVH
• RVH regresses more
slowely in VSD
• Develops LVH
• With the onset of PAH
RVH also seen
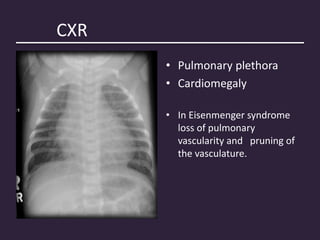
CXR
• Pulmonary plethora
• Cardiomegaly
• In Eisenmenger syndrome
loss of pulmonary
vascularity and pruning of
the vasculature.
Course & complications
• CCF in infancy
• Spontaneous closure in 70% cases
• Spontaneous closure occurs by 3 yrs, or as late as 20
yrs
• Pulmonic Stenosis– due to hypertrophy of Rt
ventricular infundibulum
• PAH
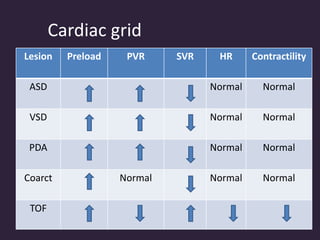
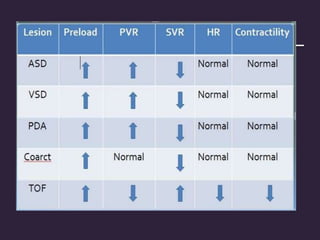
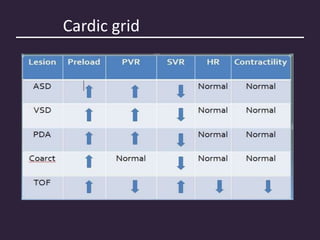
Cardiac grid
Lesion Preload PVR SVR HR Contractility
ASD Normal Normal
VSD Normal Normal
PDA Normal Normal
Coarct Normal Normal Normal
TOF
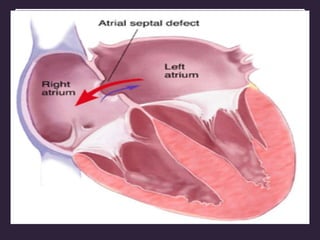
ATRIAL SEPTAL DEFECT
• Communication between the atria due to the
deficiency of tissue in the septum
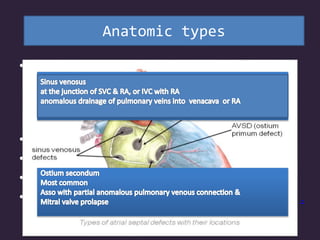
Anatomic types
• Defect at the fossa ovalis( ostium secondum
• Partial AV canal defects( ostium primum)
• Sinus venosus defects
• Coronary sinus defects .
Anatomic types
s
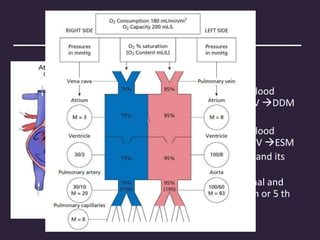
Haemodynamics
• L R shunt
• RAE
• Large volume of blood

through normal TV DDM
• RVH
• Large volume of blood
through normal PV ESM
• Pulmonary artery and its
branches enlarge
• PAP remains normal and
PVOD occur in 4 th or 5 th
decades
Physical examination
 A wide and fixed split of S2
 A loud P2 indicates
pulmonary hypertension
 A systolic ejection murmur,
of soft intensity is best
heard at the upper LSB
 A diastolic rumble heard at
the lower left sternal
border.
 A pansystolic murmur of
“mitral” regurgitation is
present in primum ASD.
Clinical picture
 Commonly asymptomatic
 Mild effort intolerance and chest infection may be the
presenting complaint
 Heart failure is rare in childhood
CVS
 Left parasternal impulse
 Mild to mod cardiomegaly
 S1 – normal or mild accentuation
 S2 – fixed and wide split without respiratory variation
 ESM gd 3 or less at Left 2nd ICS
 Low – medium pitched early diastolic murmur at the left
lower sternal border
ECG
 Secundum ASD—RT axis deviation & RVH
 rsR’ in V1 – characteristic ( indicates RV conduction delay)
 primum ASD – left axis deviation
 First degree heart block in primum ASD
 RVH
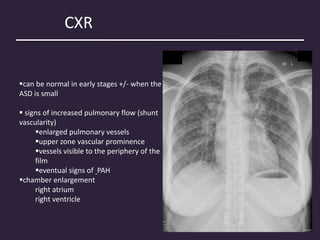
CXR
can be normal in early stages +/- when the
ASD is small
 signs of increased pulmonary flow (shunt
vascularity)
enlarged pulmonary vessels
upper zone vascular prominence
vessels visible to the periphery of the
film
eventual signs of PAH
chamber enlargement
right atrium
right ventricle
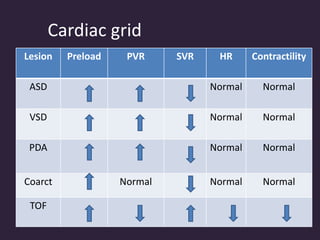
Cardiac grid
Lesion Preload PVR SVR HR Contractility
ASD Normal Normal
VSD Normal Normal
PDA Normal Normal
Coarct Normal Normal Normal
TOF
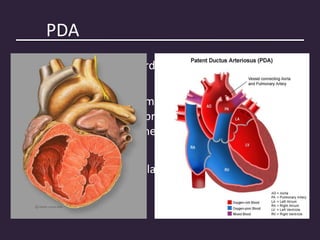
PDA
• Most common extracardiac shunt
• Connects the main pulmonary trunk near the origin
of the left PA with the proximal descending aorta just
distal to the origin of the left subclavian artery
• Left RLN lies in close relation
Haemodynamics
• L  R shunt
• Flow during systole & diastole
pressure gradient present throughout cardiac cycle
• Continuous murmur – starts after S1 peaks at S2 &
diminishes in intensity during diastole
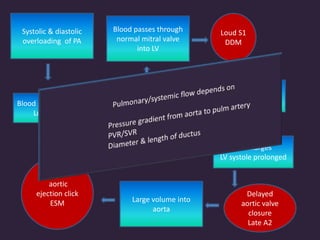
Systolic & diastolic
overloading of PA
Blood passes through
Lungs to LA LA enlarges
Blood passes through
normal mitral valve
into LV
Loud S1
DDM
Diastolic overoad of
LV
LV enlarges
LV systole prolonged
Delayed
aortic valve
closure
Late A2
Large volume into
aorta
aortic
ejection click
ESM
Clinical features
• History of maternal rubella in 1st trimester
• Common in premature infants with h/o of birth asphyxia,
respiratory distress
• Symptomatic early in life
• Heartfailure at 6 - 10 weeks
• Older children – effort intolerance,palpitation ,chest infection
CVS
• wide pulse pressure
• Hyperkinetic cardiac apex
• Thrill at 2nd left ICS
• S1 attenuated
• S2 narrow split, paradoxical split with large shunts
• Continuous murmur L 2nd ICS or below clavicle
• S3 & delayed diastolic murmurs with large shunts
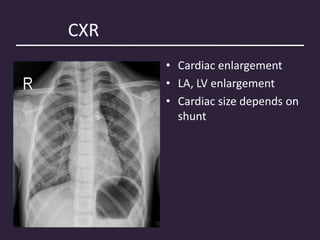
CXR
• • Cardiac enlargement
• LA, LV enlargement
• Cardiac size depends on
shunt
ECG
• LVH
• Deep Q with increased R
wave voltage in left
precordial leads
- LV volume overload
• RVH in pulmonary HTN
Complications
• Heart failure
• Pulmonary HTN
• Pulm HTN  R – L shunt  differential cyanosis
• Infective endocarditis
Surgical complications
• Bleeding during surgery ,if control of PDA lost during ligation
• Post ligation- systemic HTN
Mx – infusion of vasodilators
• Injuries to left RLN, left phrenic , thoracic duct
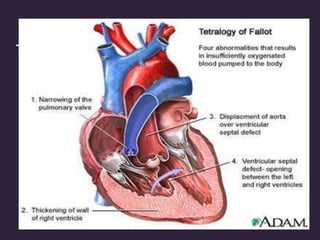
Tetrology of fallot
• Most common cyanotic cardiac lesion
• The four constituents are
• VSD
• RVH and RVOT Obstruction
• Overriding aorta
• Pulmonary stenosis and pulmonary hypoplasia
Haemodynamics
• Pulmonic stenosis  conc RVH  increase in RV pressure.
• R  L shunt occurs as RV pressure equals LV pressure
• R  L shunt is silent becase the flow occurs at insignificant
pressure difference
• Flow into pulmonary stenosis  ESM
• More severe the pulmonic stenosis  shorter the murmur
more R L  more cyanosis
• soft & inaudible P2
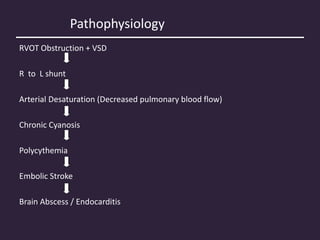
Pathophysiology
RVOT Obstruction + VSD
R to L shunt
Arterial Desaturation (Decreased pulmonary blood flow)
Chronic Cyanosis
Polycythemia
Embolic Stroke
Brain Abscess / Endocarditis
Cyanotic spells
• Episodes of paroxysmal dypsnea with marked cyanosis.
• These spells are usually self limiting but can lead to brain
damage or even death.
• It results from drastic reduction in pulmonary blood flow, with
increase in Rt  Lt shunt and decrese in Po2
Cyanotic spells- mechanism
• Exact mechanism is not known but the following postulates
are given:
• Increase in infundibular contractility
• Peripheral vasodilatation
• Hyperventilation
Cyanotic spells- mechanism
• Increase in infundibular contractility-results in decreased
pulmonary blood flow due to increased nor adrenaline level
• Peripheral vasodilatation →increase in right to left flow →
decrease in pulmonary blood flow
• Hyperventilation-- Cry→sudden rise of cardiac rate &
output→venous return in presence of relative fixed
pulmonary outflow
obstruction→R→Lshunt→pO2/pH,pCO2→Respiratory
centre response→ Hyperpnea→cardiac o/p still further
Treatment
 Oxygen
 Calm and comfort child
 Knee-chest position
 - - Compresses femoral arteries & inc SVR
 Morphine(0.05–0.10 mg/kg)
 --- May directly relax infundibulum,/action on CNS
 Intravenous fluids (10-15 ml/kg)
 Bicarbonate (1-2meq/kg)
 Beta-blocker ( propranalol 0.1 mg/kg or esmalol 0.5 mg/kg followed by 50-300
mcg/kg/min infusion)
 Vasoconstrictor (phenylephrine 5-10mcg/kg bolus or 2-5 mcg/kg/min infusion
 External compression of abdominal aorta
 General anesthesia with ETT
 Hyperventilation with FiO2 1.0 to reduce PVR
Pink tet
• A small subset of TOF patients have minimal obstruction to
pulmonary blood flow at the right ventricular outflow and PA
level and may have normal oxygen saturation.
• Some of these patients have a L–R shunt with increased
pulmonary blood flow and symptoms of CHF.
Clinical picture
 History & Clinical examination
 Tachycardia
 Low height and weight for age
 Clubbing of fingers and toes
 Systolic thrill along left parasternal border
 Parasternal lift
 Systolic ejection murmur
 Single S2
 ESM at left upper strenal border
CXR
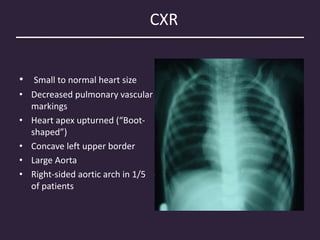
• Small to normal heart size
• Decreased pulmonary vascular
markings
• Heart apex upturned (“Boot-
shaped”)
• Concave left upper border
• Large Aorta
• Right-sided aortic arch in 1/5
of patients
• Right ventricular hypertrophy
causes the left ventricular
apex to be uplifted and cause
cardiomegaly. In addition, the
pulmonary artery segment
shadow, usually noted just
above the left atrial
appendage shadow is not
present due to small
pulmonary arteries. This give
the characteristic "Boot
shape" appearance of the
cardiac silhouette.
ECG
• Right axis deviation
• RVH
Complications
• Effort intolerance
• Anemia aggrevates dyspnoea
• Infective endocarditis
• Anoxic infarction in CNS
• Paradoxical embolism hemiplegia
• Venous thrombosis due to polycytemia
• Brain abscess
Surgical Management
Shunts
• Modified Blalock-Taussig ( subclavian to pulmonary)
• Blalock-Taussig
Full repair
• Transanular patch
• Valved conduit
Cardic grid
References
 STOELTING CO EXISTING DISEASES
 OP GHAI PAEDIATRICS
 GREGORYS PAED ANAESTHESIA
 DINARDO CARDIAC ANASTHESIA
 THE HEART – HURSTS
.
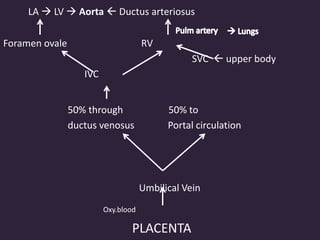
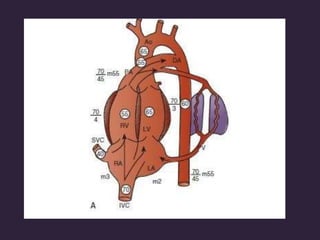
LA  LV  Aorta  Ductus arteriosus
Foramen ovale RV
SVC  upper body
IVC
50% through 50% to
ductus venosus Portal circulation
Umbilical Vein
Oxy.blood
PLACENTA
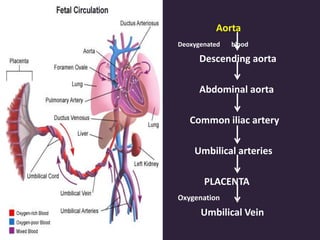
Aorta
Deoxygenated blood
Descending aorta
Abdominal aorta
Common iliac artery
Umbilical arteries
PLACENTA
Oxygenation
Umbilical Vein
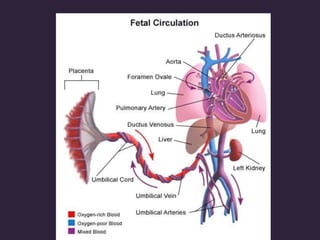
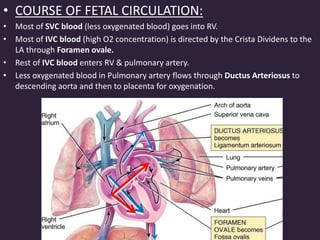
• COURSE OF FETAL CIRCULATION:
• Most of SVC blood (less oxygenated blood) goes into RV.
• Most of IVC blood (high O2 concentration) is directed by the Crista Dividens to the
LA through Foramen ovale.
• Rest of IVC blood enters RV & pulmonary artery.
• Less oxygenated blood in Pulmonary artery flows through Ductus Arteriosus to
descending aorta and then to placenta for oxygenation.
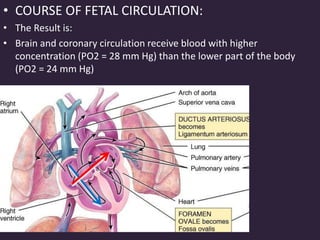
• COURSE OF FETAL CIRCULATION:
• The Result is:
• Brain and coronary circulation receive blood with higher
concentration (PO2 = 28 mm Hg) than the lower part of the body
(PO2 = 24 mm Hg)
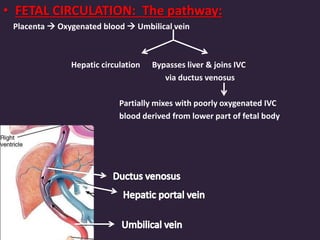
• FETAL CIRCULATION: The pathway:
Placenta  Oxygenated blood  Umbilical vein
Hepatic circulation Bypasses liver & joins IVC
via ductus venosus
Partially mixes with poorly oxygenated IVC
blood derived from lower part of fetal body
Congenital heart disease