DIAGNÓSTICO CLÍNICO Y
ESTADIAJE DEL
MESOTELIOMA-ASBESTO
DR. JORDI ROIG
Neumología
Clinical Features of Malignant Mesothelioma
Age 40-70 y
Male-to-female ratio 5:1
Risk factors
Asbestos exposure, eg, shipyard workers,
miners
Spouse of asbestos worker
Irradiation
Beryllium exposure
Latency period after asbestos
exposure
30-45 years
Type of asbestos fiber
Crocidolite  amosite > tremolite >
chrysotile
Incidence Nonasbestos exposure—1:1,000,000
Asbestos exposure—0.2-2:100
History of asbestos exposure 13%-76%
Smoking history 36%-71%
Symptoms to diagnosis
<6 mo 70%
>6 mo 28%
Survival without treatment
(after diagnosis)
6.8-15 mo
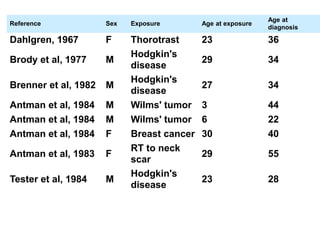
Reference Sex Exposure Age at exposure
Age at
diagnosis
Dahlgren, 1967 F Thorotrast 23 36
Brody et al, 1977 M
Hodgkin's
disease
29 34
Brenner et al, 1982 M
Hodgkin's
disease
27 34
Antman et al, 1984 M Wilms' tumor 3 44
Antman et al, 1984 M Wilms' tumor 6 22
Antman et al, 1984 F Breast cancer 30 40
Antman et al, 1983 F
RT to neck
scar
29 55
Tester et al, 1984 M
Hodgkin's
disease
23 28
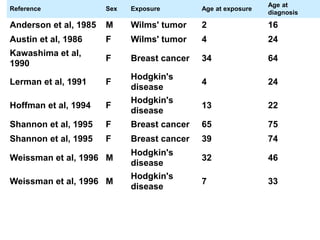
Reference Sex Exposure Age at exposure
Age at
diagnosis
Anderson et al, 1985 M Wilms' tumor 2 16
Austin et al, 1986 F Wilms' tumor 4 24
Kawashima et al,
1990
F Breast cancer 34 64
Lerman et al, 1991 F
Hodgkin's
disease
4 24
Hoffman et al, 1994 F
Hodgkin's
disease
13 22
Shannon et al, 1995 F Breast cancer 65 75
Shannon et al, 1995 F Breast cancer 39 74
Weissman et al, 1996 M
Hodgkin's
disease
32 46
Weissman et al, 1996 M
Hodgkin's
disease
7 33
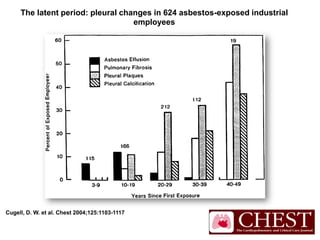
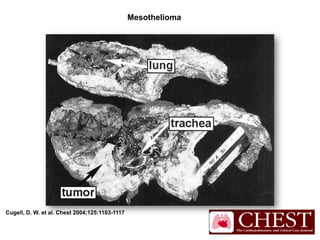
Cugell, D. W. et al. Chest 2004;125:1103-1117
The latent period: pleural changes in 624 asbestos-exposed industrial
employees
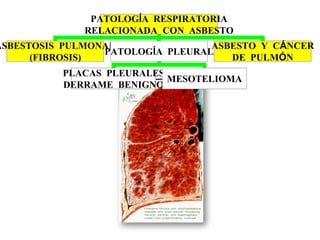
PATOLOGÍA RESPIRATORIA
RELACIONADA CON ASBESTO
ASBESTOSIS PULMONAR
(FIBROSIS)
PATOLOGÍA PLEURAL
ASBESTO Y CÁNCER
DE PULMÓN
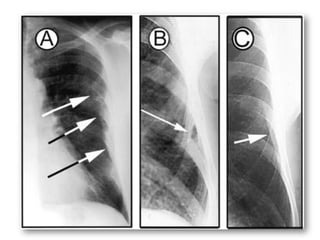
PLACAS PLEURALES
DERRAME BENIGNO
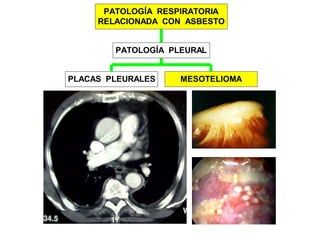
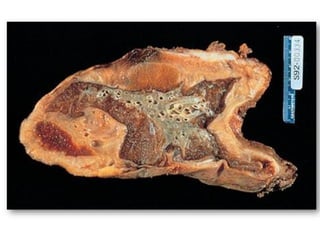
MESOTELIOMA
PLACAS PLEURALES MESOTELIOMA
PATOLOGÍA PLEURAL
PATOLOGÍA RESPIRATORIA
RELACIONADA CON ASBESTO
Clinical Presentation of Malignant
Pleural Mesothelioma (MPM)
 Symptoms Observed in Most Patients
 Chest pain
 Shortness of breath
 Weight loss
 Other Symptoms
 Cough
 Hoarseness
 Fever
 Sweats
Clinical Presentation of MPM
 Physical Examination
 Asymmetric chest excursion
 Unilaterally decreased breath sounds
 Laboratory Findings
 Laboratory studies are generally not useful
in disease diagnosis. However, leukocytosis,
anemia, thrombocytosis, and elevated LDH
are commonly observed.
Cancer: Principles and Practices of Oncology, 6th ed. Philadelphia,
PA: Lippincott Williams & Wilkins; 2001:1943-1969.
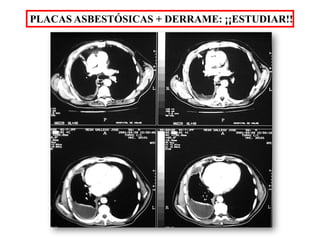
PLACAS ASBESTÓSICAS + DERRAME: ¡¡ESTUDIAR!!
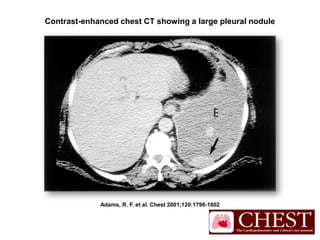
Adams, R. F. et al. Chest 2001;120:1798-1802
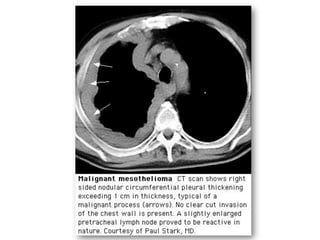
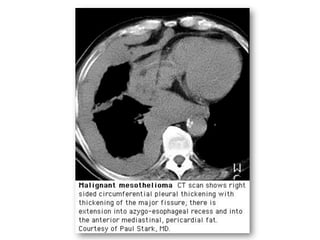
Contrast-enhanced chest CT showing a large pleural nodule
Differential Diagnosis of MPM
Often misdiagnosed
Adenocarcinoma may mimic epithelial
presentation
Adenocarcinomas from primary lung,
breast, stomach, kidney, ovary, and
prostate cancers metastasizing to
the lung pleura can resemble
mesothelioma
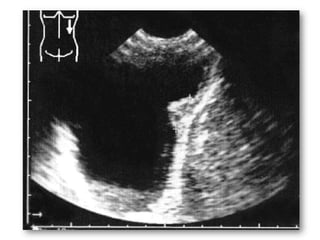
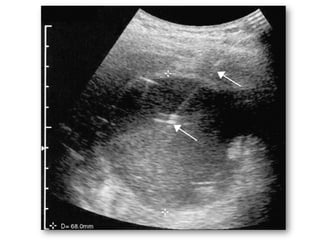
Examination of pleural fluid or BCN-FNA
aspirates may aid differential diagnosis
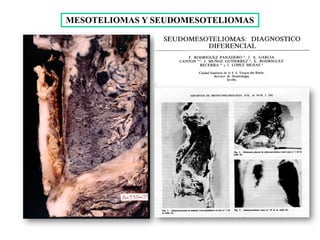
MESOTELIOMAS Y SEUDOMESOTELIOMAS
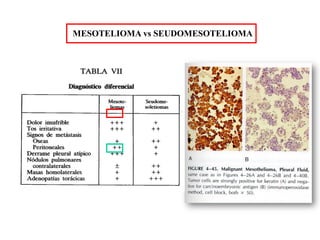
MESOTELIOMA vs SEUDOMESOTELIOMA
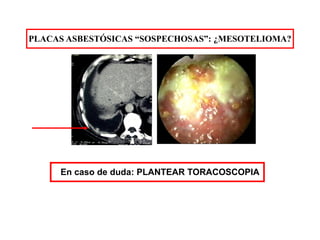
PLACAS ASBESTÓSICAS “SOSPECHOSAS”: ¿MESOTELIOMA?
En caso de duda: PLANTEAR TORACOSCOPIA
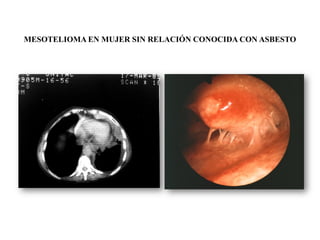
MESOTELIOMA EN MUJER SIN RELACIÓN CONOCIDA CON ASBESTO
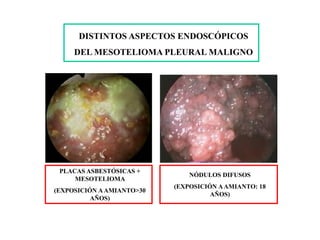
DISTINTOS ASPECTOS ENDOSCÓPICOS
DEL MESOTELIOMA PLEURAL MALIGNO
PLACAS ASBESTÓSICAS +
MESOTELIOMA
(EXPOSICIÓN AAMIANTO>30
AÑOS)
NÓDULOS DIFUSOS
(EXPOSICIÓN AAMIANTO: 18
AÑOS)
Soluble mesothelin-related
protein – A blood test (MM)
 Sensitivity 83% (n=48) and specificity
100% when compared to other effusions

 With lung tumors: ↓ specificity to 95%
 Other asbestos exposed: ↓ specificity to 82%
 May be increased prior to presentation
 Seven of 40 healthy asbestos exposed had ↑
levels and 3 developed MM at 1-5 years
 None of other 33 exposed developed MM<8 years
Robinson B et al. Lung Cancer 2005
Brigham/Dana Farber Cancer Institute staging of malignant pleural
mesothelioma
The Revised* Brigham/DFCI Staging System for Malignant Pleural
Mesothelioma
Stage Description
I
Disease completely resected within the capsule of the
parietal pleura without adenopathy; ipsilateral pleura,
lung, pericardium, diaphragm, or chest wall disease
limited to previous biopsy sites

II
All of stage I with positive resection margins and/or
intrapleural adenopathy
III
Local extension of disease into the chest wall or
mediastinum, into the heart or through the diaphragm,
into the peritoneum, or with extrapleural lymph node
involvement
IV Distant metastatic disease
*Patients with Butchart stage II or III disease are combined into stage III. Stage I
represents patients with resectable disease and negative nodes. Stage II
indicates resectable disease but positive nodes.
Cugell, D. W. et al. Chest 2004;125:1103-1117
Mesothelioma
Stage Description
T1A  Tumor limited to the ipsilateral parietal pleura, including
mediastinal and diaphragmatic pleura. No involvement of the
visceral pleura
T1B  Tumor involving the ipsilateral parietal pleura, including
mediastinal and diaphragmatic pleura. Scattered foci of tumor
also involving the visceral pleura
T2  Tumor involving each of the ipsilateral pleural surfaces (parietal,
mediastinal, diaphragmatic, and visceral pleura) with at least one
of the following features:
 Involvement of the diaphragmatic muscle
 Confluent visceral pleural tumor (including the fissures) or extension of
tumor from visceral pleura into the underlying pulmonary parenchyma
New International Mesothelioma
Interest Group (IMIG) Staging System
Chest 1995;108:1122-1128.
Stage Description
T3  Tumor involving each of the ipsilateral pleural
surfaces (parietal, mediastinal, diaphragmatic, and
visceral pleura) with at least one of the following
features:
 Involvement of the endothoracic fascia
 Extension into the mediastinal fat
 Solitary, completely resectable focus of tumor
extending into the soft tissues of the chest wall
 Nontransmural involvement of the pericardium
New International Mesothelioma
Interest Group (IMIG) Staging System
(cont’d)
Chest 1995;108:1122-1128.
Stage Description
T4
 Locally advanced technically unresectable tumor
 Tumor involving all of the ipsilateral pleural surfaces (parietal,
mediastinal, diaphragmatic, and visceral pleura) with at least
one
of the following features:
 Diffuse extension or multifocal masses of tumor to the
peritoneum
 Direct transdiaphragmatic extension of tumor to the
peritoneum
 Direct extension of tumor to the contralateral pleura
 Direct extension of tumor to one or more mediastinal
organs
 Direct extension of tumor into the spine
 Tumor extending through to the internal surface of the
pericardium with
or without a pericardial effusion; or tumor involving the
myocardium
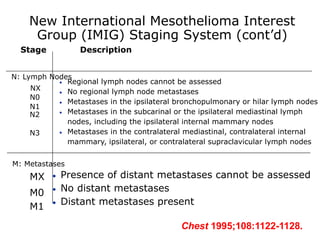
New International Mesothelioma Interest
Group (IMIG) Staging System (cont’d)
Chest 1995;108:1122-1128.
Stage Description
N: Lymph Nodes
 Regional lymph nodes cannot be assessed
 No regional lymph node metastases
 Metastases in the ipsilateral bronchopulmonary or hilar lymph nodes
 Metastases in the subcarinal or the ipsilateral mediastinal lymph
nodes, including the ipsilateral internal mammary nodes
 Metastases in the contralateral mediastinal, contralateral internal
mammary, ipsilateral, or contralateral supraclavicular lymph nodes
 Presence of distant metastases cannot be assessed
 No distant metastases
 Distant metastases present
NX
N0
N1
N2
N3
M: Metastases
MX
M0
M1
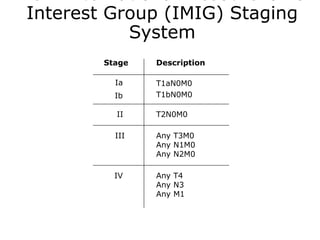
New International Mesothelioma Interest
Group (IMIG) Staging System (cont’d)
Chest 1995;108:1122-1128.
Stage Description
Ia T1aN0M0
T1bN0M0
II T2N0M0
III Any T3M0
Any N1M0
Any N2M0
IV Any T4
Any N3
Any M1
Ib
Interest Group (IMIG) Staging
System
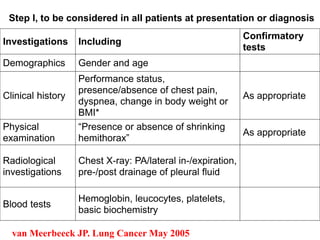
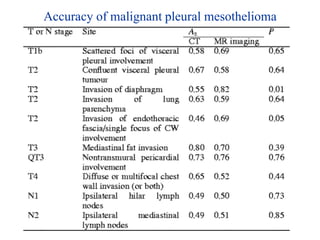
Accuracy of malignant pleural mesothelioma
Investigations Including
Confirmatory
tests
Demographics Gender and age
Clinical history
Performance status,
presence/absence of chest pain,
dyspnea, change in body weight or
BMI*
As appropriate
Physical
examination
“Presence or absence of shrinking
hemithorax”
As appropriate
Radiological
investigations
Chest X-ray: PA/lateral in-/expiration,
pre-/post drainage of pleural fluid
Blood tests
Hemoglobin, leucocytes, platelets,
basic biochemistry
van Meerbeeck JP. Lung Cancer May 2005
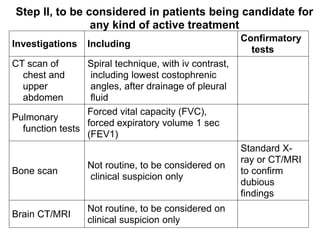
Step I, to be considered in all patients at presentation or diagnosis
Investigations Including
Confirmatory
tests
CT scan of
chest and
upper
abdomen
Spiral technique, with iv contrast,
including lowest costophrenic
angles, after drainage of pleural
fluid
Pulmonary
function tests
Forced vital capacity (FVC),
forced expiratory volume 1 sec
(FEV1)
Bone scan
Not routine, to be considered on
clinical suspicion only
Standard X-
ray or CT/MRI
to confirm
dubious
findings
Brain CT/MRI
Not routine, to be considered on
clinical suspicion only
Step II, to be considered in patients being candidate for
any kind of active treatment
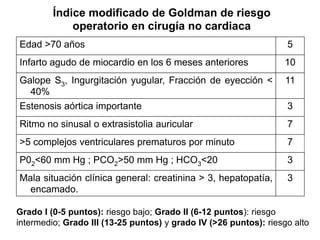
Índice modificado de Goldman de riesgo
operatorio en cirugía no cardiaca
Edad >70 años 5
Infarto agudo de miocardio en los 6 meses anteriores 10
Galope S3, Ingurgitación yugular, Fracción de eyección <
40%
11
Estenosis aórtica importante 3
Ritmo no sinusal o extrasistolia auricular 7
>5 complejos ventriculares prematuros por minuto 7
P02<60 mm Hg ; PCO2>50 mm Hg ; HCO3<20 3
Mala situación clínica general: creatinina > 3, hepatopatía,
encamado.
3
Grado I (0-5 puntos): riesgo bajo; Grado II (6-12 puntos): riesgo
intermedio; Grado III (13-25 puntos) y grado IV (>26 puntos): riesgo alto
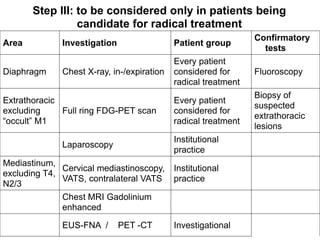
Area Investigation Patient group
Confirmatory
tests
Diaphragm Chest X-ray, in-/expiration
Every patient
considered for
radical treatment
Fluoroscopy
Extrathoracic
excluding
“occult” M1
Full ring FDG-PET scan
Every patient
considered for
radical treatment
Biopsy of
suspected
extrathoracic
lesions
Laparoscopy
Institutional
practice
Mediastinum,
excluding T4,
N2/3
Cervical mediastinoscopy,
VATS, contralateral VATS
Institutional
practice
Chest MRI Gadolinium
enhanced
EUS-FNA / PET -CT Investigational
Step III: to be considered only in patients being
candidate for radical treatment
The consensus panel further agrees on that:
1. The interval within which the assessment has to
be finalized should be as short as possible.
2. Recent (<1-month-old) imaging studies should be
available prior to invasive procedures.
3. Further research is done with regard to the
comparative efficacy of the different intrathoracic
techniques (mediastinoscopy, VATS, EUS-FNA)
and the value of the newer ones (PET-CT, EUS-
FNA).
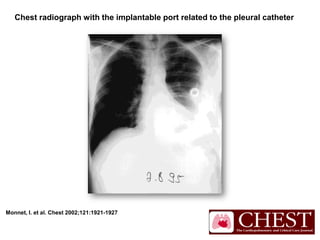
Monnet, I. et al. Chest 2002;121:1921-1927
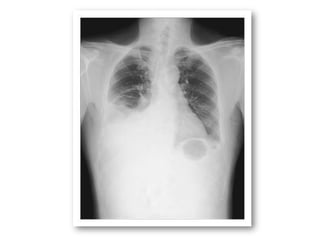
Chest radiograph with the implantable port related to the pleural catheter
Diagnostico clínico y estadiaje del  mesotelioma asbesto