The Emerging Picture of “Value
       Based Pricing”
     Kakushin Web-Based Conference
            17 October 2012

              Jon Sussex
            Deputy Director
      Office of Health Economics
             www.ohe.org


                                     1
Agenda

• What we know about UK Government “VBP”
  proposals
• What that might mean in practice
• Centrality of “threshold” concept
• Non-linear pricing etc.
• Conclusions
At the NICE Annual Conference, 11 May 2011,
    Earl Howe (Minister of Health) stated:

 • “What Ministers are seeking are new arrangements to
   encourage the development of drugs to address areas of
   unmet need and bring prices and benefits into line”
 • “We've got to think about moving away from the drugs
   budget and towards a health budget”
 • Ministers “are not too afraid of increasing the drugs budget,
   as such”
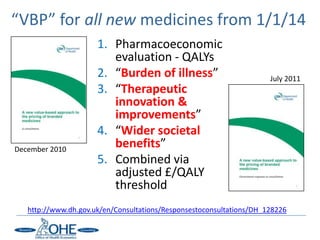
“VBP” for all new medicines from 1/1/14
                      1. Pharmacoeconomic
                         evaluation - QALYs
                      2. “Burden of illness”                          July 2011
                      3. “Therapeutic
                         innovation &
                         improvements”
                      4. “Wider societal
December 2010
                         benefits”
                      5. Combined via
                         adjusted £/QALY
                         threshold
   http://www.dh.gov.uk/en/Consultations/Responsestoconsultations/DH_128226
“4.10 The Government proposes that the price threshold
structure is determined as follows:
i. there would be a basic threshold, reflecting the benefits
displaced elsewhere in the NHS when funds are allocated to new
medicines;
ii. there would be higher thresholds for medicines that tackle
diseases where there is greater “burden of illness”: the more the
medicine is focused on diseases with unmet need or which are
particularly severe, the higher the threshold;
iii. there would be higher thresholds for medicines that can
demonstrate greater therapeutic innovation and improvements
compared with other products;
iv. there would be higher thresholds for medicines that can
demonstrate wider societal benefits.”
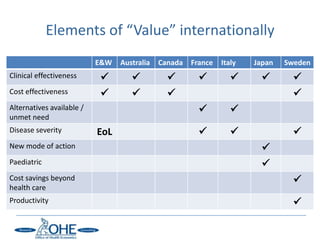
Elements of “Value” internationally
                           E&W   Australia   Canada   France   Italy   Japan   Sweden
Clinical effectiveness                                                     
Cost effectiveness                                                            
Alternatives available /                                         
unmet need
Disease severity           EoL                                                 
New mode of action                                                       
Paediatric                                                               
Cost savings beyond                                                              
health care
Productivity                                                                     
VBP – Taxonomy of approaches
     What elements                     How measured                            How                          How linked to
       of value                         and valued                          aggregated                         price
    • QALYs                           • Natural units                   • Deliberative                    • Formula
    • Other types of                  • Categories                        process                         • Negotiation
      health gain                     • Yes/No                          • Weighted
    • Severity                                                            QALYs
    • ‘Unmet need’                    • Whose                           • MCDA*
    • ‘Innovation’                      values?                         • Net benefit £
    • Wider societal
      impacts

                                                                       *MCDA = Multi-Criteria Decision Analysis

For full info see OHE Research Paper 11/04; Sussex, Towse & Devlin; August 2011 at:
http://www.ohe.org/publications/recent-publications/list-by-title-20/detail/date////operationalising-value-based-pricing-of-medicines-a-
taxonomy-of-approaches.html
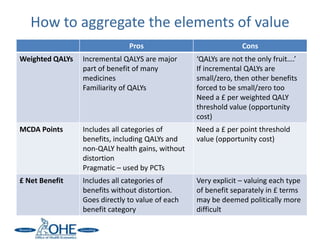
How to aggregate the elements of value
                               Pros                             Cons
Weighted QALYs   Incremental QALYS are major      ‘QALYs are not the only fruit….’
                 part of benefit of many          If incremental QALYs are
                 medicines                        small/zero, then other benefits
                 Familiarity of QALYs             forced to be small/zero too
                                                  Need a £ per weighted QALY
                                                  threshold value (opportunity
                                                  cost)
MCDA Points      Includes all categories of       Need a £ per point threshold
                 benefits, including QALYs and    value (opportunity cost)
                 non-QALY health gains, without
                 distortion
                 Pragmatic – used by PCTs
£ Net Benefit    Includes all categories of       Very explicit – valuing each type
                 benefits without distortion.     of benefit separately in £ terms
                 Goes directly to value of each   may be deemed politically more
                 benefit category                 difficult
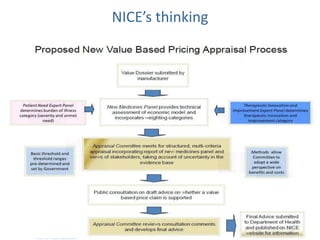
NICE’s thinking
DH Response to the Consultation
• 5.8 “…we intend to maintain the effect of the funding direction…”
• 5.9 “…there are questions about the impact of medicine prices on
  companies’ decisions on where to allocate investments or conduct
  research…”
• 5.28 “..the Government does not agree that a new medicine should
  be automatically exempted..because its total budget impact is
  ..below an arbitrary threshold..”
• 5.47 “…the benefits of enabling pricing by indication are likely to be
  outweighed by the practical difficulties…explore alternatives..”
• 5.60 “..we recognise the value that incremental developments can
  bring…”
• 5.102 “…we have not ruled out the possibility that there may be a
  role for some type of Patient Access Scheme (PAS) arrangements…”
• 6.5 “Our preference ..would be..to achieve a negotiated
  settlement…”
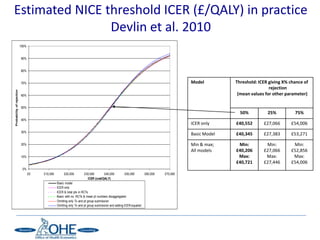
Estimated NICE threshold ICER (£/QALY) in practice
                Devlin et al. 2010
                           100%


                           90%


                           80%


                           70%                                                                                                          Model         Threshold: ICER giving X% chance of
                                                                                                                                                                      rejection
Probability of rejection


                           60%                                                                                                                         (mean values for other parameter)

                           50%
                                                                                                                                                        50%          25%          75%
                           40%
                                                                                                                                        ICER only     £40,552      £27,066      £54,006
                           30%
                                                                                                                                        Basic Model   £40,345      £27,383      £53,271

                           20%                                                                                                          Min & max;     Min:         Min:         Min:
                                                                                                                                        All models    £40,206      £27,066      £52,856
                           10%                                                                                                                         Max:         Max:         Max:
                                                                                                                                                      £40,721      £27,446      £54,006
                            0%
                                  £0   £10,000        £20,000        £30,000       £40,000          £50,000         £60,000   £70,000
                                                                       ICER (cost/QALY)
                                                 Basic model
                                                 ICER only
                                                 ICER & total pts in RCTs
                                                 Basic with no. RCTs & mean pt numbers disaggregated
                                                 Omitting only Tx and pt group submission
                                                 Omitting only Tx and pt group submission and adding ICER-squared
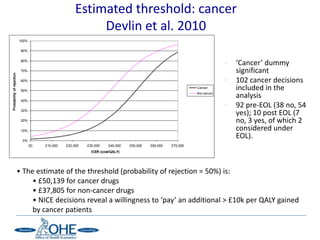
Estimated threshold: cancer
                                                           Devlin et al. 2010
                           100%

                            90%

                            80%
                                                                                                                           •   ‘Cancer’ dummy
                            70%                                                                                                significant
Probability of rejection


                            60%                                                                                            •   102 cancer decisions
                            50%
                                                                                                              Cancer           included in the
                                                                                                              Not cancer
                                                                                                                               analysis
                            40%
                                                                                                                           •   92 pre-EOL (38 no, 54
                            30%
                                                                                                                               yes); 10 post EOL (7
                            20%                                                                                                no, 3 yes, of which 2
                            10%                                                                                                considered under
                            0%
                                                                                                                               EOL).
                                  £0   £10,000   £20,000   £30,000    £40,000   £50,000   £60,000   £70,000
                                                             ICER (cost/QALY)


                           • The estimate of the threshold (probability of rejection = 50%) is:
                                • £50,139 for cancer drugs
                                • £37,805 for non-cancer drugs
                                • NICE decisions reveal a willingness to ‘pay’ an additional > £10k per QALY gained
                                by cancer patients
“Thresholds” or converting benefits into £

• NB: If benefits include more than QALYs then idea of a
  unique £/QALY threshold becomes redundant
• NHS opportunity cost (OC)
• Social value of a QALY (SV)
• Equal in an ideal world but the world is not ideal
• SV of a QALY in UK appears to be around or a bit above
  NICE’s £20k-£30k range but there is much uncertainty
  as valuations vary wildly across individuals
• If SV>OC then health care budget spending is below
  socially desired levels
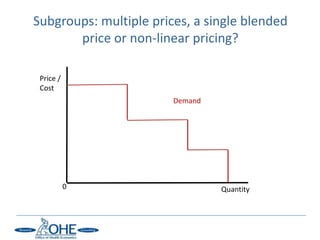
Subgroups: multiple prices, a single blended
       price or non-linear pricing?

 Price /
 Cost
                        Demand


           0                     Quantity
Different prices for different indications
           with different values?
• Single ‘blended’ price
• Or different prices for different indications:
  • NICE technology appraisal TA176 for cetuximab
    required a 16% discount when used with
    oxaliplatin (+ 5-fluorouracil and folinic acid)
  • But not for another (+5FU, folinic acid and
    irinotecan) where the patient cannot take
    oxaliplatin
Negotiation and PAS
• Imprecision / uncertainty / multiple indications =>
  plenty of scope for negotiation where the “value
  based price” is a binding constraint

• VBP does not imply no further role for Patient Access
  Schemes and non-linear pricing:
  Government VBP consultation response, July 2011:
  “We have not ruled out … ‘PAS’ arrangements in the
  new system.”
“VBP”: big change or name change?

• Wider scope of benefits and costs taken into
  account
• Chance for more openness or likelihood of
  less?
• Price negotiation for individual medicines, not
  regulation of company profit from total sales
  to NHS
To enquire about additional information and analyses, please
contact Jon Sussex at jsussex@ohe.org

To keep up with the latest news and research, subscribe to our blog, OHE
News
Follow us on Twitter @OHENews, LinkedIn and SlideShare

Office of Health Economics (OHE)
Southside, 7th Floor
105 Victoria Street
London SW1E 6QT
United Kingdom
+44 20 7747 8850
www.ohe.org
OHE’s publications may be downloaded free of charge for registered users of its
website.

©2012 OHE