“Yes! We CanEnd TB: Led by countries,
powered by people”
Dr.Avinash
2.
World TB Day
•On this day in 1882 Robert Koch discovered Tuberculosis bacilli.
• In 1982, on the one-hundredth anniversary of Robert Koch's
presentation, the
International Union Against Tuberculosis and Lung Disease (IUATLD)
proposed that 24 March be proclaimed an official World TB Day.
• To raise awareness about tuberculosis and promote global efforts to
end the disease.
3.
Tuberculosis
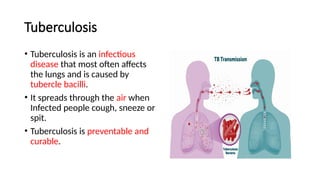
• Tuberculosis isan infectious
disease that most often affects
the lungs and is caused by
tubercle bacilli.
• It spreads through the air when
Infected people cough, sneeze or
spit.
• Tuberculosis is preventable and
curable.
4.
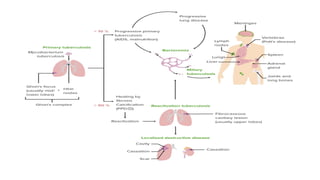
• About aquarter of the global population is estimated to have been
infected with TB bacteria. About 5-10% of people infected with TB will
eventually get symptoms and develop TB disease.
• Those who are infected but not yet ill with the disease cannot
transmit TB disease.
• TB disease usually treated with anti-TB drugs and can be fatal without
treatment.
5.
Clinical features
• TBcan affect any organ system
in human body
• Respiratory system is the most
commonly affected in nearly
85% of cases
• Pulmonary TB
• Extra pulmonary TB
7.
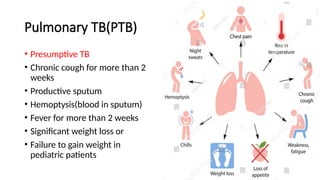
Pulmonary TB(PTB)
• PresumptiveTB
• Chronic cough for more than 2
weeks
• Productive sputum
• Hemoptysis(blood in sputum)
• Fever for more than 2 weeks
• Significant weight loss or
• Failure to gain weight in
pediatric patients
8.
Extra Pulmonary TB(EPTB)
•Symptoms will be organ specific
• 20-30% of will have pulmonary
TB
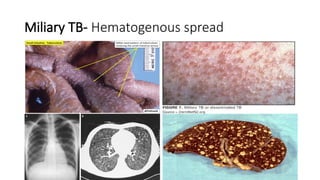
• Spread- Hematogenous or
lymphatic spread
• Constitutional symptoms like
fever, malaise, weight loss and
night sweats
9.
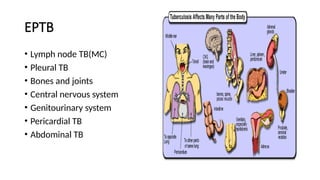
EPTB
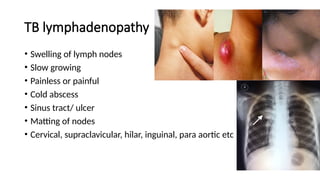
• Lymph nodeTB(MC)
• Pleural TB
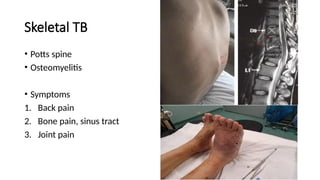
• Bones and joints
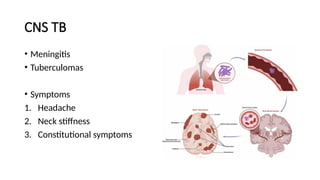
• Central nervous system
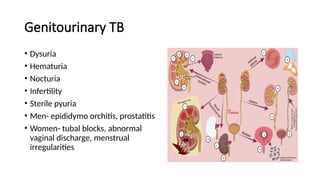
• Genitourinary system
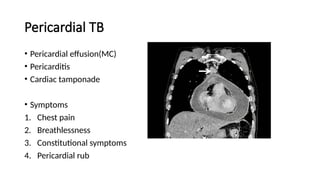
• Pericardial TB
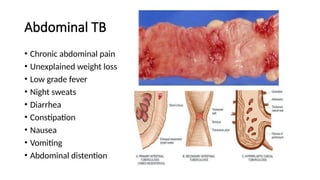
• Abdominal TB
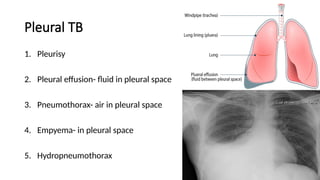
Pleural TB
1. Pleurisy
2.Pleural effusion- fluid in pleural space
3. Pneumothorax- air in pleural space
4. Empyema- in pleural space
5. Hydropneumothorax
12.
• Symptoms andsigns
1. Chest pain
2. Cough- dry or with sputum
3. Progressive breathlessness
4. Constitutional symptoms
5. Pleural rub on auscultation
6. Dullness on percussion in pleural effusion, hyper resonance in
pneumothorax
Case definitions
• Abacteriologically confirmed TB case is one from whom a biological
specimen is positive by smear microscopy, culture or WHO approved
Rapid Diagnostics such as Xpert MTB/RIF(WRD).
• A clinically diagnosed TB case is one who does not fulfil the criteria
for bacteriological confirmation but has been diagnosed with active
TB by a clinician.
• This definition includes cases diagnosed on the basis of X-ray
abnormalities or suggestive histology and extrapulmonary cases
without laboratory confirmation.
22.
Classification based onhistory of previous TB
treatment
• New patients have never been treated for TB or have taken anti-TB
drugs for less than 1 month.
• Previously treated patients have received 1 month or more of anti-TB
drugs in the past. They are further classified by the outcome of thier
most recent course of treatment.
• Relapse patients have previously been treated for TB, were declared
cured or treatment completed at the end of their most recent course
of treatment, and are now diagnosed with a recurrent episode of TB.
23.
• Treatment afterfailure patients are those who have previously been
treated for TB and whose treatment failed at the end of their most
recent course of treatment.
• Treatment after loss to follow up patients have previously been
treated for TB and were declared lost to follow up at the end of their
most recent course of treatment.
24.
Classification based ondrug resistance
• H mono/poly DR-TB – Isoniazid resistant / resistant to INH & first-line
drugs other than Rifampicin
• Multidrug resistance(MDR): Rifampicin resistance with or without
Isoniazid resistance
• Pre-extensively drug-resistant TB (Pre-XDR-TB) – MDR-TB with
additional Fluoroquinolone resistance detected
• Extensively drug-resistant TB (XDR-TB) – Pre-XDR-TB with resistance
to Linezolid or Bedaquiline or both detected.
25.
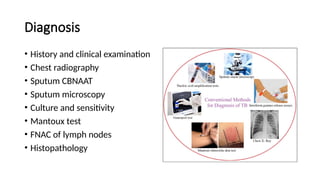
Diagnosis
• History andclinical examination
• Chest radiography
• Sputum CBNAAT
• Sputum microscopy
• Culture and sensitivity
• Mantoux test
• FNAC of lymph nodes
• Histopathology
26.
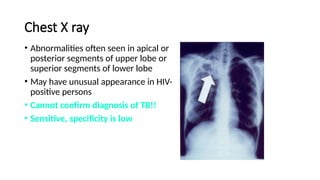
Chest X ray
•Abnormalities often seen in apical or
posterior segments of upper lobe or
superior segments of lower lobe
• May have unusual appearance in HIV-
positive persons
• Cannot confirm diagnosis of TB!!
• Sensitive, specificity is low
27.
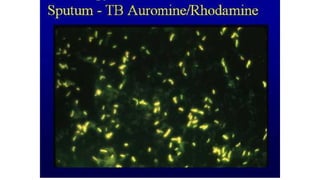
SPUTUM SMEAR
• Rapid, results within hours
• Inexpensive
• Simple, relatively easy to perform
• Reliable(40-64% sensitive, 90%
specificity)
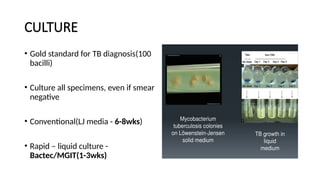
CULTURE
• Gold standardfor TB diagnosis(100
bacilli)
• Culture all specimens, even if smear
negative
• Conventional(LJ media - 6-8wks)
• Rapid – liquid culture -
Bactec/MGIT(1-3wks)
31.
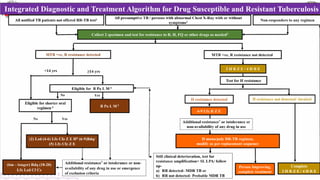
DRUG RESISTANCE
• Conventional/Rapidculture & DST
• GOLD standard
• CBNAAT - Gene Xpert – R resistance
• TruNAAT
• LPA(line probe assay) – first and
second line drugs
32.
Treatment
• 93% ofTB patients are sensitive
to first line anti-TB drugs
• Regimen includes 2 months of
HRZE and 4 months of HRE
• H-Isoniazid
• R-Rifampicin
• Z-Pyrazinamide
• E-Ethambutol
"Shorter is Safer"
•Drug-Resistant TB (DR-TB): The BPaLM regimen (Bedaquiline,
Pretomanid, Linezolid, and Moxifloxacin) is now the standard,
reducing treatment from 18 months to just 6 months.
• Drug-Susceptible TB (DS-TB): Shorter 4-month regimens (e.g.,
2HPMZ/2HPM) are now recommended for eligible adults and
adolescents to improve adherence and quality of life.
36.
TB Preventive Treatment(TPT)
• We cannot end TB without treating Latent TB Infection (LTBI).
• Proactively screen and start TB Preventive Treatment (TPT) for all
household contacts and high-risk groups (PLHIV, diabetics).
• Use shorter regimens like 1HP (one month daily) or 3HP (three
months weekly) to ensure completion.
37.
Holistic care
• TBis a social disease; treating the bacteria is only half the battle.
• Address the "Four Pillars of Success":
• Nutrition: Ensure patients access support programs (e.g., Nikshay Poshan
Yojana).
• Stigma: Provide respectful, person-centered care to encourage retention.
• Comorbidities: Systematically screen for Diabetes and HIV, as they
significantly drive TB mortality.
• Mental Health: Support the psychological burden of long-term therapy.
38.
• In 2026,curing TB is no longer a biological mystery—it is a test of our
implementation and leadership. We have the tools; now we must
have the will.
• Yes! We Can End TB.
•Thank you