Detailed exploration of acute promyelocytic leukemia with differentiation syndrome and Burkitt’s lymphoma with tumor lysis syndrome, including pathophysiology, diagnosis, clinical features, and management strategies.
When hematologic cancerbecomes an emergency
1. APL-Differentiation syndrome
2. Burkitt’s Lymphoma with Tumor-Lysis Syndrome
Dr. Manoj Khadka
2nd-year resident
Internal Medicine
2.
Table of Content
•Case scenario
• Introduction
• Pathophysiology
• Clinical features
• Diagnosis
• Management
3.
Case scenario 1
•53 yrs/M, no known comorbidities, came to ER (2083-3-28)
- Fever for 10 days (Tmax-101 F, a/w chills & rigor)
- Dry cough for 10 days
- Gum bleed 10 days back
• Labs:
• Hb-7, MCV-98, Plt- 10k, WBC-7.42k
(N3% L16% Blast 70% Metamyelocyte 2% Myelocyte 8%)
• CRP-45, ESR-85
• MP, K39, Scrub, Dengue, Leptospira, Brucella: Negative
• Blood & Urine C/S: Negative
• PT/INR: 13.4/1.36 secs, APTT-26.8 secs
• LFT/RFT-WNL (Cr-1.1mg/dL)
4.
Case 1…
• PBS:
•RBC- sparse distribution, normocytic normochromic
• WBC- shift to left with 65% blasts (Blast 65% N6% L16%
Myelocyte 10% metamyelocyte 2%)
• Platelet: 18k on manual count
• Atypical cells: Blast cells
• Bone Marrow Aspiration & Biopsy
- Hypercellular marrow (95%)
- Blast 60%, myelocyte 9%, metamyelocyte 5%, Band 3%, N2%
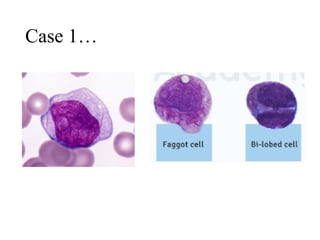
- Some cells show Auer rods & faggot cells, with some bilobed nuclei
Acute Promyelocytic Leukemia(APL)
• Accounts for 5-20% of adult AML cases
• Estimated annual incidence:1-7.4 cases/1,000,000 person-yrs
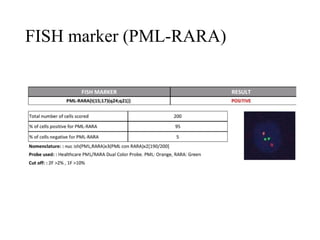
• t(15;17) translocation
• Found in more than 95% of APL cases
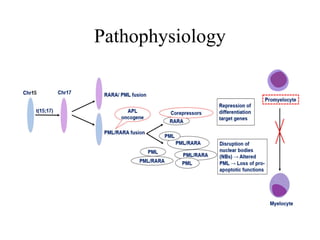
• Between promyelocytic leukemia (PML) gene on chromosome 15
& retinoic acid receptor α (RARA) gene on chromosome 17.
• Formation of the PML:RARA fusion protein, interfere multiple
cellular pathways (increased proliferation of myeloid progenitors &
differentiation block at promyelocytic stage)
• APL is a distinct clinical entity characterized by a marked
tendency towards coagulopathy, hemorrhage & early death
Differentiation syndrome (DS)
•Initially termed all-trans retinoic acid (ATRA) syndrome or retinoic
acid syndrome
• Originally described in APL patients receiving therapy with ATRA
or arsenic trioxide (ATO)
• Occurs in setting of neutrophil recovery, with characteristic findings
of leukocytosis, culture-negative fevers, hypotension, dyspnea, pleural
& pericardial effusions, weight gain, edema & AKI
• Typically occurs 1 - 2 weeks into ATRA &/or ATO therapy, with
incidence from 3 - 37%.
• Immediate treatment with steroids has reduced APL DS-associated
mortality to about 1%
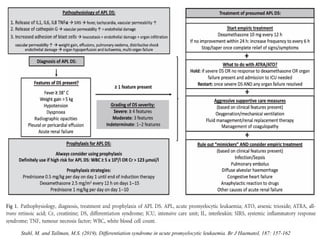
Stahl, M. andTallman, M.S. (2019), Differentiation syndrome in acute promyelocytic leukaemia. Br J Haematol, 187: 157-162
25.
Case scenario 2
•20 yrs/M, presents with
• Rapidly progressive swelling of left side of the jaw for 3 weeks
• Low-grade intermittent fever for 1 week
• Unintentional weight loss
• Local Examination of Jaw
• Diffuse swelling involving the left mandible (~7 × 6 cm), firm, non-
tender to mildly tender.
• Gingiva over the involved area is swollen and erythematous.
• Displacement and mobility of adjacent teeth.
• Lymph Node exam
• Small, firm, non-tender left submandibular and upper cervical
lymph nodes palpable.
26.
Case 2…
Tissue biopsy(mandibular mass)
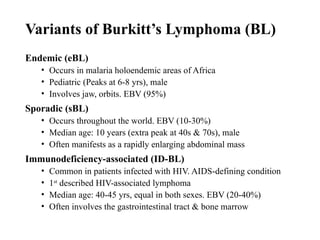
• Diffuse proliferation of medium-sized atypical lymphoid cells with
numerous mitotic figures and apoptotic cells, producing a characteristic
starry-sky appearance.
27.
Case 2…
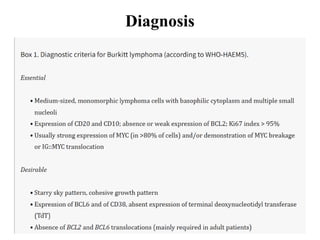
Immunohistochemistry:
• CD20:positive
• CD10: positive
• BCL6: positive
• Ki-67: approximately 95–100%
• BCL2: negative/weak
• TdT: negative
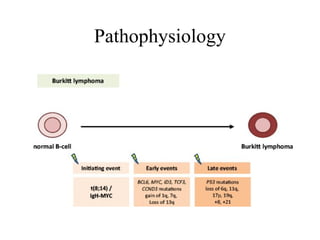
Molecular testing demonstrates a MYC rearrangement.
28.
Burkitt’s Lymphoma
• Anaggressive mature B-cell lymphoma
• 1958: 1st
described by Irish surgeon Denis Burkitt among 38 children in
Uganda with rapidly enlarging jaw sarcoma
• 1964: 1st
human neoplasm to be associated with a virus (EBV, named
after virologist M. Anthony Epstein & Yvonne M. Barr)
• 1972: 1st
human neoplasm shown to harbor a recurrent chromosomal
aberration, t(8;14)
29.
Variants of Burkitt’sLymphoma (BL)
Endemic (eBL)
• Occurs in malaria holoendemic areas of Africa
• Pediatric (Peaks at 6-8 yrs), male
• Involves jaw, orbits. EBV (95%)
Sporadic (sBL)
• Occurs throughout the world. EBV (10-30%)
• Median age: 10 years (extra peak at 40s & 70s), male
• Often manifests as a rapidly enlarging abdominal mass
Immunodeficiency-associated (ID-BL)
• Common in patients infected with HIV. AIDS-defining condition
• 1st
described HIV-associated lymphoma
• Median age: 40-45 yrs, equal in both sexes. EBV (20-40%)
• Often involves the gastrointestinal tract & bone marrow
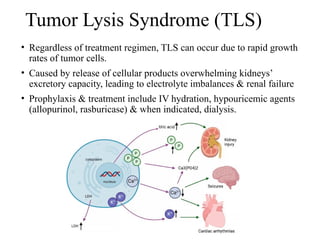
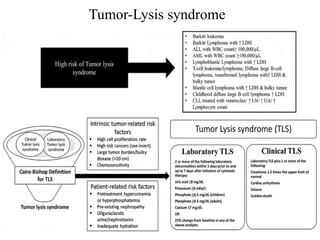
Tumor Lysis Syndrome(TLS)
• Regardless of treatment regimen, TLS can occur due to rapid growth
rates of tumor cells.
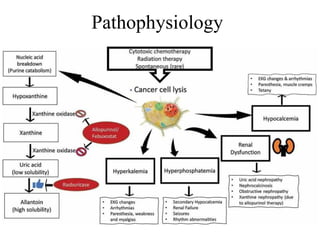
• Caused by release of cellular products overwhelming kidneys’
excretory capacity, leading to electrolyte imbalances & renal failure
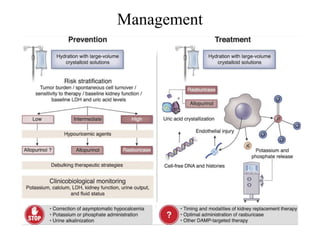
• Prophylaxis & treatment include IV hydration, hypouricemic agents
(allopurinol, rasburicase) & when indicated, dialysis.
References
• Abddaoui M,Aghlallou Y, Tlemçani I, Amrani Hassani M. Acute Promyelocytic Leukemia:
Pathophysiology, Diagnosis and Clinical Management. Hematol Rep. 2025 Nov 28;17(6):66.
• Ryan MM. Acute Promyelocytic Leukemia: A Summary. J Adv Pract Oncol. 2018 Mar;9(2):178-187.
• Iyer SG, Elias L, Stanchina M, Watts J. The treatment of acute promyelocytic leukemia in 2023:
Paradigm, advances, and future directions. Front Oncol. 2023 Jan 18;12:1062524.
• Issa GC, Stein EM, DiNardo CD. How I treat acute myeloid leukemia with differentiation therapy.
Blood. 2025 Mar 20;145(12):1251-1259.
• Stahl M, Tallman MS. Differentiation syndrome in acute promyelocytic leukaemia. Br J Haematol.
2019 Oct;187(2):157-162.
• Anagnostopoulos I, Zamo A, Horn H, Staiger A, Ott G. Burkitt Lymphoma-A Guide to Biological
Features, Diagnosis and Differential Diagnosis. Cancers (Basel). 2026 Feb 10;18(4):579
• Naing PT, Kaur A, Lynch DT. Burkitt Lymphoma. 2025 Feb 17. In: StatPearls. Treasure Island (FL):
StatPearls Publishing; 2026 Jan.
• Bodor C, Reiniger L. Catalog of genetic progression of human cancers: non-Hodgkin
lymphoma. Cancer Metastasis Rev. 2016 Mar;35(1):109-27.
• Puri I, Sharma D, Gunturu KS, Ahmed AA. Diagnosis and management of tumor lysis
syndrome. J Community Hosp Intern Med Perspect. 2020 Jun 14;10(3):269-272.
• Joseph A, Zafrani L. How I Treat Tumor Lysis Syndrome. Clin J Am Soc Nephrol. 2023 Dec
1;18(12):1634-1636.
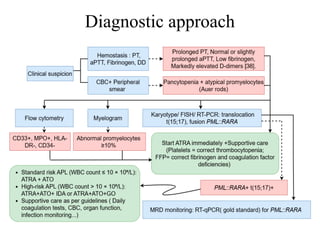
#4 Abnormal promyelocytes usually account for ≥10% of marrow cells, often displaying eccentric and bilobed nuclei, folded contours, and prominent nucleoli
Auer rods, which may be seen in bundles, forming the so-called faggot cells, a hallmark of the hypergranular variant of APL
#5 Initially, Patient was admitted on 2083/03/28 with the provisional diagnosis of fever under evaluation with bicytopenia.
Diagnosis: Acute promyleocytic myeloid lukemia (APML) with differentiation syndrome/ATRA syndrome.
patient was transferred from hematology ward with the above diagnosis for increase SOB and on respiratory distress not maintaining on 15lt reservior mask, Likely due to pulmonary edema as part of differentiation syndrome following ATO for APML. so patient was shifted to MICU for CPAP and possible need for intubation.
Patient was tranfused 2 pint of PRP and 3 pint of FFP in hematology ward on 2083/04/11 before transferring to MICU.
Vitals at MICU presentation:
BP: 160/80 mmHg
PR: 160
RR: 52
SPO2: 92%
Management on MICU:
- Patient was kept in NIV/CPAP where patient maintained the saturation.
- During ICU at first, patient develop PSVT, during arrival which was reverted to sinus rhythm after carotid sinus massage.
later again the HR was spiked and for PSVT 6 mg OF ADENOSINE was given following which there was decrease in HR and normal rhythm.
- Patient was agitated so Dexmed was started at 6ml/hr rate.
- patient was given medication as per the hematology consult and cardex.
case was seen by medicine oncall residents.
planned for single donor platelets.
After sometimes, the patient remained in severe respiratory distress with persistent tachypnea (RR 55-56/min) and developed marked tachycardia (HR 180-210/min). ECG was suggestive of paroxysmal supraventricular tachycardia (PSVT), for which three sequential doses of IV adenosine were administered without sustained response, and the tachycardia recurred within minutes. A trial of non-invasive ventilation (NIV) was attempted but was not tolerated because of worsening respiratory distress and declining sensorium.
In view of progressive drowsiness and impending respiratory failure, the patient underwent endotracheal intubation. Following the initial intubation, the patient developed severe hypoxemia (SpO2 60-65%), necessitating bag-mask ventilation and subsequent re-intubation. Oxygenation improved significantly after successful re-intubation and confirmation of airway placement. During the peri-intubation period, the patient developed profound bradycardia (HR 37/min), which responded to immediate administration of IV atropine and adrenaline, along with supportive medication with successful hemodynamic recovery.
The patient was subsequently stabilized on mechanical ventilation (AC/VC mode). Persistent PSVT eventually terminated following IV verapamil 5 mg stat, after which the heart rate normalized.
Patient was tranfused single donor platelets 1 pint ober 30 mins
and FFP 2 pint each pint over 30 mins.
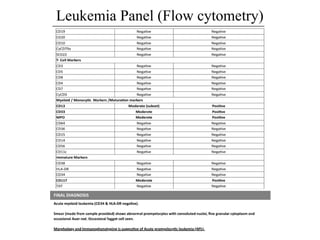
#6 CD38 (in conjunction with CD34 positivity) is used as a marker for bone marrow hematopoietic stem cells. CD38 (in conjunction with CD34 positivity) is used as a marker for bone marrow hematopoietic stem cells.
.HLA-DR is a key marker used to classify leukemias, being typically positive in B-cell and T-cell acute lymphoblastic leukemias (ALL) and most types of acute myeloid leukemia (AML), but characteristically negative in typical acute promyelocytic leukemia (APL).
CD13 and CD33 are myeloid-associated surface antigens typically positive in Acute Myeloid Leukemia (AML) and related myeloid disorders
CD117 (also known as c-kit) is a protein marker most notably positive in gastrointestinal stromal tumors (GISTs), mast cell disorders, acute
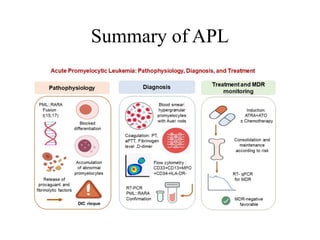
#10 Schematic representation of chromosomal translocation t(15;17) that occurs at APL: The chromosomal translocation t(15;17) generates the PML/RARA fusion protein, which disrupts regulation of differentiation target genes and alters PML nuclear bodies, leading to a block in promyelocyte maturation
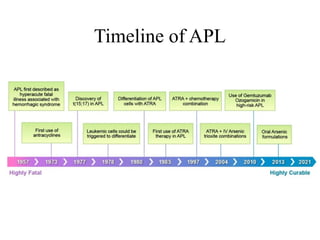
#12 Although APL is associated with high cure rates, relapse can still occur in a fraction of adult patients after achieving complete remission (CR)
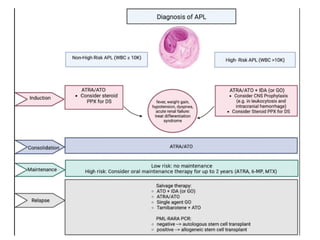
#13 Immediate ATRA treatment which targets the Retinoic acid (RA) receptor and induces terminal differentiation of APL blasts, is critical as it is known to rapidly reduce the biologic drivers of APL-associated coagulopathy.
ATO has emerged as one of the most active agents in APL treatment regimens. The mechanism of its action is based on the direct degradation of PML-RARα fusion transcripts. This leads to the transcription of RARα target genes which in turn causes the apparent differentiation and growth arrest of leukemia-initiating cells, either by apoptosis or by the loss of self-renewal ability
In low- or intermediate-risk patients, ATRA combined with ATO without chemotherapy is now established as the standard of care, providing highly effective outcomes. This regimen eradicates leukemic promyelocytes through synergistic induction of differentiation and apoptosis, leading to morphological and molecular remission while avoiding the cardiac and hematologic toxicities associated with anthracyclines
Supportive transfusion therapy. recommended transfusion thresholds are to maintain fibrinogen concentrations above 100–150 mg/dL and platelet counts above 30,000–50,000/µL
Following induction therapy, consolidation represents a pivotal step to eradicate residual leukemic clones and ensure sustained remission.
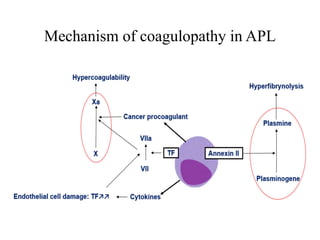
#17 APL is both a diagnostic and therapeutic emergency, as patients consistently present with a clinical picture that includes coagulopathy leading to a significant risk of bleeding
The onset of APL is usually associated with a severe thrombohemorrhagic diathesis, mainly driven by disseminated intravascular coagulation (DIC), which remains the leading cause of early mortality. A systematic screening panel, that includes prothrombin time (PT), activated partial thromboplastin time (aPTT), D-dimers, and fibrinogen levels should be promptly implemented to aid in early diagnosis and guide the immediate initiation of supportive care aimed at preventing hemorrhagic complications
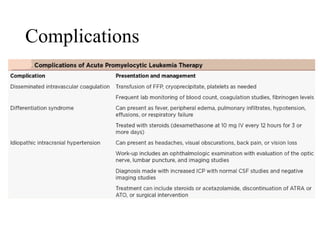
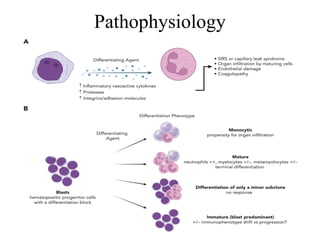
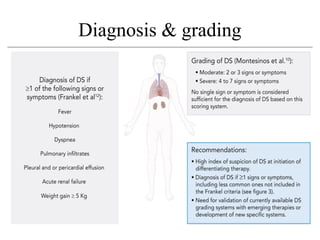
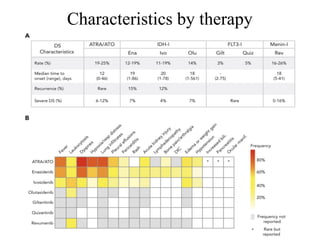
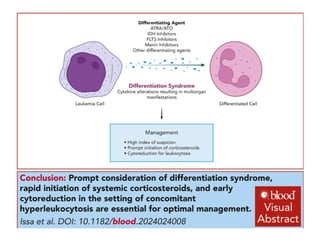
#19 The terminal differentiation of leukemic blasts via differentiating-agent therapy can lead to a constellation of signs and symptoms, originally referred to as “retinoic acid syndrome” and now termed “differentiation syndrome” (DS), characterized predominantly by systemic inflammatory response system–like features of dyspnea, pulmonary infiltrates, pleural and pericardial effusions, unexplained fevers, hypotension, edema, and renal insufficiency
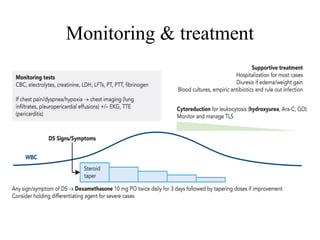
#20 We recommend strict daily assessments of the patient’s weight during APL induction therapy and consider an increase of >5 kg from the baseline weight a red flag for developing APL DS
#21 All-trans retinoic acid and arsenic trioxide are classic examples of differentiating agents for treatment of acute promyelocytic leukemia (APL); newer therapies functioning through differentiation include isocitrate dehydrogenase 1 and 2 inhibitors, FMS-like tyrosine kinase 3 inhibitors, and menin inhibitors
#22 Leukocytosis is common with DS (>50%) & corticosteroids can further elevate the WBC count. Concurrent cytoreductive management with hydroxyurea, GO, and/or cytarabine recommended whenever the WBC count is >25 × 109/L (or >10 × 109/L for APL), to minimize additional complications of leukostasis including DIC.
#26 starry sky” pattern is usually present, resulting from the interspersed tingible body macrophages.
#27 TdT Means in Lymphoma
Marks Immature Cells: TdT is normally found in young B-cells and T-cells.
Identifies Lymphoblastic Lymphoma: About 90% to 95% of lymphoblastic lymphomas test positive for TdT.
#28 Non-Hodgkin's Lymphoma (NHL) and has the fastest doubling time among human tumors
Plaster busts of young children with Burkitt’s lymphoma (WTI/DPB/B/7/4b ‘Album, maps and diagrams relating to cancers in Africa,’ Denis Parsons Burkitt Collection, Wellcome Archive, London, UK).
he noted the unique combination of jaw and orbital involvement and a predilection for extranodal spread to the adrenal glands, kidneys, liver, thyroid, pancreas, stomach and ovaries [1]. Shortly thereafter observations by O’Connor and Davies found that the histologic appearance of the facial tumors was identical to that of lymphomas characterized by abdominal masses, and a lymphoid origin was confirmed
in 1964, Epstein and colleagues were able to identify by electron microscopy, in a small fraction of cells in one of these cell lines, the presence of intracellular particles that had the characteristic morphological features of a virus
#29 postulated that jaw involvement is related to poor dentition, thus allowing EBV to gain access to jaw marrow cells, and that the change in the clinical presentation is likely related to improved dentition.
BL risk is decreased in children carrying genetic variants that protect against malaria, such as the sickle cell trait
#30 CD10 Marker: Also called CALLA (Common Acute Lymphoblastic Leukemia Antigen). One of first markers to identify leukemic cells in children
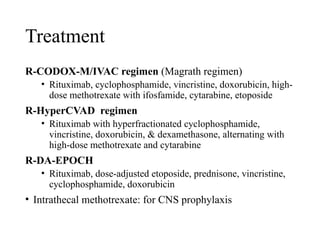
#32 intensive short-duration approach is generally preferred due to its quicker administration and clinical familiarity, whereas dose-adjusted EPOCH-R is an alternative for older or less fit patients
#36 When the calcium phosphate product (calcium concentration × phosphate concentration) exceeds 60 mg2/dL2, there is an increased risk of nephrocalcinosis.
Both of these xanthine oxidase inhibitors are ineffective in dissolving already-formed urate crystals and should be started 48–72 hours before chemotherapy to be effective
Rasburicase is a recombinant urate oxidase that converts uric acid into soluble allantoin. Avoid in G-6-PD defeciency
#37 Allopurinol is the agent of choice in intermediate-risk patients. The usual dose of allopurinol is 100 mg/m2 every 8 h (maximum 800 mg per day) in adults
dose of rasburicase is 0.2 mg/kg once daily for 5–7 days
Monitor electrolytes 4-6 hrly
Since the risk of calcium phosphate deposition is high, only patients with symptomatic hypocalcemia require treatment with IV calcium gluconate (Cairo & Bishop, 2004).