medicoseacademics@gmail.com
0310-7990649
Vestibular System &
Equilibrium
Dr Faiza
MBBS (Best Graduate, AIMC Lahore)
FCPS Physiology,
MHPE (Riphah Int University, Islamabad)
ICMT, CHPE, DHPE (STMU)
MPH (GC University, Faisalabad)
MBA (Virtual University of Pakistan)
medicoseacademics@gmail.com
0310-7990649
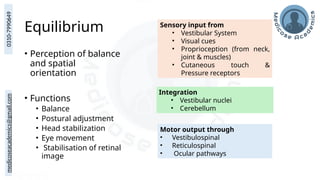
Equilibrium
• Perception of balance
and spatial
orientation
• Functions
• Balance
• Postural adjustment
• Head stabilization
• Eye movement
• Stabilisation of retinal
image
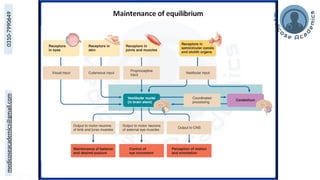
Sensory input from
• Vestibular System
• Visual cues
• Proprioception (from neck,
joint & muscles)
• Cutaneous touch &
Pressure receptors
Integration
• Vestibular nuclei
• Cerebellum
Motor output through
• Vestibulospinal
• Reticulospinal
• Ocular pathways
medicoseacademics@gmail.com
0310-7990649
medicoseacademics@gmail.com
0310-7990649
Vestibular System
• Vestibular system:
• Vestibular apparatus
• Central vestibular nuclei
• Functions
• Maintenance of balance and equilibrium
• Head motion
• Head position
• Head-on-neck adjustments
• Head-on-body adjustments
medicoseacademics@gmail.com
0310-7990649
medicoseacademics@gmail.com
0310-7990649
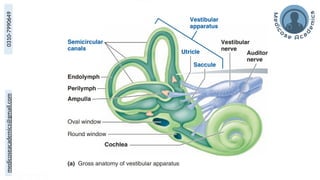
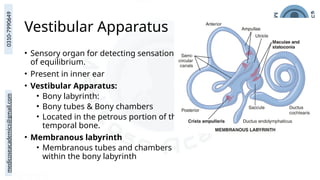
Vestibular Apparatus
• Sensory organ for detecting sensations
of equilibrium.
• Present in inner ear
• Vestibular Apparatus:
• Bony labyrinth:
• Bony tubes & Bony chambers
• Located in the petrous portion of the
temporal bone.
• Membranous labyrinth
• Membranous tubes and chambers
within the bony labyrinth
medicoseacademics@gmail.com
0310-7990649
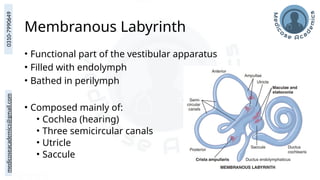
Membranous Labyrinth
• Functional part of the vestibular apparatus
• Filled with endolymph
• Bathed in perilymph
• Composed mainly of:
• Cochlea (hearing)
• Three semicircular canals
• Utricle
• Saccule
medicoseacademics@gmail.com
0310-7990649
Functions of Vestibular Apparatus
• Utricle and saccule
• Detect head position relative to gravity
• Detect linear acceleration
• Help in static equilibrium
• Semicircular canals
• Detect angular acceleration
• Detect beginning and stopping of rotation
• Help in dynamic equilibrium
medicoseacademics@gmail.com
0310-7990649
Otolith Organs
Utricle & Saccule
medicoseacademics@gmail.com
0310-7990649
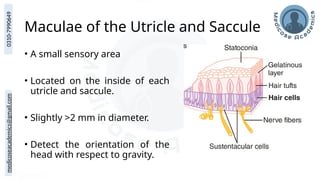
Maculae of the Utricle and Saccule
• A small sensory area
• Located on the inside of each
utricle and saccule.
• Slightly >2 mm in diameter.
• Detect the orientation of the
head with respect to gravity.
medicoseacademics@gmail.com
0310-7990649
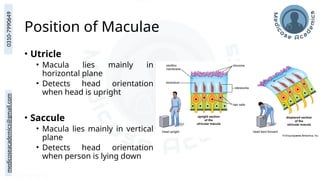
Position of Maculae
• Utricle
• Macula lies mainly in
horizontal plane
• Detects head orientation
when head is upright
• Saccule
• Macula lies mainly in vertical
plane
• Detects head orientation
when person is lying down
medicoseacademics@gmail.com
0310-7990649
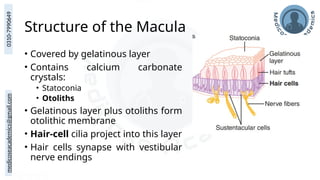
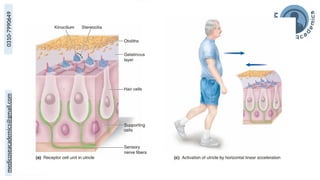
Structure of the Macula
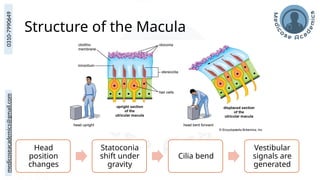
• Covered by gelatinous layer
• Contains calcium carbonate
crystals:
• Statoconia
• Otoliths
• Gelatinous layer plus otoliths form
otolithic membrane
• Hair-cell cilia project into this layer
• Hair cells synapse with vestibular
nerve endings
medicoseacademics@gmail.com
0310-7990649
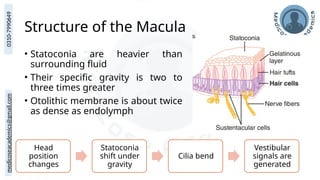
Structure of the Macula
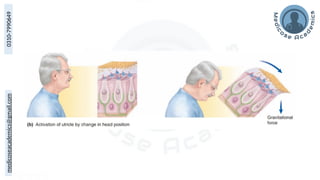
• Statoconia are heavier than
surrounding fluid
• Their specific gravity is two to
three times greater
• Otolithic membrane is about twice
as dense as endolymph
Head
position
changes
Statoconia
shift under
gravity
Cilia bend
Vestibular
signals are
generated
medicoseacademics@gmail.com
0310-7990649
Structure of the Macula
Head
position
changes
Statoconia
shift under
gravity
Cilia bend
Vestibular
signals are
generated
medicoseacademics@gmail.com
0310-7990649
Directional Sensitivity of Hair Cells
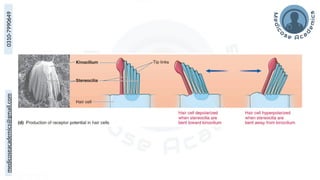
• Kinocilium and Stereocilia
• Each hair cell has:
• About 100 small cilia called stereocilia
• One large cilium called the kinocilium
• Kinocilium is located on one side of the hair cell.
• Stereocilia become progressively shorter away from
koinocilium
• Filamentous attachments between sterocilia
medicoseacademics@gmail.com
0310-7990649
medicoseacademics@gmail.com
0310-7990649
Directional Sensitivity of Hair Cells
Stereocilia bend
toward the
kinocilium
Filamentous
attachments pull
on the
stereocilia in
sequence
Stereocilia are
pulled outward
from the cell
body
Several hundred
cation channels
open
Influx of Cations
from the
surrounding
endolymphatic
fluid
Receptor
membrane
depolarization
occurs
Increased
impulse
transmission
medicoseacademics@gmail.com
0310-7990649
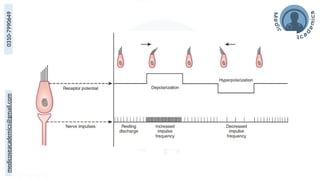
Directional Sensitivity of Hair Cells
Stereocilia bend
away from
kinocilium
Tension on
Filamentous
attachments
decrease
Closure of Ion
channels
Receptor
Hyperpolarizati
on
 Vestibular hair cells release excitatory neurotransmitter continuously (Glutamate or Aspartate)
 Resting discharge is about 100 impulses per second
medicoseacademics@gmail.com
0310-7990649
Pattern Coding in Maculae
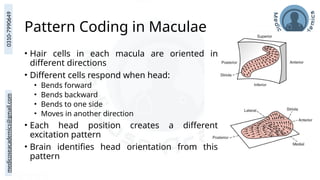
• Hair cells in each macula are oriented in
different directions
• Different cells respond when head:
• Bends forward
• Bends backward
• Bends to one side
• Moves in another direction
• Each head position creates a different
excitation pattern
• Brain identifies head orientation from this
pattern
medicoseacademics@gmail.com
0310-7990649
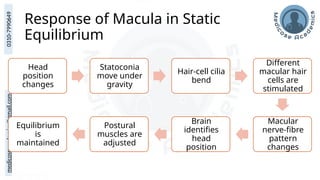
Response of Macula in Static
Equilibrium
Head
position
changes
Statoconia
move under
gravity
Hair-cell cilia
bend
Different
macular hair
cells are
stimulated
Macular
nerve-fibre
pattern
changes
Brain
identifies
head
position
Postural
muscles are
adjusted
Equilibrium
is
maintained
medicoseacademics@gmail.com
0310-7990649
medicoseacademics@gmail.com
0310-7990649
medicoseacademics@gmail.com
0310-7990649
Linear Acceleration
• Utricle mainly responds to horizontal acceleration
• Saccule mainly responds to vertical acceleration
• Otoliths move opposite to direction of acceleration
• Hair-cell processes are distorted
• Vestibular nerve activity changes
medicoseacademics@gmail.com
0310-7990649
Linear Acceleration
Body suddenly moves forward
Statoconia fall backward on cilia
Disequilibrium signal goes to
nervous centres
Person feels falling backward
Person leans forward
Equilibrium is restored
 Maculae detect linear acceleration
 They do not detect linear velocity
 Runner leans forward at start due to
acceleration
 After reaching steady speed,
forward lean is not needed in
vacuum
 In air, forward lean occurs due to air
resistance acting on skin pressure
receptors
medicoseacademics@gmail.com
0310-7990649
medicoseacademics@gmail.com
0310-7990649
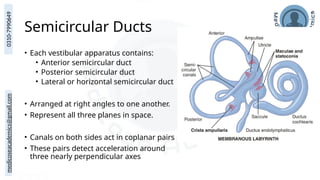
Semicircular Ducts
• Each vestibular apparatus contains:
• Anterior semicircular duct
• Posterior semicircular duct
• Lateral or horizontal semicircular duct
• Arranged at right angles to one another.
• Represent all three planes in space.
• Canals on both sides act in coplanar pairs
• These pairs detect acceleration around
three nearly perpendicular axes
medicoseacademics@gmail.com
0310-7990649
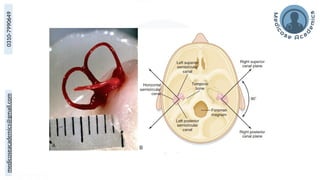
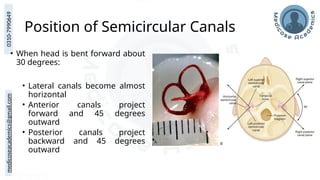
Position of Semicircular Canals
• When head is bent forward about
30 degrees:
• Lateral canals become almost
horizontal
• Anterior canals project
forward and 45 degrees
outward
• Posterior canals project
backward and 45 degrees
outward
medicoseacademics@gmail.com
0310-7990649
Semicircular Canals
• Rotation produces maximum stimulation of the semicircular
canals lying nearest to the plane of rotation.
• The semicircular canals on one side are mirror images of
those on the opposite side.
• The pattern of stimulation reaching the brain varies with:
• Direction of rotation
• Plane of rotation
medicoseacademics@gmail.com
0310-7990649
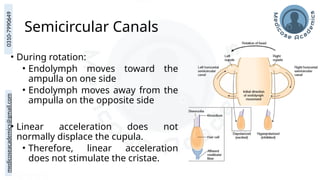
Semicircular Canals
• During rotation:
• Endolymph moves toward the
ampulla on one side
• Endolymph moves away from the
ampulla on the opposite side
• Linear acceleration does not
normally displace the cupula.
• Therefore, linear acceleration
does not stimulate the cristae.
medicoseacademics@gmail.com
0310-7990649
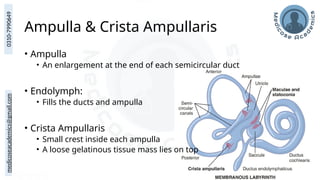
Ampulla & Crista Ampullaris
• Ampulla
• An enlargement at the end of each semicircular duct
• Endolymph:
• Fills the ducts and ampulla
• Crista Ampullaris
• Small crest inside each ampulla
• A loose gelatinous tissue mass lies on top
medicoseacademics@gmail.com
0310-7990649
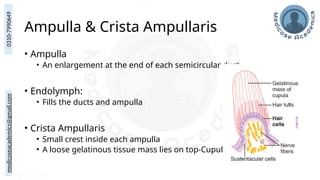
Ampulla & Crista Ampullaris
• Ampulla
• An enlargement at the end of each semicircular duct
• Endolymph:
• Fills the ducts and ampulla
• Crista Ampullaris
• Small crest inside each ampulla
• A loose gelatinous tissue mass lies on top-Cupula
medicoseacademics@gmail.com
0310-7990649
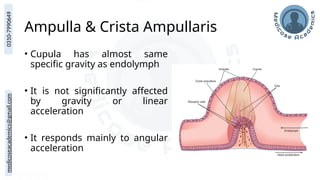
Ampulla & Crista Ampullaris
• Cupula has almost same
specific gravity as endolymph
• It is not significantly affected
by gravity or linear
acceleration
• It responds mainly to angular
acceleration
medicoseacademics@gmail.com
0310-7990649
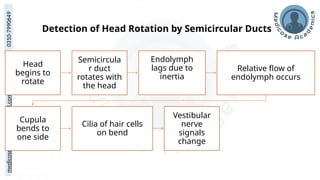
Head
begins to
rotate
Semicircula
r duct
rotates with
the head
Endolymph
lags due to
inertia
Relative flow of
endolymph occurs
Cupula
bends to
one side
Cilia of hair cells
on bend
Vestibular
nerve
signals
change
Detection of Head Rotation by Semicircular Ducts
medicoseacademics@gmail.com
0310-7990649
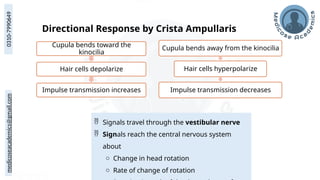
 Signals travel through the vestibular nerve
 Signals reach the central nervous system
about
o Change in head rotation
o Rate of change of rotation
Cupula bends toward the
kinocilia
Hair cells depolarize
Impulse transmission increases
Cupula bends away from the kinocilia
Hair cells hyperpolarize
Impulse transmission decreases
Directional Response by Crista Ampullaris
medicoseacademics@gmail.com
0310-7990649
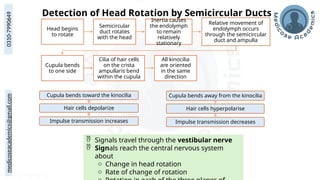
Head begins
to rotate
Semicircular
duct rotates
with the head
Inertia causes
the endolymph
to remain
relatively
stationary
Relative movement of
endolymph occurs
through the semicircular
duct and ampulla
Cupula bends
to one side
Cilia of hair cells
on the crista
ampullaris bend
within the cupula
All kinocilia
are oriented
in the same
direction
Detection of Head Rotation by Semicircular Ducts
Cupula bends toward the kinocilia
Hair cells depolarize
Impulse transmission increases
Cupula bends away from the kinocilia
Hair cells hyperpolarise
Impulse transmission decreases
 Signals travel through the vestibular nerve
 Signals reach the central nervous system
about
o Change in head rotation
o Rate of change of rotation
medicoseacademics@gmail.com
0310-7990649
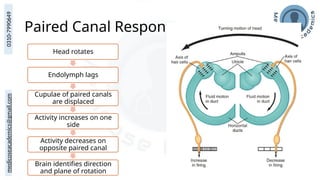
Paired Canal Response
Head rotates
Endolymph lags
Cupulae of paired canals
are displaced
Activity increases on one
side
Activity decreases on
opposite paired canal
Brain identifies direction
and plane of rotation
medicoseacademics@gmail.com
0310-7990649
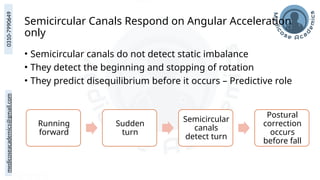
Semicircular Canals Respond on Angular Acceleration
only
• Semicircular canals do not detect static imbalance
• They detect the beginning and stopping of rotation
• They predict disequilibrium before it occurs – Predictive role
Running
forward
Sudden
turn
Semicircular
canals
detect turn
Postural
correction
occurs
before fall
medicoseacademics@gmail.com
0310-7990649
medicoseacademics@gmail.com
0310-7990649
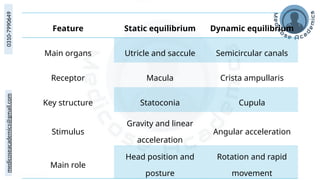
Feature Static equilibrium Dynamic equilibrium
Main organs Utricle and saccule Semicircular canals
Receptor Macula Crista ampullaris
Key structure Statoconia Cupula
Stimulus
Gravity and linear
acceleration
Angular acceleration
Main role
Head position and
posture
Rotation and rapid
movement
medicoseacademics@gmail.com
0310-7990649
Vestibular System &
Equilibrium
Dr Faiza
MBBS (Best Graduate, AIMC Lahore)
FCPS Physiology,
MHPE (Riphah Int University, Islamabad)
ICMT, CHPE, DHPE (STMU)
MPH (GC University, Faisalabad)
MBA (Virtual University of Pakistan)
medicoseacademics@gmail.com
0310-7990649
Maintenance of Equilibrium
medicoseacademics@gmail.com
0310-7990649
Cerebellum and Semicircular Duct
Signals
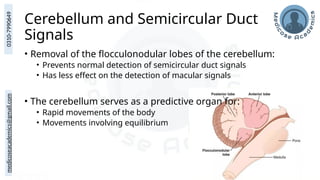
• Removal of the flocculonodular lobes of the cerebellum:
• Prevents normal detection of semicircular duct signals
• Has less effect on the detection of macular signals
• The cerebellum serves as a predictive organ for:
• Rapid movements of the body
• Movements involving equilibrium
medicoseacademics@gmail.com
0310-7990649
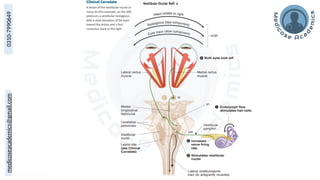
Vestibular Stabilization of Vision
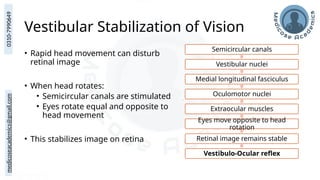
• Rapid head movement can disturb
retinal image
• When head rotates:
• Semicircular canals are stimulated
• Eyes rotate equal and opposite to
head movement
• This stabilizes image on retina
Semicircular canals
Vestibular nuclei
Medial longitudinal fasciculus
Oculomotor nuclei
Extraocular muscles
Eyes move opposite to head
rotation
Retinal image remains stable
Vestibulo-Ocular reflex
medicoseacademics@gmail.com
0310-7990649
Nystagmus
• Nystagmus is a characteristic jerky movement of the eyes.
• It occurs at:
• The beginning of rotation
• The end of rotation
• Maintains visual fixation on stationary points while the body
rotates.
medicoseacademics@gmail.com
0310-7990649
medicoseacademics@gmail.com
0310-7990649
Components of Nystagmus
• When rotation begins:
• The eyes move slowly opposite to the direction of rotation
• This slow movement maintains visual fixation
• Initiated by vestibular labyrinth
• When the limit of slow eye movement is reached:
• The eyes rapidly move back to a new fixation point
• Triggered by brainstem centre
• Slow movement then begins again
medicoseacademics@gmail.com
0310-7990649
Direction and Types of Nystagmus
• Nystagmus may be:
• Horizontal : when the eyes move in the horizontal plane.
• Vertical: when the head is tilted sideways during rotation.
• Rotatory: when the head is tilted forward
• The direction of nystagmus - according to the quick
component.
• During rotation, the quick component is in the same direction as
rotation.
• Post-rotatory nystagmus is in the opposite direction.
medicoseacademics@gmail.com
0310-7990649
07/22/2026 49
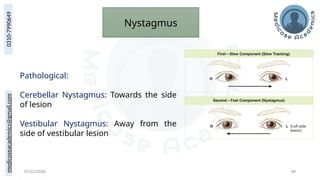
Nystagmus
Pathological:
Cerebellar Nystagmus: Towards the side
of lesion
Vestibular Nystagmus: Away from the
side of vestibular lesion
medicoseacademics@gmail.com
0310-7990649
Nystagmus at Rest
• Nystagmus occurring at rest indicates pathology.
• It may be:
• Congenital
• Acquired
• Acquired nystagmus may occur due to:
• Temporal bone fracture affecting the semicircular canals
• Damage to the flocculonodular lobe
• Damage to the fastigial nucleus
• Stroke
• Multiple sclerosis
• Head injury
• Brain tumours
• Antiseizure drugs
• Alcohol
• Sedatives
medicoseacademics@gmail.com
0310-7990649
Caloric Test
• Tests vestibular labyrinth function
• Warm or cold water is placed in external auditory meatus (COWS)
• Warm water: 40°C
• Cold water: 30°C
• Temperature difference creates endolymph currents
• Cupula moves
• Cold water Opposite side nystagmus
→
Warm water Same side nystagmus
→
• In unilateral lesion, response is reduced or absent on affected side
medicoseacademics@gmail.com
0310-7990649
Additional Inputs for Equilibrium
• Vestibular apparatus detects head movement and
orientation
• Other inputs are also needed:
• Neck proprioceptors
• Body proprioceptors
• Visual input
• Cutaneous touch receptors
• Pressure receptors in feet
• Exteroceptive input such as air pressure
medicoseacademics@gmail.com
0310-7990649
Neck Proprioceptors
• Vestibular apparatus detects movement of head only
• Nervous system also needs head position relative to body
• Neck proprioceptors provide this information
• Neck signals reach:
• Vestibular nuclei
• Reticular nuclei
• Cerebellum
medicoseacademics@gmail.com
0310-7990649
Head Tilt Versus Whole-Body Tilt
• Head tilts by neck bending
• Neck proprioceptors oppose vestibular signals
• False disequilibrium is prevented
• Whole body tilts
• Vestibular signals are not opposed
• Disequilibrium is perceived
medicoseacademics@gmail.com
0310-7990649
Proprioceptive and Exteroceptive
Inputs
• Footpad pressure tells:
• Weight distribution between feet
• Forward or backward shift of weight
• During running:
• Air pressure against front of body signals opposing force
• Person leans forward to oppose it
medicoseacademics@gmail.com
0310-7990649
Central Vestibular Pathway
Sensory input from
• Vestibular System
• Visual cues
• Proprioception (from neck,
joint & muscles)
• Cutaneous touch &
Pressure receptors
Integration
• Vestibular nuclei
Project to
• Oculomotor nuclei through medial
longitudinal fasciculus
• Spinal cord through vestibulospinal
tracts
• Cerebellum
• Reticular formation
• Opposite vestibular complex
• Thalamus
• Cerebral cortex
medicoseacademics@gmail.com
0310-7990649
Vestibular Output
• Eye movement output
• MLF Oculomotor nuclei Stable retinal image
→ →
• Postural output
• Vestibulospinal and reticulospinal tracts Trunk, neck and
→
antigravity muscles
• Conscious output
• Thalamus Cerebral cortex Awareness of movement and
→ →
orientation
medicoseacademics@gmail.com
0310-7990649
Vestibulospinal Pathways
• Lateral vestibulospinal tract
• Activates trunk and extensor muscles
• Supports posture
• Helps maintain equilibrium
• Medial vestibulospinal tract
• Activates neck muscles
• Produces head-on-neck adjustment
• Contributes to vestibulocollic reflex
medicoseacademics@gmail.com
0310-7990649
Cerebellum in Equilibrium
• Flocculonodular lobe:
• Concerned with dynamic equilibrium
• Works with semicircular canals
• Damage causes:
• Loss of dynamic equilibrium during rapid movements
• Static equilibrium is not seriously disturbed
• Uvula may play a role in static equilibrium
medicoseacademics@gmail.com
0310-7990649
Cortical Perception
• Vestibular signals ascend to thalamus and cerebral cortex
• Contribute to conscious awareness of:
• Head movement
• Body movement
• Body orientation
• Equilibrium status
medicoseacademics@gmail.com
0310-7990649
Postural Reflexes
• Activated when:
• Head moves
• Head tilts
• Neck bends
• Three types:
• Vestibular reflexes
• Tonic neck reflexes
• Righting reflexes
• Main receptors:
• Vestibular apparatus
• Neck stretch receptors
• Body-wall mechanoreceptors
medicoseacademics@gmail.com
0310-7990649
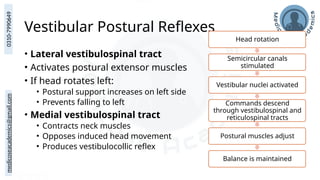
Vestibular Postural Reflexes
• Lateral vestibulospinal tract
• Activates postural extensor muscles
• If head rotates left:
• Postural support increases on left side
• Prevents falling to left
• Medial vestibulospinal tract
• Contracts neck muscles
• Opposes induced head movement
• Produces vestibulocollic reflex
Head rotation
Semicircular canals
stimulated
Vestibular nuclei activated
Commands descend
through vestibulospinal and
reticulospinal tracts
Postural muscles adjust
Balance is maintained
medicoseacademics@gmail.com
0310-7990649
Otolith-Mediated Postural Responses
• Head tilt changes linear acceleration on otolith hair cells
• Produces:
• Eye movements
• Postural adjustments
• Forward tilt of head and body
• Forelimbs extend
• Hind limbs flex
• Backward tilt of head and body
• Forelimbs flex
• Hind limbs extend
medicoseacademics@gmail.com
0310-7990649
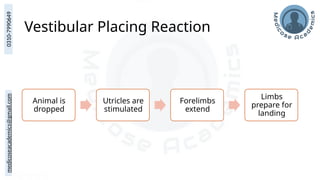
Vestibular Placing Reaction
Animal is
dropped
Utricles are
stimulated
Forelimbs
extend
Limbs
prepare for
landing
medicoseacademics@gmail.com
0310-7990649
Tonic Neck Reflexes
• Activated by muscle spindles in neck muscles
• Neck muscles have high concentration of muscle spindles
• Occur when neck bends without tilting head
• Neck extension
• Forelimbs extend
• Hind limbs flex
• Neck flexion
• Forelimbs flex
• Hind limbs extend
medicoseacademics@gmail.com
0310-7990649
Asymmetrical Tonic Neck Reflex
• Neck bends to left
• Extensor activity increases in left limbs
• Flexor activity decreases in right limbs
• Posture adjusts according to neck position
medicoseacademics@gmail.com
0310-7990649
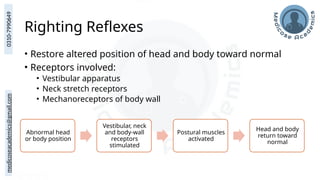
Righting Reflexes
• Restore altered position of head and body toward normal
• Receptors involved:
• Vestibular apparatus
• Neck stretch receptors
• Mechanoreceptors of body wall
Abnormal head
or body position
Vestibular, neck
and body-wall
receptors
stimulated
Postural muscles
activated
Head and body
return toward
normal
medicoseacademics@gmail.com
0310-7990649
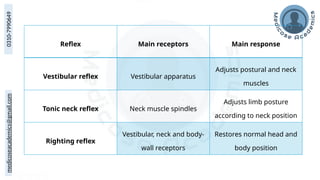
Reflex Main receptors Main response
Vestibular reflex Vestibular apparatus
Adjusts postural and neck
muscles
Tonic neck reflex Neck muscle spindles
Adjusts limb posture
according to neck position
Righting reflex
Vestibular, neck and body-
wall receptors
Restores normal head and
body position
medicoseacademics@gmail.com
0310-7990649
Spatial Orientation
• Depends on:
• Vestibular receptors
• Visual cues
• Joint proprioceptors
• Cutaneous touch and pressure receptors
• These inputs are combined at cortical level
• They form a continuous picture of body orientation in space
medicoseacademics@gmail.com
0310-7990649
Clinical Corelation
medicoseacademics@gmail.com
0310-7990649
Labyrinthine Lesions
• Loss of left labyrinthine function
• Person tends to fall to left
• Irritation/excess stimulation of left labyrinth
• Person tends to fall to right
medicoseacademics@gmail.com
0310-7990649
Vertigo
• Sensation of rotation without actual rotation
• Prominent when one labyrinth is inflamed
*Dizziness and lightheadedness do not always mean
vestibular disease
medicoseacademics@gmail.com
0310-7990649
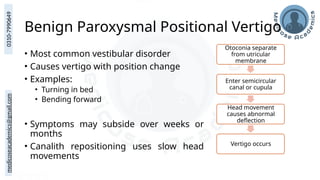
Benign Paroxysmal Positional Vertigo
• Most common vestibular disorder
• Causes vertigo with position change
• Examples:
• Turning in bed
• Bending forward
• Symptoms may subside over weeks or
months
• Canalith repositioning uses slow head
movements
Otoconia separate
from utricular
membrane
Enter semicircular
canal or cupula
Head movement
causes abnormal
deflection
Vertigo occurs
medicoseacademics@gmail.com
0310-7990649
Ménière Disease
• Inner-ear abnormality
• Features:
• Vertigo or severe dizziness
• Tinnitus
• Fluctuating hearing loss
• Pressure or pain in affected ear
• Symptoms may last several hours
• Hearing loss may become permanent
medicoseacademics@gmail.com
0310-7990649
Ménière Disease
• Often diagnosed between 30 and 60 years
• Affects both sexes similarly
• No cure
• Symptoms may be controlled by reducing fluid
retention
• Measures:
• Low-salt or salt-free diet
• No caffeine
• No alcohol
• Diuretics such as hydrochlorothiazide
• Meclizine may reduce vestibular excitability and
vestibular-cerebellar conduction
Immune reaction
Fluid volume increases
in membranous
labyrinth
Membranous labyrinth
ruptures
Endolymph and
perilymph mix
Vestibular and hearing
symptoms occur
medicoseacademics@gmail.com
0310-7990649
Motion Sickness
• Due to excessive vestibular stimulation
• Occurs when conflicting information reaches vestibular and other sensory
systems
• Symptoms:
• Nausea
• Vomiting
• Sweating
• Pallor
• Blood pressure changes
• Prevention:
• Antihistamines
• Scopolamine (anticholinergic)
medicoseacademics@gmail.com
0310-7990649
Space Motion Sickness
• Occurs during first exposure to microgravity
• Symptoms:
• Nausea
• Vomiting
• Vertigo
• May improve after a few days
• May recur during re-entry
• Due to mismatch between vestibular input, gravity sensors and
other spatial-orientation inputs
medicoseacademics@gmail.com
0310-7990649
Dr Faiza, FCPS Physiology
Thank You
References:
• Guyton, A. C., & Hall, J. E. (2021). Textbook of Medical Physiology (15th ed., Chapter 56: Cortical
& Brain stem control of motor function). Philadelphia, PA: Elsevier.
• Barrett, K. E., Barman, S. M., Brooks, H. L., & Yuan, J. X.-J. (2019). Ganong’s Review of Medical
Physiology (26th ed., Chapter 11: Hearing & Equilibrium). New York, NY: McGraw-Hill
Education.
• Sherwood, L. (2015). Human Physiology: From Cells to Systems (9th ed., Chapter 6: Peripheral
Nervous system: Afferent Division; Special senses). Boston, MA: Cengage Learning.