Treatment of
dyslipidemia
Asma mutni ID 33121670
Objectives :
1)list non-pharmacological measures for treatment
of dyslipidemia .
Classify drugs used in treatment of dyslipidemia .2)
3) Mention the MOA , most common side effect and
the effect on lipid profile of each class .
4) outline preventive measure of dyslipidemia .
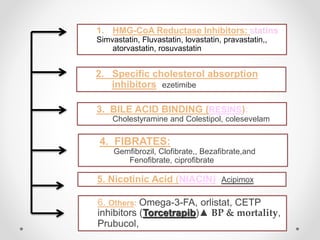
1. HMG-CoA Reductase Inhibitors: statins
Simvastatin, Fluvastatin, lovastatin, pravastatin,,
atorvastatin, rosuvastatin
2. Specific cholesterol absorption
inhibitors: ezetimibe
3. BILE ACID BINDING (RESINS):
Cholestyramine and Colestipol, colesevelam
4. FIBRATES:
Gemfibrozil, Clofibrate,, Bezafibrate,and
Fenofibrate, ciprofibrate
5. Nicotinic Acid (NIACIN), Acipimox
6. Others: Omega-3-FA, orlistat, CETP
inhibitors (Torcetrapib)▲ BP & mortality,
Prubucol,
HMG-CoA Reductase Inhibitors: statins
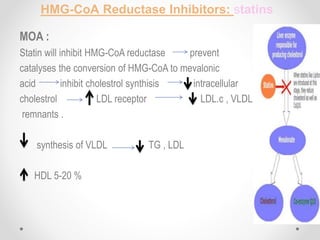
MOA :
Statin will inhibit HMG-CoA reductase prevent
catalyses the conversion of HMG-CoA to mevalonic
acid inhibit cholestrol synthisis intracellular
cholestrol LDL receptor LDL.c , VLDL
remnants .
synthesis of VLDL TG , LDL
HDL 5-20 %
Cont.
atorvastatin, rosuvastatin long acting inhibitor .
Simvastatin, Fluvastatin, lovastatin, pravastatin short acting inhibitor giving
by mouth at night ? To reduce peak cholesterol synthesis in the early morning .
absorption with food .
They are well absorbed and excreted by liver ,their site of action, and are
subject to extensive presystemic metabolism via cytochrome p450 and
glucoronidation pathway .
Excretion : 80% metabolized and excreted in bile
and 20% excreted unchanged drug in urine
Importance ?? Frequent checkup liver and kidney function
Clinical uses of HMG-CoA reductase inhibitors (statins)
1) Secondary prevention of CHD (e.g. angina,
following myocardial infarction or stroke).
2) Primary prevention of arterial disease in patients
who are at high risk of atherosclerosis.
3) Atorvastatin lowers serum cholesterol in patients
with homozygous familial hypercholesterolaemia.
4) In severe drug-resistant dyslipidaemia (e.g.
heterozygous familial hypercholesterolaemia),
ezetimibe is combined with statin treatment.
5) 2ry hyperlipidemia e.g DM , nephrotic syndrome
6) # in pregnancy .
cont..
side effect :
most common :
muscle pain (myalgia )1)
2) GIT disturbance
3) raised concentration of liver enzyme in plasma
4) insomnia
5) rash
rarly :
1)myositis ( common in lean body mass and
uncorrected hypothyroidism pt .
2) angio-oedema
Specific Cholesterol Absorption
Inhibitors(Ezetimibe= zetia)
MOA :
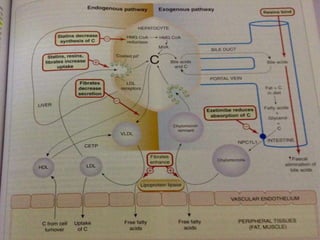
inhibit absorption of cholesterol from duodenum by blocking transport
protein (NPC1L1) in the brush border of enterocyte without affecting
the absorption of fat soluble vitamins , TG or bile acid .
Adverse effect :
1. GIT: Diarrhea, abdominal pain, hepatitis if combined with
statins, rarely myositis alone or with statins
2. CNS: Headache, fatigue, dizziness
3. Skin: Allergic reactions (rare)
Therapeutic uses of
ezetimibe
1) In compination with statin to treat hypercholesterolemia.
2) Alone in mild cases or when statin is contraindication
Patients with moderate to severe hepatic insufficiency
should not be treated with ezetimibe.
Bile Acid Sequestrants (Resins)
and colesevelamCholestyramine and colestipol
MOA :
These drugs bind to bile acid (cholesterol metabolite) and bile salts in
small intestine form resins bile acid complex which is
insoluble complex excreted in feces preventing the bile acid
reabsorption and returning to liver bile acid concentration
increase conversion of cholesterol to bile acid by
hepatocyteintracellular cholesterol uptake of
LDL LDL level in plasma .
Side effect :
Minimal systemic effect because it dose not absorbed from GIT .
in high doses and elderly ::Local effect
-Bulky unappetizing and inconvenient .
- GIT : abdominal fullness , diarrhea , constipation , nausea , bloating in
colesevelam is less .
- decrease absorption of fat soluble vit. (ADEK) but not colesevelam .
- Hypernatremia and Hyperchloremia
Therapeutic uses
Drug of choice in TTT of hyperlipidemia In children &
pregnant women
Hypercholestrolemia; Type IIA, and IIB Alone or + Statins
or Niacin .
4. FIBRATES:
Gemfibrozil, Clofibrate,, Bezafibrate,and Fenofibrate, ciprofibrate
MOA :
• -peroxisome proliferator activated receptor (PPAR)
which is nuclear receptor that regulate lipid metabolism.
• -activation of this receptor  bind to peroxisome
proliferator response elements fibrates-mediated gene
expression increase expression of lipoprotein lipase
• decrease triacylglycerol concentration.
also increase HDL level by increase expression of apo AI
and apo AII.
:Adverse effect of fibrates
1) Muscles: rare Myalgia & Myositis (▲Kidney,Liver) ▲if
+Statins (Simvastatin+Gemfibrozil) less with fenofibrate
2) GIT: (the most common) 5% Dyspepsia, abdominal pain,
nausea, diarrhea, (▲Liver enzymes 3%
3) Skin 2%: Rash, urticaria, hair loss
4) Blood: ▼WBCS, anemia, ▼ K► Arrhythmias
5) Others; Headache, fatigue, impotence.
Therapeutic uses :
2nd line of TTT hypertriacylglycerolemuas after
statin .
Fenofibrate and gemfibrozil are particularly
useful in treating Type III hyperlipidemia
(dysbetalipoproteinemia)
- Patients with hypertriacylglycerolemia (Type
IV [elevated VLDL] or Type V [elevated VLDL
plus chylomicron] disease) who do not respond
to diet or other drugs
5. Nicotinic Acid (NIACIN), Acipimox
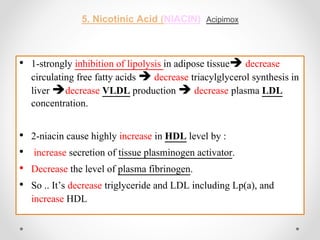
• 1-strongly inhibition of lipolysis in adipose tissue decrease
circulating free fatty acids  decrease triacylglycerol synthesis in
liver decrease VLDL production  decrease plasma LDL
concentration.
• 2-niacin cause highly increase in HDL level by :
• increase secretion of tissue plasminogen activator.
• Decrease the level of plasma fibrinogen.
• So .. It’s decrease triglyceride and LDL including Lp(a), and
increase HDL
Adverse Effects:
1. CVS: flushing arrhythmias. Postural hypotnsion
2. Skin: pruritis, rash, dry skin, ↑pigmentation, acanthosis
nigricans
3. GI: nausea, vomiting, diarrhea, flatulence, dyspepsia, activation
of peptic ulcer
4. Liver; Hepatotoxicity
5. Endocrine: Insulin resistance and hyperglycemia. Not
acipimox
6. ▲Uric acid: Hyperuricemia 20% (gout)
7. CNS: headache, dizziness. Blurring vision (Macular edema).
Therapeutic uses
•Niacin lowers plasma levels of both cholesterol
and triacylglycerol. Therefore, it is particularly useful in the treatment
of familial hyperlipidemia
1. Not widely used due to ADR
2. Useful in all forms of dyslipidemia (# type1)
3. In hypertriglyceridemia (III, IV, V) with or without levated
LDL.
4. Mostly used to lower VLDL & raise HDL
5. Adjunct to; statins, fibrates; (Niacin + Statins)►
myopathy
6. Prevention of pancreatitis
Other drugs used to lowering lipid
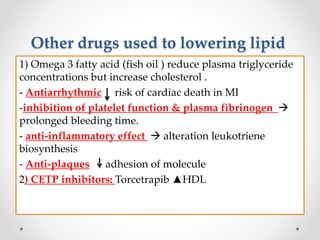
1) Omega 3 fatty acid (fish oil ) reduce plasma triglyceride
concentrations but increase cholesterol .
- Antiarrhythmic risk of cardiac death in MI
-inhibition of platelet function & plasma fibrinogen 
prolonged bleeding time.
- anti-inflammatory effect  alteration leukotriene
biosynthesis
- Anti-plaques adhesion of molecule
2) CETP inhibitors: Torcetrapib ▲HDL
non-pharmacological measures for treatment
of dyslipidemia
Our goal is increase HDL and decrease LDL
1 ) supplement healthy habit .
2) Moderate alcohol consumption raise HDL.
3) Regular exercise also increase circulating HDL .
4) Antioxidants (e.g vit. C and vit E ) .
5) Oestrogen (has antioxidant property) in women protect them from
atherosclerosis .
6) Fish oil : supply omega 3 FA that decrease LDL .
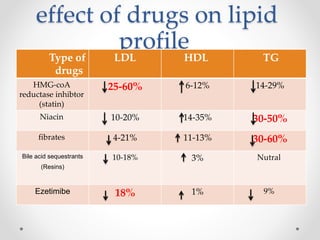
effect of drugs on lipid
profile
TGHDLLDLType of
drugs
14-29%6-12%25-60%HMG-coA
reductase inhibtor
(statin)
30-50%14-35%10-20%Niacin
30-60%11-13%4-21%fibrates
Nutral3%10-18%Bile acid sequestrants
(Resins)
9%1%18%Ezetimibe
preventive measures of
dyslipidemia
Primary prevention (Risk factors)
1- Diet control ;
↓protein intake , CHO, fat, salt .
Total cholesterol should be < 200 .
Antioxidants as vit.E , C , nuts,cereals, fresh fruit & vegetables .
Fish oil : supply omega 3 FA that decrease LDL .
2- Regular check body weight , BP .
3- quit smoking and alcohol .
4- Physical activity .
5- Control oral contraceptive .
6) TTT of hypertension and , to lesser extent , DM
7) Reduce the incidence of symptomatic atheromatous disease .
8) Reduce atrial thrombosis by antithrombotic drugs .
Secondary prevention (Early stage)
1- Screening :
A- All adult > 20 y (Fasting lipid profile)
B- High risk group (Fasting lipid profile)
2-↓complications ..
Tertiary prevention (Late stage)
↓impairments .
Rehabilitation ..
My references :
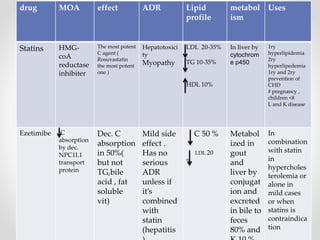
Usesmetabol
ism
Lipid
profile
ADReffectMOAdrug
1ry
hyperlipidemia
2ry
hyperlipedemia
1ry and 2ry
prevention of
CHD
# pregnancy ,
children <8
L and K disease
In liver by
cytochrom
e p450
LDL 20-35%
TG 10-35%
HDL 10%
Hepatotoxici
ty
Myopathy
The most potent
C agent (
Rosuvastatin
the most potent
one )
HMG-
coA
reductase
inhibiter
Statins
In
combination
with statin
in
hypercholes
terolemia or
alone in
mild cases
or when
statins is
contraindica
tion
Metabol
ized in
gout
and
liver by
conjugat
ion and
excreted
in bile to
feces
80% and
C 50 %
LDL 20
%
Mild side
effect .
Has no
serious
ADR
unless if
it’s
combined
with
statin
(hepatitis
Dec. C
absorption
in 50%(
but not
TG,bile
acid , fat
soluble
vit)
C
absorption
by dec.
NPC1L1
transport
protein
Ezetimibe
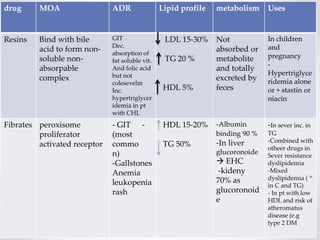
UsesmetabolismLipid profileADRMOAdrug
In children
and
pregnancy
-
Hypertriglyce
ridemia alone
or + stastin or
niacin
Not
absorbed or
metabolite
and totally
excreted by
feces
LDL 15-30%
TG 20 %
HDL 5%
GIT
Dec.
absorption of
fat soluble vit.
And folic acid
but not
colesevelm
Inc.
hypertriglycer
idemia in pt
with CHL
Bind with bile
acid to form non-
soluble non-
absorpable
complex
Resins
-In sever inc. in
TG
-Combined with
otheer drugs in
Sever resistance
dyslipidemia
-Mixed
dyslipidemia ( ^
in C and TG)
- In pt with low
HDL and risk of
atheromatus
disease (e.g
type 2 DM
-Albumin
binding 90 %
-In liver
glucoronoide
 EHC
-kideny
70% as
glucoronoid
e
HDL 15-20%
TG 50%
-- GIT
(most
commo
n)
-Gallstones
Anemia
leukopenia
rash
peroxisome
proliferator
activated receptor
Fibrates
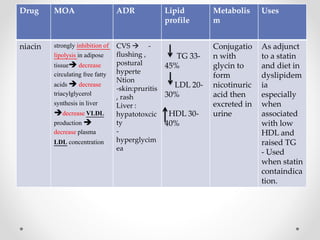
UsesMetabolis
m
Lipid
profile
ADRMOADrug
As adjunct
to a statin
and diet in
dyslipidem
ia
especially
when
associated
with low
HDL and
raised TG
- Used
when statin
containdica
tion.
Conjugatio
n with
glycin to
form
nicotinuric
acid then
excreted in
urine
TG 33-
45%
LDL 20-
30%
HDL 30-
40%
-CVS 
flushing ,
postural
hyperte
Ntion
-skin:pruritis
, rash
Liver :
hypatotoxcic
ty
-
hyperglycim
ea
strongly inhibition of
lipolysis in adipose
tissue decrease
circulating free fatty
acids  decrease
triacylglycerol
synthesis in liver
decrease VLDL
production 
decrease plasma
LDL concentration
niacin
Thank you !
Questions ^,^
The most effective TG lowering drug is fibrates
The drug causing hepatitis is statin
Best drug to increase HDL is niacin
TTT od dyslipidemia in pregnant women resine
Drug can be used in primary previntion of dyslipidemia statin .
Ezetimibe is contraindication in hepatic insufficiency .
The least drug cause abdominal side effect from bile acid
sequestrant is colesevelam
The most common side effect of fibrate is GIT problem