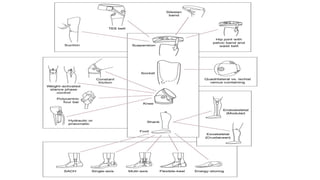
TRANSFEMORAL GAIT DEVIATIONS with causes and managment
The document discusses typical gait deviations observed in transfemoral amputees and assesses their causes, including prosthetic and amputee-related factors. It outlines various management strategies like socket adjustments, gait training, and strength building. Additionally, the document provides specific assessments and views for analyzing issues during different phases of the gait cycle.
Objectives:
1) Review typicalgait deviations in transfemoral amputees (e.g., hip hiking, circumduction).
2) Discuss assessment methods, including gait analysis and clinical evaluation.
3) Explore strategies for managing these deviations, including prosthetic modifications,
therapeutic interventions, and gait training.
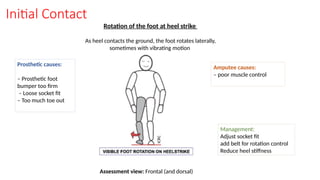
Initial Contact
Rotation ofthe foot at heel strike
As heel contacts the ground, the foot rotates laterally,
sometimes with vibrating motion
Prosthetic causes:
– Prosthetic foot
bumper too firm
– Loose socket fit
– Too much toe out
Amputee causes:
– poor muscle control
Management:
Adjust socket fit
add belt for rotation control
Reduce heel stiffness
Assessment view: Frontal (and dorsal)
6.
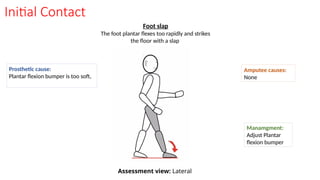
Initial Contact
Foot slap
Thefoot plantar flexes too rapidly and strikes
the floor with a slap
Prosthetic cause:
Plantar flexion bumper is too soft,
Amputee causes:
None
Manamgment:
Adjust Plantar
flexion bumper
Assessment view: Lateral
Loading Response
Knee instability(Knee buckling )
Prosthetic knee flexion is not stable or controlled and may look “jerky”
Prosthetic causes:
- Knee set too far anterior
– The socket is placed too far anteriorly
– Heel support is too hard that “unlocks”
the knee at heel strike
– Hip flexion contracture not
accommodated in the socket.
Amputee causes:
– Weak hip extensors.
-Severe hip flexion contracture may
cause instability
Management:
Realign limb
reduce heel stiffness
Gait training
hip extensors strengthening
Assessment view: Lateral
9.
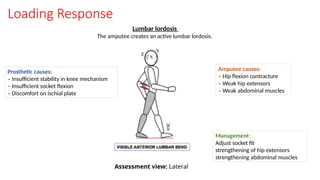
Loading Response
Lumbar lordosis
Theamputee creates an active lumbar lordosis.
Prosthetic causes:
– Insufficient stability in knee mechanism
– Insufficient socket flexion
– Discomfort on ischial plate
Amputee causes:
– Hip flexion contracture
– Weak hip extensors
– Weak abdominal muscles
Management:
Adjust socket fit
strengthening of hip extensors
strengthening abdominal muscles
Assessment view: Lateral
10.
Midstance
Lateral trunk bending(towards the prosthetic side)
Amputee leans towards the prosthesis
Prosthetic causes :
– Prosthesis too short
– High medial wall socket
– Excessive abduction of socket
– Insufficient femoral support of
lateral socket wall (too wide open)
Amputee causes:
– hip abduction contracture
– Very short residual limb
– Sensitive or painful stump
– Weak hip abductor muscles
(Trendelenberg gait)
– Bad gait habit
Manamgment:
Realign prosthesis
Adjust height prosthesis
Adjust socket fit
Gait training and strengthening
Assessment view: Frontal and dorsal
11.
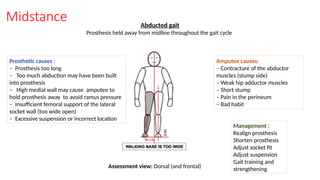
Midstance Abducted gait
Prosthesisheld away from midline throughout the gait cycle
Prosthetic causes :
– Prosthesis too long
– Too much abduction may have been built
into prosthesis
– High medial wall may cause amputee to
hold prosthesis away to avoid ramus pressure
– Insufficient femoral support of the lateral
socket wall (too wide open)
– Excessive suspension or incorrect location
Amputee causes:
– Contracture of the abductor
muscles (stump side)
– Weak hip adductor muscles
– Short stump
– Pain in the perineum
– Bad habit
Management :
Realign prosthesis
Shorten prosthesis
Adjust socket fit
Adjust suspension
Gait training and
strengthening
Assessment view: Dorsal (and frontal)
Terminal Stance
Drop off
Thereis a downwards movement of the body
as weight is transferred forwards over the prosthetic foot (early knee flexion).
Prosthetic causes:
– Too soft dorsiflexion resistance in
prosthetic foot
– Socket set too far forward to the foot
– Too much dorsiflexion
– Foot too small
Amputee causes:
none
Management:
Adjust socket
placement
Adjust foot unit
Assessment view: Lateral
Initial swing
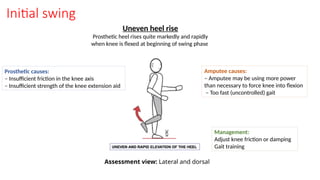
Uneven heelrise
Prosthetic heel rises quite markedly and rapidly
when knee is flexed at beginning of swing phase
Prosthetic causes:
– Insufficient friction in the knee axis
– Insufficient strength of the knee extension aid
Amputee causes:
– Amputee may be using more power
than necessary to force knee into flexion
– Too fast (uncontrolled) gait
Management:
Adjust knee friction or damping
Gait training
Assessment view: Lateral and dorsal
16.
Initial swing
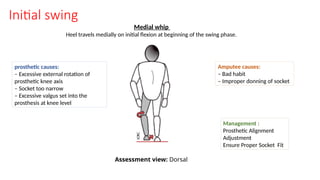
Medial whip
Heeltravels medially on initial flexion at beginning of the swing phase.
prosthetic causes:
– Excessive external rotation of
prosthetic knee axis
– Socket too narrow
– Excessive valgus set into the
prosthesis at knee level
Amputee causes:
– Bad habit
– Improper donning of socket
Management :
Prosthetic Alignment
Adjustment
Ensure Proper Socket Fit
Assessment view: Dorsal
Initial swing
Lateral whip
Heeltravels laterally on initial flexion at beginning of the swing phase.
prosthetic causes:
– Excessive internal rotation
of prosthetic knee axis
– Socket too narrow
– Excessive varus set into
the prosthesis at knee level
Amputee causes:
– Improper donning of socket
– Bad habit
Management :
Prosthetic Alignment
Adjustment
Ensure Proper Socket Fit
Assessment view: Dorsal
Initial and Swingphase
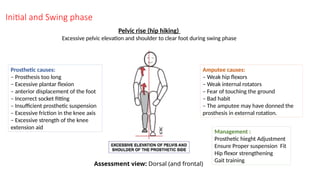
Pelvic rise (hip hiking)
Excessive pelvic elevation and shoulder to clear foot during swing phase
Prosthetic causes:
– Prosthesis too long
– Excessive plantar flexion
– anterior displacement of the foot
– Incorrect socket fitting
– Insufficient prosthetic suspension
– Excessive friction in the knee axis
– Excessive strength of the knee
extension aid
Amputee causes:
– Weak hip flexors
– Weak internal rotators
– Fear of touching the ground
– Bad habit
– The amputee may have donned the
prosthesis in external rotation.
Management :
Prosthetic hieght Adjustment
Ensure Proper suspension Fit
Hip flexor strengthening
Gait training
Assessment view: Dorsal (and frontal)
21.
Swing phase
Vaulting
The amputeerises up on the toe of the sound leg to swing the
prosthesis through from toe off to heel strike.
Prosthetic causes:
– Prosthesis too long
– Excessive plantar flexion
– Prosthesis too stable
– Socket suspension may be inadequate
Amputee causes:
– Fear of stubbing toe
– Residual limb discomfort
– fairly frequent habit pattern
Management :
Prosthetic highet Adjustment
Ensure Proper suspension Fit
examine stump
Gait training
Assessment view: Lateral and dorsal
22.
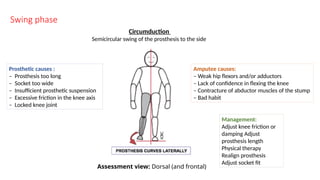
Swing phase
Circumduction
Semicircular swingof the prosthesis to the side
Prosthetic causes :
– Prosthesis too long
– Socket too wide
– Insufficient prosthetic suspension
– Excessive friction in the knee axis
– Locked knee joint
Amputee causes:
– Weak hip flexors and/or adductors
– Lack of confidence in flexing the knee
– Contracture of abductor muscles of the stump
– Bad habit
Management:
Adjust knee friction or
damping Adjust
prosthesis length
Physical therapy
Realign prosthesis
Adjust socket fit
Assessment view: Dorsal (and frontal)
23.
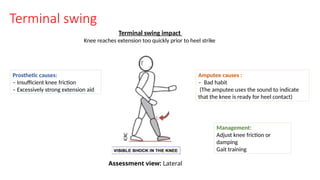
Terminal swing
Terminal swingimpact
Knee reaches extension too quickly prior to heel strike
Prosthetic causes:
– Insufficient knee friction
– Excessively strong extension aid
Amputee causes :
– Bad habit
(The amputee uses the sound to indicate
that the knee is ready for heel contact)
Management:
Adjust knee friction or
damping
Gait training
Assessment view: Lateral
Various gait cycles
Unevenstep length
The length of the step taken with the prosthesis differs from that of the sound leg
Prosthetic causes:
– Insufficient flexion of the socket
– Insufficient prosthetic
suspension (pistoning)
– Insufficient friction at the
prosthetic knee
amputee causes:
– Short, weak or painful stump
– Hip flexion contracture
– The amputee feels insecure
with the knee mechanism.
Management:
Adjust socket fit
Physical therapy
Realign prosthesis
Assessment view: Lateral



 Most read

 Most read
 Most read