What is PulseOximetry ?
Pulse oximetry is a non-invasive means of measuring oxygen
saturation of arterial blood. Oxygen saturation is defined as the
amount of hemoglobin that is bound to O2 divided by the amount of
total hemoglobin that is available to bind with O2.
Mandatory for any anesthetic even cases with moderate sedation.
Pulse oximetry, sometimes called the fifth vital sign, is a non invasive
method of measuring haemoglobin saturation (Sp02) by using a light
signal transmitted through a tissue
A low Sp02 can provide a warning sign of hypoxemia before other
signs such as cyanosis or a change in heart rate are observed.
TECHNIQUES:
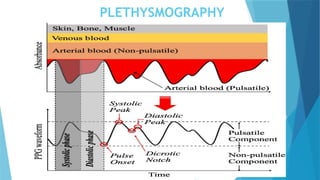
Combines theprinciples of oximetry and plethysmography to measure saturation.
Sensor containing light sources (2/3 light emitting diodes)
A light detector (photodiode) placed across the finger, toe, earlobe or any perfused tissue that
can be transilluminated.
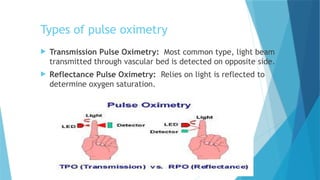
When light source and detector are placed on the opposite side, transmittance oximetry is
used.
When light source and detector are placed on the same side of patient (eg: forehead)
backscatter of light is recorded by the detector.
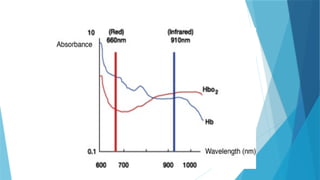
Oximetry depends on the observation that oxygenated and reduced hemoglobin differ in their
absorption of red and infrared light (lambert-beer law).
5.
OPERATING PRINCIPLES
Thepulse oximeter estimates Sp02 from the differential absorption of red and infrared light in
tissue.
Oxyhemoglobin absorbs more infrared light (940nm)
Deoxyhemoglobin absorbs more red light (660nm)– thus appears blue/cyanotic to the naked
eye.
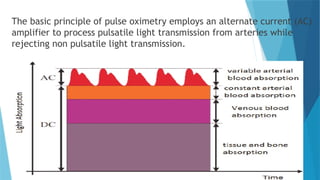
Thus the change in the light absorption during arterial pulsations is the basis of oximetric
determinations.
The ratio of red and infrared wavelengths is analyzed by microprocessor to provide spo2
Greater ratio--- lower is arterial hemoglobin saturation.
Pulse oximetry computes ratio between these two signals and relates this ratio to arterial oxygen
saturation using an empirical algorithm.
Whereas the arterial pulsations are identified by plethysmography, allowing corrections for light
absorption by venous blood and tissue.
7.
The basic principleof pulse oximetry employs an alternate current (AC)
amplifier to process pulsatile light transmission from arteries while
rejecting non pulsatile light transmission.
8.
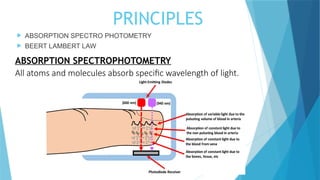
PRINCIPLES
ABSORPTION SPECTROPHOTOMETRY
BEERT LAMBERT LAW
All atoms and molecules absorb specific wavelength of light.
ABSORPTION SPECTROPHOTOMETRY
9.
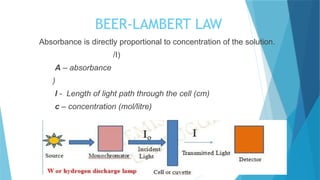
BEER-LAMBERT LAW
Absorbance isdirectly proportional to concentration of the solution.
/I)
A – absorbance
)
l - Length of light path through the cell (cm)
c – concentration (mol/litre)
Types of pulseoximetry
Transmission Pulse Oximetry: Most common type, light beam
transmitted through vascular bed is detected on opposite side.
Reflectance Pulse Oximetry: Relies on light is reflected to
determine oxygen saturation.
12.
Sites of SpO2probe application
ADULTS and CHILDREN INFANTS and NEONATES
• Finger
• Thumb
• Toe
• Pinna
• Lobe of Ear
• Palm
• Sole
13.
Applications of pulseoximetry
1. Monitoring oxygenation for adult and children in critical
areas
A. Anaesthesia
I. In operation room or general anaesthesia
II. Monitored anaesthesia care or during conscious sedation
B. PACU
C. Intensive care units
D. Emergency Department
14.
Applications of pulseoximetry
2. Monitoring oxygenation in neonatal areas
A. Intensive care
B. Newborn nursery
C. Delivery suites
3. Transport
A. Internal (within the hospital)
B. External
I. Ambulance
II. Air transport
15.
Applications of pulseoximetry
4. Diagnostic lab
5. Home care patients
6. Controlling oxygen administration
7. Avoiding hyperoxemia
8. Monitoring peripheral circulation
9. Determining systolic blood pressure
10. Locating arteries
11. Monitoring vascular volume and sympathetic tone
12. Intrapartum fetal monitoring
16.
A sudden decreasein spo2
1. Disconnection.
2. Fat / Pulmonary embolism.
3. O2 delivery failure.
4. Hypoxia gas mixture.
5. ETT obstruction.
6. Pulmonary edema.
7. Anaphylaxsis / Malignant hyperthermia.
17.
Monitoring oxygenation
1. Reductionin number of hypoxic events (especially during
induction and emergence)
2. To detect inadvertent Bronchial intubation by fall in Spo2,
not a reliable method especially if supplemental oxygen is
used.
3. Regional and monitored anaesthesia care
4. Post anaesthesia care unit
5. Transport
18.
Monitoring peripheral oxygenation
1.Detects arm position that compromises circulation.
2. Detects decreased perfusion in toe in lithotomy position.
3. Brachial artery compression during shoulder arthroscopy.
4. Compromised peripheral circulation distal to site of
fracture.
5. To evaluate effects of sympathetic block as indicated by
SPO2 due to vasodilation.
19.
ADVANTAGES OF PULSEOXIMETRY
Simple to use, user friendly.
Accuracy.
Non - invasive.
Require no warm up time.
Independence from gases and vapours.
Fast response time.
Continuous measurements.
20.
Tone modulator- variable pitch of tone.
Convenient.
Light weight.
Fast start time within a few beats after
application of probe.
Economical.
Separate respiratory and circulatory variables.
21.
Limitations and disadvantages
Poor function with poor perfusion.
Difficulty in detecting high oxygen partial
pressures.
Delayed hypoxic event detection.
Erratic performance with dysrhythmias.
Motion Artifact
22.
INACCURACY is seenin
Different Haemoglobin:
Methheamoglobin
1.<1% of the total Haemoglobin.
2.Oxidation product of Hb that forms a reversible complex with oxygen
and impairs the unloading of oxygen to tissues.
3.Congenital or acquired .
4.Drugs causing Meth Haemoglobinemia include nitrobenzene,
benzocaine, prilocaine, and dapsone.
5.Absorbs light equally at red and infrared wavelengths that are used
by most pulse oximeters.
23.
Carboxyhemoglobin:
1. Anincrease in Hb CO may occur during laser surgery in the airway, but the
levels are not high enough to keep pulse oximeter from reliably estimating
saturation.
2. Pulse oximeters that differentiate between oxyhemoglobin and
carboxyhemoglobin and that can measure carboxyhemoglobin are now
available.
Fetal hemoglobin: Hb F does not appear or affect the accuracy to a clinically
important degree, although very high levels may cause it to read slightly low.
Hemoglobin S
Inaccurate readings.
Sulfheamoglobin
May be caused by drugs such as metaclopramide, dapsone and sulfonamides–
artificially lower oxygen saturation.
26.
Recent Advances
ErrorCorrection
Two most common errors with pulse oximetry are motion artifacts and signal
loss secondary to hypoperfusion. Recently quite a few manufacturers have
incorporated new technologies of signal analysis reducing these inaccuracies.
Multi-wavelength Pulse Oximeters
Eight-wavelength pulse oximeter capable of measuring several species of Hb
has been developed. It claims capability to accurately measure MetHb and COHb.
Reflectance Pulse Oximetry
Reflectance oximetry has been used to monitor fetal oxygen saturation with
scalp probes and has shown to decrease surgical intervention in the face of non-
reassuring fetal status.58 Esophageal probes have been designed and have shown
success in measuring SpO2 during cardiothoracic surgery when finger probes have
failed.




 Most read
 Most read